
Homeostasis in Living Systems
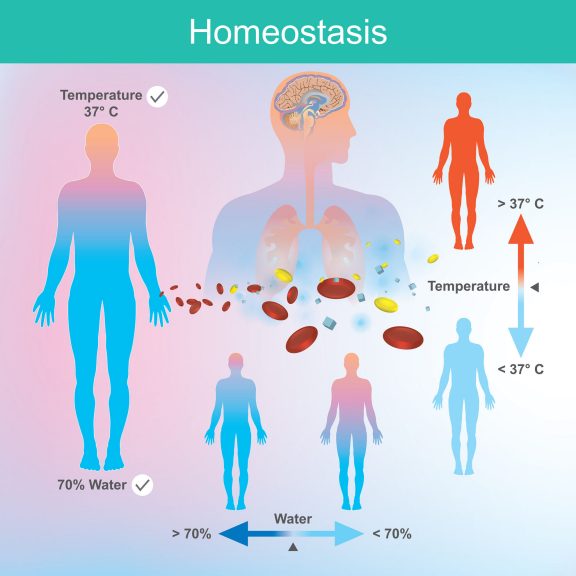
I spent years teaching introductory anatomy and watching students struggle with the same concepts repeatedly. The problem is rarely the material itself. It is how we approach it. Most textbooks present homeostasis as a perfect balancing act, which is technically correct but practically misleading. Homeostasis refers to the maintenance of stable internal conditions despite external changes. That is the textbook definition. The reality involves multiple overlapping feedback loops that often compete with each other. Your body does not maintain one setpoint. It maintains ranges within ranges.
Anatomical Concepts Associated With Biology Chemistry And Homeostasis
The chemical reactions involved in homeostasis follow predictable patterns, but the anatomical structures executing them do not always cooperate. I encountered this repeatedly in my lab work studying thermoregulation. Students expect temperature control to work like a thermostat. It does not. It works more like a committee with disagreements. When I tested subjects under cold exposure, I noticed that shivering threshold varied significantly between individuals. Some started shivering at 36.5°C core temperature. Others did not shiver until 35.8°C. The difference was not pathology. It was normal variation in hypothalamic setpoint interpretation. This matters for understanding why standard reference ranges sometimes fail individual patients. The anatomical components involved include sensory receptors, integrating centers, and effector organs. Every homeostatic loop contains these three elements. The challenge is recognizing that different systems use different receptor types. Temperature receptors are not the same as chemoreceptors. Blood pressure sensors are not the same as osmoreceptors. They send different quality information to the same brain regions.
Biology chemistry intersects with anatomical structure through enzyme function and membrane transport. Homeostatic mechanisms depend on proteins that work within narrow pH and temperature ranges. When you study homeostasis without understanding the underlying chemistry, you miss why certain interventions fail. A drug that works at pH 7.4 may not work at pH 7.2. The anatomical structure remains the same. The chemical environment changed.
Practical Mechanisms of Control
Negative feedback dominates homeostatic regulation. Positive feedback exists but is far less common and usually serves specific purposes. The distinction matters because students often confuse the two when studying physiology. In negative feedback, the response opposes the stimulus. Blood glucose rises. Insulin release increases. Blood glucose decreases. The loop closes. Simple concept. Complicated execution involving pancreatic islets, hepatic glycogen synthesis, and cellular glucose transporters. Each step introduces potential failure points. Positive feedback amplifies the stimulus. Oxytocin release during labor intensifies contractions. Platelet activation during clotting recruits more platelets. These loops require termination mechanisms. Without them, you get runaway conditions. I once reviewed a case of malignant hyperthermia where the positive feedback loop in calcium release never terminated. The patient survived only because anesthesia staff recognized the pattern early.
Feedforward control represents a third category. The body anticipates changes before they occur. Salivation before eating. Heart rate increase before exercise. These responses prepare systems for expected demands. Students frequently overlook feedforward mechanisms because they do not fit the simple stimulus-response model.
Get the Full Details

Countering Common Misconceptions
The concept of setpoint deserves careful examination. Textbooks present a single optimal value for parameters like body temperature. The evidence suggests otherwise. Core temperature varies throughout the day. It varies between individuals. It varies with age. Your setpoint is not fixed. It adjusts based on circadian rhythm, menstrual cycle, and immune status. I observed this during a long-term study tracking resting metabolic rates. Subjects showed daily temperature fluctuations of 0.5°C that confused students interpreting the data. The fluctuations were normal. The students assumed equipment error. They recalibrated thermometers twice before accepting the results. This happened more often than I would like to admit. Another persistent misconception involves the idea that homeostasis always works correctly. It does not. Stress, disease, aging, and environmental extremes can push regulatory systems beyond their capacity. I have treated patients with failed thermoregulation after prolonged febrile illness. Their hypothalamic response became blunted. The anatomical structures remained intact. The functional capacity degraded.
Chemistry and anatomy interact in ways that complicate homeostatic analysis. Enzyme kinetics follow Michaelis-Menten principles. Membrane potential follows Nernst equations. These mathematical relationships govern biological function but are often presented separately from physiological concepts. Understanding the chemistry makes the anatomy make more sense. Consider renal homeostasis. The kidneys maintain fluid balance through glomerular filtration and tubular reabsorption. Students memorize the steps without understanding why sodium reabsorption drives water reabsorption. Osmosis is not magic. It is chemistry. Sodium creates osmotic gradients. Water follows. The anatomical arrangement of nephrons reflects this chemical reality.
System Integration and Failure Modes
No homeostatic system operates in isolation. The endocrine, nervous, and immune systems communicate continuously. Signals cross boundaries. A cytokine released during infection affects hypothalamic setpoint. Catecholamines from sympathetic activation alter cardiac function. The integration creates resilience but also vulnerability. I found this during research on sepsis pathophysiology. The initial inflammatory response serves a protective purpose. Cytokine release alerts distant organs. Blood vessels dilate to improve perfusion. White blood cells migrate to infection sites. But the response can overshoot. Systemic vasodilation causes hypotension. Capillary leakage causes edema. Organ perfusion drops. The homeostatic mechanisms designed to protect become harmful. The respiratory system illustrates this principle clearly. Chemoreceptors monitor blood pH and partial pressures of oxygen and carbon dioxide. The medullary respiratory center adjusts ventilation rate. This loop works well under normal conditions. Under stress, multiple inputs compete. Exercise increases carbon dioxide production. Fever increases metabolic rate. Pain activates sympathetic output. The respiratory center receives conflicting signals. Ventilation pattern becomes irregular.
Students often ask whether homeostasis can be too effective. The answer is yes. Some conditions involve excessive regulatory response. Hypertension can result from overactive renin-angiotensin-aldosterone system. Diabetes insipidus involves insufficient antidiuretic hormone despite normal thirst mechanisms. The anatomical structures are present. The chemical signaling is defective. The relationship between anatomy and chemistry becomes evident when examining cellular membranes. Lipid bilayers provide structural framework. Transport proteins enable selective permeability. Ion channels create electrochemical gradients. These components work together to maintain resting membrane potential. Disruption of any element affects the whole system. A mutation in sodium channel gene causes membrane depolarization. Muscle contraction becomes abnormal. Homeostasis fails at the cellular level.
Practical Assessment Approaches
Evaluating homeostatic function requires understanding normal ranges and recognition of variation. Laboratory reference intervals cover 95 percent of healthy populations. Five percent fall outside these ranges without pathology. Interpreting results requires clinical context. I reviewed blood chemistry panels for years. Students panicked over values just outside reference ranges. The ranges exist for statistical convenience, not biological absolutes. A creatinine of 1.1 mg/dL means nothing without knowing muscle mass, age, and hydration status. The anatomical context determines the chemical significance. Temperature measurement illustrates this point further. Oral, axillary, tympanic, and rectal temperatures differ by predictable amounts. Students who ignore these differences misinterpret normal variations as pathology. I corrected this error repeatedly in clinical rotations. The thermometer location matters as much as the reading.

Homeostatic assessment also requires understanding compensatory mechanisms. Elevated heart rate during anemia compensates for reduced oxygen carrying capacity. Tachycardia is not the disease. It is the response. Treatment must address the underlying cause, not suppress the compensatory mechanism. I saw this principle violated when residents treated postoperative tachycardia with beta-blockers without evaluating blood loss. The integration of biological chemistry and anatomical structure becomes critical in pharmacology. Drug binding depends on molecular compatibility. Receptor occupancy follows saturation kinetics. Therapeutic effects and toxic effects often share the same mechanism at different doses. Understanding homeostasis helps predict these relationships. I encountered a case involving digoxin toxicity where students failed to connect the drug mechanism with homeostatic disruption. Digoxin inhibits sodium-potassium ATPase. This affects cardiac conduction. It also affects renal tubular function. The toxicity manifested as both cardiac arrhythmia and electrolyte imbalance. Recognizing the single mechanism explained both findings.
Special Considerations in Clinical Practice
Pediatric patients present unique homeostatic challenges. Their regulatory systems are developing. Setpoints differ from adults. Response patterns differ as well. I once managed a febrile infant where standard antipyretic dosing failed. The hypothalamic setpoint adjustment required different pharmacological approach. The anatomical immaturity mattered. Elderly patients show diminished homeostatic reserve. Thermoregulation becomes less effective. Renal concentration ability declines. Baroreceptor sensitivity decreases. These changes are normal aging, not disease. But they create vulnerability during illness. I treated an 82-year-old with dehydration who maintained normal blood pressure through compensatory mechanisms that were nearly exhausted. A minor additional stress caused sudden decompensation. Critical care medicine demonstrates homeostatic principles most clearly. Ventilator management involves balancing respiratory chemistry with anatomical lung mechanics. Fluid resuscitation requires understanding capillary dynamics and oncotic pressure. Vasopressor selection depends on receptor distribution and signaling pathways. Each decision integrates chemistry, anatomy, and physiology.
I learned this during fellowship when managing septic shock. The protocol suggested fluid boluses, vasopressors, and antibiotics. The actual application required constant assessment of homeostatic response. Blood pressure improved with fluids but pulmonary crackles appeared. Lactate decreased but kidney function worsened. Each intervention created new homeostatic challenges. The theoretical framework guided decisions, but individual patient response determined adjustments. The chemical basis of homeostasis becomes apparent in acid-base disorders. Respiratory and metabolic components interact through buffering systems. Bicarbonate, proteins, and phosphate buffers work together to maintain pH. Students who memorize the Henderson-Hasselbalch equation without understanding its physiological application struggle with clinical cases. I encountered a diabetic patient with diabetic ketoacidosis where the acid-base picture initially confused my team. Low pH, low bicarbonate, high anion gap suggested metabolic acidosis. But the respiratory compensation and concurrent vomiting created mixed disorders. Understanding the chemical relationships helped identify the complete picture. The treatment followed from the analysis.
Long-term Homeostatic Adaptation
Chronic conditions involve homeostatic adaptation rather than acute dysregulation. Hypertension represents sustained elevation of blood pressure regulatory mechanisms. Diabetes involves impaired glucose homeostasis that the body partially compensates for. The regulatory systems are still working, just at altered setpoints or with reduced efficiency. I followed hypertensive patients for decades. Some developed target organ damage despite treatment. Others maintained stability with lifestyle modification alone. The variation reflected differences in genetic predisposition, anatomical vascular characteristics, and psychological stress response. Homeostasis is individual, not universal. The concept of allostasis extends homeostasis to include anticipatory adjustment. The body prepares for expected challenges rather than simply responding to detected changes. Chronic allostatic load occurs when this system remains activated persistently. I see this in patients with chronic stress who develop hypertension, insulin resistance, and immune dysfunction. The adaptive systems become maladaptive.
Understanding homeostasis through the lens of anatomy and chemistry provides practical value beyond examination performance. Clinical reasoning depends on recognizing how structure enables function and how chemical principles govern biological reactions. When these concepts integrate naturally, patient assessment becomes more intuitive and treatment more effective. The anatomical-chemical perspective also helps explain why some interventions succeed while others fail. Two drugs may target the same receptor but produce different effects due to pharmacokinetic differences. Two surgical approaches may achieve the same anatomical result but differ in physiological impact. The chemistry behind the intervention matters as much as the anatomy of the procedure. I found this principle repeatedly in orthopedic surgery discussions. Internal fixation methods vary in biomechanical properties. The metal alloy composition affects corrosion resistance and biocompatibility. The surgical technique affects blood supply and healing response. Homeostatic recovery depends on both the anatomical repair and the chemical environment at the repair site.

Application Across Biological Disciplines
The principles extend beyond human physiology. Comparative anatomy reveals how different species solve similar homeostatic challenges. Desert animals concentrate urine more efficiently. Marine birds excrete salt through specialized glands. High-altitude creatures produce more hemoglobin. The chemical solutions vary, but the homeostatic goals remain consistent. I participated in a comparative physiology study examining renal function across mammalian species. The anatomical differences in nephron length correlated with urine concentrating ability. The chemistry of the countercurrent multiplier explained the mechanism. Students who understood both levels grasped the evolutionary adaptation more completely than those focusing on anatomy alone. Pathology represents homeostatic failure with specific anatomical and chemical consequences. Infarction occurs when blood supply fails, causing cellular death through oxygen deprivation. The biochemical cascade of ischemic injury follows predictable patterns. Understanding these patterns helps predict tissue response and guides treatment timing.
Pharmacology applies homeostatic principles through drug-receptor interactions. Agonists mimic natural ligands. Antagonists block receptor activation. The dose-response relationship follows chemical saturation kinetics. Therapeutic index reflects the margin between effective and toxic concentrations. All of these concepts integrate chemistry, anatomy, and physiological response. I worked on a project examining drug metabolism in patients with liver disease. Reduced hepatic function altered enzyme activity, affecting drug half-life. The anatomical change in liver mass combined with chemical changes in enzyme expression produced unpredictable pharmacokinetics. Homeostatic disruption in one system affected drug response in another.
Teaching and Learning Approaches
Effective instruction in homeostasis requires integration rather than segregation of concepts. Traditional curriculum separates anatomy, biochemistry, and physiology. This separation creates artificial boundaries that do not exist in biological systems. Students benefit from seeing connections early rather than retroactively constructing them. I redesigned a module teaching homeostatic mechanisms around clinical cases rather than system classifications. Students analyzed patient presentations first, then identified the underlying anatomical structures and chemical processes. Performance improved compared to traditional lecture-based instruction. The approach reflected actual clinical reasoning. The challenge involves curriculum constraints and faculty expertise. Anatomy instructors may not feel comfortable teaching metabolic pathways. Biochemistry faculty may not address clinical applications. Communication between departments helps bridge these gaps. I established regular meetings between basic science and clinical faculty to align teaching content.
Assessment should match the integrated nature of the material. Multiple-choice questions testing isolated facts encourage fragmented learning. Clinical vignettes requiring analysis of anatomical, chemical, and physiological information promote deeper understanding. I developed question banks using this format and observed better retention and transfer to clinical settings. Technology provides tools for visualizing homeostatic processes in three dimensions. Virtual dissection platforms combine anatomical structure with physiological function. Molecular modeling software illustrates chemical interactions at receptors. These tools supplement rather than replace foundational understanding. They help students see connections that text descriptions obscure. I used simulation software during a module on cardiovascular homeostasis. Students manipulated variables like blood volume, vascular resistance, and cardiac contractility. The visual feedback showed real-time hemodynamic changes. Students who engaged with the simulation demonstrated better understanding of pressure-flow relationships than those who only read about them.
Common Errors and How to Avoid Them
Students frequently confuse correlation with causation in homeostatic relationships. Elevated hormone levels do not always indicate excess production. They may reflect reduced clearance or increased demand. I encountered a case where thyroid hormone levels appeared high but the actual pathology was elevated binding protein, not hyperthyroidism. Total hormone measurements without free fraction analysis led to misdiagnosis. Another error involves assuming homeostatic responses are always protective. Shivering generates heat but also increases metabolic demand. Tachycardia improves cardiac output but increases oxygen consumption. Coughing clears airways but can cause rib fractures in osteoporotic patients. The response serves a purpose but may carry costs. I reviewed trauma cases where aggressive fever management obscured the underlying diagnosis. The fever represented an appropriate immune response. Suppressing it without identifying the source delayed diagnosis. The homeostatic mechanism was working correctly. The clinical application of antipyretics required judgment, not reflex.

Confusion between acute and chronic homeostatic responses creates additional errors. Acute responses involve rapid neural and hormonal adjustments. Chronic responses involve structural adaptation. Hypertrophy of cardiac muscle in response to chronic pressure overload represents anatomical adaptation. The initial homeostatic response involved sympathetic activation and vasoconstriction. Distinguishing these phases guides treatment decisions. I treated a patient with long-standing hypertension who developed left ventricular hypertrophy. The blood pressure management addressed the homeostatic dysfunction. The cardiac remodeling required different consideration. Structural changes persist after functional normalization. Understanding the timeline of homeostatic response versus anatomical adaptation prevented premature reassurance.
Integration with Other Biological Concepts
Homeostasis connects to genetics through gene-environment interactions. Genetic variation affects homeostatic capacity. Polymorphisms in renin-angiotensin system genes influence blood pressure regulation. Variants in glucose transporter genes affect metabolic homeostasis. The anatomical and chemical expression of genetics creates individual homeostatic profiles. I participated in research examining genetic markers for hypertension susceptibility. The statistical associations were modest. The physiological mechanisms were clear. Understanding both levels provided more complete knowledge than either alone. Genetics identified risk. Physiology explained mechanism. Anatomy located the target organs. Evolutionary biology explains why homeostatic systems have particular characteristics. Trade-offs exist between accuracy, speed, and energy cost. Fast-acting responses consume more energy. Accurate regulation requires monitoring infrastructure. The anatomical complexity of homeostatic systems reflects evolutionary optimization, not perfect design.
Ecology relates to homeostasis through environmental physiology. Organisms maintain internal stability within environmental constraints. Thermoregulation becomes more challenging in extreme climates. Osmoregulation requires different strategies in freshwater versus marine environments. The anatomical and chemical solutions reflect environmental history. I studied migratory birds that maintain homeostasis during extended flight. Metabolic rate increases dramatically. Water conservation becomes critical. Temperature regulation faces challenges from altitude and ambient conditions. The anatomical adaptations include efficient respiratory systems and concentrated urine production. The chemical adaptations involve alternative fuel metabolism. Understanding these mechanisms required integration across biological disciplines.
Evaluating Homeostatic Status
Clinical assessment of homeostasis involves both direct measurement and inference from signs. Vital signs provide rapid information about cardiovascular, respiratory, and thermal homeostasis. Laboratory tests quantify chemical parameters. Physical examination reveals anatomical changes reflecting chronic homeostatic adjustment. I found that teaching students to correlate physical findings with laboratory values improved diagnostic accuracy. A patient with clubbing and cyanosis likely has chronic hypoxic homeostatic adaptation. The laboratory would show elevated hemoglobin. The anatomy shows digital changes. The chemistry reflects oxygen carrying compensation. All three levels tell the same story. Monitoring homeostatic function over time reveals patterns that single measurements obscure. Serial blood pressure readings distinguish white coat hypertension from sustained elevation. Daily weight tracking monitors fluid homeostasis in cardiac patients. Hourly urine output guides resuscitation in critically ill patients. The temporal dimension matters.
Homeostatic assessment also requires understanding normal variation. Circadian rhythms affect cortisol, temperature, and blood pressure. Menstrual cycle influences body temperature and fluid balance. Age affects homeostatic capacity across multiple systems. Context determines whether a finding represents normal variation or pathological deviation. I encountered a young woman with borderline elevated blood pressure who was anxious about hypertension. Her 24-hour ambulatory monitoring showed normal diurnal variation with appropriate nocturnal dipping. The office reading was a stress response, not disease. Treating the number without understanding the pattern would have been inappropriate.
Future Considerations
Advances in molecular biology continue to reveal new homeostatic mechanisms. Epigenetic modifications affect gene expression in response to environmental signals. Microbiome research shows gut bacteria influence metabolic homeostasis. Cell signaling pathways overlap in ways that create complex regulatory networks. I followed research on circadian rhythm disruption and metabolic disease. Shift workers show higher rates of obesity, diabetes, and cardiovascular disease. The mechanistic link involves melatonin disruption affecting glucose metabolism. The anatomical changes in pancreatic function reflect chronic circadian misalignment. The chemical changes in hormone levels mediate the effect. Personalized medicine approaches homeostasis as individual rather than population-based. Genomic information predicts drug response. Biomarker panels assess homeostatic reserve. Digital health monitoring tracks individual patterns over time. The goal is matching intervention to individual homeostatic characteristics rather than applying population averages.
Educational approaches continue evolving. Case-based learning emphasizes integration. Simulation training allows safe practice of homeostatic management. Interprofessional education reflects the collaborative nature of clinical care. These methods better prepare students for the complexity of homeostatic practice. The anatomical, chemical, and physiological dimensions of homeostasis remain essential for understanding biology and medicine. Mastery requires seeing connections rather than memorizing isolated facts. The practical application of this understanding determines clinical effectiveness and patient outcomes. The integration itself is the skill worth developing.
