How to Actually Learn Anatomical Directional Terms
The way most people study directional terms is wrong. They memorize definitions and then get confused on a test because the question isn't asking for a definition. It's asking you to apply them to a diagram they've never seen before. I spent years watching students hit the same wall. Here's what I did instead. I stopped treating it like vocabulary and started treating it like a coordinate system. That's all these terms are. They're coordinates for locating things on a body. Once you understand the framework, you stop memorizing and start reasoning.
Anatomical Directional Terms Practice for Real Results
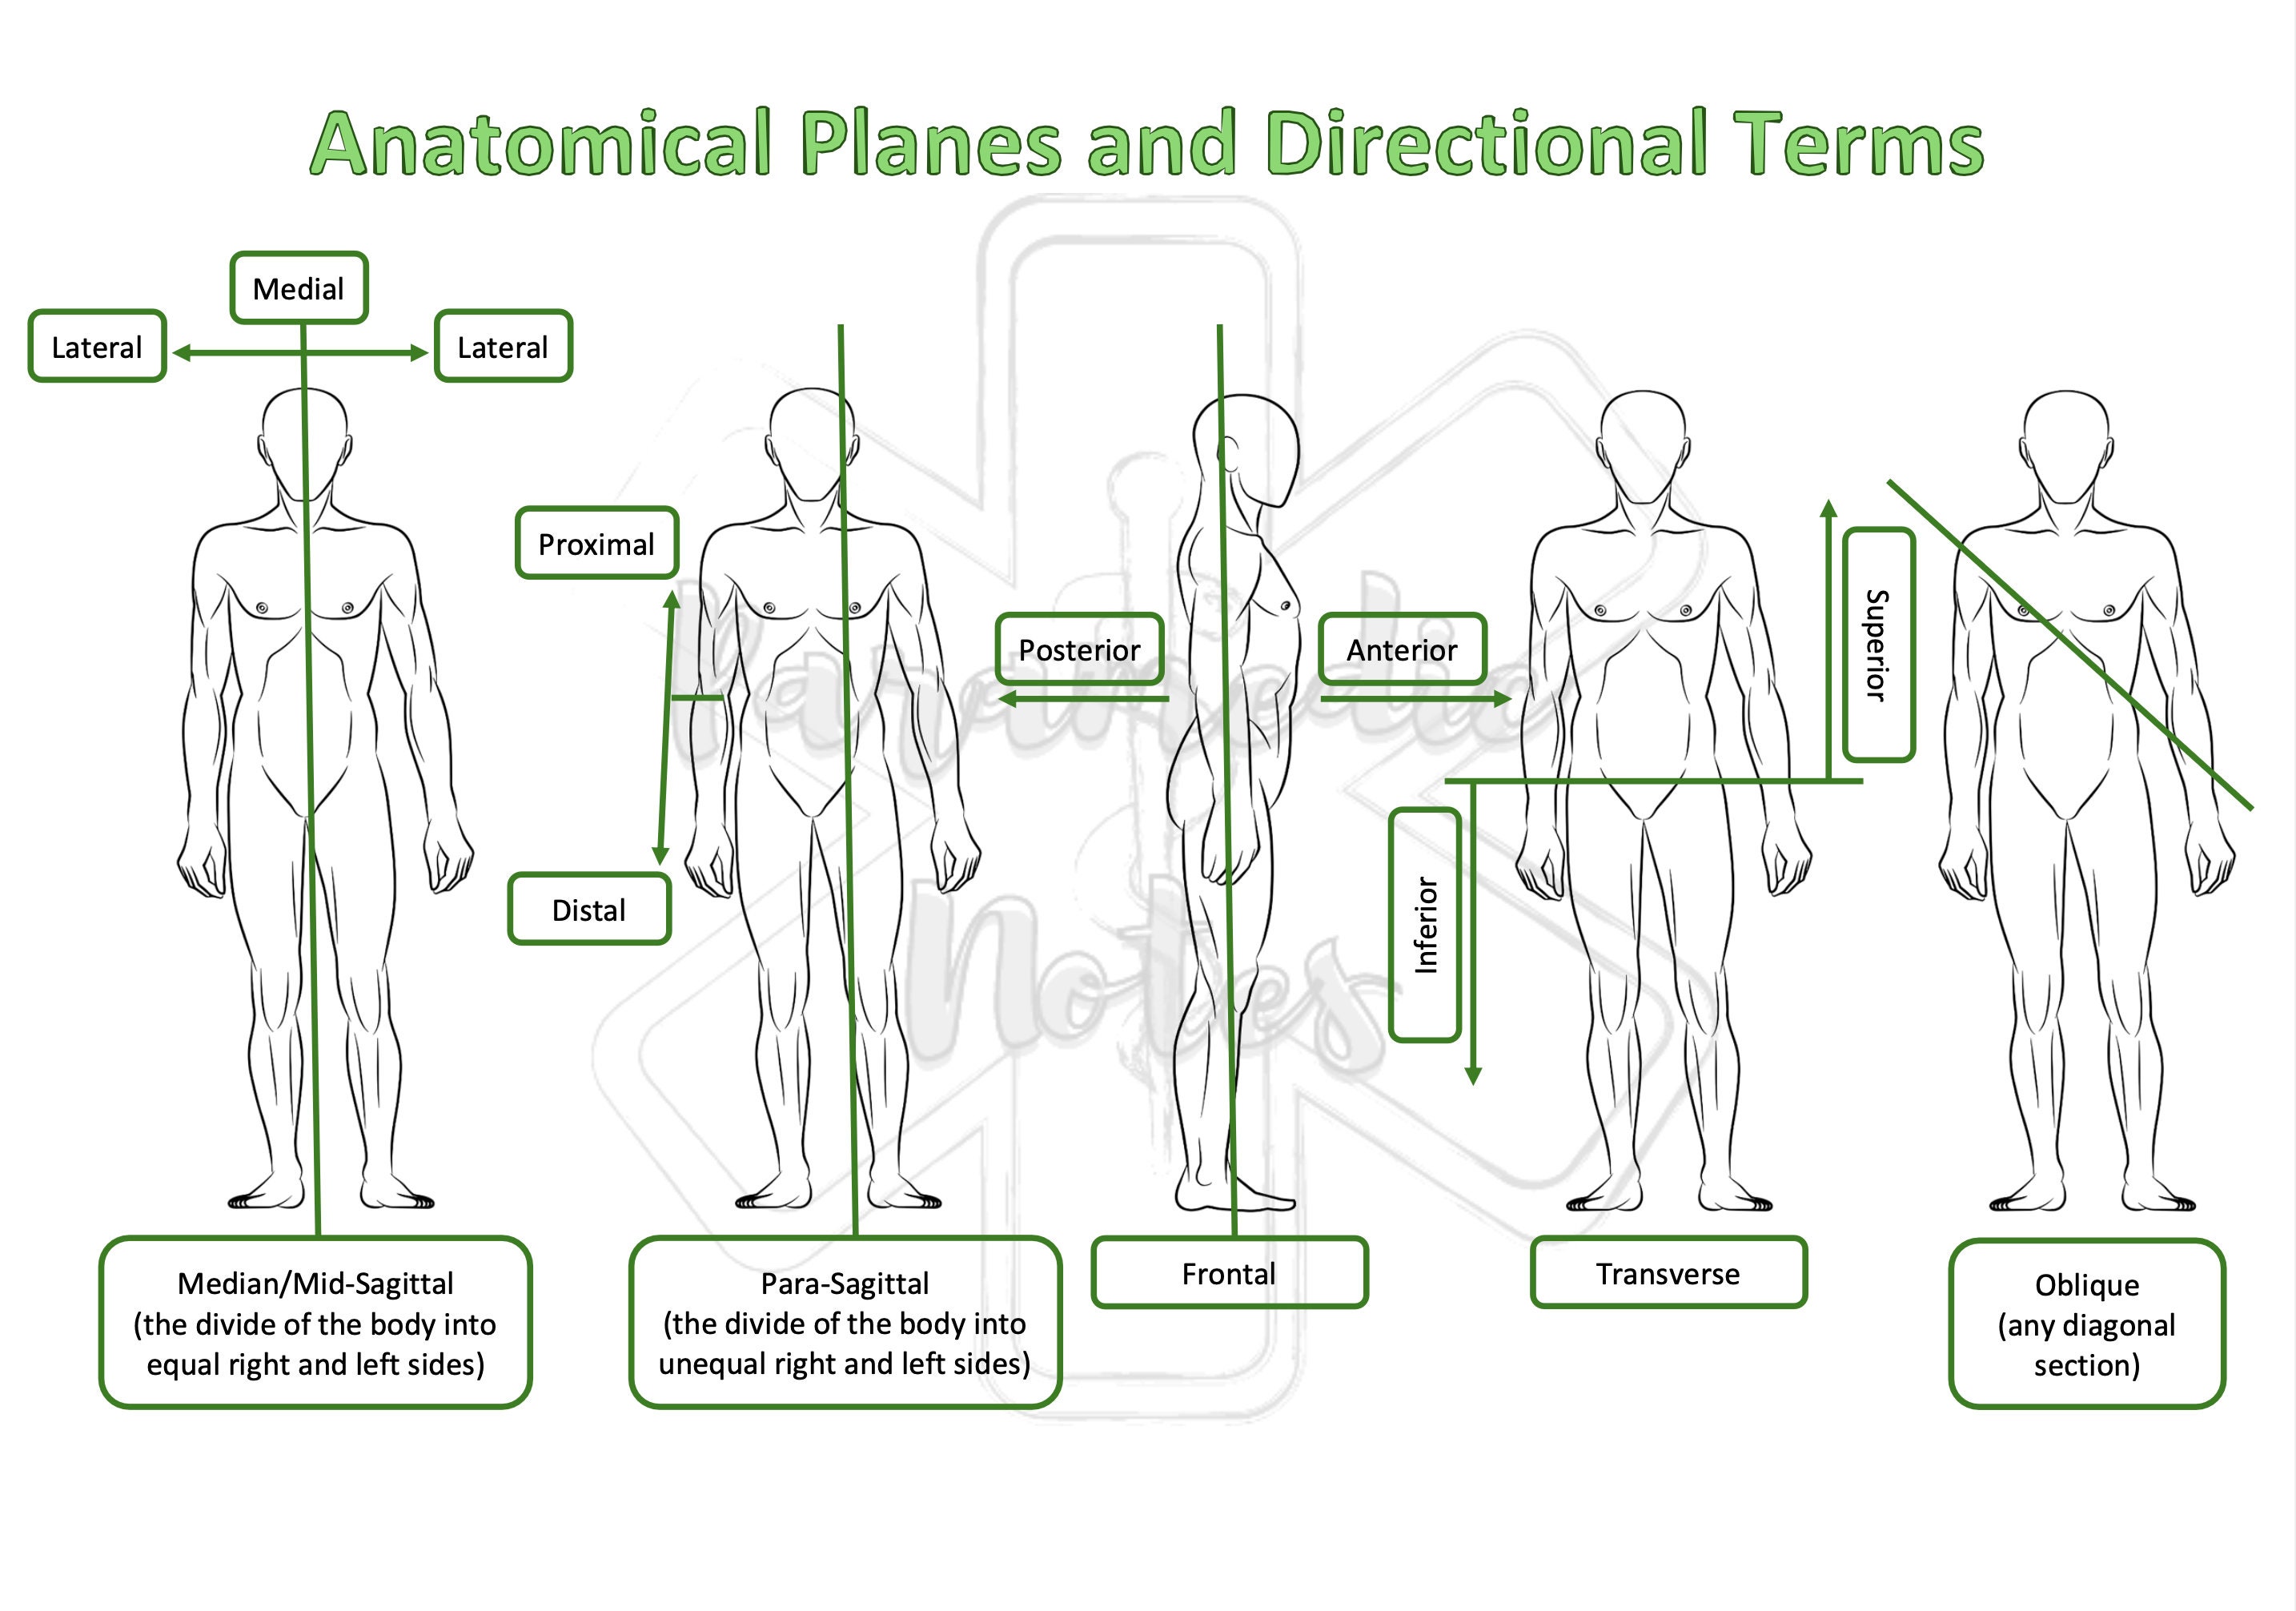
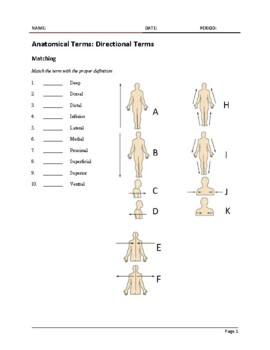
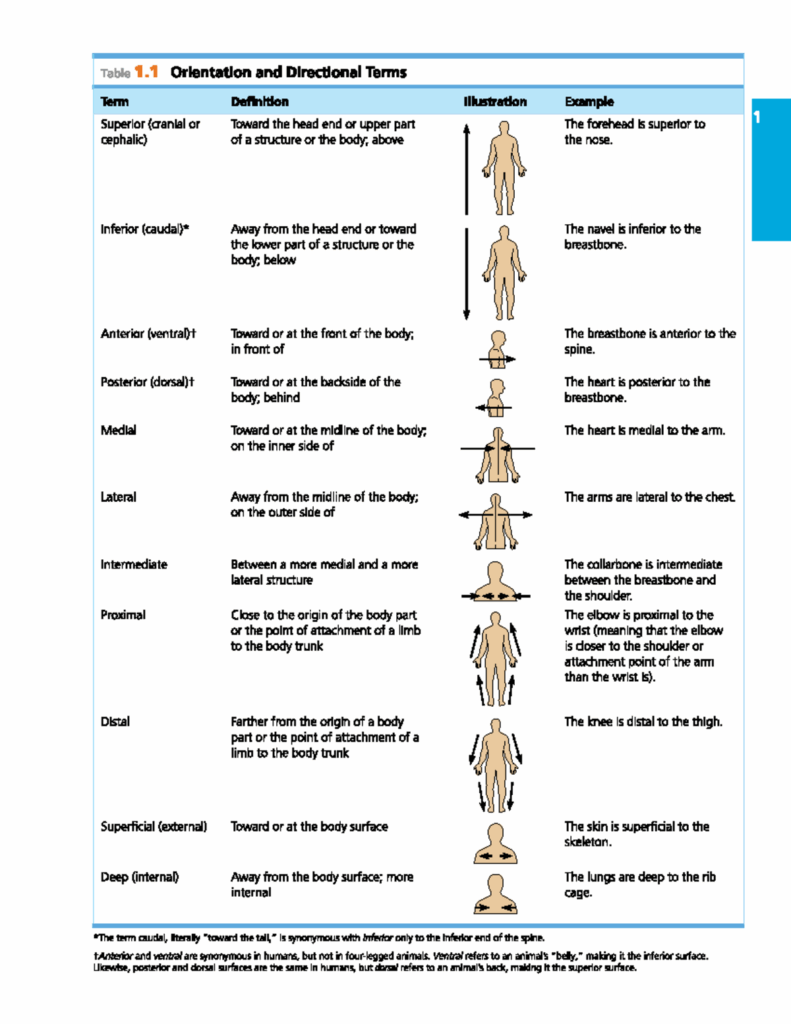
The standard terms you need are superior and inferior, anterior and posterior, medial and lateral, proximal and distal, superficial and deep, and ipsilateral and contralateral. Then there are the planes: sagittal, frontal (coronal), and transverse (axial). That's really it. Everything else is a variation or a combination of these. My method was simple and it cuts the learning time down to about a week if you're doing it right. Draw the anatomical position figure once. Not 20 times. Once. Use it as your reference point for everything. Every directional term is measured relative to that single standard posture: standing upright, facing forward, arms at the sides, palms forward. If you deviate from that mentally, your answers will be wrong. After drawing the figure, I'd take a real cadaver photo or a detailed anatomical illustration and ask myself five questions about it. Where is structure A relative to structure B? Is it medial, lateral, superior, inferior, anterior, posterior? What plane would I slice through to see both structures? Which structures are ipsilateral versus contralateral? Which is more superficial? I'd do this for one image per day and write out the full answer, not just the one-word term.
The writing part matters. When I just thought the answer, I got things wrong about 40% of the time. When I wrote it out and had to justify it, the error rate dropped to under 10%. The justification step forces you to engage with the anatomy rather than pattern-match to terms you half-remember. I hit a wall with proximal and distal early on. These terms apply to limbs and the appendicular skeleton. They mean closer to or farther from the point of attachment. But I kept applying them to axial structures like the ribs and spine by accident. During my first anatomy practical, I wrote "distal" when describing the position of the lumbar vertebrae relative to the thoracic vertebrae. That was wrong. It should be inferior. The professor circled it and wrote "limb terminology" next to it in red pen. My workaround was to create a hard boundary rule for myself: proximal and distal only for anything attached to the axial skeleton via a limb girdle or a true limb. Everything else defaults to superior and inferior. I put a sticky note on my desk that said "limbs only" for the next three weeks. It sounds extreme but it worked. After about 18 days, the distinction stopped feeling arbitrary and started feeling automatic.
Get the Full Details

Another thing nobody tells you: "deep" and "superficial" don't always map to what you intuitively think. In a supine patient, superficial doesn't mean "toward the ceiling." It means toward the anterior surface of the body. Directional terms are body-referenced, not environment-referenced. This trips people up repeatedly, especially in radiology contexts where the patient is lying down. I also learned that the term "ventral" and "dorsal" are technically correct but region-dependent. Ventral equals anterior in the trunk. But in the head, ventral means inferior and dorsal means superior. If you're studying neuroanatomy or cranial nerves, this switch will catch you if you're not paying attention. I keep a separate reference card for cephalic directional terms because the convention flip is real and it's easy to forget under pressure. For the planes, my advice is to visualize actual surgical incisions or CT slices rather than memorizing textbook diagrams. A transverse plane through the abdomen at the level of L4 is roughly where the aorta bifurcates into the common iliac arteries. If you anchor the plane to a landmark you can picture, you'll remember it. Abstract geometry descriptions fade fast.
There's a limit to how much practice this method covers though. Directional terms work well for external anatomy and cross-sectional imaging. They break down when you're dealing with organs that have rotated during development. The left kidney sits at a different vertebral level than the right. The spleen is posterior and superior to the stomach but also lateral. Single directional terms become insufficient for describing relationships involving hollow viscera or complex three-dimensional arrangements. In those cases, clinicians switch to topographic and regional terminology. Instead of saying the pancreas is medial to the spleen, they'll say it's in the left hypochondriac region with a note about its retroperitoneal position. If you're studying for clinical rotations or radiology boards, directional terms alone won't carry you. You need regional anatomy on top. The other hard limitation is clinical positioning. Directional terms assume the anatomical position. In a trauma bay, a patient might be prone, rotated, or in Trendelenburg. The terms don't change meaning, but applying them correctly requires you to mentally reorient the body back to anatomical position first. I've seen surgeons describe a wound as "lateral" when the patient was laterally decubitus and the structural relationship was actually medial. The mistake came from describing relative to the bed rather than relative to the patient.
If you want a resource to work from, the OpenStax Anatomy and Physiology textbook has a free downloadable chapter on anatomical terminology with practice questions that are actually useful. The University of Michigan's anatomical terminology quiz is also decent for self-testing. Both are free and don't require creating an account. I'd skip the commercial flashcard apps unless they let you import custom sets. Generic decks rarely include the kind of image-based questions you'll actually face on exams. Here's a practice set you can use today. I used something like this and it took me about 45 minutes total to work through, with the writing step included. Set 1: Upper Extremity
Look at a standard anatomical illustration of the upper limb in the anatomical position. Describe the position of each structure relative to the others: the elbow relative to the shoulder, the wrist relative to the elbow, the little finger relative to the thumb, the biceps relative to the triceps, the radial artery relative to the ulnar artery, the deltoid relative to the acromion. Set 2: Cross-Sectional Imaging Find a CT scan at the level of the kidneys. Identify which kidney is higher. Describe the liver relative to the right kidney. Describe the spleen relative to the left kidney. What plane is this image in? Now find a sagittal MRI of the brain and describe the position of the pituitary gland relative to the optic chiasm.
Set 3: Clinical Scenario A patient presents with pain in the right inguinal region. The pain radiates inferiorly and laterally toward the right thigh. The patient is supine. Describe the path of radiation using anatomical directional terms. Now imagine the same patient is standing. Does anything change in your description? Working through sets like this for two weeks, writing out the answers each time, was what pushed my practical accuracy from rough to reliable. It's not glamorous. It's repetitive. But it works, and it's faster than waiting until the exam to realize you don't actually understand the difference between proximal and inferior when applied to the brachial plexus.
I still use these terms daily in my work. They're the baseline language. Getting them solid early saves hours of relearning later when you're trying to read a case study or communicate with a colleague across specialties. That's the whole point of practice. Not passing a quiz. Building a muscle you'll use every day without thinking about it.