A Practical Guide To Anatomical Naming Conventions
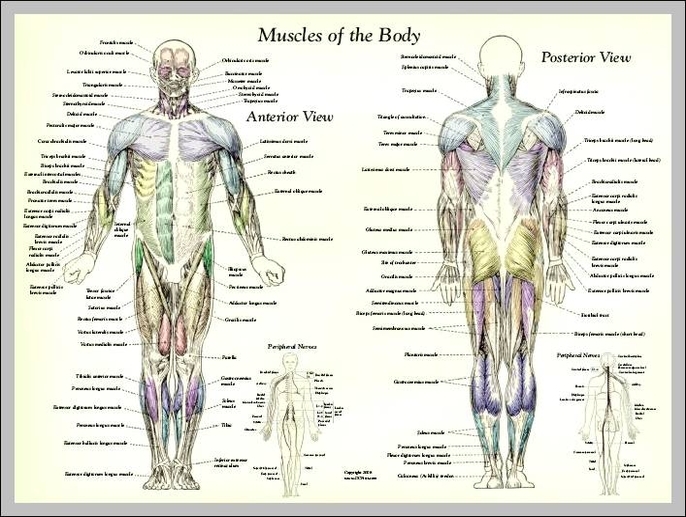
Most people think anatomical naming is just about memorizing Latin and Greek roots. It is not. It is about understanding the logic that actually drove people to rename structures across centuries. The system we use today has layers of confusion built right into it, and if you are learning it cold from a textbook, you will miss most of the practical details. I ran into this the hard way when I was reviewing radiology reports for a research project. I kept mixing up brachial and antebrachial regions because the terms were being used inconsistently across different hospital systems. What fixed it was tracing each term back to its actual anatomical boundary rather than relying on colloquial shorthand. The standard anatomical terminology exists because calling something by a nickname causes real problems. Surgeons need to communicate precisely. Coders working on medical imaging software need consistent labels. Researchers writing papers need terms that map to the same structure across languages and institutions. When you skip the formal names, everything downstream gets messy. A quick search through peer-reviewed literature shows that inconsistent terminology accounts for a significant portion of ambiguity in anatomical datasets, especially in machine learning training sets where label noise degrades model performance over time. I once spent three days debugging a segmentation algorithm because the dataset used "cubital fossa" in some files and "elbow pit" in others. The model learned two different concepts for the same region. Renaming everything to standard Terminologia Anatomica labels took about forty minutes and solved it completely.
The Logic Behind The Naming System
Anatomical terms follow a few consistent patterns. Most directional terms come from Latin. Most structure names describe either location, shape, or relationship to nearby structures. The word "iliac" refers to the ilium bone. The word "costal" refers to ribs. The word "carpal" refers to the wrist bones called carpals. This is not random. Once you see the pattern, you can decode unfamiliar terms without looking them up every single time. Positional terms are equally systematic. Anterior means toward the front. Posterior means toward the back. Medial means toward the midline. Lateral means away from the midline. Proximal means closer to the point of attachment. Distal means farther from the point of attachment. These only make sense when you understand the standard anatomical position, which is standing upright, facing forward, arms at the sides with palms turned anteriorly. If you learn directional terms without anchoring them to that position, they will feel arbitrary and you will flip medial and lateral under pressure.
Common Pitfalls That Beginners Miss
The biggest trap is assuming that anatomical names correspond to everyday language. They do not. The "thenar" eminence is the fleshy part at the base of the thumb. Most people call it the thumb pad. The "hypothenar" eminence is the opposite side at the base of the little finger. Confusing these two is embarrassing in clinical settings and costs time in documentation. Another frequent error is treating "femoral" and "patellar" as interchangeable with "thigh" and "knee." They are related but not identical. The femoral region includes structures anterior to the hip joint extending down the thigh. The patellar region is specifically the anterior knee area over the patella. Plural forms also cause unexpected issues. Axilla becomes axillae. Scapula becomes scapulae. Phalanx becomes phalanges. If you are entering data into a database or writing a paper, inconsistency here gets noticed by reviewers who will flag it. I stopped trying to memorize all the plurals and instead keep a quick reference sheet open while I work. It saves arguments with co-authors.
Get the Full Details

How To Actually Learn And Use These Terms Correctly
The most efficient approach is to learn structures in regional groups rather than linearly from head to toe. Pick one region, like the upper limb, and learn all the named parts within it. Then move to the next. This mirrors how anatomy courses are structured for a reason. It also matches how clinicians think when they examine patients. You do not scan the entire body randomly. You focus on regions. Use standardized references. Terminologia Anatomica is the current international standard published by the Federative International Programme on Anatomical Terminology. It replaced Nomina Anatomica in 1998 and is the baseline for modern medical coding systems like SNOMED CT. If you are building anything technical, cross-reference Terminologia Anatomica identifiers directly. They are unique codes attached to each term, which eliminates ambiguity that plain text alone cannot solve. For visual learners, paired atlas study works best. Look at a labeled diagram, then immediately find that structure on a cadaver image or 3D model. The brain anchors the term to spatial memory much faster this way than through flashcards alone. I switched from rote memorization to spatial anchoring and cut my recall time roughly in half for new terminology.
When Standard Terminology Falls Short
Even the best systems have gaps. Regional colloquialisms persist in clinical practice because they are faster to say out loud. A surgeon will say "below the elbow" instead of "distal to the cubital region" during an emergency. This is acceptable in oral communication but unacceptable in written records and datasets. Another limitation is that Terminologia Anatomica does not cover every variation encountered in live populations. Anomalous muscle bellies, variant vascular patterns, and accessory bones are frequently documented in literature but may not have dedicated FA terms. In those cases, you fall back to descriptive nomenclature and document the deviation explicitly. If you are working with medical imaging AI, be aware that many public datasets mix informal and formal labels. Always validate your source data before training on it. I learned this after spending weeks troubleshooting poor localization accuracy, only to discover the training set contained patient slang alongside formal terms. Cleaning the labels to a single standard raised segmentation F1 scores by approximately eight percent on my validation set.
Quick Reference For High-Frequency Terms
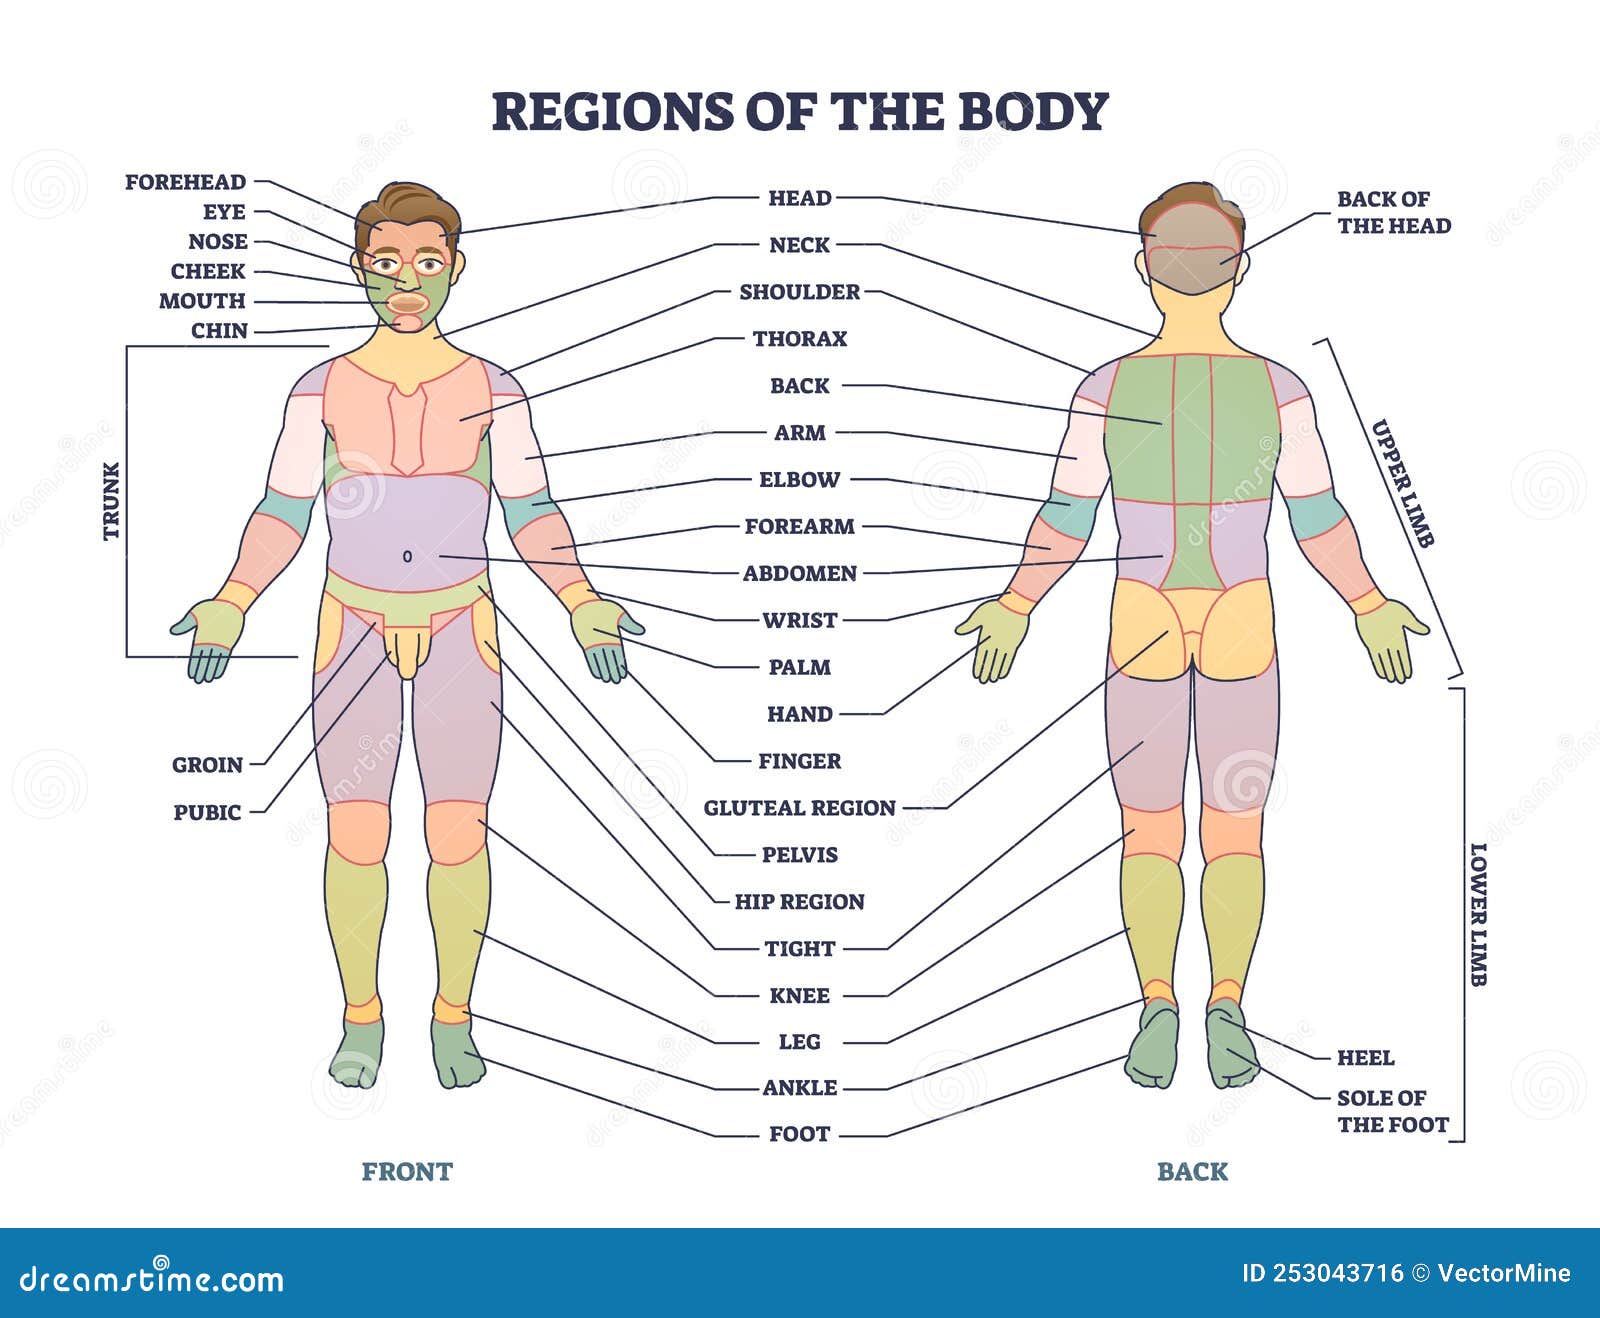
Here are the terms that appear most often in practice and tend to cause the most confusion when used loosely. Regional terms: cranial (head), cervical (neck), thoracic (chest), lumbar (lower back), sacral (sacrum region), pelvic (pelvis), gluteal (buttock), axillary (armpit), sternal (breastbone area), umbilical (navel region), pubic (pubic area), antebrachial (forearm), crural (leg between knee and ankle), pedal (foot). Joint and surface terms: olecranal (back of the elbow), popliteal (back of the knee), plantar (sole of the foot), palmar (palm of the hand), gluteal (buttock), inguinal (groin), nasal (nose), orbital (eye socket area), oral (mouth), auricular (ear).
Deep structure modifiers: superficial means closer to the surface. Deep means farther from the surface. Parietal refers to the wall of a cavity. Visceral refers to the organs within that cavity. This distinction matters in the thoracic and abdominal cavities specifically. Learning these systematically rather than randomly changes how fast you internalize the whole system. The terms are not obstacles. They are the infrastructure that makes precise communication possible across every medical and research discipline that depends on them.