Understanding How the Body Divides Itself Anatomically
When I first started working with medical imaging and anatomical studies, I kept tripping over how different fields define their regions. Radiologists use one set of terms, surgeons use another, and anatomists have yet a third system. I learned the hard way that mixing these up during a consultation caused confusion with a patient who was trying to understand their own scan results. They showed me a report that mentioned "right upper quadrant" while their surgeon referred to "epigastric region" - same general area, completely different vocabulary. That moment taught me the value of understanding both systems clearly.Why Anatomical Regions Of The Body Matter in Practice
The body isn't a blank canvas that needs arbitrary divisions, but these regions exist because they make communication possible. Without standardized terminology, describing where something hurts or where a tumor sits would devolve into hand-waving gestures. Think about how many times you've heard someone point vaguely at their "stomach" when they mean something entirely different. Anatomical regions cut through that ambiguity. I remember spending weeks trying to reconcile why different textbooks placed the boundaries of the lumbar region differently. Some included L1-L4, others stopped at L3. The practical solution I found was realizing that clinical contexts dictate the division more than any rigid rule. When dealing with lower back pain, the distinction matters less than understanding which nerves and structures are actually involved. The region is a shorthand, not a biological fact.
Common Anatomical Region Systems
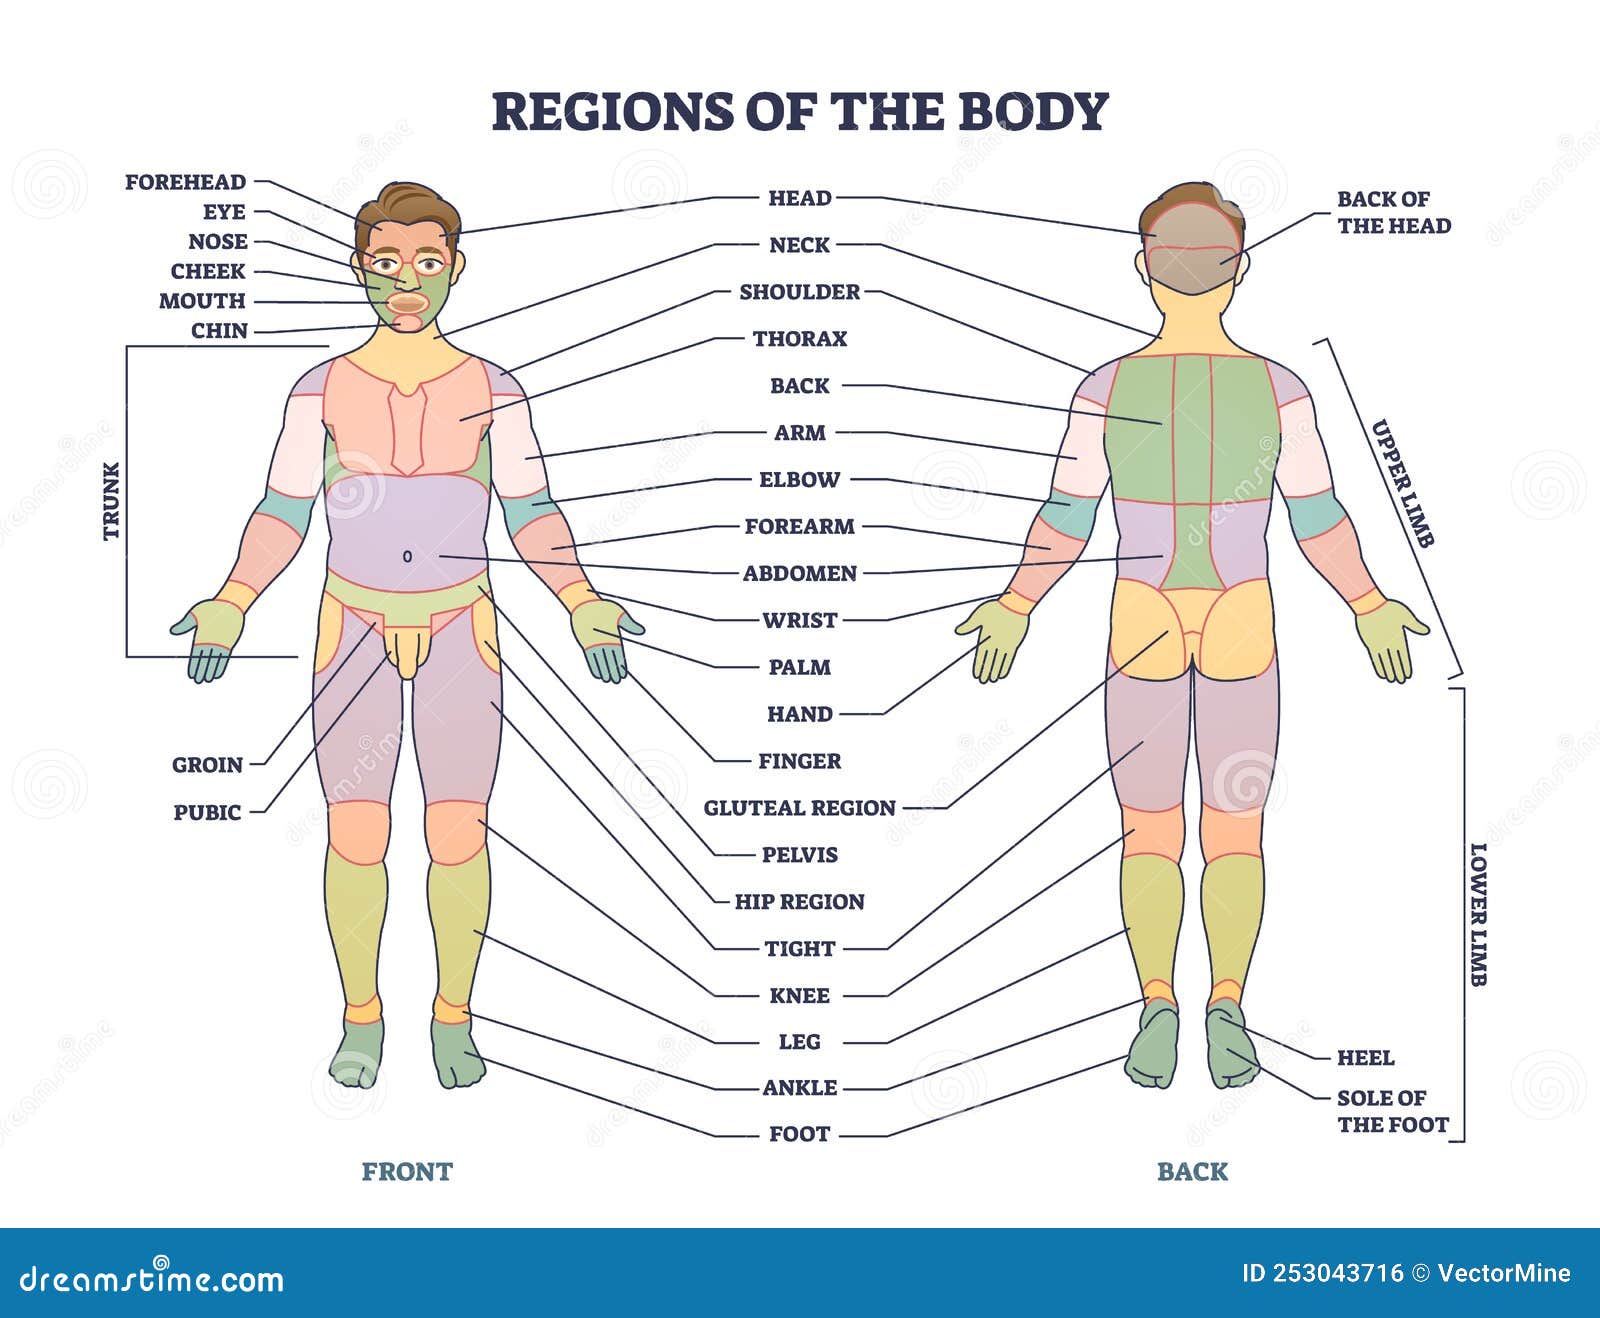
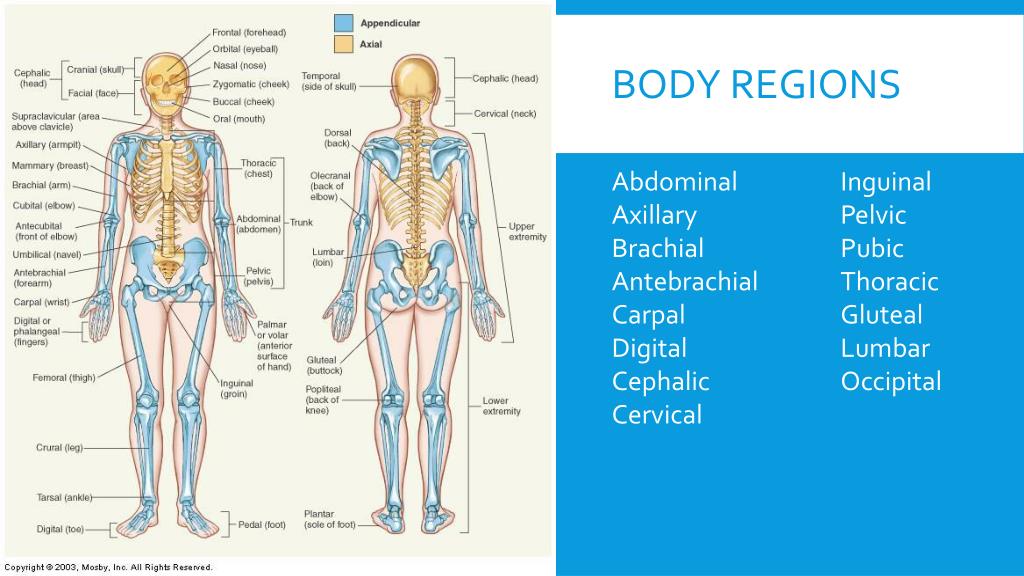
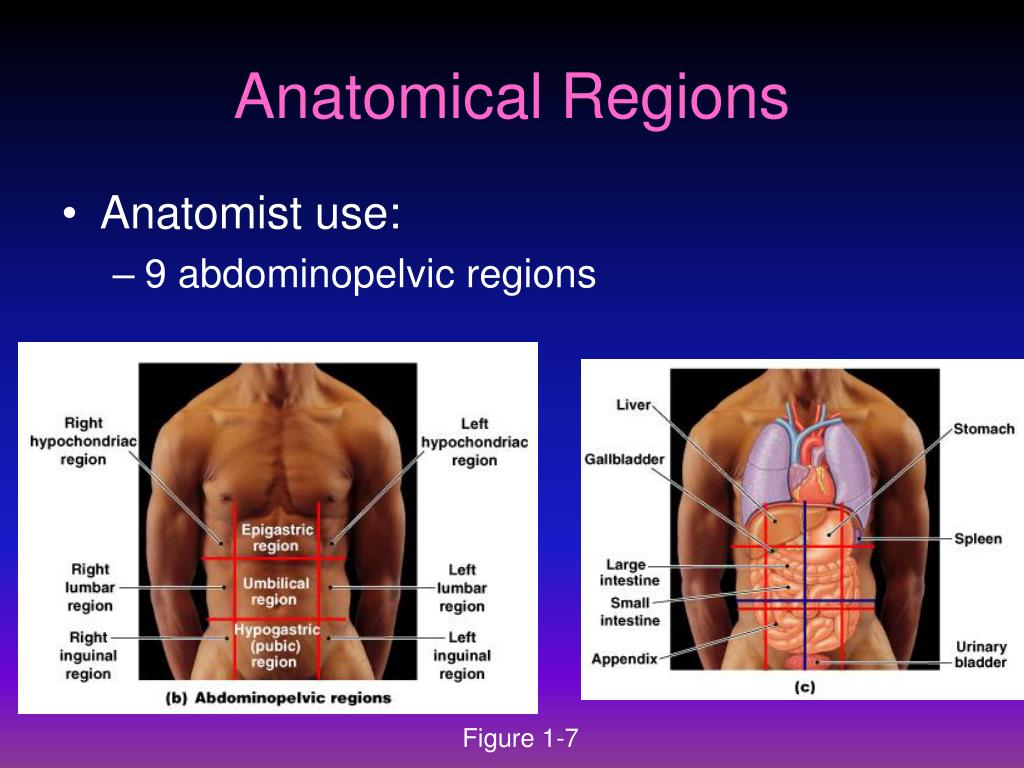
There are several frameworks people actually use in healthcare settings. The nine-region division splits the abdomen into left and right hypochondriac, epigastric, umbilical, left and right iliac, and hypogastric zones. It's widely taught in medical schools and still used for physical examination descriptions. The four-quadrant system is simpler, dividing the abdomen with a single vertical and horizontal line through the umbilicus. Emergency departments often prefer this one because it's faster to communicate during urgent situations. For the extremities, the terminology shifts completely. Upper limbs are described using brachial, antebrachial, and carpal regions. Lower limbs use femoral, crural, and tarsal divisions. These aren't arbitrary - they map closely to the underlying bones and vascular territories. I found this distinction crucial when documenting surgical approaches for vascular procedures. Getting the nomenclature wrong in operative notes can create confusion for anyone reading the chart months later.
Regional Anatomy Beyond Surface Landmarks
Surface anatomy only tells you so much. The deeper fascial planes, neurovascular bundles, and lymphatic drainage patterns define regions more accurately than skin markings ever could. When I worked on a project mapping surgical approaches for abdominal wall hernias, I discovered that the clinically apparent regions don't always align with the actual tissue planes surgeons encounter. The rectus sheath, for example, has different boundaries depending on whether you're above or below the arcuate line. Beginners often miss this entirely and attempt closures that tear through unsupported tissue. The workaround I developed involved mapping each patient's anatomy on ultrasound before making any incisions. It added maybe twenty minutes to the preoperative workup but prevented several complications that would have required revision surgery.
Get the Full Details
Counter-intuitive Aspects Most People Miss
Here's something that surprises most students: the anatomical regions change position with body habitus and posture. The iliac crest, which marks the boundary between the lumbar and gluteal regions, shifts significantly when you flex forward versus stand upright. I encountered this problem repeatedly with obese patients where surface landmarks became unreliable guides. We ended up using ultrasound navigation for regional blocks instead of blind landmark techniques. Another overlooked point is that regional terminology varies between clinical specialties. Oncologists describe tumor spread using compartment-based language rather than surface regions. A breast cancer stage depends more on which fascial planes the disease has crossed than on which "quadrant" it initially appeared in. Learning to translate between these systems became essential during my tumor board presentations where surgeons, radiologists, and oncologists all spoke slightly different dialects of the same anatomical language.
Practical Applications and Pitfalls
Regional anatomy isn't just academic exercise. Understanding these divisions directly affects how you approach diagnostic procedures, surgical incisions, and even physical therapy protocols. I once watched a colleague perform a lumbar puncture using landmarks from the wrong regional system, nearly nicking the spleen because they misunderstood the superior-inferior boundaries of the loin region. The documentation standards matter too. Medical records require consistent regional terminology, and mixing systems within a single chart creates confusion that can affect patient safety. I learned this after reviewing a transfer summary where the referring facility used quadrants while our team used nine regions. Reconciling those descriptions took additional time that could have been avoided with standardized communication from the start. Most importantly, anatomical regions serve as the foundation for understanding pathology location, progression patterns, and treatment planning. Whether you're describing a rash distribution, planning an incision, or documenting exam findings, getting the regional terminology right makes the difference between clear communication and costly misunderstanding.