Getting Your Bearings in the Body
I spent years reading CT scans and writing radiology reports before the directional language in my head became automatic. The first few months were brutal because every structure had a name AND a position, and your brain wants to conflate the two. You memorize that the pancreas is retroperitoneal, but you still have to consciously tell yourself which way is medial without looking at the image first. Here is the thing nobody warns you about: the terms themselves are not hard. What is hard is that they are relative, not absolute. Superior and inferior only make clean sense in standard anatomical position, which means standing upright, arms at the sides, palms facing forward. Once the patient is supine on an exam table, superior becomes closer to the head and inferior becomes closer to the feet, but radiologists and surgeons still use those terms exactly as defined, which means you have to mentally rotate the patient every single time without pausing to acknowledge the rotation. I used to miss left-sided pathology once because I looked at a prone spine image and accidentally treated caudal as left lateral. Took me six weeks to stop doing it.
Core Anatomy Directional Terms
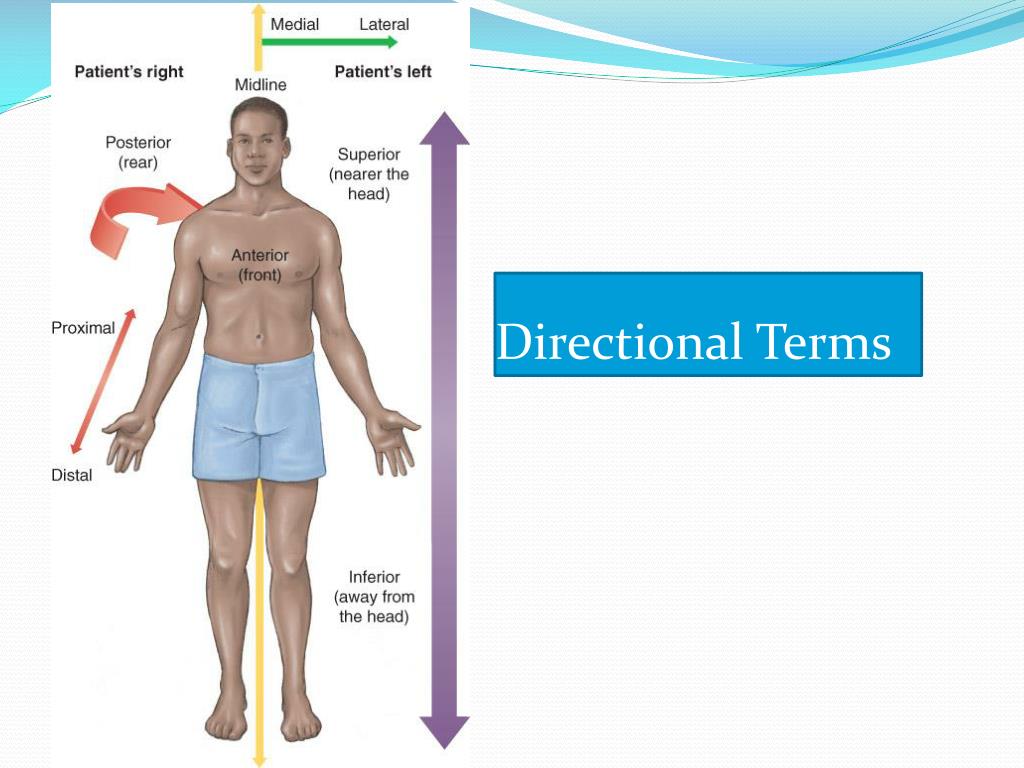
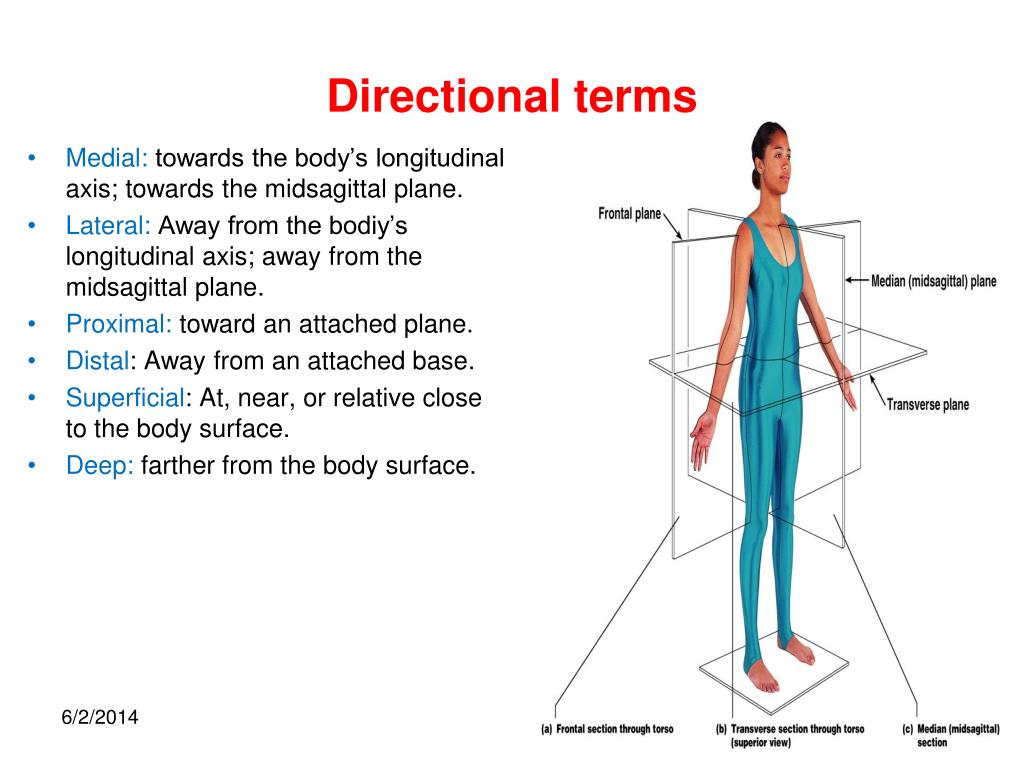
Anterior (ventral) and posterior (dorsal): front versus back. In humans these map cleanly onto belly and spine. In quadrupeds the words flip meaning, which trips up anyone who has done comparative anatomy. Keep them tied to human orientation and you will be fine. Superior and inferior: toward the head versus toward the feet. Straightforward until you start describing things in the head itself, where people sometimes swap these with rostral and caudal out of habit. Rostral points toward the nose, caudal toward the spinal cord. Use them in neuro when talking about structures inside the cranium. Outside the cranium, superior and inferior are still correct. Medial and lateral: toward the midline versus away from it. The midline is a parasagittal plane, not a physical structure, which means when you are describing something like the lateral malleolus, you are saying it sits far from that imaginary central line. Common mistake: calling the ulna lateral when describing the forearm. The ulna is medial. The radius is lateral. Your thumb side is lateral regardless of whether the arm is pronated or supinated, which is why some students get confused when the palm flips.
Proximal and distal: closer to the trunk attachment versus farther from it. These only apply to appendages and structures with a clear point of origin. You would say the elbow is proximal to the wrist, and the knee is distal to the hip. Do not use these for the trunk itself. The sternum is not proximal to the spine, it is anterior to it. That distinction matters on boards and in actual clinical notes. Superficial and deep: closer to the skin surface versus farther inward. A subcutaneous nodule is superficial to the muscle. An intra-articular lesion is deep to the joint capsule. This one seems simple until you are describing a needle trajectory and need to be precise about how many centimeters of tissue the tip crosses before reaching the target. In those cases superficial and deep are directions, not distances, and you pair them with measurements. Ipsilateral and contralateral: same side versus opposite side of the body. Surgeons live by these. If you write contralateral when you mean ipsilateral in an operative note, someone could operate on the wrong limb. I have seen near-misses happen from exactly this kind of swap. Always verify laterality against the imaging label and the patient's marking before proceeding.
Get the Full Details

Planes and Their Relationship to Direction
Sagittal planes divide the body into left and right portions. A midline sagittal plane runs directly through the midline. Paramedian sagittal planes sit to either side of it. Coronal (frontal) planes divide anterior from posterior. Transverse (axial) planes divide superior from inferior. These are not optional descriptors. They define the axis along which every directional term operates. When you read an axial CT, everything on the left side of the image is actually the patient's right side. This reversal exists because the convention is to view the patient from the feet looking up, not from the head looking down. I used to fight this for months. The workaround was brutal but effective: I stopped trying to mentally reorient and started drawing the patient's right side directly on the screen with a digital marker before reading anything. It added twelve seconds per study but eliminated nearly all laterality errors within three weeks. Oblique planes are the real problem. Echocardiography and some MRI protocols routinely use oblique views that do not align with the standard three planes. In those images, anterior might tilt toward the patient's left, and inferior might point posteriorly. You cannot rely on habit here. You have to identify the plane from the view identifier on the image and translate each directional term accordingly. If the sonographer or technologist labeled the view incorrectly, you are flying blind.
Pitfalls That People Actually Make
The biggest source of confusion is that some terms have different meanings depending on the region. Dorsal means posterior in the trunk but refers to the top of the hand and foot in the extremities. The dorsal surface of the hand is the back of the hand, which is technically posterior when the arm is in anatomical position with palms forward, but once the hand pronates, dorsal becomes anterior again in functional space. Anatomists keep using dorsal for the hand surface regardless of position because the term is tied to embryological development, not current orientation. It is annoying. It is also standard. Another trap is using cranial and caudal outside the neuraxis. Cranial and caudal refer to the head end and tail end of the embryo and, by extension, to structures along the neural tube. In the limbs, proximal and distal are the correct terms. Some clinicians use cranial for anything pointing toward the head, which is acceptable in casual speech but will cost you points on any rigorous exam. Laypeople constantly misuse medial and lateral by equating them with inner and outer in a general sense. The medial malleolus is on the inside of the ankle, yes, but medial specifically means closer to the midline, not closer to the body's interior. A structure can be medial and still be on the surface, like the medial epicondyle of the humerus. Understanding that the distinction is about horizontal positioning relative to the midline, not depth, prevents a lot of sloppy documentation.
A Practical Way to Internalize This
Stop studying the terms in isolation. Every time you encounter a structure, describe its position using at least two directional terms at once. The spleen is not just left, it is left, posterior, and inferior to the stomach. The appendix is not just lower right, it is typically right lower quadrant, posterior to the cecum, and variable in its relation to the ileum. Dual-directional descriptions force you to pick the correct plane and orientation, which is where most mistakes originate. When I was a resident, my attending made us write full positional descriptions for every mass we saw on imaging, no shortcuts. A one-line report like "left upper quadrant mass" was rejected and sent back. It took forever at first, maybe forty-five minutes for a report that used to take ten. After two months it dropped to under fifteen, and the accuracy of my laterality calls improved noticeably. The extra effort compresses into habit faster than most people expect.

When These Terms Fall Apart
Directional terms assume a relatively normal body plan. They break down with significant deformity, post-surgical alteration, or extreme positioning. A patient with a severe scoliosis does not have a clean midline. Calling something medial or lateral becomes approximate at best. A patient who has had a mastectomy loses the landmark that defines lateral chest wall anatomy. Terminology still works, but the reference points are compromised, and you need to state that explicitly in any note. Bariatric patients present the same issue on a larger scale. Depth descriptors like superficial and deep are meaningless without quantitative measurements because what counts as superficial in a thin patient is deep in a patient with a substantial pannus. I learned to switch from qualitative to quantitative language in those cases: "the lesion lies 4.2 cm beneath the skin surface" instead of "subcutaneous." It is more work to measure each time, but it is also accurate. There is no workaround for pathological displacement. If a hernia has shifted bowel into the scrotum, describing the bowel as "in the abdomen" is technically true but clinically useless. You describe where it actually is, acknowledge the displacement, and move on. Directional terms map normal anatomy. They do not replace observation.