So you want to understand what's actually inside a blood drop
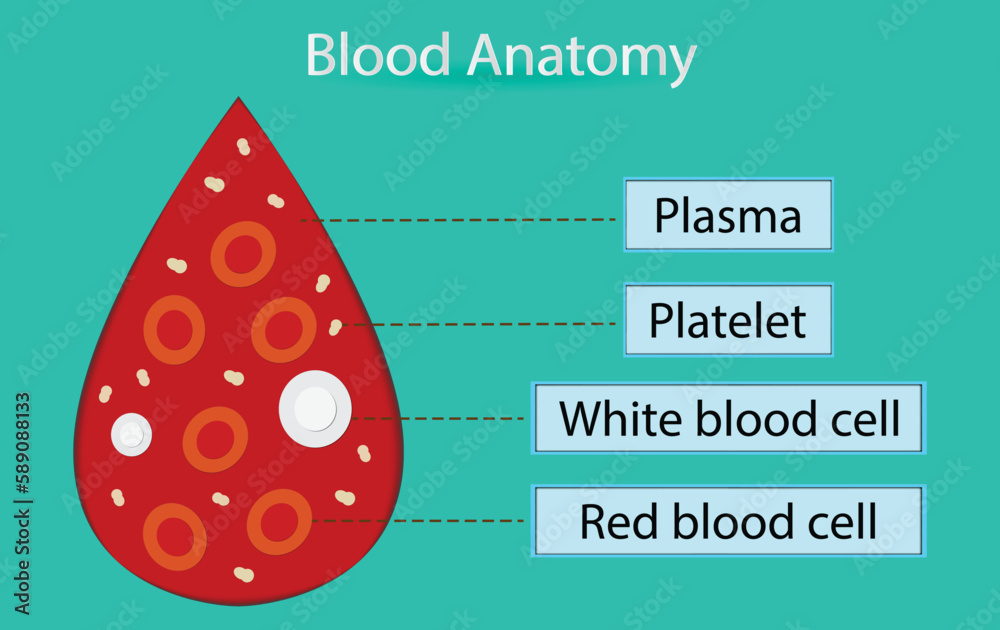
A single drop of blood, roughly 50 microliters by standard medical estimation, contains about 5 million red blood cells, somewhere between 4,000 and 11,000 white blood cells depending on your health status, and 150,000 to 400,000 platelets per microliter. The plasma makes up about 55 percent of the total volume. That's the basic accounting. What actually matters is how those components interact under real conditions, not just in a textbook diagram. Red blood cells are biconcave discs, roughly 6 to 8 micrometers in diameter. They lack nuclei in mammals, which gives them more room for hemoglobin. Each cell carries about 270 million hemoglobin molecules. The membrane is flexible enough to squeeze through capillaries as small as 3 micrometers wide. That flexibility degrades over the cell's 120-day lifespan, which is why the spleen filters them out. White blood cells come in five varieties, and they make up far less than 1 percent of blood volume. Neutrophils dominate at 40 to 75 percent of the total. Lymphocytes run next at 20 to 40 percent. Monocytes, eosinophils, and basophils fill out the rest. Their functions overlap in ways that matter clinically. A neutrophil and a macrophage will both phagocytose bacteria, but they operate on different timescales and in different tissue environments.
Platelets aren't cells. They're cytoplasmic fragments from megakaryocytes in the bone marrow. A platelet is 2 to 3 micrometers across and circulates for about 8 to 10 days. They store granules containing ADP, serotonin, calcium, and clotting factors. When vascular injury occurs, they adhere to exposed collagen through von Willebrand factor, activate, and aggregate. That's primary hemostasis. The coagulation cascade follows as secondary hemostasis. Plasma is mostly water, about 92 percent. The remaining 8 percent includes proteins like albumin, globulins, fibrinogen, electrolytes, hormones, dissolved gases, and waste products. Albumin maintains oncotic pressure and transports substances. Fibrinogen converts to fibrin during clotting. The total protein concentration in normal plasma sits around 6 to 8 grams per deciliter. I've spent years working with blood samples in lab conditions, and the thing nobody tells you is that the anatomy of a blood drop changes depending on how you handle it before you even look at it. Take EDTA anticoagulated whole blood and leave it at room temperature for four hours. Your glucose drops by roughly 5 to 7 percent per hour due to glycolysis by continuing cellular metabolism. Potassium leaks out of cells, artificially raising measured potassium levels. Platelets clump. White blood cell morphology degrades. If you're running a CBC on that sample, your platelet count will be wrong and your MCV might shift slightly from osmotic changes.
The workaround is simple but easily ignored. Separate plasma or serum within two hours of draw for chemistry panels. Keep CBC samples on ice if analysis can't happen within four hours. I learned this the hard way when I spent three days troubleshooting a lab that kept reporting falsely elevated potassium and low platelet counts. The samples were sitting on a bench between the phlebotomy station and the analyzer. Once we installed a centrifuge in the draw area and processed within the window, the results stabilized immediately. Here's something most introductory resources miss. The layering of components in a spun blood sample isn't just about density, it's about the buffy coat being deceptively thin. In a standard 5 mL EDTA tube spun at 1,500 RPM for 10 minutes, the buffy coat between the plasma and red cell layers is maybe 1 millimeter thick in a healthy adult. That thin band contains the vast majority of white blood cells and platelets. If you're pulling plasma for PCR or protein analysis and your pipette tip scratches that interface, you've contaminated your sample with leukocytes and platelets. Platelets release RNA and proteins during activation, which skews downstream assays. I've seen qPCR results ruined because someone was careless with the pipette at the buffy coat boundary. Use a P1000 pipette and withdraw plasma from the top, leaving at least 500 microliters above the buffy coat as a safety margin. Another counter-intuitive point. Hematocrit affects drug distribution. A patient with a hematocrit of 60 percent has significantly less plasma volume per milliliter of blood than someone at 40 percent. If you're calculating dosing for plasma-bound medications, the standard weight-based protocols can overshoot in polycythemic patients or undershoot in anemic ones. This matters more in critical care and oncology settings where hematocrit swings are common.
Get the Full Details

Microcirculation changes how a blood drop behaves outside the body versus inside it. Inside the body, red blood cells exhibit the Fåhraeus-Lindqvist effect, where effective viscosity decreases in vessels smaller than 300 micrometers. Outside the body on a slide or in a tube, that effect disappears. RBCs stack into rouleaux formations, especially when ESR is elevated. Rouleaux formation is a normal physical phenomenon driven by plasma proteins, particularly fibrinogen and immunoglobulins, but it also interferes with automated hematology analyzers. Some instruments flag high rouleaux as erroneous RBC counts. The workaround is dilution and mild acidification of the sample before analysis. If you're studying this for practical purposes, whether that's phlebotomy, laboratory science, or clinical work, the single most useful skill is learning to recognize pre-analytical variables. Sample hemolysis, clotting, contamination, improper volume, wrong anticoagulant, temperature abuse. These introduce errors that no amount of analytical precision can correct. A high-end analyzer will give you a beautifully precise wrong answer if the sample is compromised. The limitation of studying a static blood drop is that blood is dynamic. Composition shifts with hydration, circadian rhythm, posture, exercise, and acute stress. A fasting morning sample and an afternoon post-meal sample from the same person can show meaningful differences in glucose, triglycerides, and even white blood cell count. Neutrophilia from marginal pool redistribution after mild exercise is a classic example. If you're comparing results across time, control for these variables or the data becomes noisy.
For anyone wanting to actually observe these components, a light microscope with 40x and 100x oil immersion objectives is sufficient. A standard Wright-Giemsa stain on a peripheral blood smear reveals cell morphology clearly. You'll see neutrophil segmentation, lymphocyte nuclear density, platelet purple granules against a pink background. It's not glamorous but it's direct. The cost of entry is low. A decent used microscope runs a few hundred dollars. Stain kits are inexpensive. The learning curve is about two to three weeks of consistent practice before morphology identification becomes reliable. There's no shortcut around the basics. Draw the sample correctly, process it promptly, analyze it carefully, and question results that don't fit the clinical picture. Everything else is refinement.