Understanding Intersex Anatomy: A Clinical Breakdown
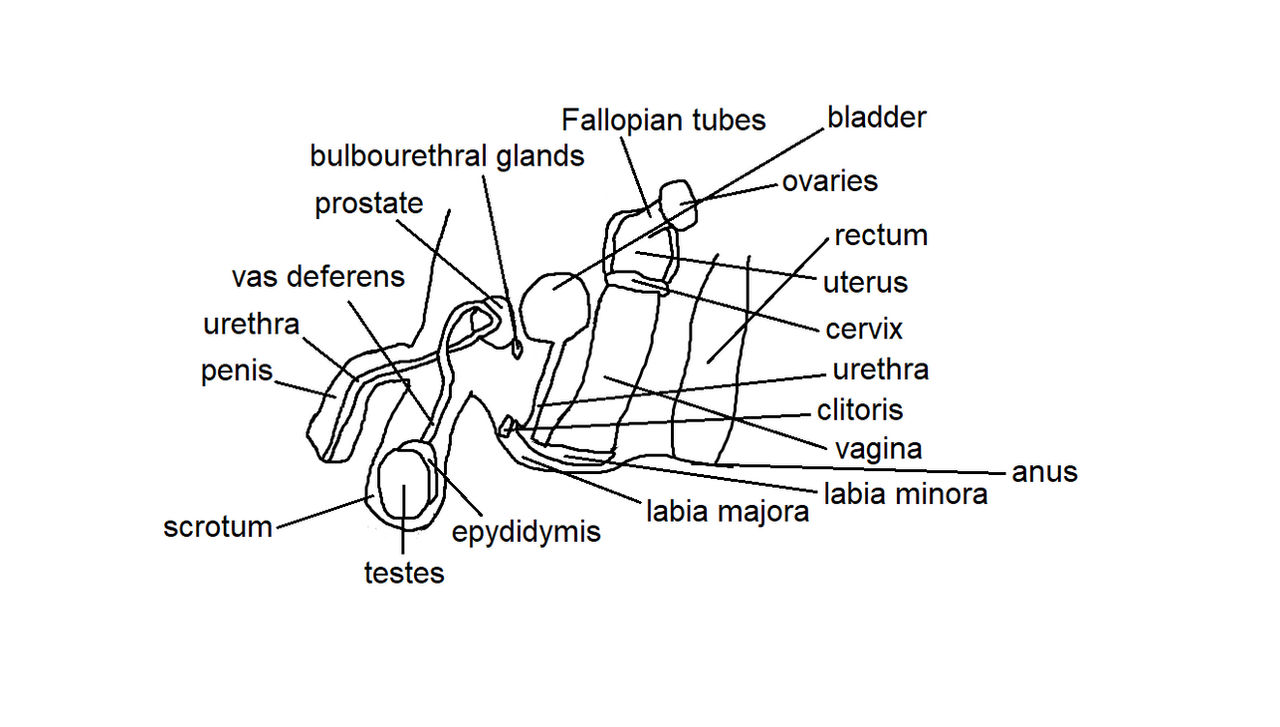
The term "hermaphrodite" is outdated and rarely used in modern medicine. Clinicians refer to these conditions as DSD — Disorders of Sex Development. Understanding Anatomy Of A Human Hermaphrodite requires going past the old textbook diagrams and looking at what actually presents in clinical practice. True hermaphroditism, now called ovotesticular DSD, is extremely rare. It affects roughly one in 2,500 to 1 in 8,000 births. The defining feature is the presence of both ovarian tissue and testicular tissue in the same individual. This might show up as one ovary and one testis, two mixed gonads, or a single ovotestis. Karyotypes vary. Some individuals are 46,XX — that is, the most common configuration found in ovotesticular DSD. Others may be 46,XY or mosaics like 45,X/46,XY. The chromosomal picture alone doesn't predict anatomy. You have to examine the actual gonads, the internal duct structures, and the external genitalia.
Internal anatomy depends on what hormone exposure happened during fetal development. If testicular tissue produced anti-Müllerian hormone (AMH), the Müllerian structures — fallopian tubes, uterus, upper vagina — may be partially or completely absent. If ovarian tissue dominated, those structures persist. Real-world presentations are rarely clean. I've seen cases where a patient had a functioning ovary on one side, a dysgenetic testis on the other, and a partially formed uterus with significant variation in the vaginal canal. The anatomy didn't match any diagram I'd ever studied.
Types of DSD and Their Anatomical Profiles
Beyond ovotesticular DSD, there are several categories that people commonly lump together under the old terminology. 46,XY DSD includes conditions like complete androgen insensitivity syndrome (CAIS). These individuals have testes — often undescended — and a 46,XY karyotype. Because their bodies don't respond to androgens, external genitalia develop along typical feminine lines. Internally, there's no uterus because AMH from the testes did its job. They have blind-ending vaginas. The gonads produce testosterone, which gets converted to estrogen, so puberty brings breast development without menstruation. 5-alpha-reductase deficiency is different. These are 46,XY individuals who can't convert testosterone to DHT. External genitalia may appear ambiguous at birth — enlarged clitoris, partial urethral fusion, palpable gonads in the labia. At puberty, the testosterone surge causes significant virilization. I worked with a patient who was raised female, presented at sixteen with deepening voice, increased muscle mass, and penile growth. The psychological and social implications of that transition were significant and required careful multidisciplinary support.
Get the Full Details

46,XX DSD encompasses congenital adrenal hyperplasia (CAH), which is by far the most common cause of ambiguous genitalia. In classic CAH, excess androgens from the adrenal glands affect female fetal development. External genitalia range from mild clitoromegaly to complete urethral and vaginal fusion. Internally, the reproductive tract is typically normal — ovaries, uterus, fallopian tubes all present. The adrenal issue is the real problem, and it's life-threatening if not managed.
Clinical Evaluation: What Actually Happens
When a baby presents with ambiguous genitalia, the workup follows a specific sequence. First, you rule out salt-wasting adrenal crisis — that's the emergency. Then you get karyotype or chromosomal microarray. Pelvic ultrasound checks for internal structures. Hormone panels include 17-hydroxyprogesterone, testosterone, DHT, LH, FSH, AMH, and cortisol. Gonadal biopsy may be necessary, especially if malignancy risk is a concern with dysgenetic gonads. Genital measurement matters. Penile length and phallic size are measured stretched, not flaccid. Perineoscrotal distance, presence of a single urogenital sinus, and degree of labial or scrotal fusion all factor into surgical planning. Prader staging, though criticized for oversimplification, is still used as a descriptive tool for external genitalia in 46,XX DSD. One thing beginners miss: the discordance between internal and external anatomy is the norm, not the exception. A patient might look externally female but have testes instead of ovaries. Or look male externally but have a uterus internally. Assuming one predicts the other leads to missed diagnoses. I once saw a case where a teenager was referred for "normal male development" but was actually living with complete androgen insensitivity and only discovered it during routine sports physical screening when no menstruation was reported. The gonadectomy was urgent due to malignancy risk in undescended testes.
Surgical Considerations and Controversies
This is where the field has changed dramatically. Historically, infant "sex assignment surgery" was standard. Normalize the anatomy early, the thinking went. Make it look typical so the child can have a normal life. That approach is now widely questioned. Multiple studies show that early non-consensual genital surgery on intersex children often causes loss of sensory function, scarring, stenosis, and psychological trauma. Patients report that the surgeries didn't deliver the expected outcome — they still required multiple revisions, still experienced reduced sensation, and still struggled with identity issues that surgery couldn't fix. The current standard, endorsed by organizations like the ESAIC and various pediatric endocrinology societies, favors deferring elective surgery until the patient can participate in consent. Medical management comes first. Hormone replacement is straightforward when needed. Surgical intervention is reserved for functional necessity — urinary tract obstruction, for example — or later, autonomous choice.
I've seen the aftermath of early surgeries that nobody bothered to document properly. A patient came to me in her thirties with chronic pelvic pain, recurrent fistulas, and complete loss of genital sensation from multiple childhood procedures. The operative reports were lost. She had no idea what had been done to her. That's not an uncommon story.
Fertility and Reproductive Potential
Fertility varies enormously by DSD type. In ovotesticular DSD, pregnancy has been reported, mostly through the ovarian component. Cases exist of successful pregnancies in 46,XX CAH patients with intact uteri. In 46,XY DSD with complete androgen insensitivity, fertility is not possible — no uterus, no ovaries. In 5-alpha-reductase deficiency, fertility potential is unclear but likely limited. Gonadal malignancy risk is a real concern, particularly in dysgenetic gonads and in CAIS where undescended testes carry an estimated 5-10% risk of germ cell tumors over a lifetime. Prophylactic gonadectomy after puberty is sometimes recommended to allow natural puberty to occur first, then remove the risk. The timing is individualized.
Psychosocial Dimensions
The psychological impact of DSD is substantial and often underaddressed. Gender identity in DSD individuals doesn't always align with their assigned sex. Studies suggest that a small but significant percentage of individuals assigned female with 46,XY DSD identify as male later in life. Conversely, some with 46,XX DSD assigned female maintain that identity. The key insight is that early surgical intervention doesn't prevent gender dysphoria. It may actually worsen it by removing agency and bodily autonomy. Patients who weren't operated on infantly and were given information and support tend to report better psychological outcomes, even when their anatomy was initially ambiguous. Support networks matter enormously. Connecting patients and families with organizations like the Intersex Society or similar groups reduces isolation and provides practical navigation advice that clinicians often can't offer. The medical community has been slow to recognize this, and that gap is starting to close.
Key Takeaways for Clinical Practice
Diagnosis requires a multidisciplinary approach — endocrinology, genetics, urology, gynecology, psychology, and ethics. No single specialist has the full picture. Hormone replacement is essential when gonadal function is insufficient. Surgery should be functional, not cosmetic, and deferred whenever possible. Documentation is critical — so many patients have no record of what was done to them. And the language matters. "Hermaphrodite" is offensive to most intersex adults. Use "DSD" or "intersex" unless the patient specifies otherwise.