What You're Actually Looking At
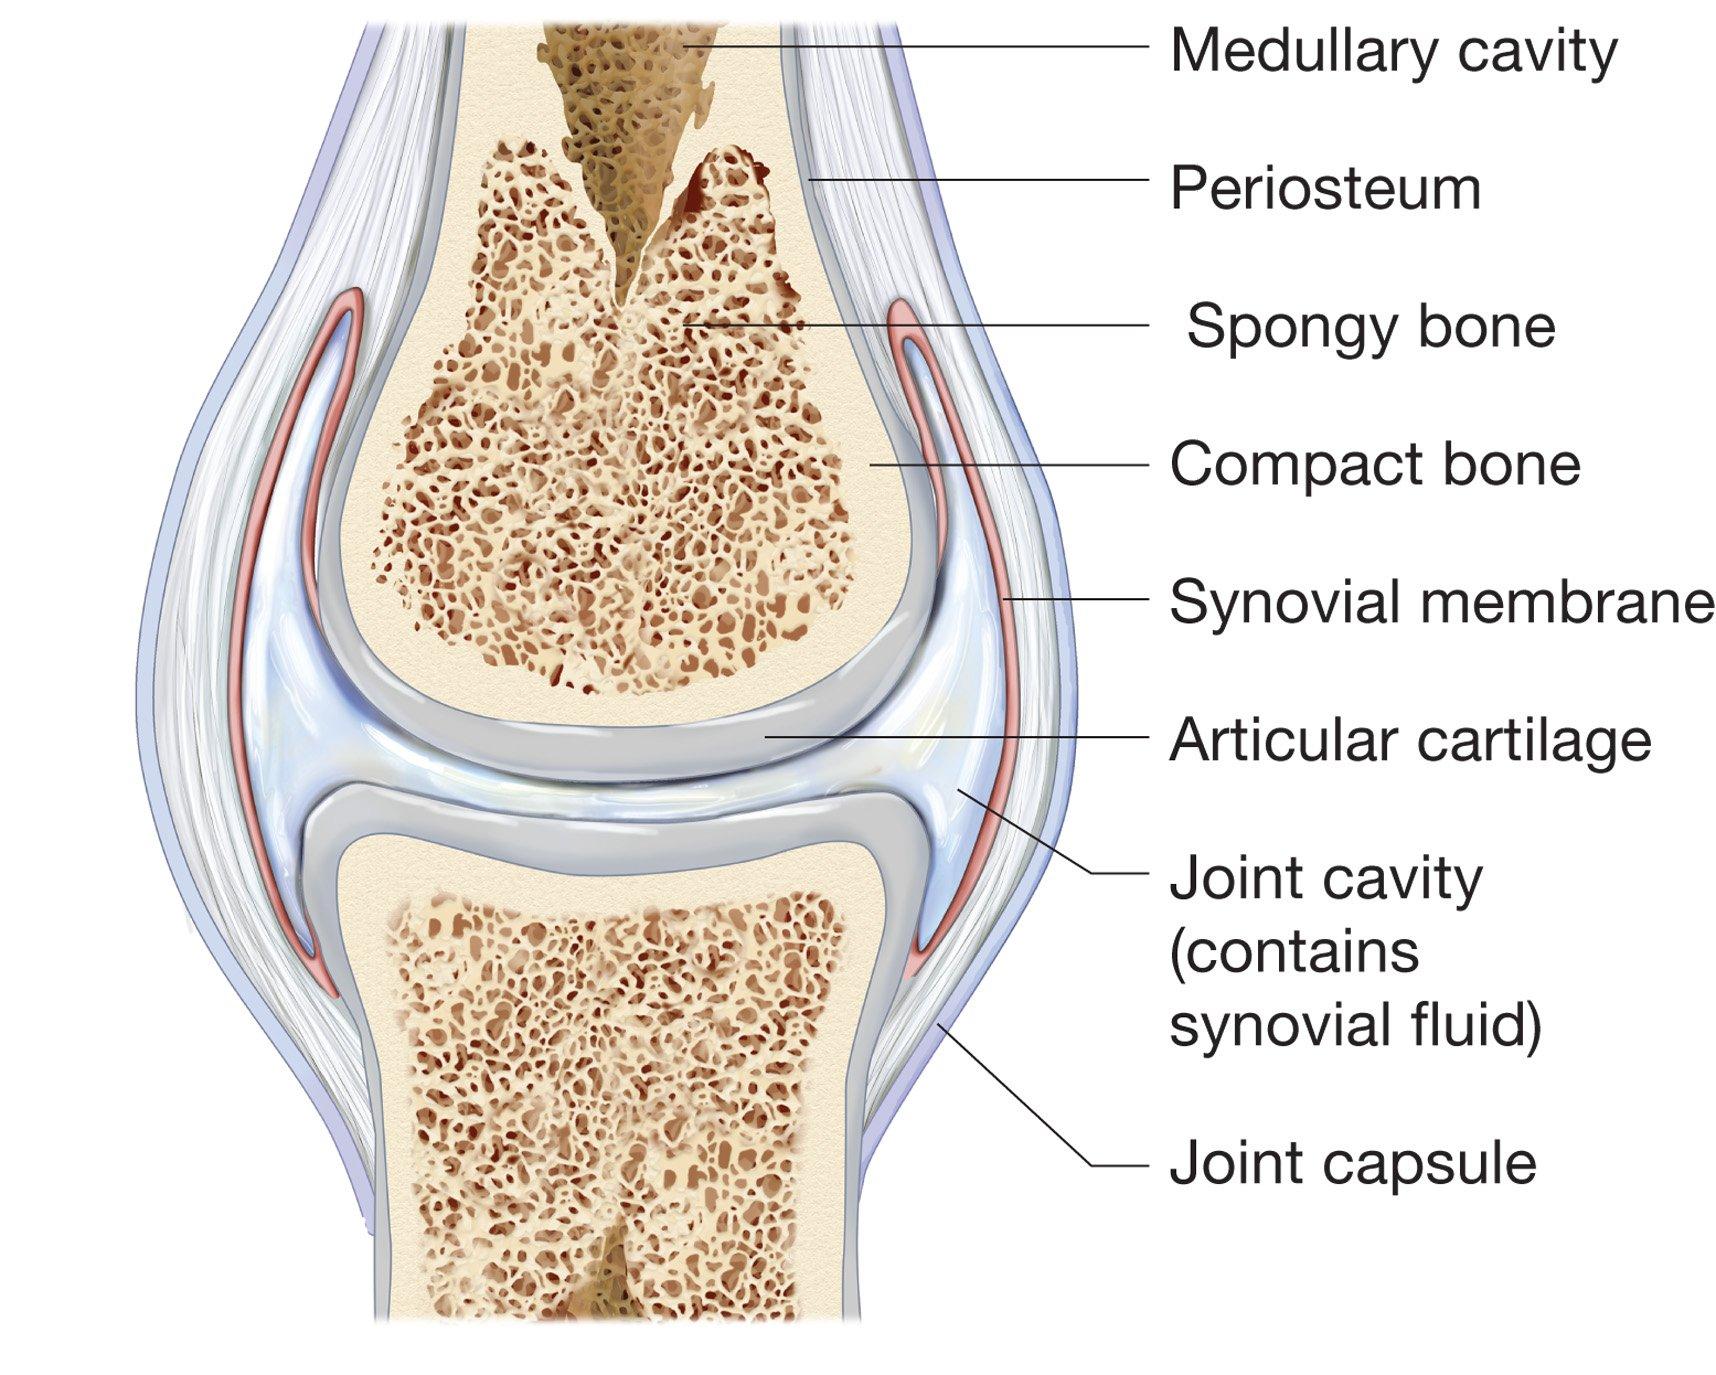
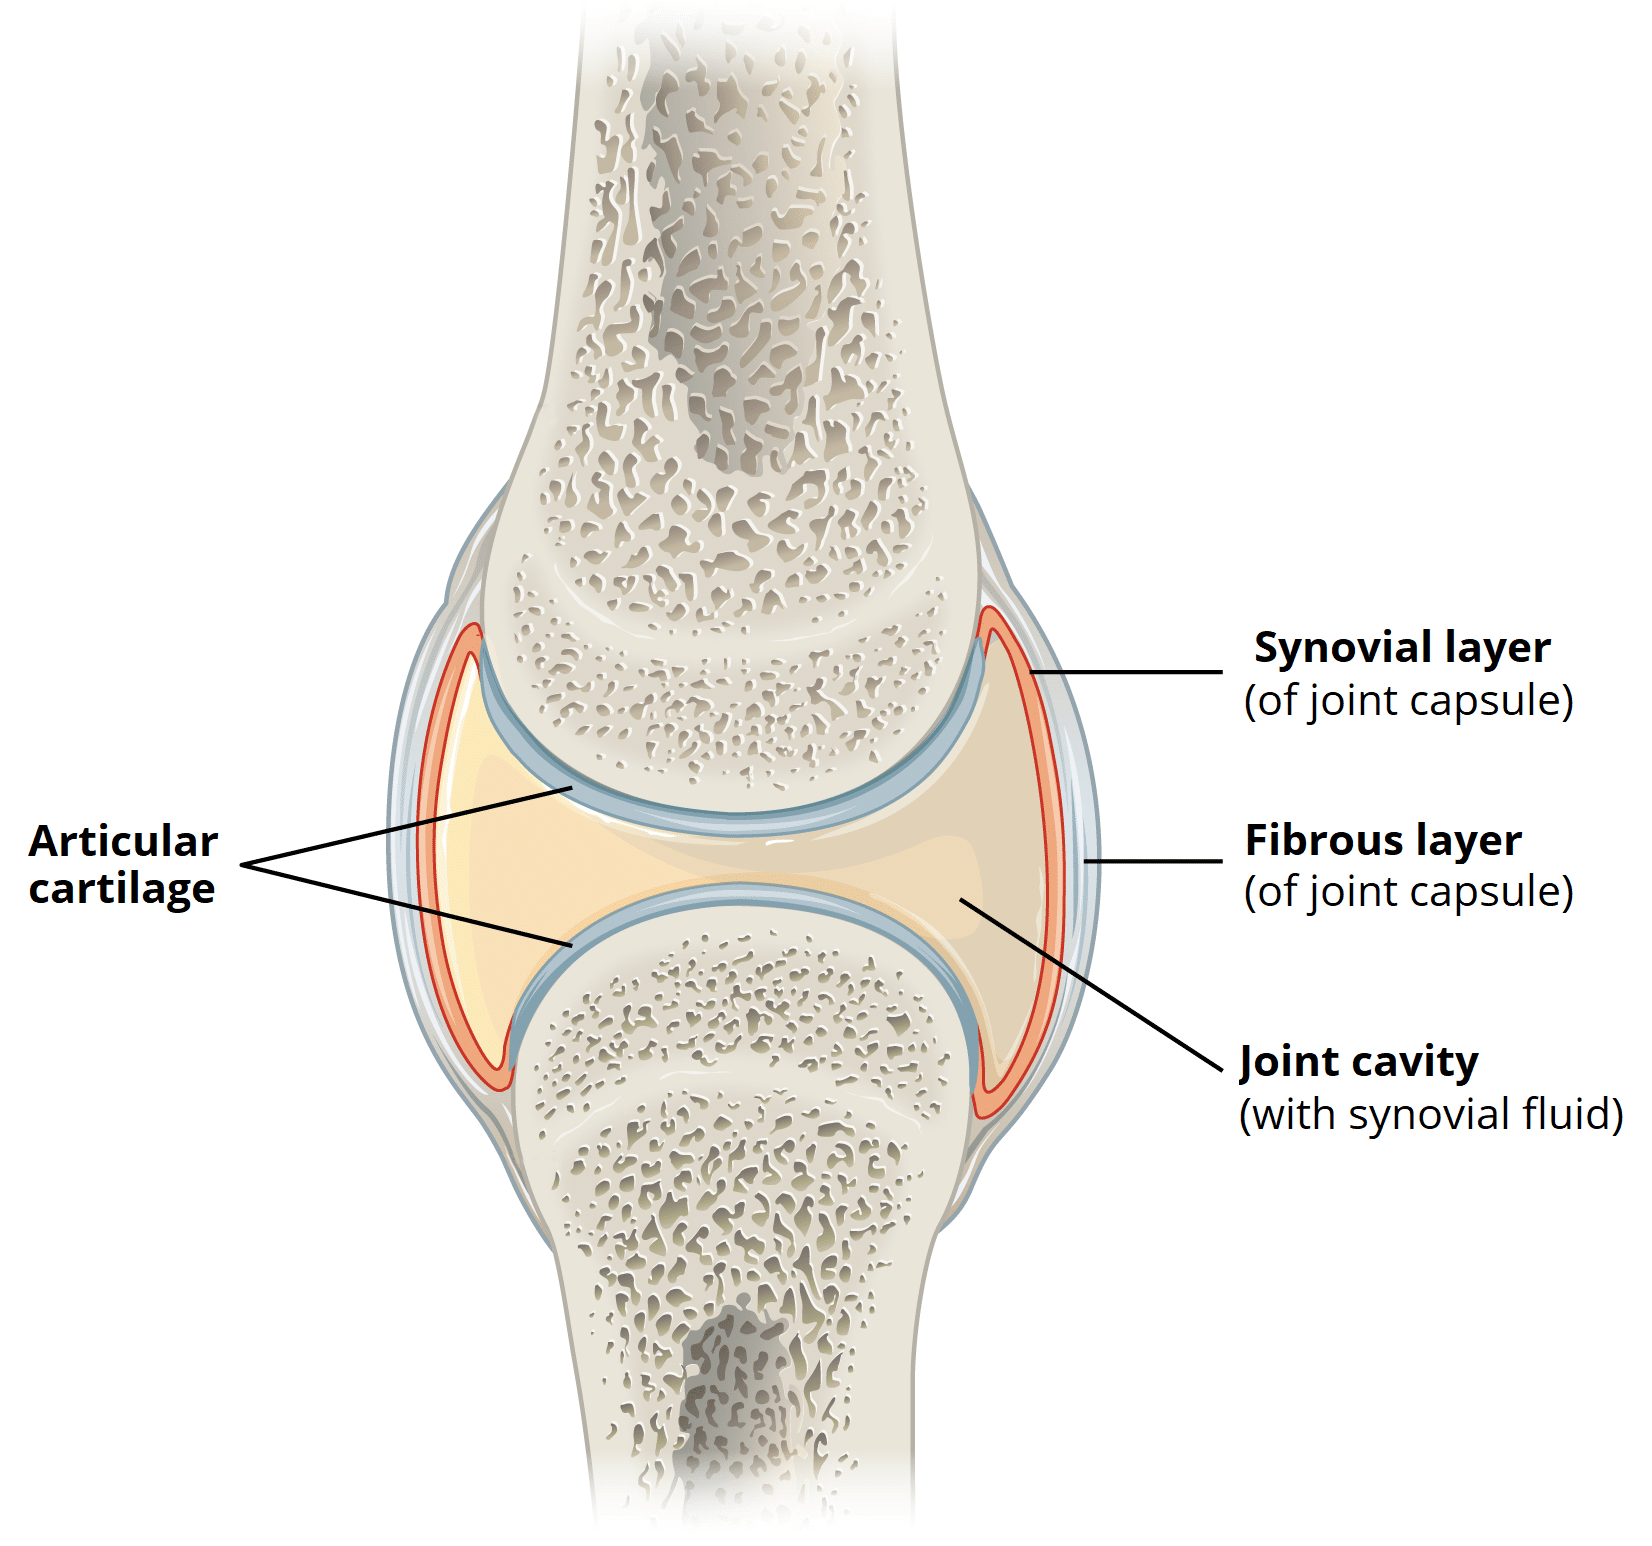
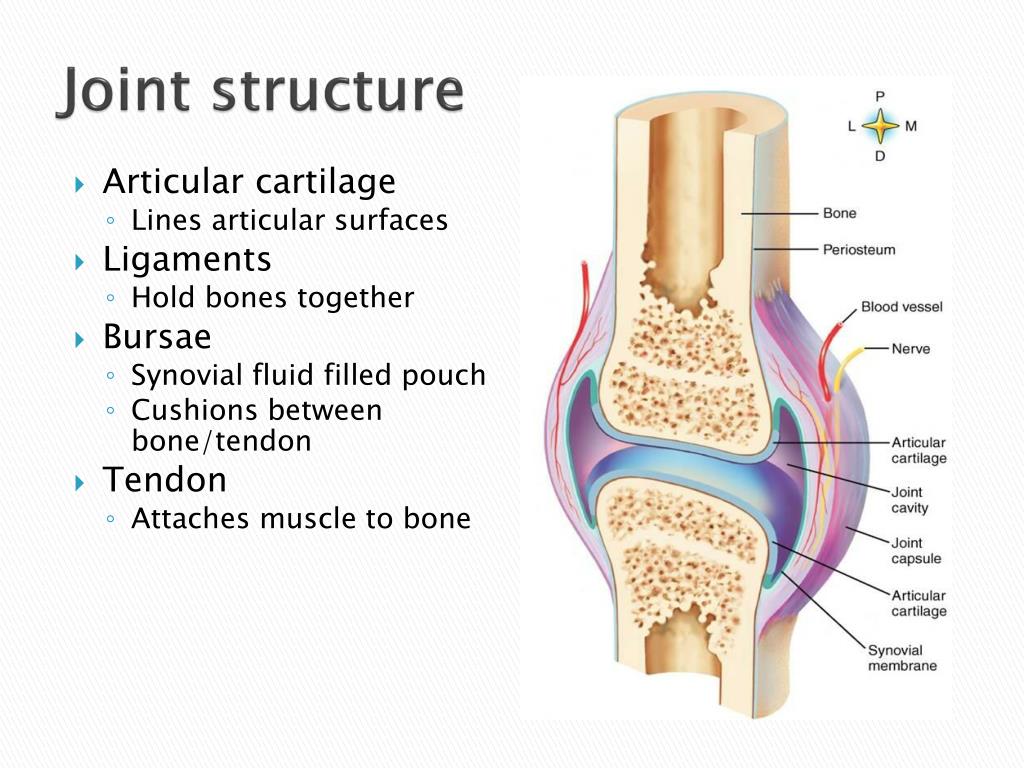
When you open an anatomy textbook to a diagram of a synovial joint, you get this clean, colored illustration that makes it look simple. The reality is messier. I spent years working with cadaver specimens before I actually understood what I was looking at, and even now when I pull up a fresh knee on the dissection table, something still catches me off guard. The structure itself follows a predictable pattern. Two bone ends meet. Between them sits articular cartilage, which is hyaline cartilage thinned to roughly one to three millimeters in most load-bearing joints. The joint cavity contains synovial fluid, a viscous, egg-white-like substance produced by the synovial membrane lining everything except the cartilage surfaces. Wrapped around it all is the fibrous joint capsule, which in some joints like the shoulder is loose enough to allow enormous range of motion and in others like the hip is thick and tight to maintain stability under massive loads.Anatomy Of A Synovial Joint: What Beginners Miss
The most common mistake people make when studying synovial joints is treating the ligaments as the primary stabilizers. That is only partially true. In many joints, particularly the knee, the ligaments are secondary restraints. The real first-line stabilizers are the capsule itself and the muscle forces crossing the joint. I remember spending an entire lab session trying to identify why a particular knee specimen kept falling apart during manipulation, only to realize we had accidentally damaged the oblique popliteal ligament complex during previous dissections. Without those fibers, the posterior capsule goes slack and everything feels looser than it should be, which threw off our assessment of the actual ligament integrity. Another thing nobody tells you until you've actually worked with these specimens: the synovial membrane is not a continuous sheet. It has folds, recesses, and septa that vary enormously between joints. The suprapatellar recess in the knee can distend to hold significant effusion, which is why clinical exams look for that particular bulge. In the hip, the synovial lining reflects differently around the ligamentum teres, creating a potential space that can fill with fluid in pathological conditions.The menisci in the knee are technically modified synovial structures, but you will often see them described as separate entities. They are fibrocartilaginous pads that deepen the tibial plateau and distribute load. The medial meniscus is firmly attached to the deep portion of the medial collateral ligament, which is why medial meniscal tears are more common and harder to heal. The lateral meniscus has that characteristic W-shaped configuration and is much more mobile. This difference in mobility matters when you're trying to understand why one tears more frequently under certain loading conditions.
What The Cartilage Actually Does
Articular cartilage is avascular, meaning it gets no direct blood supply. Nutrients diffuse through the cartilage matrix from the synovial fluid. This is why joint movement is so important for cartilage health. Without compression and decompression cycles, the fluid doesn't move through the matrix effectively, and the chondrocytes starve. I have seen young athletes with normal X-rays who developed diffuse cartilage thinning within months after prolonged immobilization following a minor injury, simply because the nourishment mechanism was disrupted. The cartilage itself has four histological zones. The superficial zone has tangentially arranged collagen fibers and flattened chondrocytes, providing a smooth wear surface. The middle zone has randomly oriented fibers and more spherical cells, handling shear forces. The deep zone has perpendicular collagen bundles anchoring into the calcified cartilage layer, which then anchors into the subchondral bone through the tidemark. The radially organized fibers in this deepest layer resist compressive forces during weight bearing.If you are palpating a joint clinically or examining imaging, understanding these zones matters because degenerative changes typically begin in the superficial layer. The fibrillation you see in early osteoarthritis starts as vertical clefts that propagate downward through these layers over time. Once the calcified layer is breached, the progression accelerates because the structural anchor is compromised.
The Synovial Fluid Question
Synovial fluid contains hyaluronic acid, which gives it its viscosity, and lubricin, which reduces friction at the cartilage surface. The fluid's lubrication properties are shear-thinning, meaning it becomes less viscous under the high-shear conditions of active movement. This is counterintuitive if you think of it like motor oil. The fluid actually flows better exactly when you need it to flow better. I once worked with a rheumatology team evaluating a patient whose joint aspirations consistently returned fluid that looked normal grossly but had abnormally low hyaluronic acid concentration under analysis. The standard macroscopic exam missed it entirely. The patient had significant pain and swelling despite what appeared to be normal synovial fluid on basic inspection. This is a practical example of why you cannot rely solely on visual assessment of synovial fluid. The lubrication quality is invisible without specific biochemical testing.Capsule And Ligament Architecture
The fibrous capsule is composed of dense irregular connective tissue with two layers. The outer fibrous layer provides structural integrity and contains mechanoreceptors that contribute to proprioception. The inner synovial membrane layer produces the fluid and contains the vascular network that supplies the cartilage peripherally. Ligaments within synovial joints are not uniform. Some are thickened portions of the capsule itself, like the iliofemoral ligament of the hip, which is sometimes called the Y-ligament of Bigelow because of its shape. Others are distinct separate bands, like the anterior cruciate ligament, which has a separate blood supply and innervation pattern from capsal ligaments. This distinction matters surgically. ACL grafts have different healing characteristics and proprioceptive restoration compared to capsal repair because the native ligament was architecturally different.One specific edge case I encountered involved a patient with medial knee instability who tested negative on standard valgus stress imaging. The instability only manifested under dynamic conditions where the gastrocnemius was actively contracting. The medial head of the gastrocnemius has a direct capsal attachment that can provide dynamic medial stability when the muscle is active. When it was relaxed during static imaging, the joint appeared stable. When the patient walked or ran, the lack of sufficient static medial capsule integrity became apparent because the muscular compensation was absent. The workaround was functional MRI and dynamic ultrasound rather than standard static imaging, which caught the instability that routine protocols missed entirely.
Get the Full Details
Functional Considerations
The classification of synovial joints by their shape and degrees of freedom is useful for basic understanding but falls apart when you examine actual human movement. A hinge joint like the elbow allows primarily flexion and extension, but there is a small amount of axial rotation that occurs during the last twenty degrees of extension, which is the close-packed position unlocking mechanism. You will not find this described adequately in introductory diagrams. Ball-and-socket joints like the shoulder and hip have fundamentally different stability requirements despite similar geometry. The glenohumeral joint has a shallow glenoid fossa and relies heavily on the rotator cuff muscles and capsal tension for stability. The hip has a deep acetabulum with a labrum that increases concavity, and the ligamentum teres, while not a major stabilizer in adults, still contributes to proprioceptive feedback. These anatomical differences explain why shoulder dislocations are common and hip dislocations require significant force.What The Joint Capsule Tells You About Movement
The orientation of collagen fibers in the capsule changes with joint position. In the loose-packed position, the capsule is at its most redundant, which is why joint mobilization techniques target this position for therapeutic intervention. In the close-packed position, the fibers become taut and the joint surfaces are maximally congruent. For the knee, this is full extension with slight external rotation of the tibia. For the hip, it is full extension with slight external rotation and abduction. The capsule also contains specialized structures called bursae, which are synovial-lined sacs that reduce friction between the capsule and overlying structures. These can become inflamed independently of the joint itself, which is why pain localization in synovial joints is frequently inaccurate. Subacromial bursitis mimics shoulder joint pathology almost perfectly because the pain referral patterns overlap substantially.One detail that comes up repeatedly in practice is the relationship between the joint capsule and nearby nerves. The posterior capsule of the hip is innervated by branches of the sciatic nerve, which means pathology in that region can refer pain down the leg in patterns that mimic radiculopathy. I had a patient who presented with what appeared to be L5 radiculopathy based on pain distribution and neurological examination, but the straight leg raise was negative and the specific provocative tests pointed elsewhere. The actual source was posterior hip capsulitis from an intra-articular labral tear, not a spinal issue. Misdiagnosis in these cases is extremely common because the referral patterns are unreliable.
Pathology And Practical Implications
Osteoarthritis is not simply wear and tear. The current understanding involves inflammatory mediators, matrix metalloproteinases, and altered mechanotransduction pathways within the chondrocytes. The cartilage breakdown is an active biological process, not a passive mechanical one. This distinction matters because treatments targeting only inflammation or only mechanics address only part of the problem. Rheumatoid arthritis specifically targets the synovial membrane first, causing pannus formation that eventually erodes cartilage and bone. The synovium in RA becomes hypertrophic and vascularized, which is why MRI with contrast can detect early disease before structural damage appears on X-ray. Standard radiographs are insensitive to early synovitis, which means patients often go months or years without accurate diagnosis.The blood supply to synovial joints varies significantly between joints and has major implications for surgical and therapeutic approaches. The hip joint has a tenuous blood supply to the femoral head in adults, with the artery to the ligamentum teres contributing minimally after skeletal maturity. Dislocations or fractures that disrupt the medial circumflex femoral artery can lead to avascular necrosis within weeks. The knee has a richer vascular supply around the capsule, but the ACL has poor intrinsic healing capacity because it lacks a robust synovial covering along much of its length, which is why surgical reconstruction is often necessary rather than conservative management alone.