How the Quadrant System Actually Works in Clinical Practice
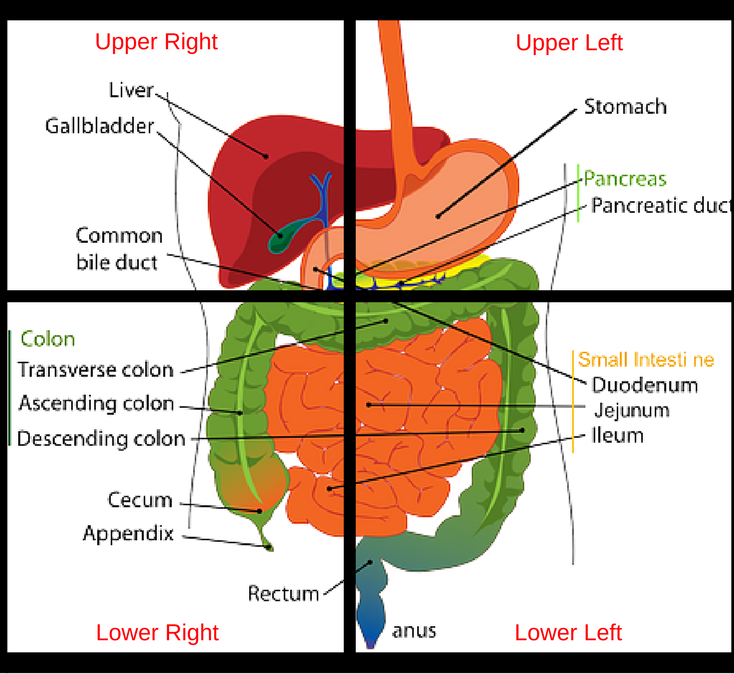
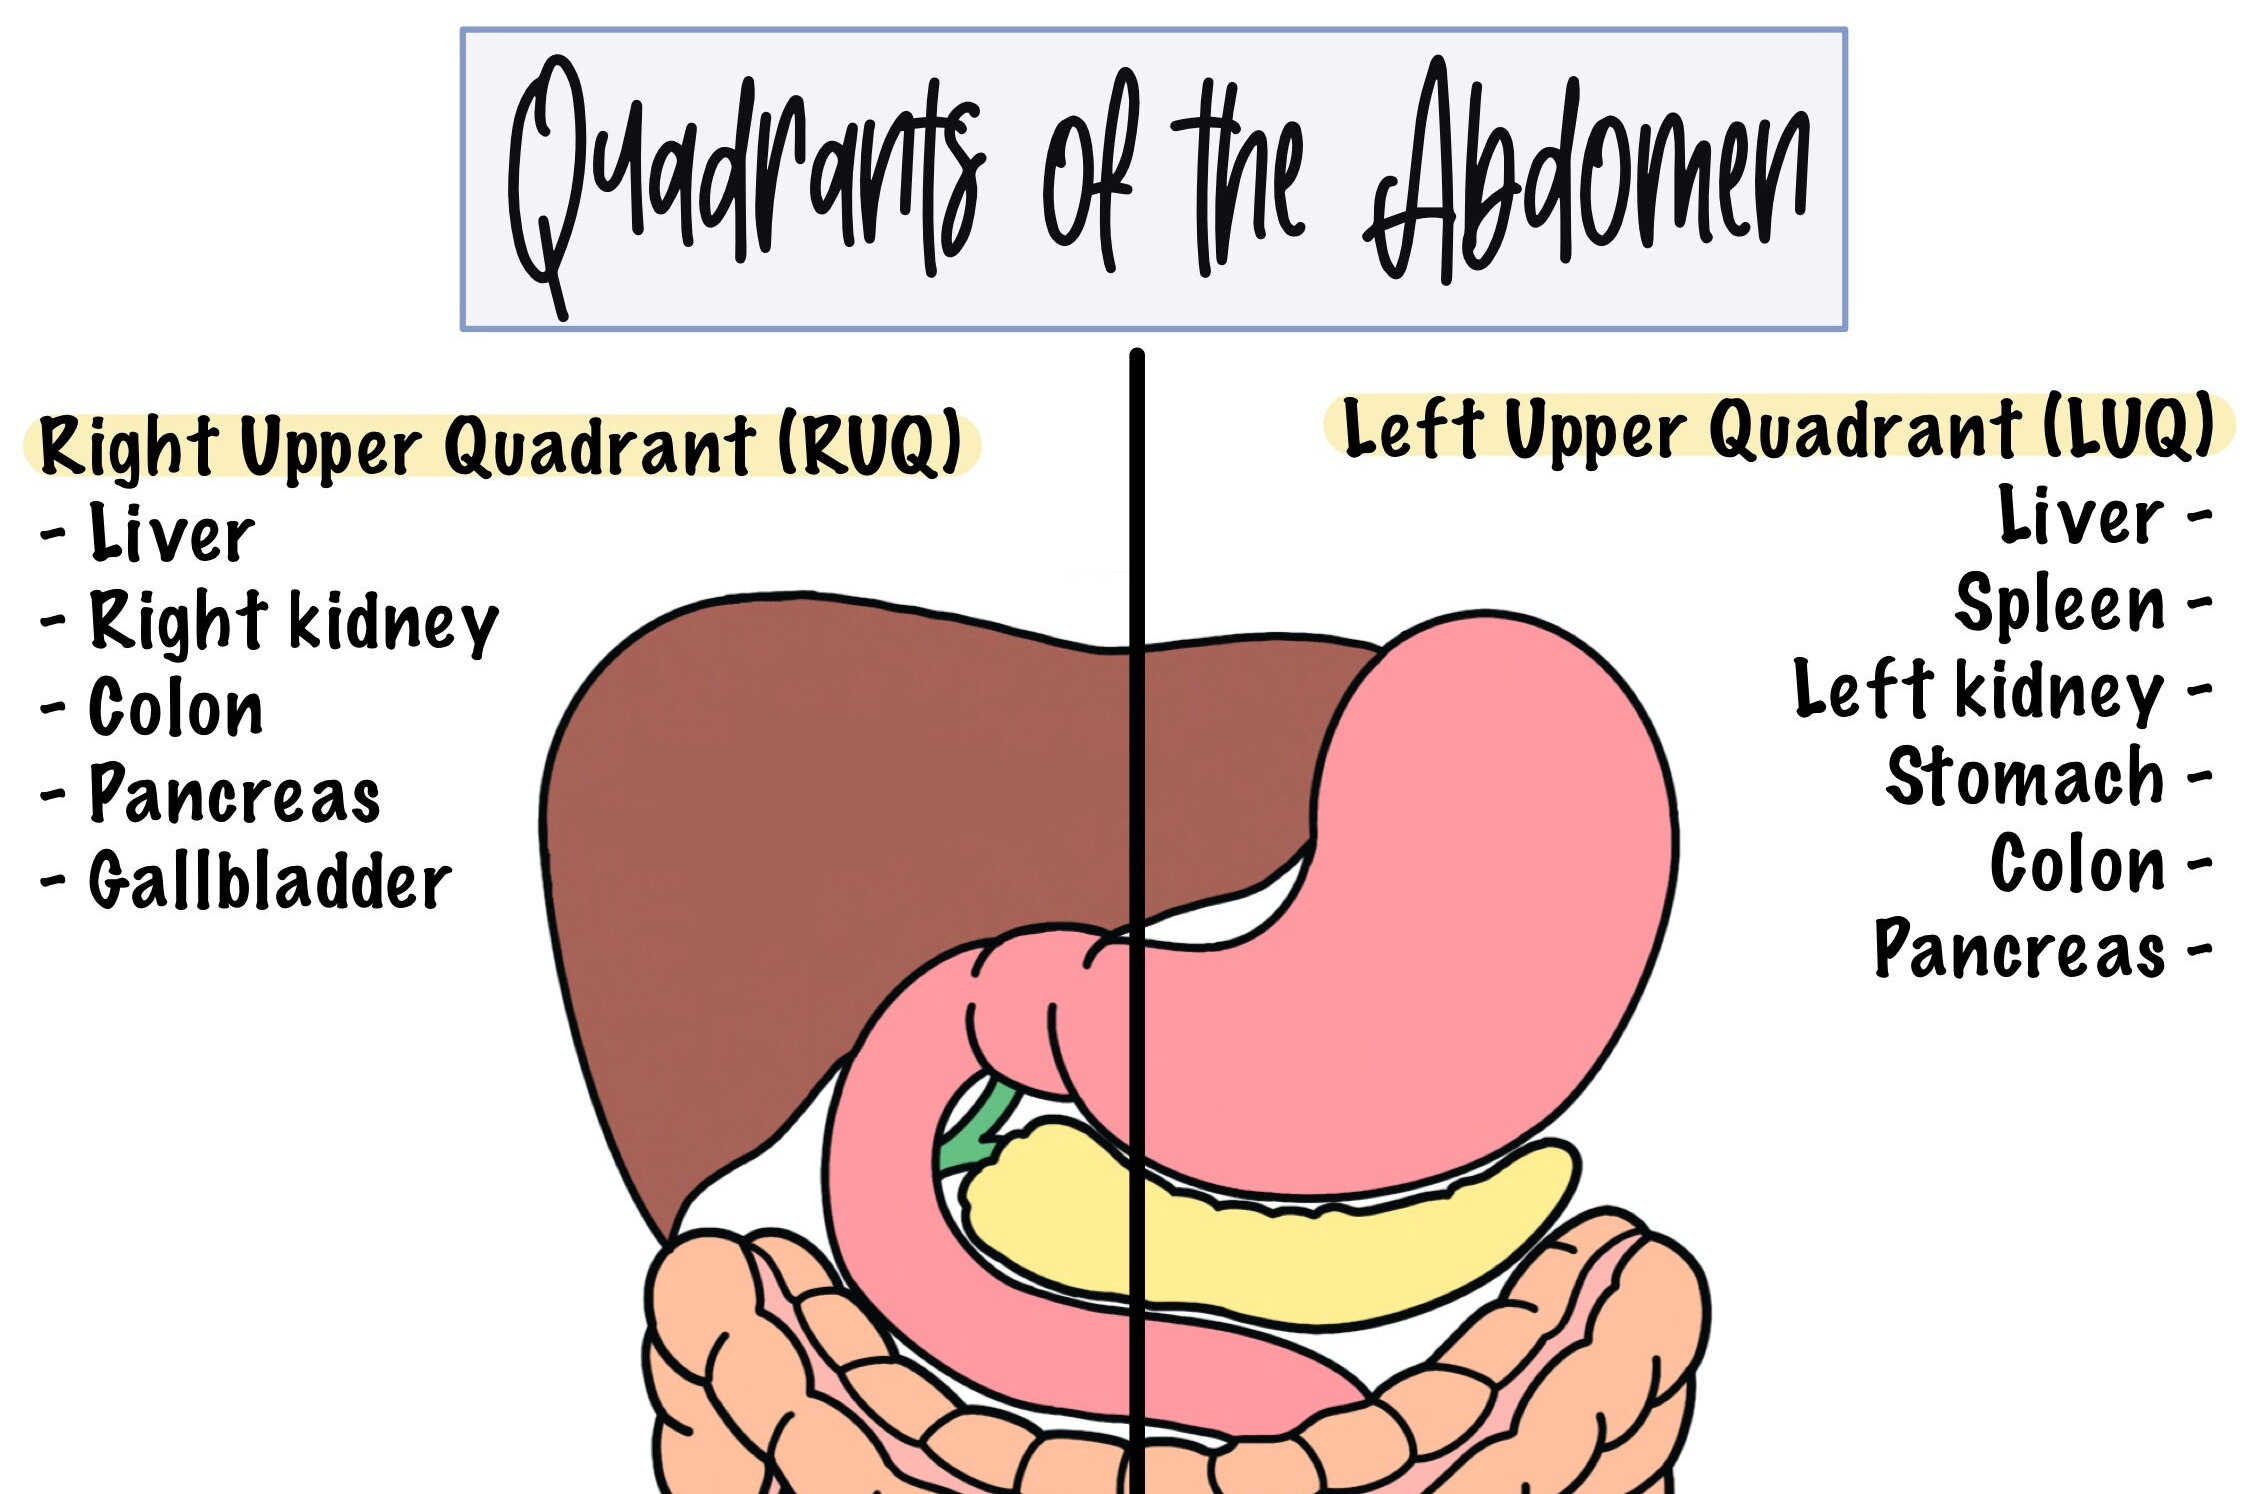
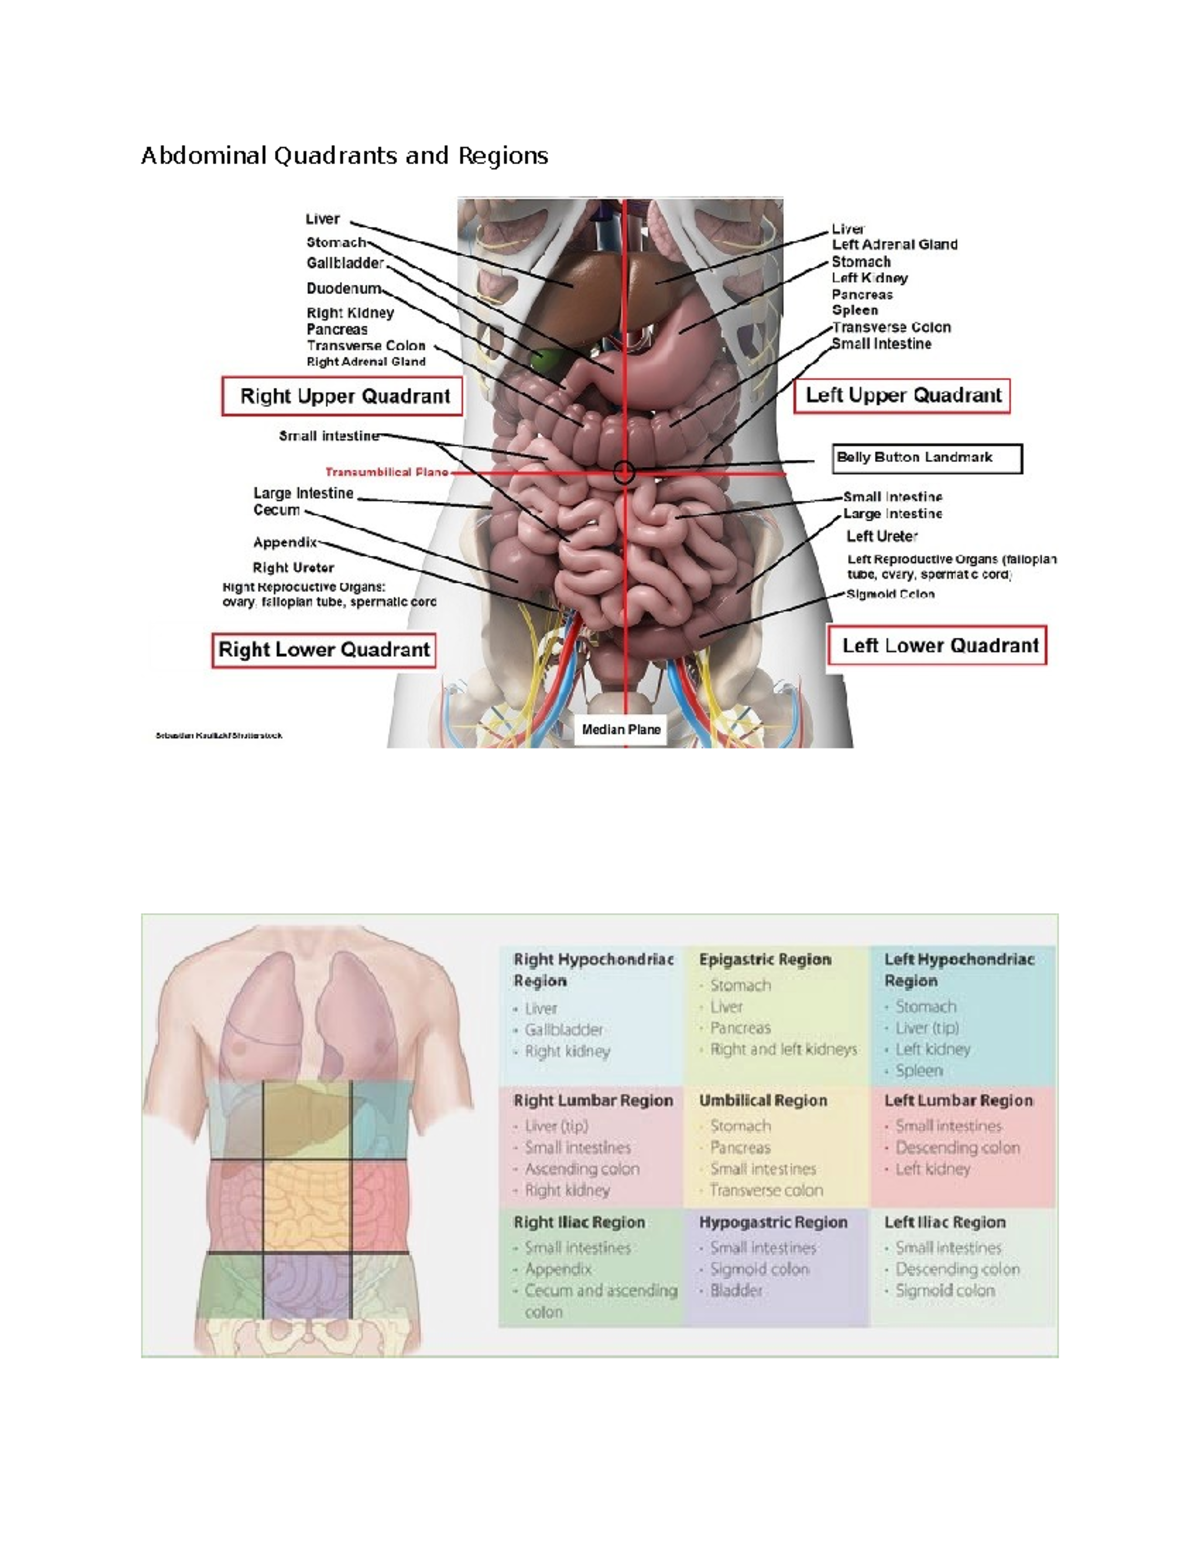
The four-quadrant method is one of those foundational anatomy frameworks that gets taught in every first-year med program and then quietly abandoned by anyone who works in clinical settings. It divides the abdomen using two imaginary planes — the midline and the transumbilical plane — creating right upper, left upper, right lower, and left lower quadrants. Simple enough. The problem is that the real anatomical relationships don't always line up neatly with those perpendicular lines, and relying on the quadrant system without understanding its blind spots will get you in trouble. Each quadrant maps to specific organs, but the mapping isn't as clean as the diagrams suggest. The right upper quadrant contains the liver, gallbladder, right kidney, hepatic flexure of the colon, and part of the duodenum. The left upper quadrant holds the stomach, spleen, left kidney, splenic flexure, pancreatic tail, and the body/tail of the pancreas. The right lower quadrant contains the appendix, cecum, terminal ileum, right ovary and fallopian tube, and the right ureter. The left lower quadrant has the sigmoid colon, left ovary and fallopian tube, and left ureter. Most textbooks list these and move on. They rarely mention that the appendix can sit anywhere from the pelvis up to the subhepatic space, which means RLQ pain doesn't always mean appendix. I spent a few years working in emergency medicine where we used the quadrant system daily for triage and documentation. One case I still remember clearly involved a patient who presented with what looked like classic RLQ pain — rebound, guarding, point tenderness at McBurney's point. By every textbook standard, this was appendicitis until proven otherwise. We prepped for surgery, but intraoperatively the appendix looked completely normal. Turns out the patient had an inflammatory mass in the cecal pole from a perforated epiploic appendagitis, a condition that mimics appendicitis almost perfectly on physical exam and even on basic ultrasound. The quadrant system pointed us in the right general direction, but it wouldn't have saved us from that misstep on its own. We switched to CT imaging after the initial ultrasound was equivocal, which caught it. That experience made me never trust the quadrant system as a standalone diagnostic tool, even though it remains useful for initial localization and communication between providers.
The transumbilical plane sits roughly at the L4 vertebral level in most adults, but that's an approximation. Body habitus shifts things considerably. In obese patients, the umbilicus sits lower, and the plane ends up over the sacral promontory rather than L4. In pregnant patients, the expanding uterus pushes everything upward and anteriorly, rearranging the quadrant contents entirely. A gravid uterus can displace the appendix from the RLQ up into the RUQ by the third trimester, which is why Appendicitis in pregnancy is often missed — the pain presents in the wrong quadrant relative to the textbook description. There's also the issue of organ mobility. The kidneys are retroperitoneal and mobile enough to shift position with respiration and body habitus. The liver is relatively fixed but can be hepatomegalic, pushing boundaries well beyond the typical quadrant map. The small bowel is intraperitoneal and moves constantly. So when you're localizing tenderness to a quadrant, you're essentially taking a snapshot of a dynamic system and freezing it into a static category. Another practical issue is interobserver variability. Two clinicians examining the same patient can reliably assign tenderness to different quadrants if they're using slightly different plane landmarks. The midline is straightforward — it's the linea alba. But the transumbilical plane depends on identifying the umbilicus, which is a surface landmark that doesn't always correspond to the underlying anatomical level. Some practitioners use the intercristal plane (connecting the iliac crests) as a proxy, which corresponds to L4, but that's a different horizontal line than the transumbilical plane in most people. This inconsistency matters when you're documenting findings or handing off a patient between shifts. A "LUQ mass" documented by one provider might actually be more midline or more superior depending on which plane they used.
When the Quadrant System Fails You
Pain referral patterns don't respect quadrant boundaries. A posterior penetrating duodenal ulcer can refer pain to the back and present primarily in the RUQ or even the epigastrium, but it might not cause anterior tenderness in any quadrant until peritonitis develops. Myocardial infarction can present as epigastric or RUQ discomfort, particularly in diabetic or elderly patients. Biliary colic from gallstones typically localizes to the RUQ but can radiate to the right scapular region or present as mid-epigastric pain. Pancreatitis usually causes epigastric pain that bores through to the back, straddling the midline and defying quadrant categorization altogether. The system also breaks down for retroperitoneal pathology. Kidney stones, pancreatic tumors, and abdominal aortic aneurysms are retroperitoneal and often don't produce the localized peritoneal signs that quadrant-based assessment relies on. An AAA can cause vague mid-abdominal discomfort that doesn't fit cleanly into any quadrant. A renal colic patient might have flank pain that wraps from the posterior costovertebral angle to the groin, crossing quadrant boundaries horizontally. In these cases, the quadrant system adds noise rather than signal. For learning and examination purposes, the four-quadrant system is adequate. It gives students a scaffold to organize their knowledge of abdominal anatomy and provides a common language for initial clinical communication. But in practice, it's more useful to think in terms of regions and zones — the epigastrium, hypochondria, flanks, suprapubic area, and the actual organ-level relationships. The nine-region system (right hypochondriac, epigastric, left hypochondriac, right lumbar, umbilical, left lumbar, right iliac, hypogastric, left iliac) is more precise but considerably more tedious to use at the bedside. Most clinicians I know settle on a hybrid approach: they use quadrants for initial assessment and documentation, then refine their thinking anatomically as they gather more data from history, labs, and imaging.
Get the Full Details

The takeaway isn't that the quadrant system is useless. It's that it's a starting point, not a conclusion. Learn it thoroughly, memorize the organ mappings, use it for communication and initial localization, but never let it replace a thorough abdominal exam or the willingness to consider pathology outside the expected quadrant boundaries. The abdomen doesn't care about your diagrams.