So You Need to Know the Anatomy Of Anterior Teeth
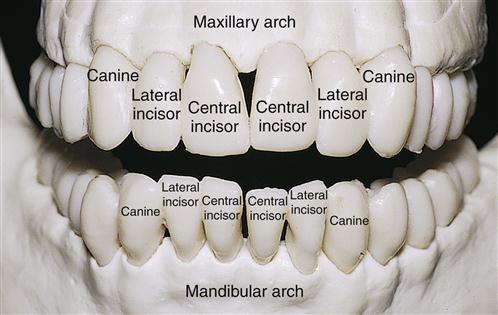
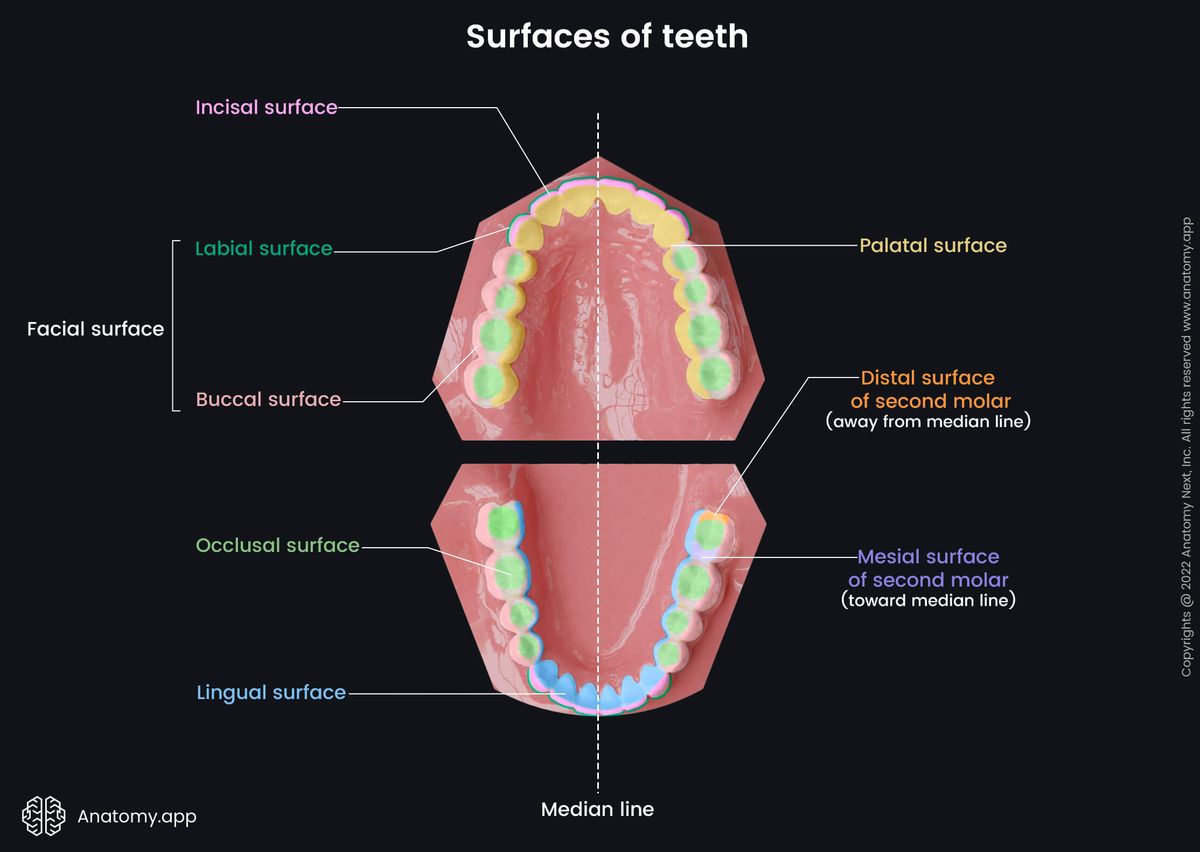
It is not complicated, but it is easy to get wrong if you just go by a diagram. I have spent years working with anterior teeth, and the first thing you need to understand is that every tooth is different. Not just between teeth, but between individual patients. A textbook diagram will get you 80 percent there, but the other 20 percent is where mistakes happen and restorations look fake or fail functionally. Anterior teeth include incisors and canines. The central incisor has a relatively straight mesial outline with a rounded distal incisogingival dimension. The lateral incisor is smaller, often with more convexity on the distal aspect, and the cingulum tends to sit more palatally. Canines are where things get interesting because they have the longest root in the anterior region and the most pronounced labial curvature. The mesial contact area of central incisors sits at the incisal third, usually near the incisal edge. The distal contact is slightly more cervical, closer to the junction of the incisal and middle thirds. This difference in contact position is what gives the smile line its natural variation. If you place both contacts at the same level, the tooth looks symmetrical and artificial.
Lingual anatomy is where most people cut corners. The cingulum is not a bump you add on top of a flat surface. It has volume, it has relief, and it determines how the tongue interacts with the restoration. In anterior crowns, if you flatten the lingual surface to save time or materials, you lose retention for the wax-up and you alter phonetics. Patients will tell you the tooth feels wrong before they can articulate why. The labial surface follows a convex curve from the cervical line to the incisal edge. But the cervical line itself is not flat. It curves apically toward the root, following the cementoenamel junction. On central incisors, the CEJ curves about 2 to 3 millimeters incisally on the mesial and slightly more on the distal. This curvature is easy to miss when you are looking at a flat study model or a 2D image. Proximal contacts are two-dimensional points in a three-dimensional space. When you are preparing a tooth for a crown, the finish line has to match the contour of the root surface underneath. A common mistake is prep the axial wall too flat, then trying to build up the restoration with bulk material. The result is either a weak margin or an overcontoured crown that irritates the gingiva.
What Actually Matters in Clinical Practice
I ran into a case last year involving a maxillary lateral incisor that had significant rotation pre-restoration. The tooth was torqued labially, which meant the proximal contacts were not aligned with adjacent teeth the way they are in a standard model. When I tried to use a generic wax pattern, the contacts were off by nearly a millimeter. The crown would not seat without excessive force, and even then the margin was open mesially. The workaround was straightforward but required extra time. I took a direct intraoral scan of the prepared tooth before waxing, then used that scan as the reference for building the wax pattern. This way, the contacts matched the actual emergence profile of the prepared tooth rather than some textbook approximation. The crown fit on the first try. Without the scan, I would have spent at least forty-five minutes adjusting the margins and proximal surfaces at the chairside. Root form matters more than you think. Two teeth that look identical from the facial can have completely different root shapes when viewed from the proximal. A maxillary canine with a flattened distal root surface will have a different emergence pattern than one with a rounded root. This affects how much reduction you need and how the final crown will support the papilla between teeth.
Get the Full Details
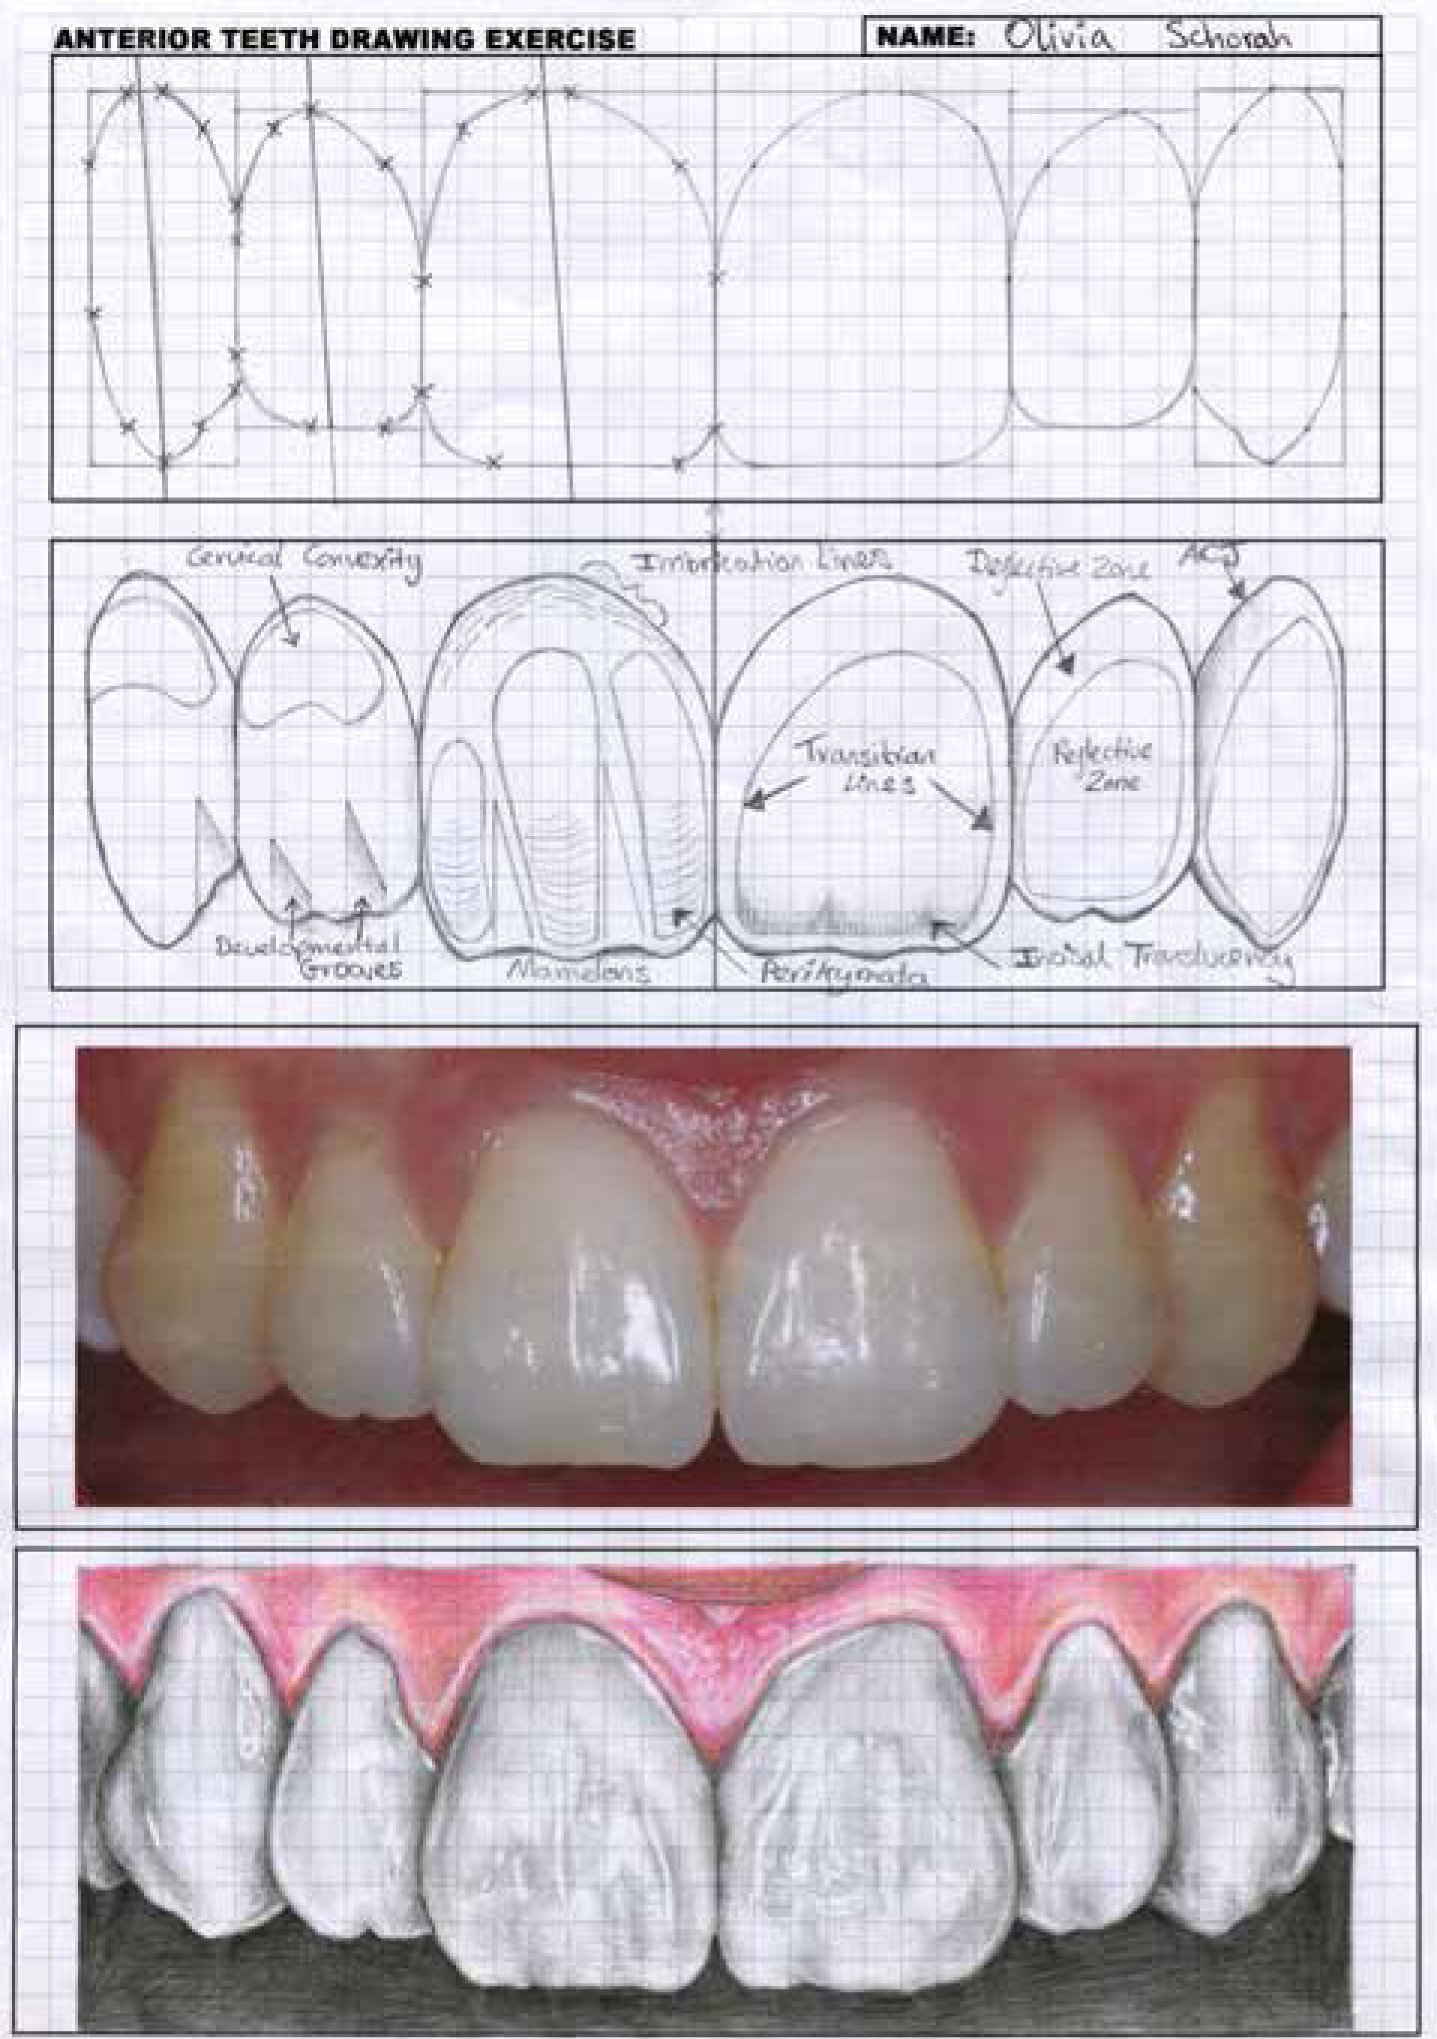
Surface texture is another thing that gets ignored. Smooth, glazed porcelain on an anterior crown looks plastic under certain lighting. Natural enamel has microscopic texture variations, especially on the incisal third where perikymata create subtle horizontal ridges. I learned this the hard way when a patient came back three days after cementation and said the tooth looked "too perfect." The fix was adding subtle characterization with stains and a light air-abrasion protocol to break up the gloss. Counter-intuitive point: More reduction does not always mean a better result. Over-reducing the lingual surface of an anterior tooth can compromise the integrity of the bond, especially with resin-modified glass ionomer cements that rely on some enamel for retention. I have seen clinicians reduce the lingual table by four millimeters because they wanted "enough space for porcelain." That tooth ended up dislodging within six months because there was no enamel left to bond to. Another thing beginners miss is the relationship between the incisal edge and the midline. The incisal edge of the central incisor should align with the philtrum when the lips are at rest. If the restoration is too long, it shows. If it is too short, the face looks aged. This is not cosmetic theory, it is basic anatomical relationship. I measure this intraorally with a caliper before I even think about waxing.
Limitations and Where This Approach Breaks Down
The anatomy of anterior teeth is well documented, but the documentation assumes average anatomy. Patients with severe attrition, wear facets, or previous restorative work do not fit the average. In those cases, the "rules" about contact location and surface curvature become guidelines at best. Digital workflows help, but they are not foolproof. An intraoral scanner will capture the surface topology accurately, but it does not tell you what the root looks like beneath the preparation. You still need to rely on pre-operative imaging and clinical judgment to understand the hidden anatomy. I have seen at least two cases where the scanner showed a clean finish line, but the X-ray revealed a buccal bone defect that would have compromised the margin placement. If you are working with compromised abutments or severely rotated teeth, the standard reference models are essentially useless. In those situations, I fall back to a custom impression and a hand-contoured wax pattern. Digital design software has improved, but the software still defaults to average anatomy unless you manually override every single parameter, and that takes more time than most clinicians want to spend.
A quick reference that actually works: the mesial contact of a maxillary central incisor is at the incisal third, the distal contact is at the incisal-third-to-middle-third junction, the cervical line curves 2 to 3 mm incisally from theCEJ on the mesial, and the cingulum is located slightly palatal to the true midline of the tooth. These are starting points, not absolute measurements. There is no shortcut that replaces understanding the relationship between the labial contour, the proximal contact position, and the lingual anatomy. If you skip any of those, the restoration will function, but it will not look or feel right. Most patients cannot tell you why something is wrong, but they know immediately when it is.