Getting Past The Textbook Description
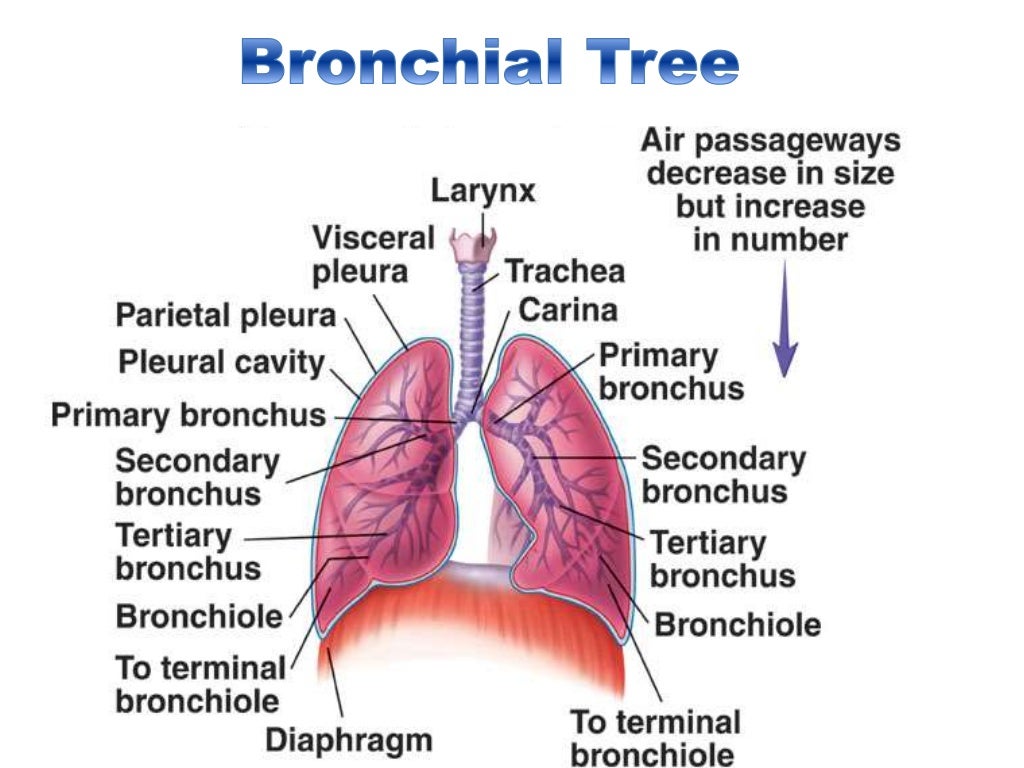
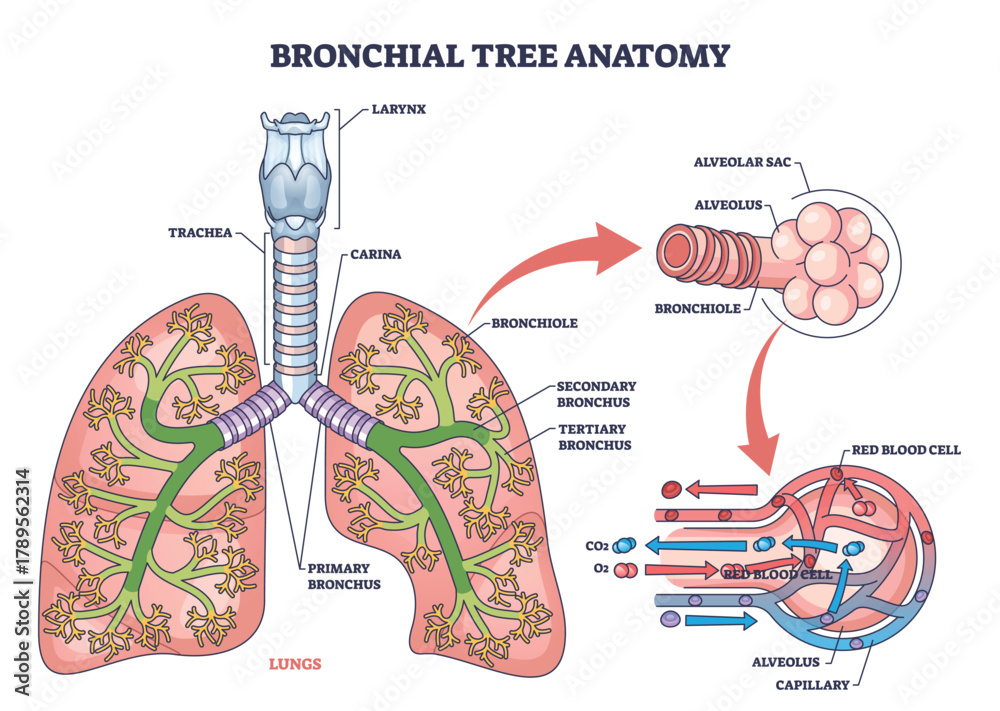
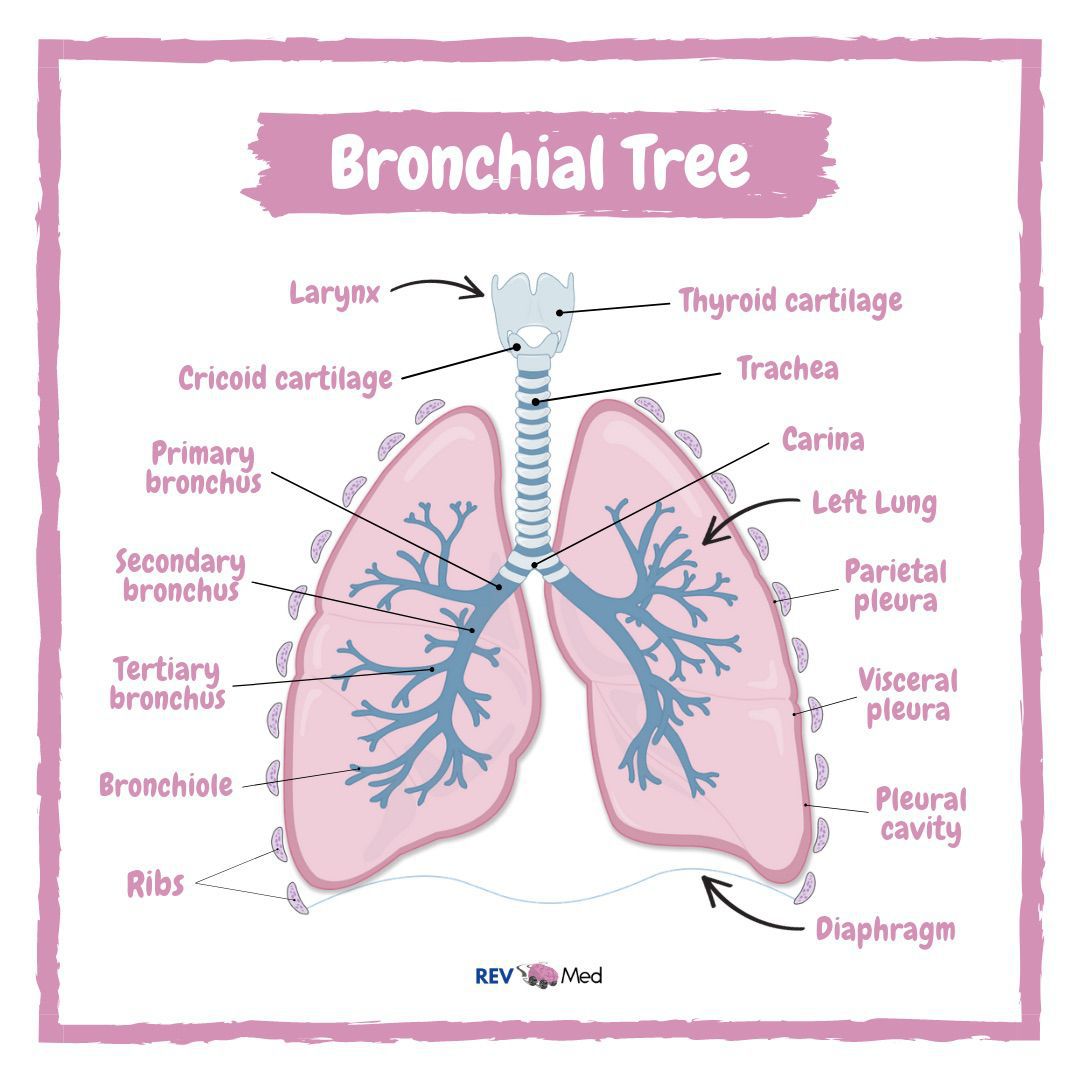
The standard diagrams show a perfect branching tree, symmetrical and neat, like some kind of educational illustration you'd find in a first-year anatomy textbook. The reality is messier than that. When you're actually studying the Anatomy Of Bronchial Tree for clinical work or surgical planning, those clean drawings don't help you understand what you're looking at. I spent a few years working with bronchoscopy and thoracic surgery imaging before I stopped relying on textbook figures and started looking at actual scans and cadaver specimens. Here's the practical breakdown of what you need to know, what the diagrams leave out, and where most people mess up when they try to apply this knowledge.
Core Structure And Branching Pattern
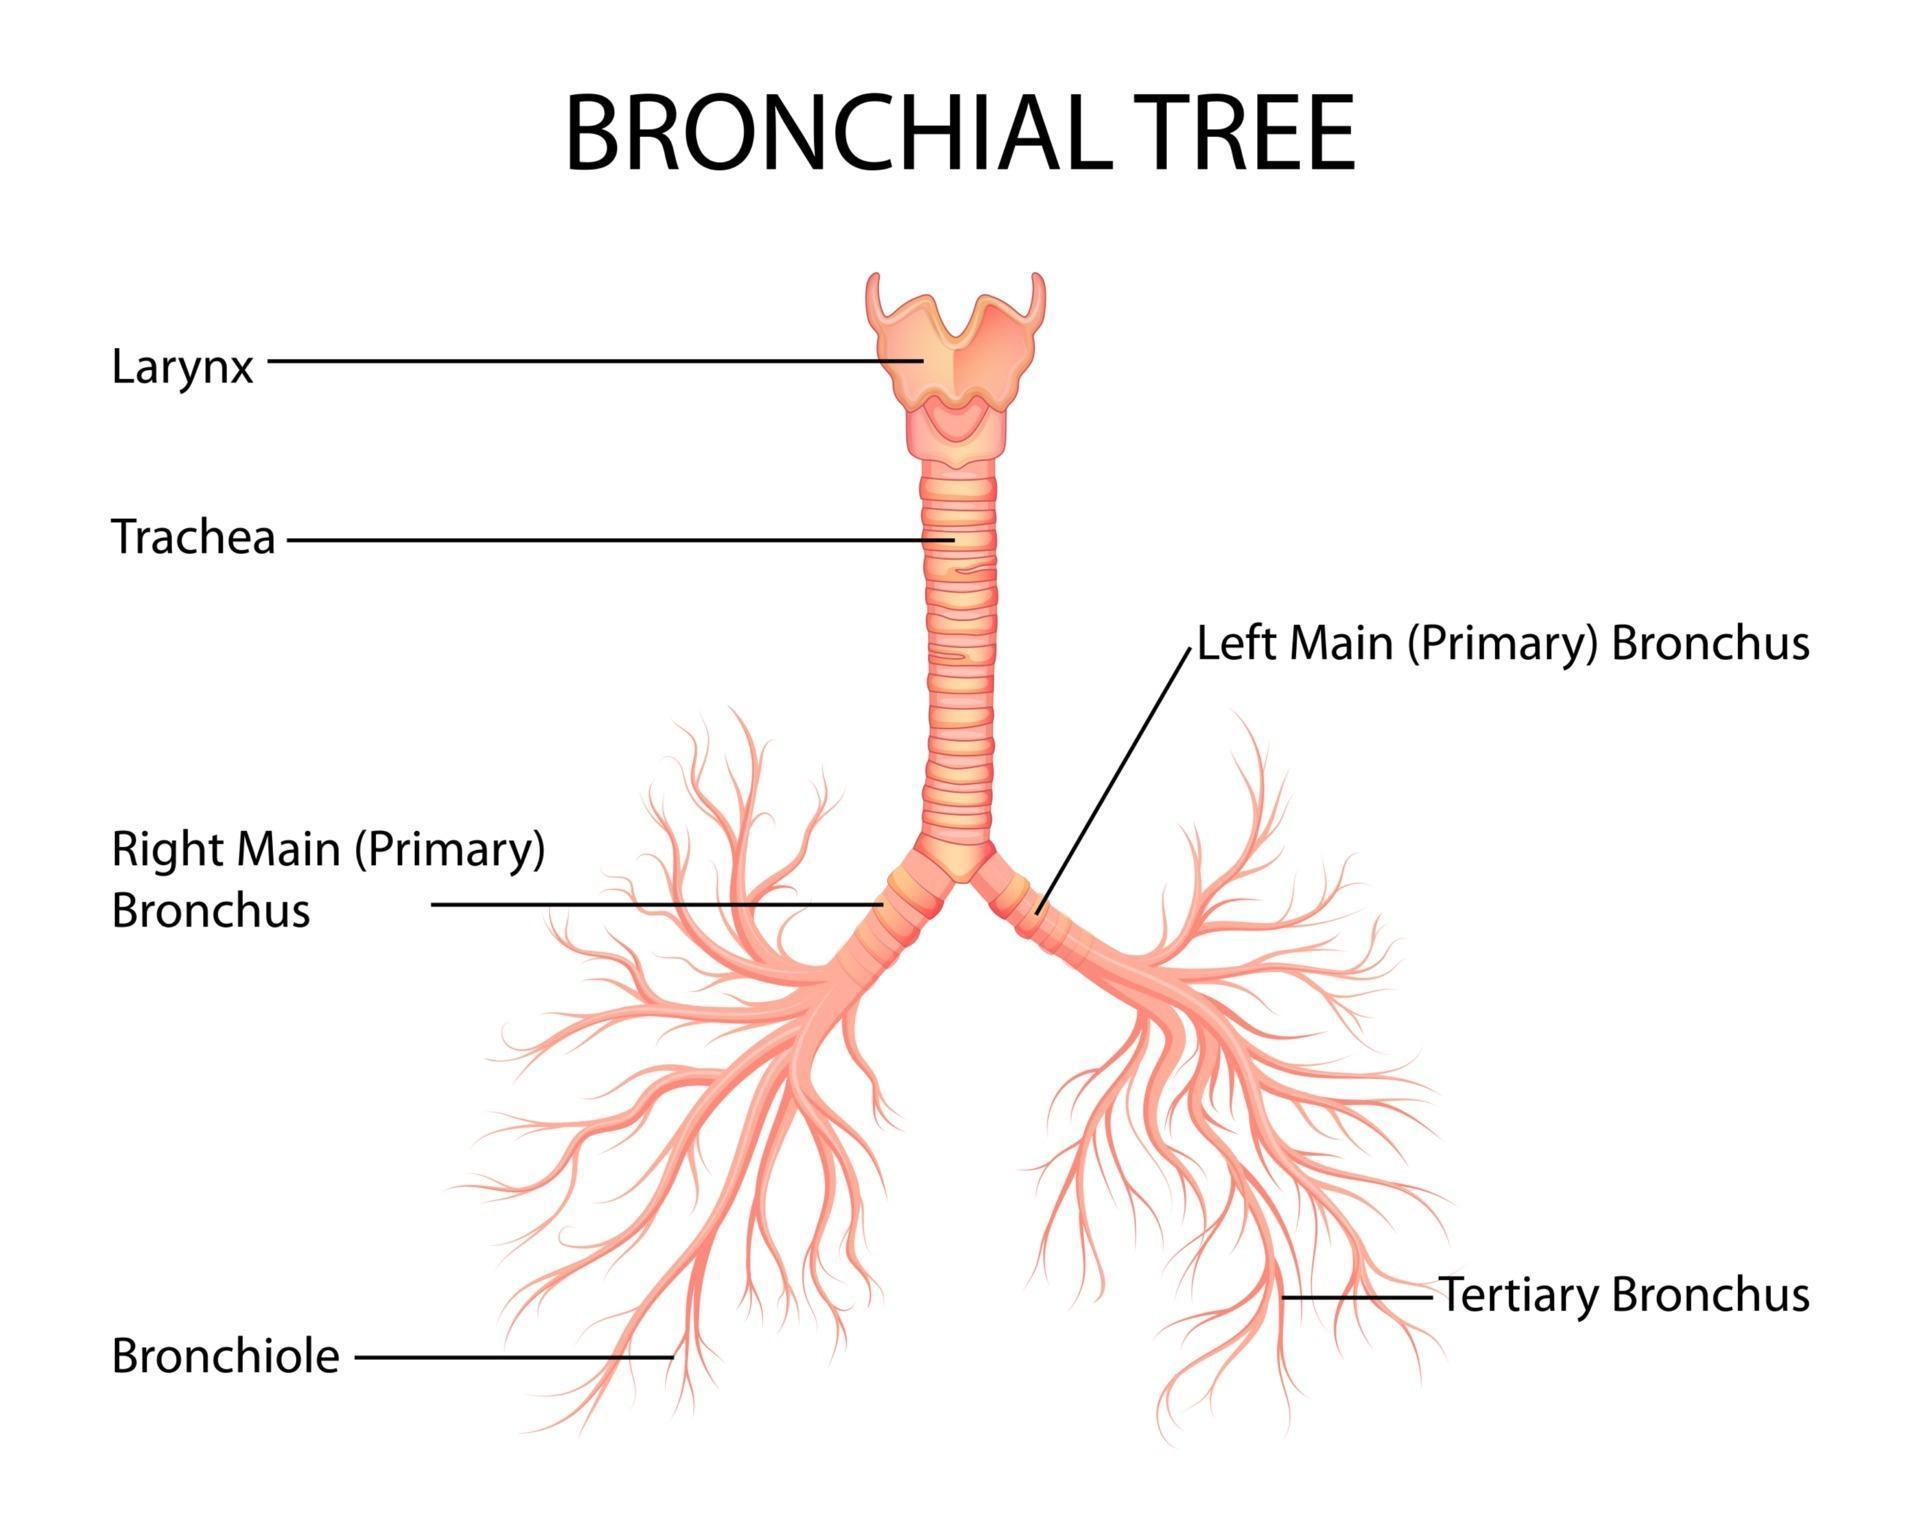
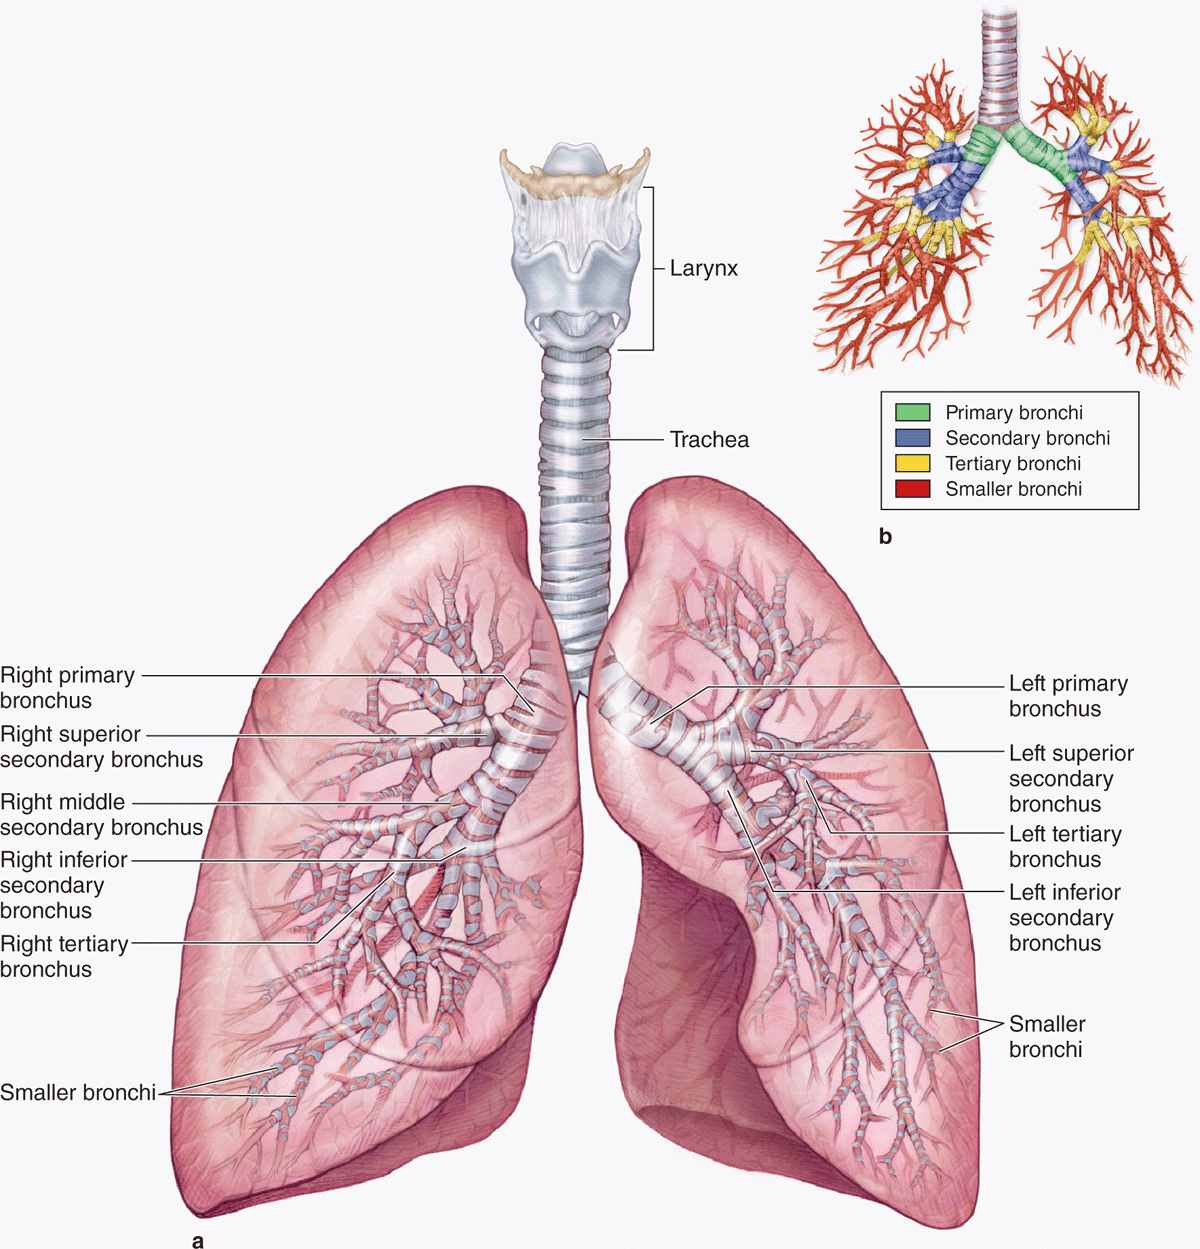
The trachea bifurcates at the carina, roughly at the level of the T4 to T5 vertebrae in adults, though this varies with body habitus and respiration phase. The right main bronchus is wider, shorter, and more vertical than the left. This isn't just trivia. It's why aspirated foreign bodies end up in the right lung far more often than the left, and it's why intubation mistakes tend toward the right side. After the main bronchi, each side branches into lobar bronchi. The right lung gets three: upper, middle, and lower lobe bronchi. The left lung gets two because the left lung only has two lobes. From there, segmental bronchi supply the ten bronchopulmonary segments on each side. Knowing segmental anatomy matters because surgeons resect by segments, not by arbitrary zones. The cartilage composition changes as the airways get smaller. You start with C-shaped cartilaginous rings in the trachea, transitioning to irregular plates in the bronchi, then essentially nothing by the time you reach terminal bronchioles. Smooth muscle becomes proportionally more significant as cartilage disappears. This is why conditions like asthma affect smaller airways more dramatically than the larger conduits.
Why The Right Side Is Different And Why It Matters
I remember a case where I was reviewing a CT scan for a lung transplant evaluation and missed a variant because I was assuming standard anatomy. The patient had a right upper lobe bronchus that branched early, giving off a separate apical and posterior segmental bronchus before the remaining right upper lobe tissue. Standard diagrams don't show this. It happens in maybe ten to fifteen percent of the population, and if you're planning a segmentectomy, missing this variant means you cut the wrong way. The left side has its own quirks. The left main bronchus has to pass under the aortic arch, which compresses it slightly against the esophagus in some people. This can be clinically relevant during esophageal surgery or when placing certain types of central lines. The left recurrent laryngeal nerve loops under the aortic arch near the ligamentum arteriosum, and surgical damage here causes hoarseness. I've seen postoperative voice changes in patients who had perfectly successful cardiac surgeries, just because of the anatomy in that tight space. Bronchial arteries, which supply the conducting airways themselves, typically arise from the descending thoracic aorta. There's usually one on the left and two on the right, but the numbering varies. These are small vessels, often less than two millimeters in diameter, and they become critically important when someone has hemoptysis. Bronchial artery embolization is a real procedure for controlling bleeding, and the variation in arterial anatomy makes it tricky. Radiologists map these individually every time because assumptions get people into trouble.
Get the Full Details
Vascular Relationships You Shouldn't Ignore
The pulmonary arteries run alongside the bronchi at each level, generally anterior to the bronchus at the hilum. But this relationship flips in the lower lobes, where the pulmonary artery passes above the bronchus rather than in front of it. This anatomical detail is the difference between a clean dissection and a major hemorrhage during lobectomy. Surgeons learn this through repetition, but if you're studying from illustrations alone, you'll never internalize the spatial relationship the way you need to. Lymphatic drainage follows the bronchial tree hierarchically. hilar nodes drain to tracheobronchial nodes, which drain to paratracheal and pretracheal stations. This matters enormously in lung cancer staging. A tumor in the right lower lobe can metastasize to ipsilateral hilar nodes and still be considered N1 disease, but once it hits contralateral mediastinal nodes, you're looking at N2 or N3, which changes everything about treatment strategy. The mapping is standardized through the IASLC lymph node map, and it directly influences whether someone gets surgery first or neoadjuvant therapy. I worked with a pulmonologist who insisted that everyone studying bronchial anatomy should learn the segmental bronchus names by drawing them from memory, not just recognizing them on a diagram. She was right. When you can draw the branching pattern from scratch, you understand the spatial relationships in a way that looking at pictures never teaches you. Try it yourself. Start with the trachea, branch to the carina, then work down through lobar and segmental levels. You'll immediately see where your gaps are.
Common Misunderstandings And Where People Get Stuck
Most students learn that there are ten bronchopulmonary segments per lung and assume symmetry between the left and right sides. They're not symmetrical. The right upper lobe has apical, posterior, and anterior segments. The left upper lobe has apicoposterior (often combined), anterior, and lingular segments split into superior and inferior. The numbering system reflects this. Right-sided segments use Roman numerals I through X starting from the top. The left side renumbers because it has fewer segments, so you get I through VIII with the lingula taking segments IV and V instead. Another common error involves the membrane portion of the trachea. That posterior flat part between the cartilaginous rings isn't just empty tissue. It contains the trachealis muscle, dense connective tissue, and the posterior membrane that connects the ends of the C-shaped cartilages. During bronchoscopy, you can see this membrane move with respiration and coughing. When people place endotracheal tubes, the cuff inflates against this membrane and the adjacent cartilage. Overinflation can cause pressure necrosis. I've seen tracheal stenosis in patients who were intubated for extended periods in the ICU, and the damage is always centered where the cuff sits. The mucociliary escalator is another concept that gets oversimplified. The ciliated epithelium moves mucus upward from the smaller airways toward the pharynx at roughly one centimeter per hour under normal conditions. Smoking slows this down significantly. I've looked at bronchial biopsies from chronic smokers where the cilia were blunted or completely absent in patches. The mucus still gets produced, but it doesn't move. That's why smokers cough in the morning. The clearance mechanism is broken, and the body compensates with forced exhalation.
One thing most resources don't emphasize enough is the innervation pattern. The bronchial tree receives parasympathetic input from the vagus nerve, causing bronchoconstriction and increased glandular secretion. Sympathetic input, traveling through the sympathetic chain, causes bronchodilation. This is why beta-2 agonists like albuterol work for acute asthma. They're mimicking sympathetic stimulation. But the parasympathetic tone is the baseline regulator, and chronic overactivity contributes to persistent airway narrowing. Anticholinergic medications like ipratropium block this pathway and provide additional bronchodilation, especially in COPD patients where parasympathetic tone is chronically elevated.
What Standard Imaging Misses
CT scans show the bronchial tree well down to about the subsegmental level, but anything smaller requires bronchoscopy or high-resolution techniques. MRI doesn't image air-filled structures effectively because there's no signal from the air itself. PET scans show metabolic activity but provide poor anatomical detail of the airways. When I need to evaluate bronchial anatomy for interventional planning, I combine CT angiography with flexible bronchoscopy. The CT gives me the macro structure and any masses or narrowing, and the bronchoscope lets me visualize the mucosal surface and navigate into specific segments. Bronchography, the old technique of injecting contrast directly into the airways, is essentially obsolete except in very specific research or rare diagnostic situations. It's invasive and uncomfortable. Modern multidetector CT with 3D reconstruction has replaced it for almost everything. But I'll say this: the 3D reconstructions can be misleading if you don't understand the underlying anatomy. The software interpolates between slices, and sometimes it creates pathways that don't exist or misses narrow collateral channels. Always verify the reconstruction against the raw axial slices. The bronchial tree's blood supply is another area where textbook simplicity falls apart. The pulmonary arteries handle gas exchange, but the bronchial arteries supply the airway walls themselves. This dual circulation means the lungs have two completely separate vascular systems with different pressures and different functions. The pulmonary system is low pressure and high volume. The bronchial system is systemic pressure and lower volume. In conditions like mitral stenosis, pulmonary hypertension can cause bronchial arteries to enlarge dramatically as they try to compensate. I've seen bronchial arteries that were over five millimeters in diameter on CT scans, which is several times normal. Those vessels bled profusely during surgery.
Practical Application
If you're studying this for clinical purposes, focus on three things. Learn the segmental anatomy well enough to draw it. Understand the right versus left differences, especially the early branching variants on the right and the aortic compression on the left. Know the lymph node stations and how they correlate with tumor location. Everything else is detail that you can look up when you need it. The anatomy doesn't change much between people, but the variations do, and the variations are what matter in practice. A standard reference will tell you the right upper lobe has three segments. The real question is whether that particular patient's bronchus branches the standard way or whether the apical and posterior segments share a common trunk. That distinction determines whether you can do a sparing segmentectomy or whether you need to remove the entire lobe. I still refer back to cadaver specimens occasionally even after years of practice. Diagrams and scans are useful, but nothing teaches you the actual three-dimensional relationships like holding the tissue. The bronchus intermedius sits exactly where you'd expect it on a diagram, but in the body, it's wrapped around vessels and lymph nodes in a way that changes the surgical approach entirely. The theory is clean. The practice is not.