Breaking Down the System Without the Textbook Fluff
The ear, nose, and throat don't work in isolation, which is the first thing most students miss. I used to chart them separately during my residency. It took me two years of dealing with referrals coming back with vague symptoms to realize the structures are constantly cross-contaminating each other through pressure changes and mucosal pathways. If you're studying this for clinical practice, stop treating the canals and sinuses like separate rooms. They're connected plumbing. Let's start with the ear because it's the misunderstood section of the triad. The external auditory canal isn't just a tube. It has three distinct zones with different nerve supplies. The outer third is cartilaginous and innervated by branches of the facial and vagus nerves. The middle and inner thirds are bony and share supply with Cranial Nerve V. This matters because pain from otitis externa can refer to the jaw, and vice versa. I had a patient present with what looked like a simple earache. Took me twenty minutes to notice theTMJ tenderness and realize the whole episode was referred pain from bruxism, not an infection. Prescribing antibiotics would have been a waste of everyone's time. The middle ear space is roughly 1cc in volume. That's important because it explains why effusions are so common and why pressure equalization matters more than most people think. The Eustachian tube connects it to the nasopharynx and opens during swallowing. When it doesn't open properly, you get negative pressure buildup, fluid accumulation, and hearing loss that mimics sensorineal issues but is actually conductive. Audiometry distinguishes them, but you shouldn't need a full workup to suspect the difference.
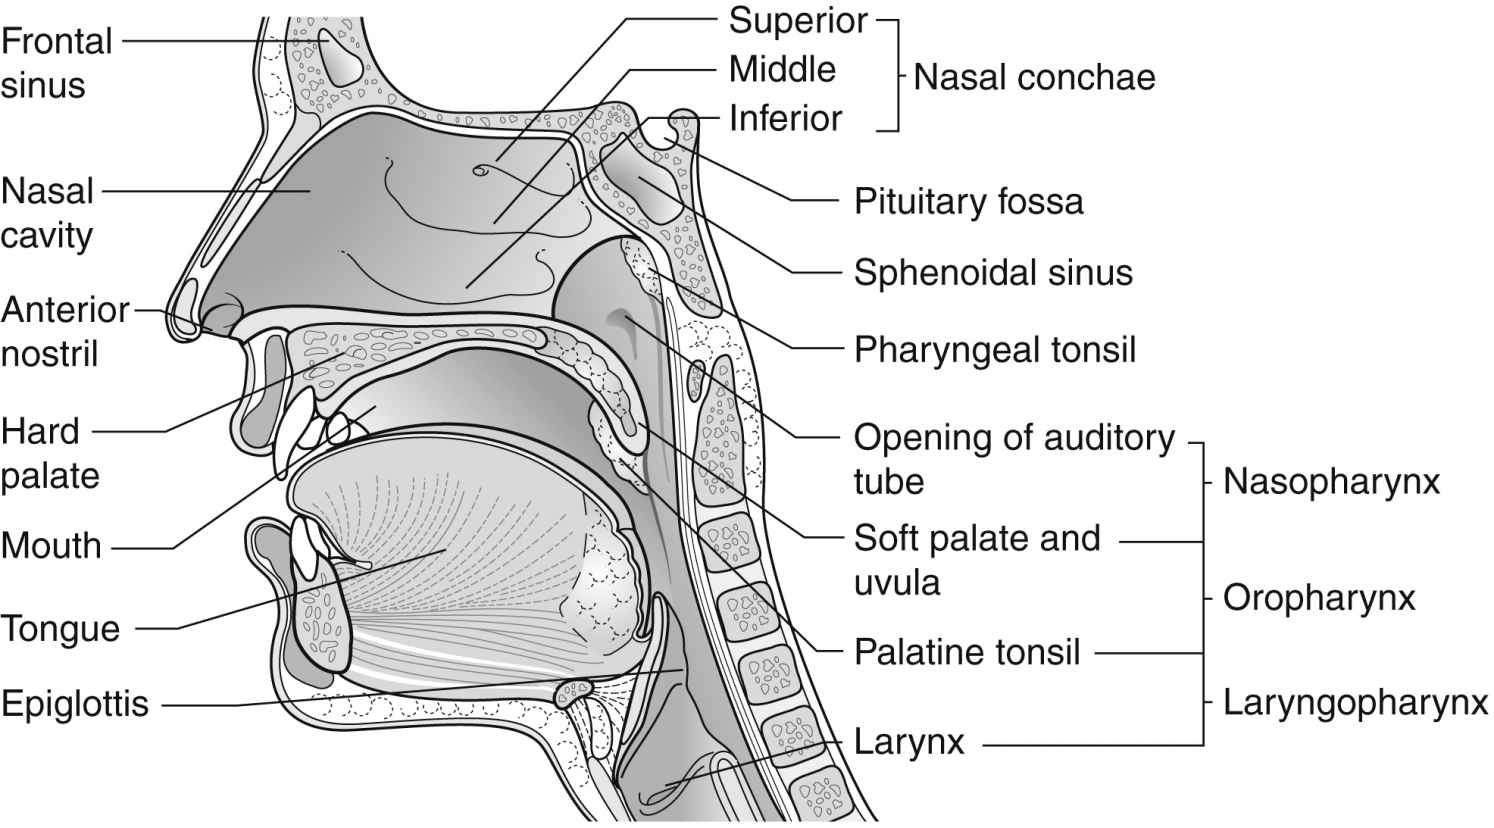
The nasal cavity occupies about 3 cubic centimeters per side and is lined with respiratory epithelium that produces roughly 1 liter of mucus daily. Most of that drains posteriorly into the throat. You swallow it unconsciously. The turbinates cycle between congestion and decongestion every few hours — that's the nasal cycle, controlled by the autonomic nervous system. It's not a pathology when one side feels more blocked than the other. It's normal physiology. I've lost count of how many patients came in concerned about "nasal obstruction" only to discover they were complaining about the normal unilateral congestion phase. The paranasal sinuses are the real shortcut for pathology. They're air-filled spaces that drain through narrow ostia into the nasal meatus. The maxillary sinus drains through the middle meatus via the hiatus semilunaris. If that ostium gets blocked from inflammation or anatomical variation, you get bacterial overgrowth. That's sinusitis. The frontal and ethmoid sinuses share drainage pathways through the same region, which is why infections here tend to spread laterally rather than staying contained.
The Throat Connection Most People Skip
The oropharynx and nasopharynx aren't just passageways. They're immune surveillance zones with dense lymphoid tissue. The adenoids and tonsils form Waldeyer's ring, which is significant because this tissue responds to pathogens by hypertrophying. In children, this is normal. In adults, persistent enlargement usually signals something else going on. I saw a 45-year-old patient with chronic unilateral tonsillar hypertrophy. Biopsy revealed squamous cell carcinoma at an early stage. The lesson here is straightforward: asymmetry in adult lymphoid tissue deserves investigation, not dismissal. The larynx sits at the intersection of the respiratory and digestive tracts. The vocal cords originate from the thyroid cartilage and insert on the arytenoid cartilages. Their tension is modulated by the cricothyroid and intrinsic laryngeal muscles. Vagal nerve damage causes vocal cord paralysis on the affected side, which presents as hoarseness and aspiration risk. A transient lesion from intubation can mimic this, but persistent hoarseness beyond three weeks warrants laryngoscopy. That's not a suggestion. It's the standard.
Get the Full Details

Counter-Intuitive Things Nobody Teaches Early
The nasolacrimal duct drains into the inferior nasal meatus, not the nasal cavity generally. This means eye infections can seed the nose and nasal infections can irritate the eyes. I've seen conjunctivitis treated topically while the actual source was a retained nasal foreign body in a pediatric patient. Checking the nose before assuming ocular pathology is cheap insurance. Another thing: the olfactory epithelium sits in the superior nasal vault, behind the superior turbinate. Standard anterior rhinoscopy misses it entirely. That's why patients with nasal polyps often report reduced smell before they report congestion. The polyps physically block airflow to the olfactory cleft. Treating the congestion without addressing the cleft obstruction doesn't restore smell. I learned this from a patient who complained her nose was "clear" after polyp surgery but her sense of smell never returned. The endoscopic approach to the olfactory cleft made the difference. The soft palate separates the oropharynx from the nasopharynx during swallowing. Velopharyngeal incompetence causes nasal regurgitation of food and liquid. This can be congenital or acquired from surgery, trauma, or neurological disease. It's often overlooked because clinicians focus on the more dramatic symptoms and miss the subtle hypernasal quality of speech that accompanies it. A simple mirror fog test or nasal endoscopy during phonation confirms it in minutes.
What Actually Works When Dealing with Issues
For nasal congestion that won't resolve with saline irrigation, topical intranasal corticosteroids are first-line. Oxymetazoline and similar decongestant sprays work faster but cause rebound congestion after 3 to 5 days of use. I tell patients to limit them to a maximum of 5 days. The compliance rate is terrible, and the resulting rhinitis medicamentosa is genuinely miserable to treat. Fluticasone and mometasone don't have that limitation but take 1 to 2 weeks for full effect. Setting expectations upfront prevents patients from abandoning them prematurely. Earwax impaction is another area where well-intentioned advice causes more problems. Cotton swabs push wax deeper. Irrigation kits work for mild cases but can cause otitis externa if the tympanic membrane has a prior perforation. I recommend dropping 3 drops of mineral oil or carbamide peroxide into the ear canal twice daily for 3 to 5 days, then letting gravity do the work. If that fails, manual removal under microscopy takes about 10 minutes and eliminates the recurrence risk for months. Home irrigation attempts that fail repeatedly should just go straight to the clinic. Throat infections require a different calculus. Strep pharyngitis affects roughly 15 to 30 percent of sore throats in children and 5 to 15 percent in adults. Rapid antigen detection tests have sensitivity around 85 to 95 percent in children but lower sensitivity in adults. A negative test in an adult should be backed up by culture. Treating based on clinical criteria alone — Centor score — leads to unnecessary antibiotic prescriptions. I run cultures on any adult with a Centor score of 2 or less and a negative rapid test. It adds two days to the diagnosis but prevents about 70 percent of unnecessary antibiotic courses in that population.
The Boundaries of What You Can Do Yourself
Self-management has a hard ceiling. If you have unilateral hearing loss, persistent ear fullness lasting more than 3 weeks, epistaxis from one nostril only, a neck mass that doesn't resolve in 2 weeks, or hoarseness beyond 3 weeks, you need in-person evaluation. These aren't borderline recommendations. They're the line between watchful waiting and missing something that won't wait. Chronic sinus symptoms that persist beyond 12 weeks despite topical steroids and saline irrigation usually need CT imaging of the sinuses. The anatomy varies enough between individuals that visualizing the ostiomeatal complex on imaging changes management in roughly 40 percent of refractory cases. Some patients need functional endoscopic sinus surgery. Others just need a different steroid formulation or a longer treatment window. The CT scan tells you which path to take. The ear-nose-throat system is deceptively simple on paper and genuinely complicated in practice. The connections between structures create diagnostic puzzles that don't follow textbook patterns. Experience teaches you to look at the whole region individual symptoms. A nasal issue can explain ear symptoms. A throat issue can explain ear pain. The anatomy doesn't respect the categories we put it into.