Understanding The Female Perineum: An Anatomical Guide
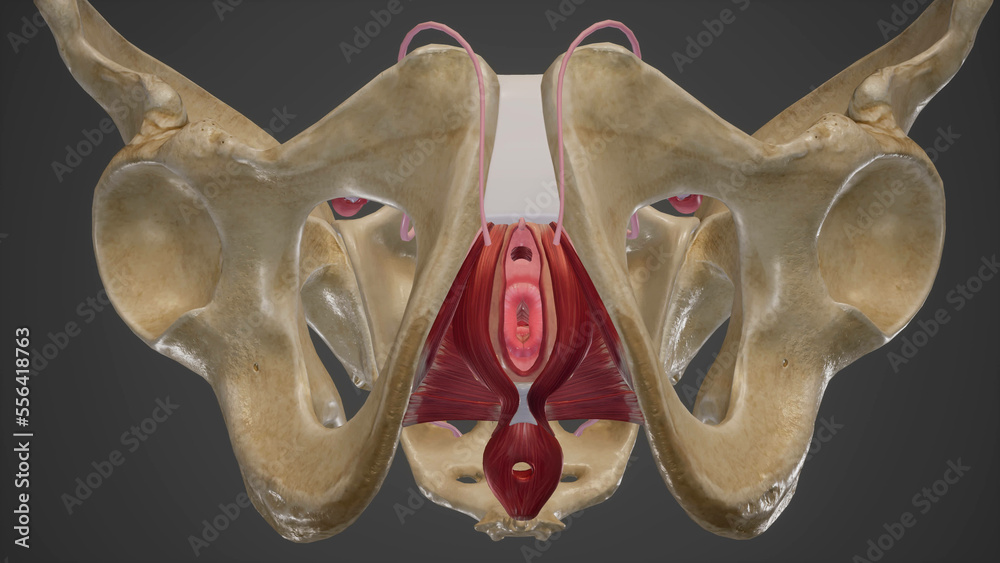
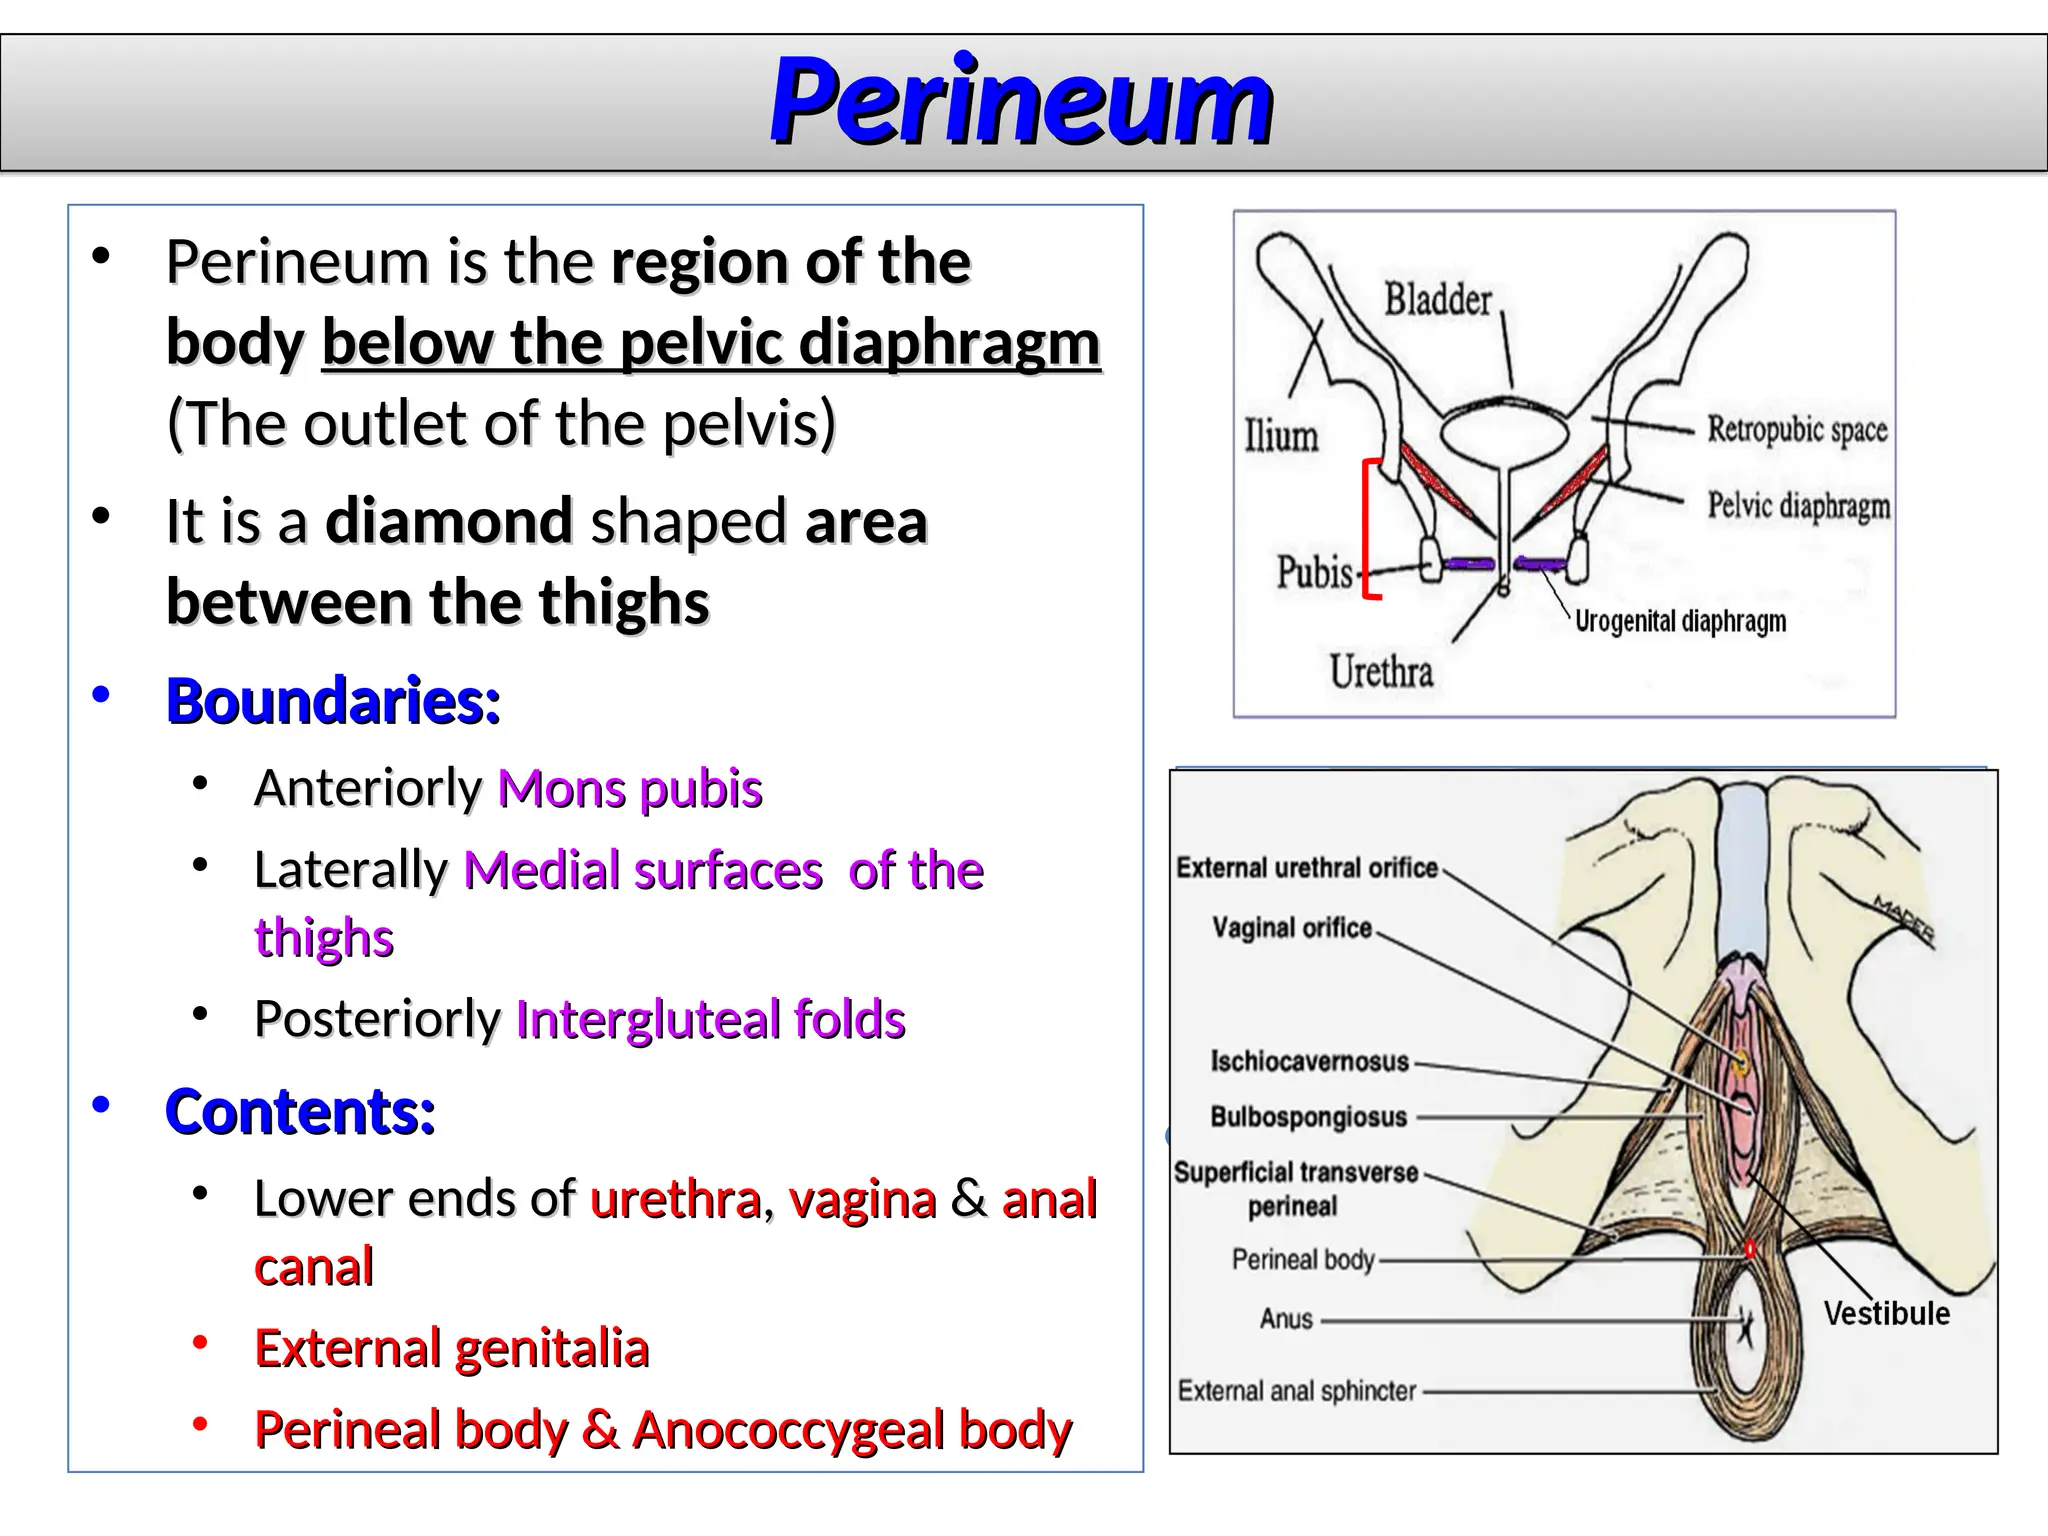
The perineum is the diamond-shaped region between the thighs, extending from the pubic symphysis anteriorly to the coccyx posteriorly. In females, this area carries particular clinical significance because it undergoes substantial stretching during vaginal delivery and serves as a critical landmark for pelvic floor assessment. When clinicians refer to the anatomy of female perineum, they are describing the complex arrangement of skin, fascia, muscles, and neurovascular structures that occupy the superficial and deep perineal spaces. The region is bounded laterally by the ischiopubic rami and ischia, and it contains several clinically important structures including the vaginal orifice, urethral opening, clitoral structures, and the perineal body at its center. I have spent considerable time working with pelvic floor patients and studying obstetric anatomy. One thing most people do not understand is how the perineum functions as a dynamic structural unit rather than a static region. During the second stage of labor, the perineal tissues must stretch significantly while maintaining their structural integrity. The rate of descent, fetal head size, and maternal positioning all influence the mechanical stress placed on these tissues.
Structural Layers And Their Clinical Relevance
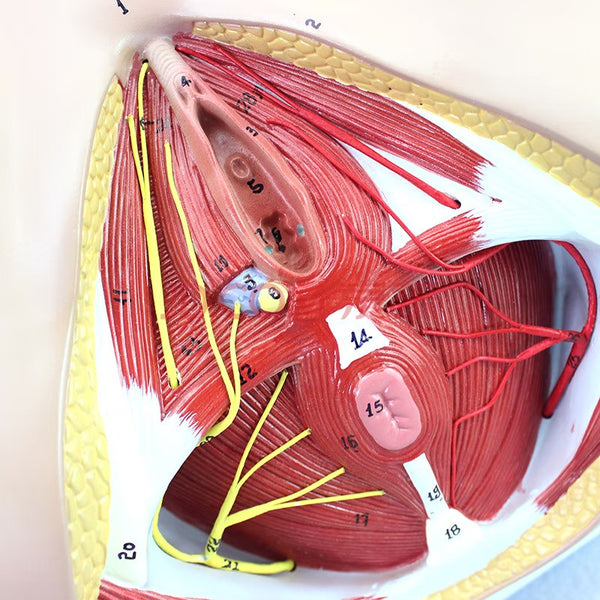
The female perineum consists of multiple layered structures that work together to support pelvic organ function. Starting from the surface, the skin layer contains specialized glandular structures and nerve endings that provide sensory feedback crucial for both urinary and sexual function. Beneath the skin lies the superficial perineal pouch, which contains the bulbospongiosus muscle, ischiocavernosus muscle, and the superficial transverse perineal muscle. These muscles surround the vaginal introitus and play a role in constriction during sexual activity as well as supporting the perineal body. The bulb of the vestibule, homologous to the male corpus spongiosum, sits lateral to the vaginal opening and becomes engorged during arousal. The deep perineal pouch contains the deeper muscular and fascial structures, including portions of the external urethral sphincter and the compressor urethrae muscle. These structures are essential for continence mechanisms and are frequently assessed in urogynecological practice.
The perineal body itself is a fibromuscular mass located approximately one centimeter posterior to the vaginal introitus. It serves as the central anchoring point for multiple muscle groups including the bulbospongiosus, superficial and deep transverse perineal muscles, external anal sphincter, and fibers from the levator ani. Damage to this structure during childbirth can lead to significant functional deficits including fecal incontinence and pelvic organ prolapse.
Get the Full Details

Neurovascular Supply And Sensory Considerations
The perineum receives innervation primarily from the pudendal nerve, which arises from the S2 through S4 nerve roots. This nerve exits the pelvis through the greater sciatic foramen, wraps around the ischial spine, and re-enters through the lesser sciatic foramen. It then travels through Alcock canal before branching into the inferior rectal nerve, perineal nerve, and dorsal nerve of the clitoris. From my clinical experience, pudendal nerve entrapment or injury is more common than many practitioners realize. Women presenting with chronic perineal pain often have been misdiagnosed with vulvodynia or other conditions when the underlying issue is actually neurogenic. A blockage at Alcock canal can produce symptoms that mimic several other pathologies, making accurate diagnosis essential before pursuing treatment. The blood supply comes primarily from the internal pudendal artery, a branch of the internal iliac system. Venous drainage follows the arterial supply and communicates with the systemic venous plexus. Understanding this vascular arrangement is critical during perineal surgery to avoid excessive bleeding and to preserve tissue viability.
Practical Assessment Techniques
Clinical examination of the perineum requires both knowledge of normal anatomy and familiarity with pathological variations. The Bristol Perineal Injury Classification system provides a framework for documenting perineal trauma following delivery, ranging from first-degree tears involving only the perineal skin to fourth-degree tears extending through the anal sphincter and rectal mucosa. I routinely assess perineal body integrity in postpartum patients using a combination of visual inspection and digital palpation. The perineal body should feel firm and centrally located, serving as a clear anatomical landmark. When it becomes attenuated or displaced, the risk of subsequent pelvic floor dysfunction increases substantially. Patients with a perineal body length of less than two centimeters post-delivery often benefit from targeted pelvic floor rehabilitation. One counter-intuitive finding from my practice is that episiotomy, particularly mediolateral episiotomy, does not consistently reduce the risk of severe perineal trauma and may actually increase the likelihood of extended tearing in some cases. Current evidence supports restrictive episiotomy practices rather than routine use, reserving the procedure for specific indications such as fetal compromise requiring expedited delivery or significant shoulder dystocia.
Common Pathological Conditions
Perineal trauma during childbirth represents the most common acute pathology affecting this region. Third- and fourth-degree obstetric anal sphincter injuries occur in approximately one to three percent of vaginal deliveries in developed countries. These injuries require meticulous surgical repair and postoperative management to optimize healing outcomes. Perineal body cysts and Bartholin gland abscesses represent another category of common conditions. The Bartholin glands, located at approximately the four and eight o'clock positions relative to the vaginal introitus, can become obstructed leading to cyst formation or infected abscess development. Word catheter placement remains the standard initial intervention for Bartholin gland abscesses, providing continuous drainage while preserving gland function. Vulvovaginal granulomas, also known as endometriosis of the perineum, represent a rare but clinically important condition. These implants of endometrial tissue within the perineal scar following episiotomy or laceration repair produce cyclical pain and nodularity that correlates with the menstrual cycle. Surgical excision provides definitive treatment, though recurrence is possible if the diagnosis is delayed.
Surgical And Procedural Considerations
Perineal surgery, whether for reconstructive purposes or therapeutic intervention, requires detailed anatomical knowledge to avoid compromising functional outcomes. The relationship between the perineal body, external anal sphincter, and levator ani muscles must be preserved during any surgical procedure in this region. Posterior colporrhaphy for posterior compartment prolapse involves plication of the rectovaginal fascia and reconstruction of the perineal body. Outcomes depend significantly on the surgeon's ability to restore the normal anatomical relationships while avoiding excessive tension that could compromise tissue perfusion or cause dyspareunia. The rate of recurrent prolapse following this procedure is approximately ten to fifteen percent at five years, which is an important consideration when counseling patients. Perineal nerve blocks are frequently employed during obstetric procedures and minor gynecological surgeries. The injection technique involves identifying the ischial spine as a landmark and depositing local anesthetic anterior and medial to it. Complications from this block are rare but can include intravascular injection, hematoma formation, or transient neurological symptoms. Patients should be monitored for at least thirty minutes following administration to ensure safety.
Rehabilitation And Long-Term Management
Pelvic floor rehabilitation following perineal trauma represents an essential component of comprehensive care. Standardized programs incorporating supervised exercises, biofeedback, and progressive loading have demonstrated improvement in both strength and function compared to unsupervised exercise alone. The typical timeframe for meaningful improvement following perineal repair is six to twelve weeks, with continued gains possible up to two years post-injury. One limitation of current rehabilitation approaches is that they do not always address the fascial and connective tissue components of perineal injury. Muscle strengthening alone may not restore the structural integrity of a damaged perineal body, which explains why some patients continue to experience symptoms despite adequate pelvic floor exercise. Combined approaches addressing both muscular and fascial components tend to produce superior outcomes in complex cases. Dyspareunia following perineal trauma is reported by approximately twenty to thirty percent of women in the first year post-injury. This symptom often responds to graded exposure therapy, topical estrogen when appropriate, and targeted manual therapy to the perineal scar tissue. Patients should be counseled that persistent pain beyond six months warrants comprehensive evaluation to exclude other contributing factors such as pudendal neuralgia or pelvic floor hypertonicity.
Key Anatomical Relationships To Remember
The perineal membrane spans the anterior half of the perineal diamond and provides attachment for the superficial and deep perineal muscles. This membrane is continuous with the fascia of Gamna and the obturator internus fascia, creating a potential plane for surgical dissection. Understanding these relationships is essential for avoiding inadvertent entry into the urinary tract or rectum during perineal procedures. The rectovaginal septum, also called the fascia of Denonvilliers in males, separates the posterior vaginal wall from the anterior rectal wall. This septum varies considerably in thickness and integrity between individuals and is frequently disrupted during anterior third repairs or posterior colporrhaphy. Its condition directly influences the durability of prolapse repair and should be assessed intraoperatively whenever possible. The urogenital hiatus formed by the levator ani muscles measures approximately two to three centimeters in diameter in nulliparous women and can increase to four to six centimeters following vaginal delivery. This enlargement permits descent of pelvic organs and contributes to the development of stress urinary incontinence and prolapse. Measurements obtained via dynamic MRI or translabial ultrasound provide more accurate assessment than clinical examination alone, though these modalities are not universally available.