Vein Mapping and the Reality of the GSV
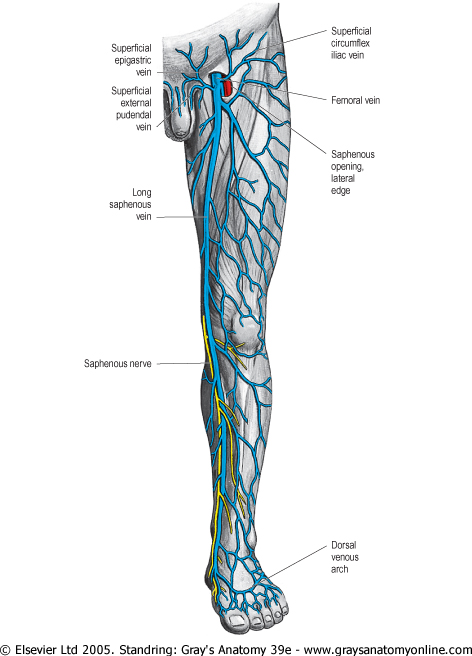
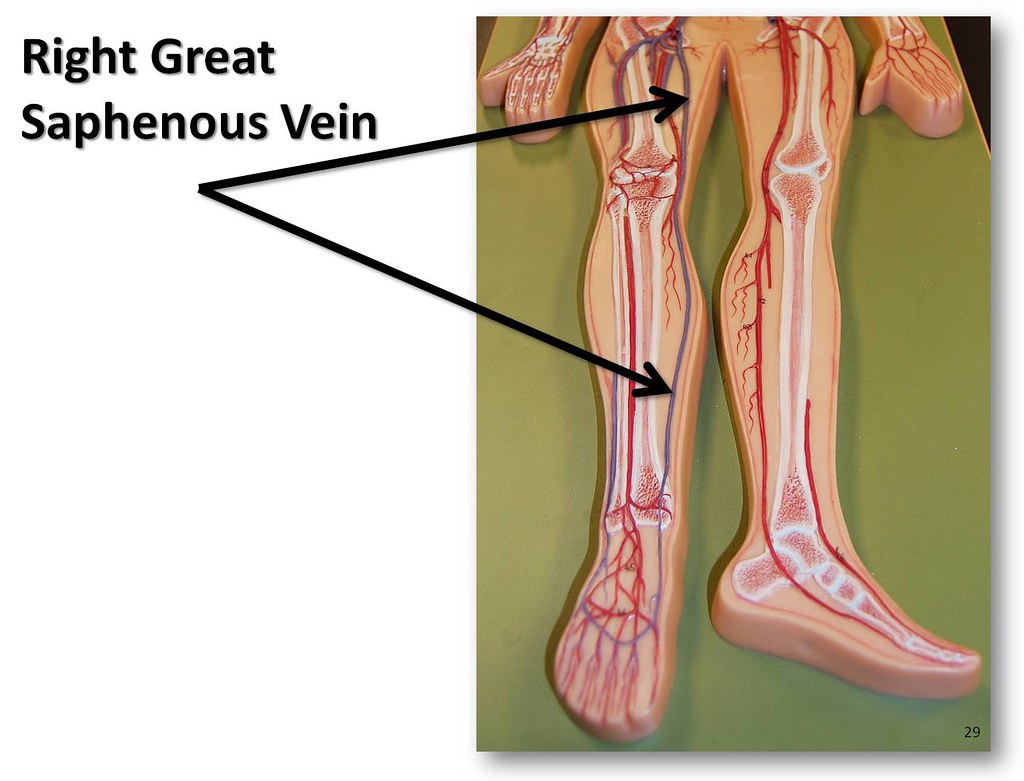
The anatomy of great saphenous vein is something you learn three ways: textbooks, ultrasound labs, and then the mess of real clinical practice where none of it lines up perfectly. I've been doing vascular access and venous mapping work for over a decade, and the GSV still throws people when they need it most. Let's skip the fluff and talk about what actually matters when you're standing at a patient's leg with a probe in your hand. The greater saphenous vein begins at the dorsal venous arch of the foot. It runs anterior to the medial malleolus. This is the landmark everyone uses. It then travels up the medial aspect of the leg, posterior to the medial border of the tibia, continuing past the knee along the medial thigh before draining into the femoral vein at the saphenofemoral junction. The standard length is roughly 60 cm, but that number means nothing in practice because patient anatomy varies widely. The valve architecture is what actually determines utility. There are typically 7 to 10 valves along the GSV course. The most clinically relevant ones sit at the saphenofemoral junction, mid-thigh, and just above the knee. When you're assessing whether this vein is worth harvesting for coronary bypass or using for peripheral access, those valves matter more than any textbook diameter measurement.
The GSV is a superficial vein. It sits in the subcutaneous tissue layer, variable depth depending on body habitus. In thin patients it can be nearly subcutaneous at 2 to 3 mm depth. In obese patients it may lie 4 to 6 cm below the skin surface. This depth variation is why ultrasound guidance isn't optional if you want consistent results. One thing people consistently get wrong is the relationship between the GSV and the saphenous nerve. They run together for most of their course along the medial leg and thigh. The nerve is usually posterolateral to the vein. When you're doing a harvest or even a simple cannulation, damaging that nerve causes medial leg and foot paresthesia that can last months. I've seen this happen because the nerve was visually obscured by surrounding fat during a rushed dissection.
What Ultrasound Shows vs What Surgery Finds
Pre-procedural duplex scanning of the GSV is standard practice now, but the numbers on the screen don't always tell the full story. The vein needs to have an internal diameter of at least 3 mm to be considered viable for most applications. Below that, thrombosis rates climb sharply and graft failure becomes common. The flow velocity matters too. Normal GSV flow velocities are 5 to 20 cm/s in the supine position. Anything consistently above 30 cm/s suggests significant reflux or compensatory hyperflow. Here's the part textbooks don't emphasize enough: the GSV is compressible and phasic with respiration. If it's not, you already know there's pathology. But the converse is also important. A vein that looks patent on B-mode with good compressibility can still have significant valve incompetence that only shows up with Doppler and proper Valsalva maneuvering. I always scan in both supine and Trendelenburg positions and apply proximal compression to provoke retrograde flow if the clinical picture warrants it. The segmental mapping approach works best. Instead of just measuring the proximal and distal ends, I map the vein in 5 cm segments from the ankle to the femoral junction. This takes about 10 to 15 minutes and catches focal stenoses or segmental varicosities that would otherwise force you to abandon the vein mid-procedure.
Get the Full Details

A Specific Problem That Almost Wasted a Case
Last year I encountered a patient who needed a GSV harvest for a below-knee bypass. Pre-op duplex looked perfect. The vein was 5 mm throughout, compressible, with no visible reflux and normal phasic flow. We went to the OR, opened up, and found that about 8 cm above the medial malleolus the vein was completely fibrotic and non-compressible. The duplex had missed it because the calcified segment was isoechogenic to surrounding tissue and the sonographer hadn't done a segmental sweep with light transducer pressure. The workaround was straightforward but not obvious without experience. I took the ultrasound probe back to the bedside and used a high-frequency linear array with very light contact pressure. Under minimal compression, the fibrotic segment actually appeared hypoechoic compared to the surrounding normal vein walls. We marked the problematic area with a skin pen, adjusted our surgical approach to start the harvest more proximally, and avoided the bad segment entirely. The rest of the vein was fine and the graft performed well. This happened to me twice in three years. Both times the common duplex protocol failed to catch it because the sonographers were using standard pressure settings. Light touch with a high-frequency probe is the fix. It adds maybe two minutes to the scan but prevents catastrophic intraoperative surprises.
Course Variants You Need to Know About
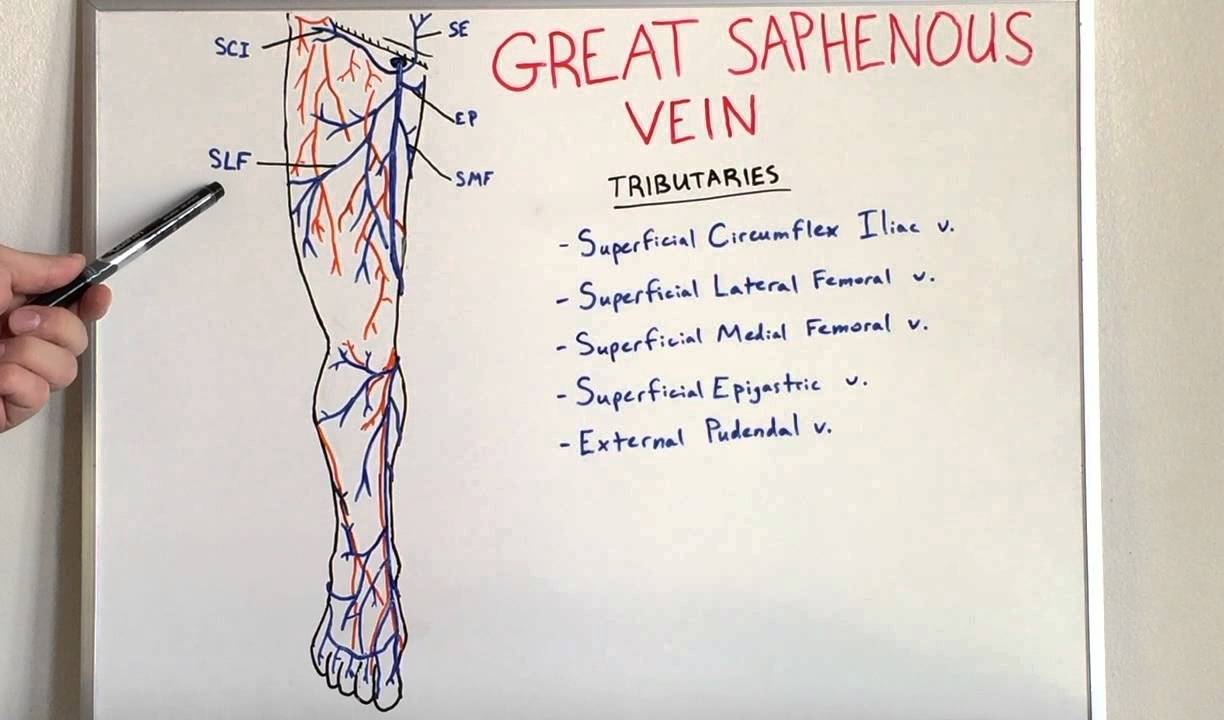
The classic description of the GSV is a straight medial path. Real anatomy is far less cooperative. Roughly 15 to 20% of limbs show some degree of anatomical variation. The most common variant is a bifid or duplicated GSV, which occurs in about 5 to 8% of cases. The duplication is most frequent in the proximal thigh near the saphenofemoral junction but can occur anywhere along the course. Another variant worth noting is the GSV that terminates into the deep system rather than the femoral vein. This happens in roughly 1 to 3% of cases and can cause significant confusion if you're operating based on standard anatomical assumptions. I've personally identified this on intraoperative ultrasound when the expected junction simply wasn't there and the vein continued laterally toward the profunda femoris. The peroneal or terminal tributaries can also vary. The posterior accessory saphenous vein drains into the GSV in about 30% of limbs and represents a common source of recurrent varicosity if it's not addressed during stripping or ablation procedures. Missing this tributary is one of the top reasons patients return with new varicose veins within two years.
Limitations and When the GSV Just Doesn't Work
The biggest limitation of the GSV as a conduit or access site is its tendency toward chronic venous insufficiency post-harvest. Up to 40% of patients report some degree of medial leg swelling or discomfort after GSV removal, though severe complications are uncommon. This isn't a problem if you're using the vein once and moving on, but it matters if you're preserving the GSV for future access. The vein also suffers from inherent qualities that make it less ideal than the small saphenous vein for certain applications. The GSV has a larger diameter but thinner walls and more variable valve architecture. For coronary artery bypass grafting specifically, some data suggest the radial artery or even the internal mammary artery may provide better long-term patency in certain patient subsets, particularly younger patients with higher graft flow demands. There are absolute contraindications that shouldn't be debated. Active infection in the GSV territory, known DVT involving the GSV, severe peripheral arterial disease with inadequate arterial inflow, and prior radiation to the limb all make GSV harvesting or cannulation a bad idea. The vein may also be unsuitable due to diffuse varicosity where the wall is too diseased to function as a conduit regardless of diameter measurements.

If the GSV is unavailable or unsuitable, the alternative pathways are limited. The arm veins, particularly the basilic and cephalic, serve as secondary options for bypass grafting but have lower long-term patency rates. The small saphenous vein is an option for shorter segment replacements but has limited length. For dialysis access, the brachiocephalic or brachiobasilic fistulas are the next step when GSV-based options are exhausted.
Practical Takeaways
Segmental ultrasound mapping with light compression takes 10 to 15 minutes and catches problems standard protocols miss. Always check for the posterior accessory saphenous vein and document its status. The saphenous nerve stays with the vein and should be visualized whenever possible during dissection. If the vein looks perfect on standard duplex but you're operating in a high-risk case, go back with a high-frequency probe and very light pressure. And remember that the textbook course is just the starting point, not the destination you'll actually find.