How to actually find and use heart anatomy diagrams without wasting time
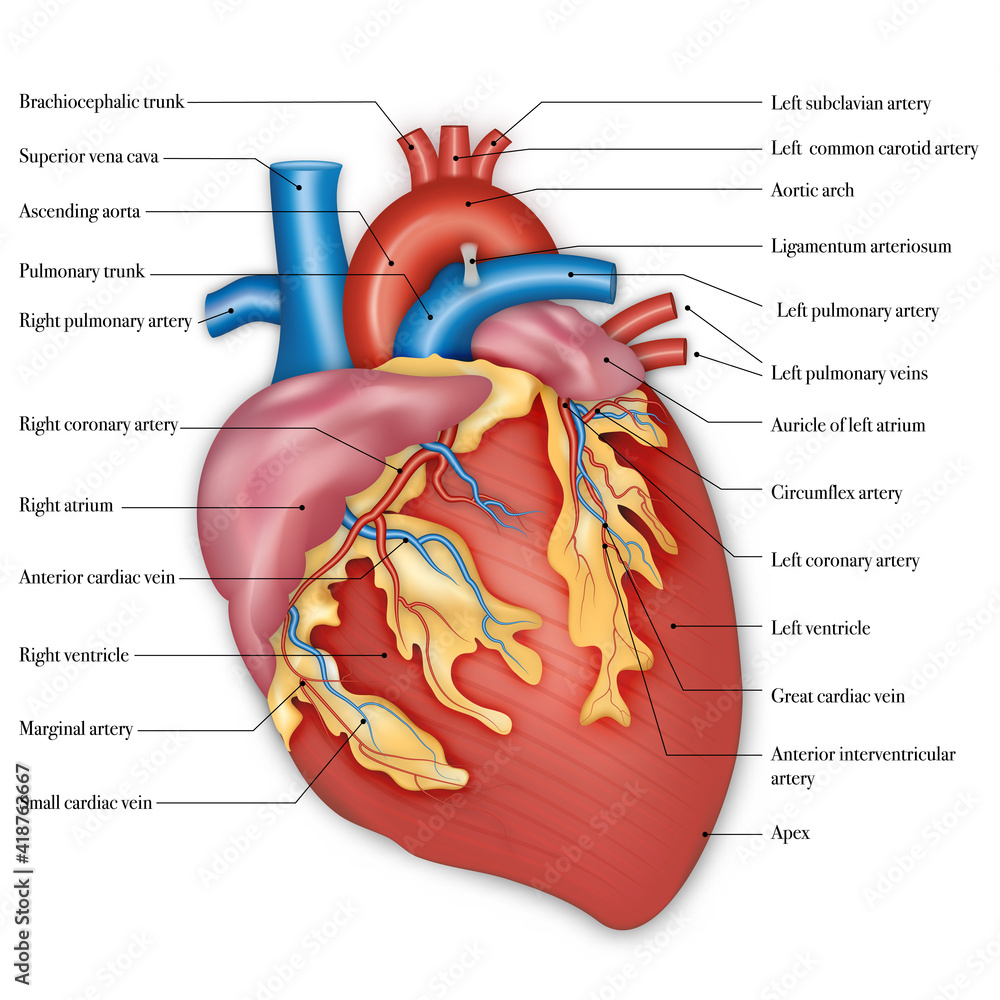
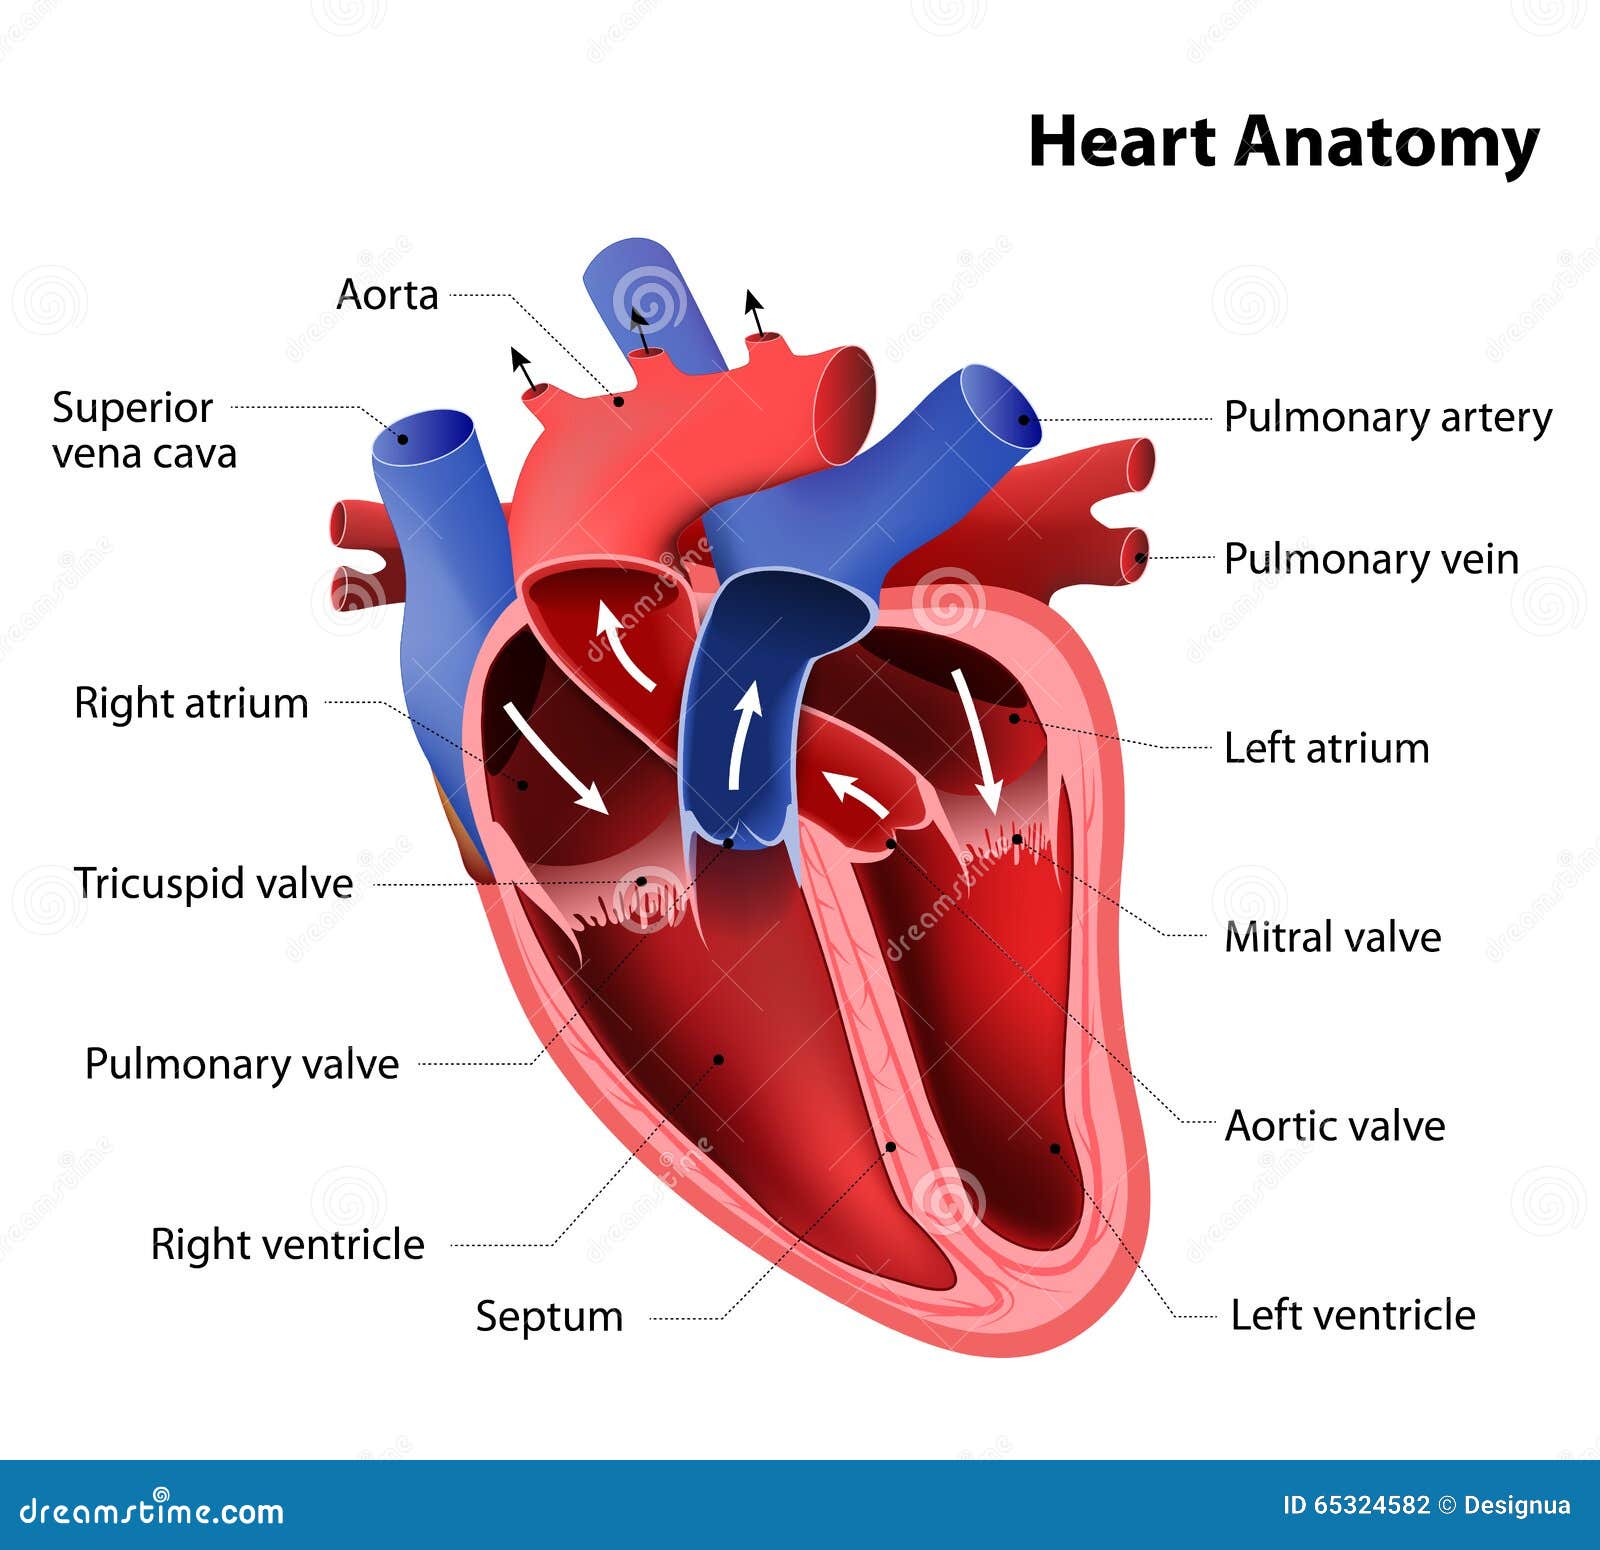
Most people looking for an Anatomy Of Heart Picture end up scrolling through three pages of low-res clip art or overly stylized illustrations that look nice but are anatomically wrong. The real problem isn't finding one — it's finding one that is accurate enough to be useful in a presentation, a study session, or a patient education handout. I spent about two weeks last year trying to track down a heart cross-section diagram that showed the coronary arteries with correct anatomical orientation. Every source I found had the right ventricle where the left one should be, or they labeled the pulmonary veins as arteries. It's surprisingly common. Cheap medical illustration packages recycle the same wrong base image across dozens of products. What actually works for me is starting at the Netter Atlas of Human Anatomy plate collection or the ProPublica Open Heart Diagrams project. Netter plates are licensed to universities, so if you have institutional access, go there first. If not, the Open Anatomy repository at openanatomy.org has DICOM-based 3D heart models you can screenshot at any angle. That's the workaround I used — instead of hunting for a 2D image, I rotated a 3D model to get the exact superior-inferior view I needed, then exported it as a PNG at 300 DPI.
For a quick free option that won't embarrass you in a clinical setting, the UCLA Cardiology Department PDF library has public-domain diagrams. The 2019 revision correctly labels the anterior interventricular artery as the LAD and shows its branches. I verified the nomenclature against the Terminologia Anatomica before using it, and it checked out.
What to check before you use any heart diagram
Not every labeled structure is in the right place. Here's the checklist I run through now: Chamber orientation. In standard anatomical position, the apex points left and inferior. If the pointy end is on the right side of the image, the diagram is either a radiological view (which is fine if you label it as such) or it's wrong. Radiological images flip the patient's left to your right, which trips up half the people who use them in patient education. Great vessel sequence. The aorta should exit from the left ventricle and arch posteriorly over the pulmonary trunk. If you see the aorta coming from the right ventricle, the image is showing transposition or it's just incorrect. Neither is useful unless that's the specific pathology you're illustrating.
Get the Full Details
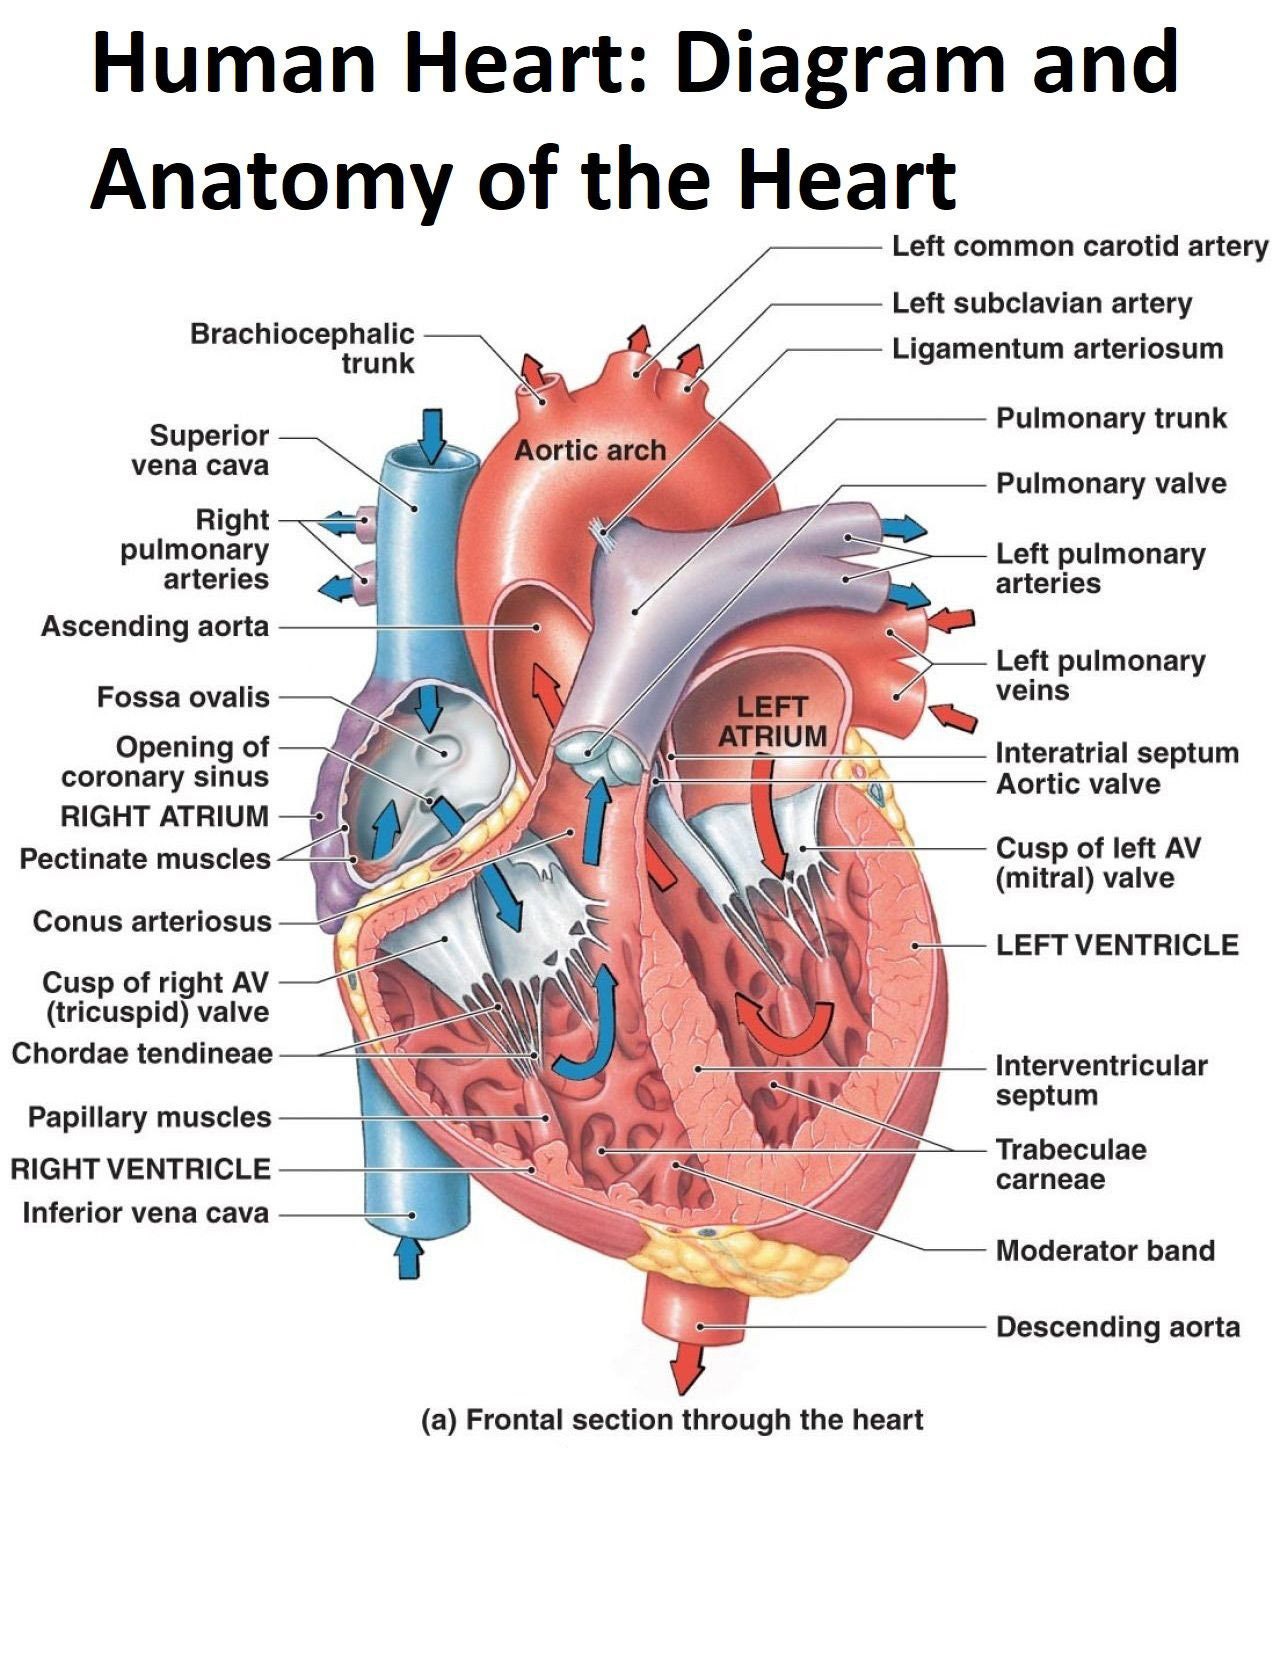
Coronary dominance. About 85% of people are right-dominant, meaning the posterior descending artery comes from the right coronary artery. Some diagrams default to left dominance without stating it. Check the PDA origin before you present it to anyone who knows cardiology. I once submitted a diagram to a hospital education committee that passed all these checks except one: the trabeculae carneae on the right ventricle were drawn with the coarse, irregular pattern typical of the left ventricle. The reviewer caught it. I re-exported from the 3D model and resubmitted. Two days of work lost over a texture detail. Don't skip the detail check.
When a static picture won't cut it
A flat diagram of the heart has inherent limitations. It can't show dynamic flow, valve timing, or the way the interventricular septum behaves during systole. If your audience needs to understand why aortic stenosis causes concentric hypertrophy, a still image gets you about 60% there before you start talking. In those cases, I recommend pairing the diagram with a short echocardiography clip from the ASE Image Library (ase.org — free with registration). A 15-second apical four-chamber view during systole teaches more than a labeled diagram because it shows the mitral valve leaflets coapting and the ventricular walls thickening in real time. The combination of static anatomy and dynamic function covers the gap without turning your presentation into a physiology lecture. Another case where a picture fails: congenital defects with complex spatial relationships. Double outlet right ventricle, transposition with VSD, truncus arteriosus — these are three-dimensional problems that 2D diagrams compress into something that looks almost right but isn't. The 3D Cardiac Modeling Project at childrenscardiology.org has interactive 3D reconstructions from CT scans of actual surgical cases. Free. Accurate. Worth the extra ten minutes to learn the interface.
The resolution trap
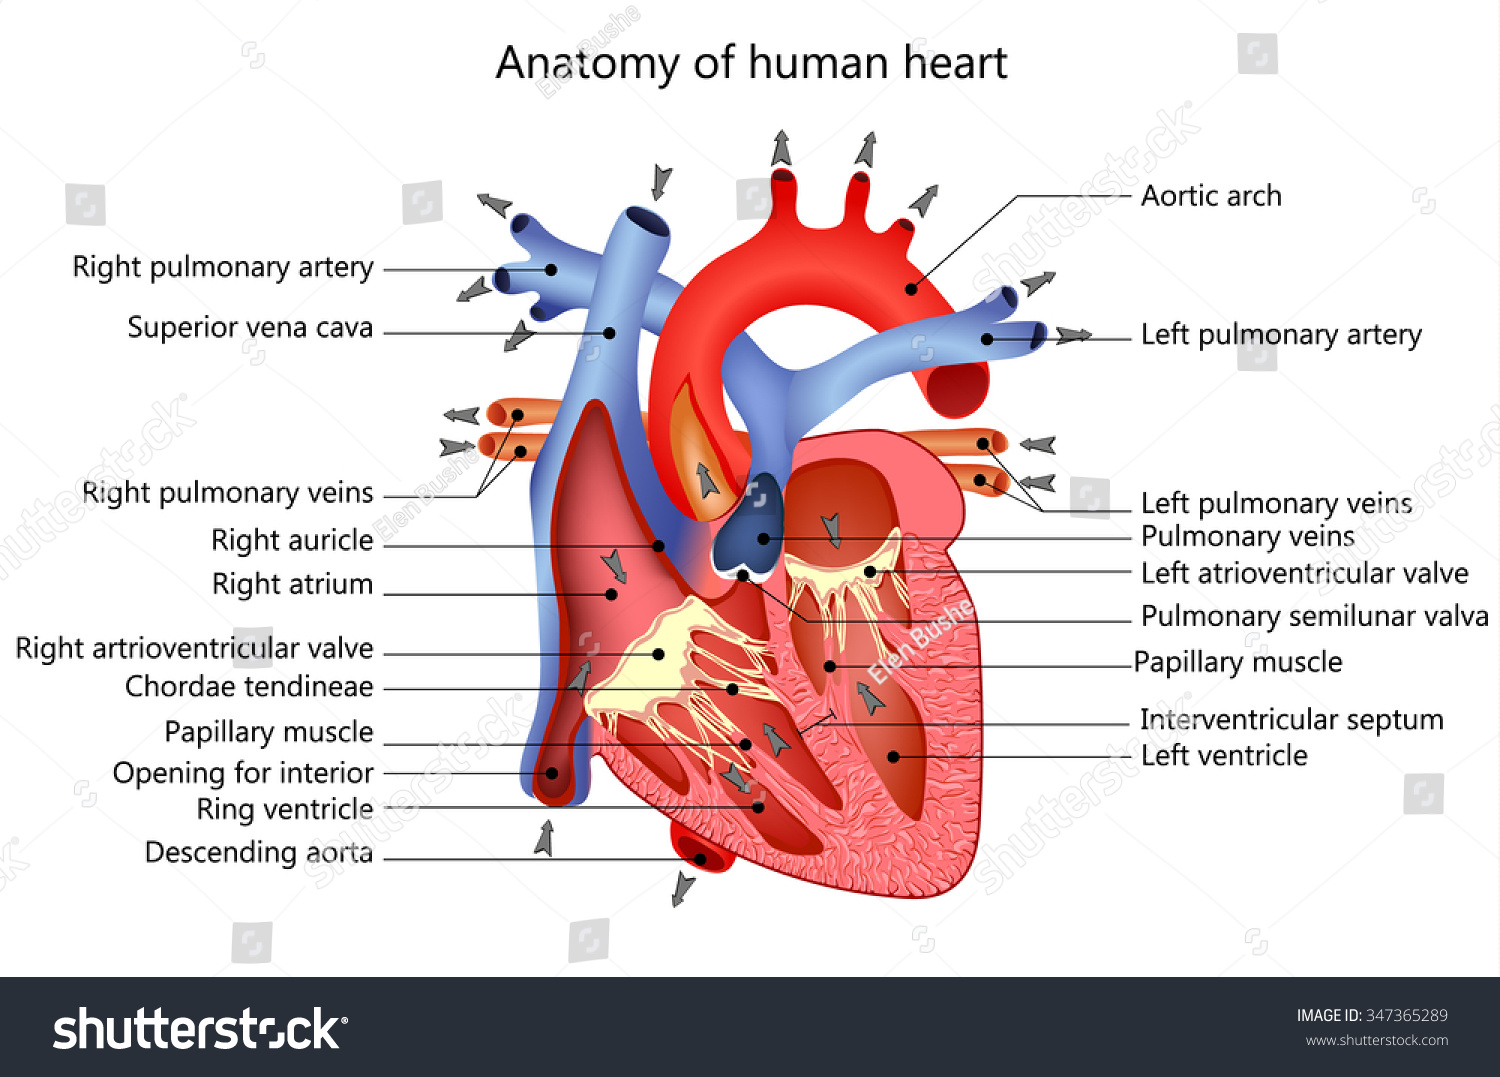
Here's something nobody tells you: a high-resolution image that is anatomically wrong is worse than a low-resolution one that is right. A blurry but accurate diagram from a textbook can be understood. A crisp but inverted diagram from a stock photo site will be cited in a slide deck for months, and nobody will correct you until someone who actually knows cardiology sees it. The rule I follow now: if I can't verify the source within five minutes, I don't use it. That means checking the author's credentials, the publication date, and whether the image has been peer-reviewed or adopted by an academic institution. An image from a 2017 radiology textbook will age better than one from a 2024 AI-generated stock art site, no contest. I learned this after a colleague used an AI-generated heart diagram at a grand rounds presentation and the attending physician pointed out that the sinoatrial node was drawn inside the myocardium instead of at the junction of the SVC and right atrium. The room went quiet. It was fixable, but the cost was higher than the time it would have taken to verify the source upfront.
File format and licensing
If you're using the image for anything beyond personal study, check the license. Netter plates require a separate reproduction license even if you bought the book. The Open Anatomy models are CC-BY, so you can use them freely with attribution. Hospital department PDFs vary — UCLA's are public domain, but Vanderbilt's require you to credit the department on the slide. For print materials, always request TIFF or PNG at 300 DPI minimum. JPEG introduces compression artifacts around the vessel boundaries that become visible when projected at 16:9. I converted a JPEG I'd been using for two years to PNG and the color separation between the red oxygenated vessels and blue deoxygenated ones sharpened noticeably on a large screen. Cheap fix, real difference.
Summary of what matters
Find the image from a verified academic or clinical source. Check chamber orientation, great vessel sequence, and coronary dominance before you use it. Pair static diagrams with dynamic clips when function matters. Verify licensing if you're reproducing. And always prefer a lower-resolution image you've vetted over a high-resolution one you haven't. The effort is ten minutes. The cost of getting it wrong is much higher.