Why Your Lower Back Hurts When You Sit For More Than Twenty Minutes
The anatomy of hips and lower back is not two separate systems. They work as a continuous kinetic chain, and most people treat them as if they don't share any responsibility for each other. I spent years watching physical therapists, strength coaches, and chiropractors argue over whether hip tightness or lumbar stability was the primary problem. Both sides were right, and both sides were wrong. The issue is almost never isolated to one region. When I first started studying this, I was working with athletes who had recurring lower back pain that no amount of core training fixed. We tried everything. Planks, deadlifts, bird dogs, McGill's big three. One guy, a marathon runner in his early thirties, came in with what looked like classic lumbar strain. He could not sit through a movie without needing to stand up and walk around. We eventually discovered his hip flexors were so shortened from years of being in a seated position that his pelvis was locked into an anterior tilt. His lumbar spine was held in constant extension just to keep him upright. Every time he bent forward, his lumbar discs were getting compressed before his hips even began to flex. Fixing the hip flexors alone didn't solve it, but it removed the primary driver. That took about six weeks of consistent work.
Anatomy Of Hips And Lower Back — What Actually Connects Them
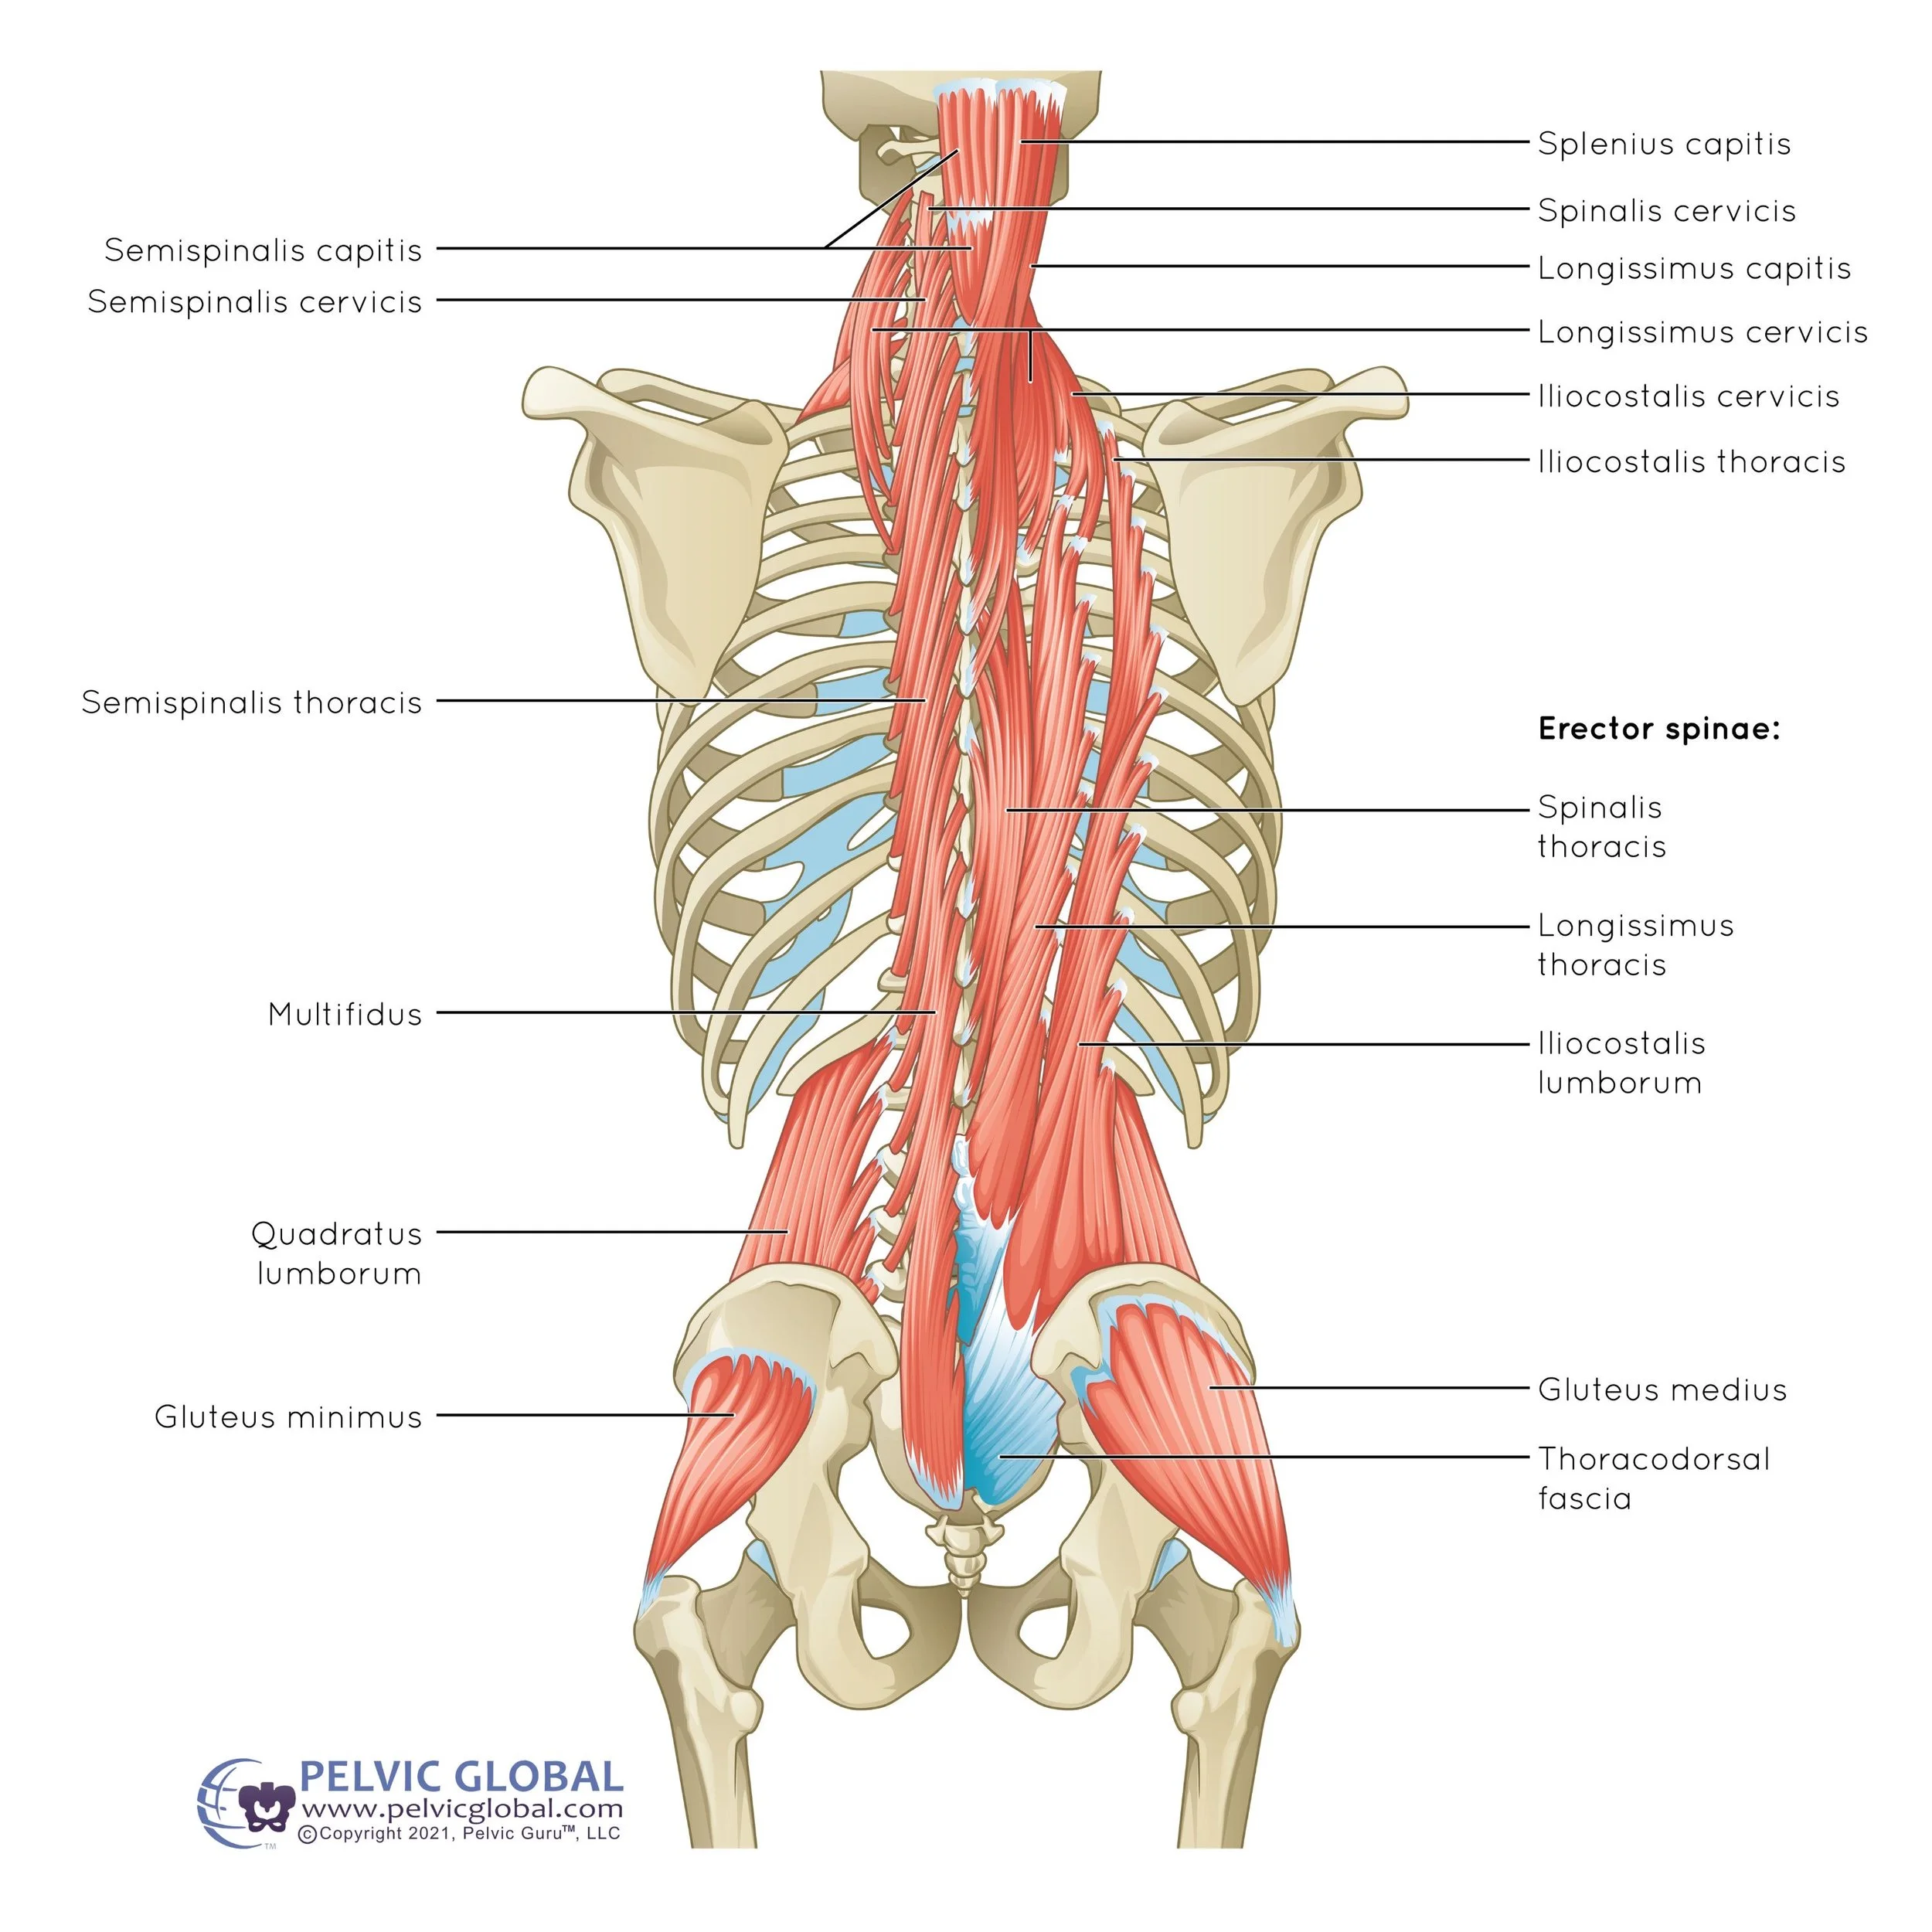
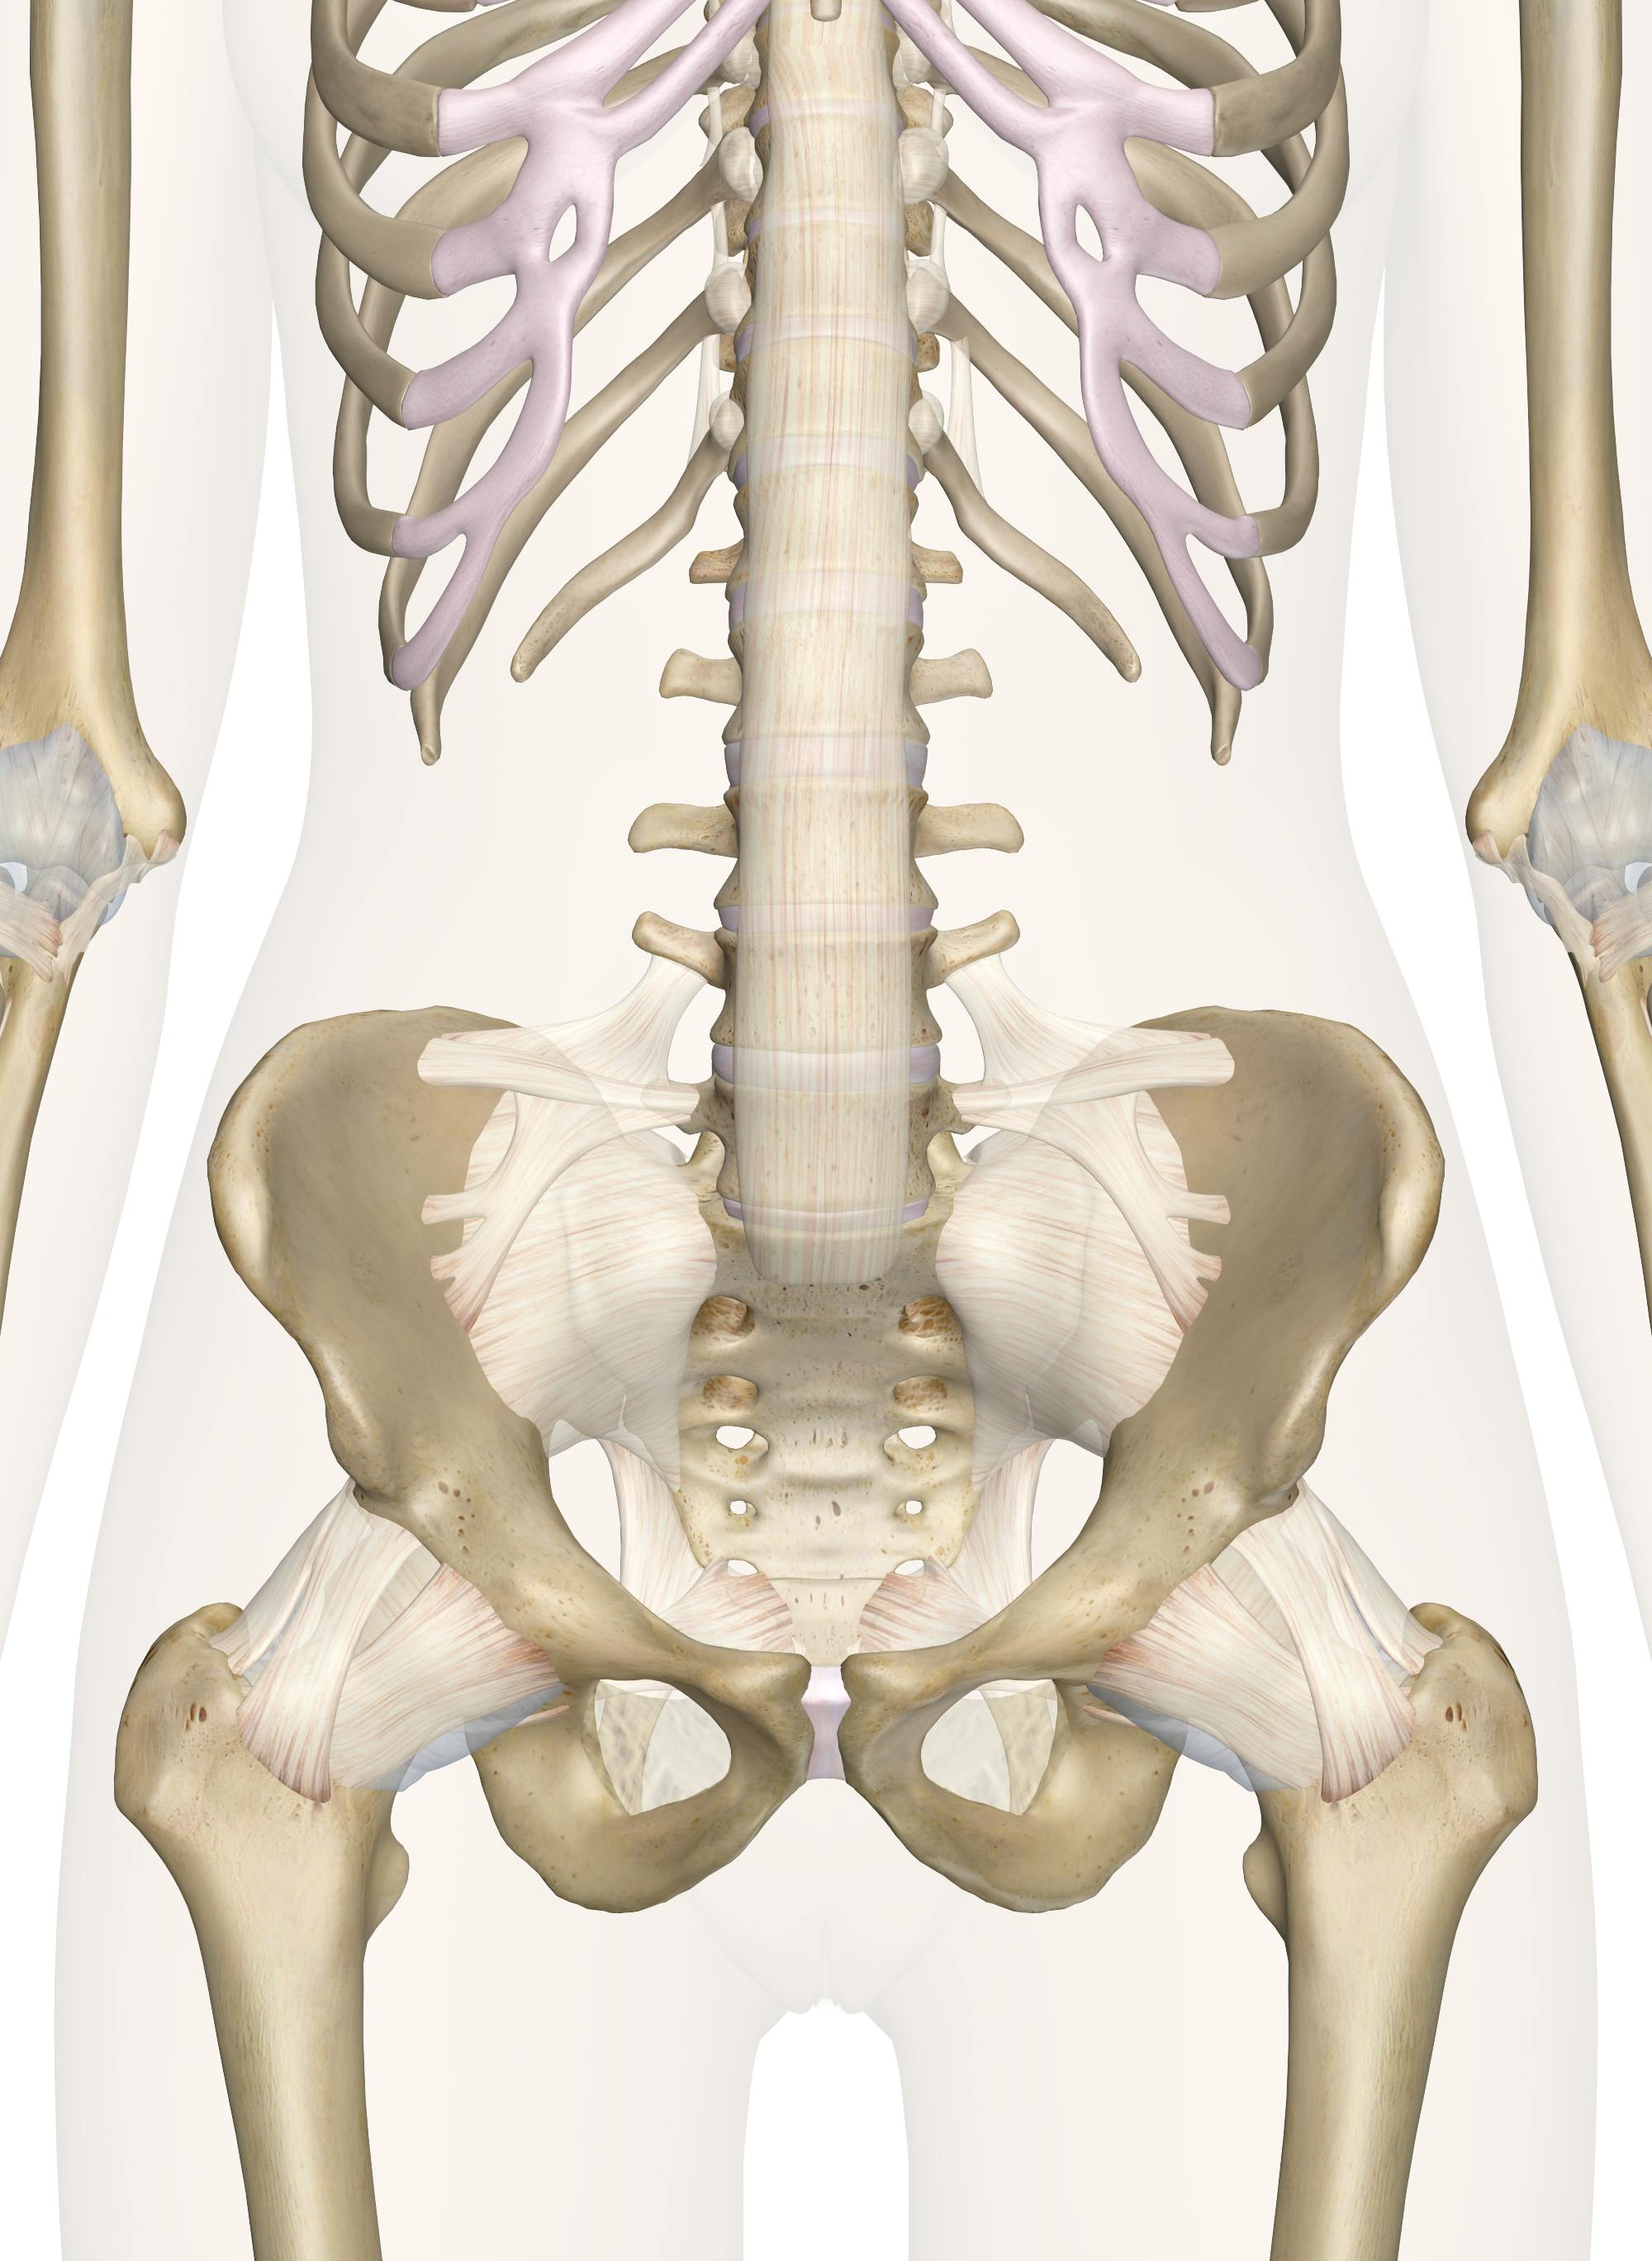
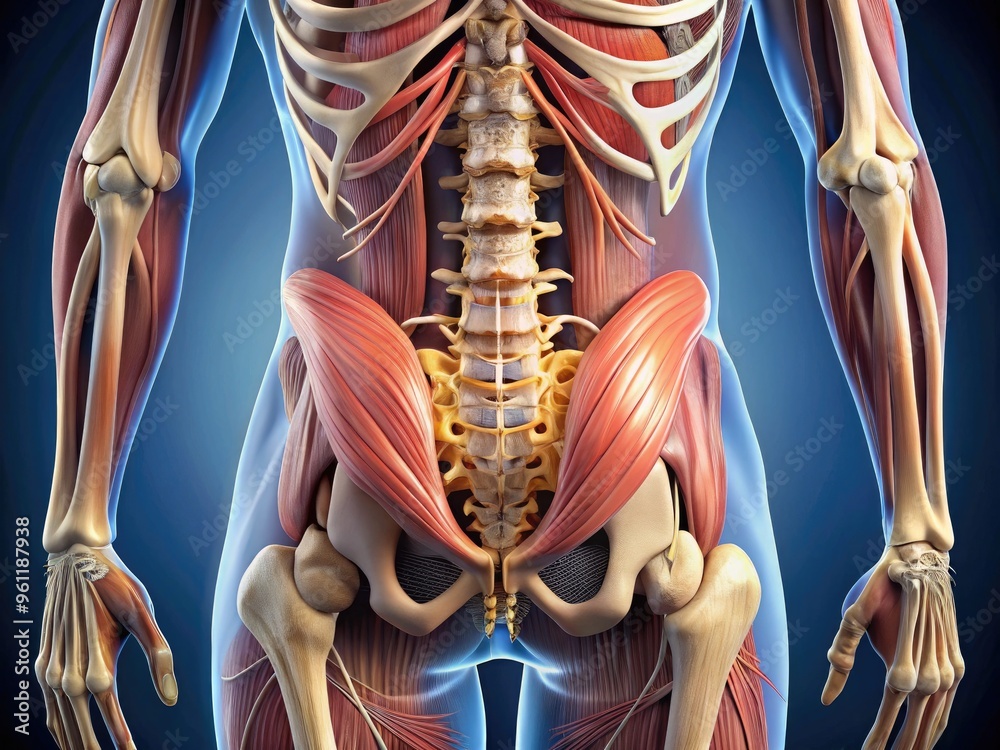
The lumbar spine consists of five vertebrae, L1 through L5, sitting on top of the sacrum, which is fused to the ilium of the pelvis. The connection between L5 and S1, the lumbosacral junction, bears the most mechanical load in the entire spine. This is where the spine transitions from mobile to fixed, and it is also where most disc issues occur. The hip joints sit just anterior to this junction, separated by muscle layers and fascial planes. The psoas major originates from the transverse processes and vertebral bodies of T12 through L5, then travels down and merges with the iliacus to insert on the lesser trochanter of the femur. This means the psoas directly connects the lumbar spine to the hip. When the psoas is tight or short, it pulls the lumbar vertebrae into flexion and the femur into extension simultaneously. The net effect is increased lumbar lordosis and reduced ability to posteriorly tilt the pelvis. Most people who sit all day have a psoas that has adapted to a shortened length. It becomes hypertonic not because it is strong, but because it has been chronically lengthened under tension and then adapted to a shorter range. The erector spinae and multifidus are the primary extensors of the lumbar spine. They attach along the posterior elements of each vertebra and insert into the ribs, skull, and nearby structures. Their job is to prevent the trunk from collapsing forward. When the hip extensors, specifically the gluteus maximus, are weak or inhibited, the erectors and multifidus compensate by working harder to maintain upright posture. This leads to fatigue, spasm, and eventually pain. The gluteus maximus is the largest muscle in the body and it is almost universally underactive in people who spend significant time sitting. You can test this easily. Have someone lie on their stomach and try to lift their leg against resistance. If the lower back takes over instead of the glute, you have found the pattern.
The QL, or quadratus lumborum, is another structure that deserves attention. It runs from the top of the iliac crest to the twelfth rib and the transverse processes of L1 through L4. It stabilizes the 12th rib during breathing and laterally flexes the lumbar spine. When someone has unilateral hip hiking or favors one side when standing, the QL on the dominant side becomes overworked. I had a client who developed sharp right-sided low back pain after adopting a new squat routine. She was asymmetrically loading the bar and her right QL was taking up the slack. Once we corrected the bar placement and added single-leg work, the pain decreased significantly within three weeks. The fascia connecting these regions matters more than most people realize. The thoracolumbar fascia is a dense connective tissue sheet that covers the deep muscles of the lower back and connects to the gluteus maximus and the latissimus dorsi. Forces from the legs, arms, and trunk all pass through this aponeurosis. Tight lats can pull on the thoracolumbar fascia, which in turn pulls on the lumbar spine. A client of mine couldn't improve her deadlift form despite weeks of coaching because her lats were so restricted that she couldn't engage them properly. Once we addressed the lat mobility, her lumbar positioning during the lift changed dramatically.
Get the Full Details
How The Hip Spine Relationship Affects Movement
The hip joint is a ball-and-socket with roughly 120 to 130 degrees of flexion available in a healthy individual. The lumbar spine contributes about 40 to 45 degrees of flexion across all five vertebrae. When you bend forward to pick something up, a person with good hip mobility will flex primarily at the hip, keeping the lumbar spine relatively neutral. A person with restricted hip flexion will compensate by rounding the lower back. This shifts load from the hip extensors to the posterior lumbar structures, including the discs, ligaments, and facet joints. The anterior pelvic tilt is the most common postural adaptation I see. It is characterized by increased lumbar lordosis, protruding abdomen, and shortened hip flexors. The posterior pelvic tilt shows the opposite pattern: flattened lumbar curve, tucked pelvis, and often tight hamstrings. Neither extreme is ideal. The goal is neutral pelvis, which is roughly defined as the position where the ASIS and the pubic symphysis sit in the same vertical plane when standing. In practice, this varies between individuals and depends on bone structure. Pregnancy changes this relationship permanently for many women. The increasing weight of the uterus shifts the center of gravity forward, forcing compensatory changes in lumbar curve and hip positioning. Even after delivery, some women retain altered hip and lumbar mechanics. I worked with a postpartum client whose lower back pain returned two years after birth because her glute medius had never recovered its activation pattern. She was walking with a Trendelenburg gait without realizing it, and her lumbar spine was absorbing lateral forces it was never designed to handle.
Assessment Without Overcomplicating It
You do not need an MRI to understand most hip and lower back issues. A basic movement assessment reveals more than imaging in many cases. Start with a squat. Watch how the person moves. Do the heels lift? Does the lumbar spine round excessively? Does one knee cave inward? These are all data points. The Thomas test checks hip flexor length. Have the person lie supine at the edge of a table, pull one knee to the chest, and observe the other leg. If it lifts off the table or cannot stay extended, the hip flexors on that side are tight. The straight leg raise assesses hamstring and sciatic nerve mobility. If someone gets sharp pain before reaching 70 degrees, there is likely neural involvement rather than simple muscle tightness. Standing flexion test helps identify which side of the pelvis is restricted during forward bending. Place your hands on the posterior superior iliac spines and have the person bend forward. One PSIS will move more than the other if there is a somatic dysfunction. This is a crude but useful screening tool. It should not be used in isolation, but it gives you direction.
Palpation of the L5-S1 junction, the sacroiliac region, and the greater trochanter can reveal tenderness patterns. The gluteus medius insertion on the greater trochanter is a common source of referred pain to the lateral hip and lower back. I remember one client who had been treated for sciatica for months without relief. The actual problem was greater trochanteric pain syndrome from chronic gluteus medius tendinopathy. Once we redirected treatment toward that structure, her symptoms improved enough that she no longer needed the neuropathic medications she had been on.
Intervention Strategy
The order of operations matters. Release first, then strengthen, then integrate. If you strengthen a muscle without addressing the restrictions that caused the imbalance in the first place, you are just reinforcing bad movement patterns. For hip flexor release, I prefer PNF stretching over static holds. The contract-relax technique, where the person contracts the hip flexor against resistance for five seconds and then relaxes into a deeper stretch, tends to produce more lasting changes than passive stretching alone. Do three to five repetitions on each side, holding each contraction for five seconds. This usually takes about ten minutes per session. Glute activation requires a different approach. Band walks, clamshells, and single-leg bridges are standard tools, but the key is progression. Start with bodyweight only. Only add resistance when the movement quality is consistent. I have seen too many people add band resistance to a glute bridge before they could even perform a proper bodyweight bridge. The lumbar spine compensates immediately, and the glutes remain dormant.
Lumbar stabilization work should focus on anti-extension and anti-rotation. Dead bugs and pallof presses are effective because they challenge the core without loading the spine in flexion. A client of mine was doing hundreds of crunches daily for lower back pain. The crunches made things worse because they loaded the lumbar spine in flexion, which is the exact position she needed to avoid. Switching to dead bugs and focusing on rib cage control reduced her pain within two weeks. For the QL, lateral bending stretches and side-lying hip abductions help. The stretch is simple: stand with feet hip-width apart, reach one arm overhead and lean to the opposite side until you feel tension along the lateral trunk. Hold for thirty seconds. Repeat three times per side. Do not bounce. The QL responds poorly to aggressive stretching and more to sustained, gentle load.
What I Wish People Understood Earlier
The biggest misconception is that hip problems cause back pain or back problems cause hip pain. The reality is that both are usually symptoms of the same underlying issue: poor movement quality from prolonged sitting and inadequate lower body strengthening. The hips and lower back are codependent. You cannot fix one without addressing the other. Another thing that surprises people is how much the thoracic spine affects the lumbar spine. If the upper back is stiff, the lower back has to move more than it should to compensate. I had a client whose lower back pain was resolved simply by improving her thoracic extension mobility. She spent most of her day at a desk, and her thoracic spine had adapted to a rounded position. Once we added foam rolling and extension work for the upper back, her lumbar spine stopped trying to make up for the lack of thoracic movement. There is also the breathing connection. The diaphragm attaches to the lumbar vertebrae through the crura. Shallow chest breathing keeps the diaphragm in a partially shortened position, which increases lumbar extension and reduces pelvic floor coordination. Diaphragmatic breathing, practiced for five minutes daily, can improve lumbar-pelvic rhythm over time. It sounds simple, but most people do not breathe correctly, and it shows up in their movement.

Anatomy Of Hips And Lower Back — Where This Approach Falls Short
The practical application I described works well for mechanical, non-specific lower back and hip pain. It does not work for structural pathologies. A herniated disc with radiculopathy, spinal stenosis, spondylolisthesis, or fractures require medical evaluation and often different treatment entirely. Stretching a hip flexor will not fix a nerve root compression caused by a disc bulge pressing on the L5 nerve root. I learned this the hard way when a client insisted on continuing hip mobility work despite having positive straight leg raise findings bilaterally with neurological symptoms. He needed imaging and a referral, not more stretches. He delayed treatment for three months and ended up with a surgical intervention that could have been avoided with earlier diagnosis. Another limitation is that these protocols assume the person can perform the movements correctly. Someone with severe obesity, advanced arthritis, or post-surgical restrictions may not be able to do a squat, a dead bug, or a single-leg bridge. Modification is necessary, and the modifications themselves require knowledge. Generic YouTube videos are not sufficient for this population. The timeline is also variable. Some people see improvement in two to three weeks. Others take three to four months. It depends on duration of symptoms, compliance, age, body composition, and whether there is ongoing mechanical irritation. There is no universal timeline, and anyone promising rapid results is oversimplifying the situation.
Finally, the hip and lower back relationship is not the only factor. Foot mechanics, ankle dorsiflexion, and scapular stability all feed into this chain. If you address the hips and lumbar spine in isolation while ignoring a severe ankle mobility restriction, the compensation will simply move elsewhere in the chain. The system is interconnected, and treating one link without considering the others often leads to partial or temporary improvement at best.