
So you want to understand the brain. Let's get practical.
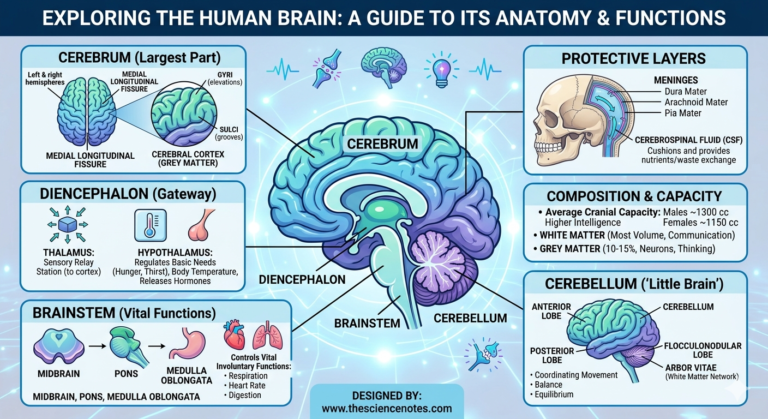
The Anatomy Of Human Brain And Its Functions is one of those topics that sounds straightforward until you actually try to teach it or apply it clinically. The brain isn't a neat collection of labeled parts where each piece does exactly one thing. That was the first misconception I had when I was studying neuroscience, and it took me months to unlearn it. Here's what actually matters when you're trying to work with this material. The human brain weighs roughly 1.4 kilograms in an adult. It contains about 86 billion neurons and a comparable number of glial cells. The gross anatomy breaks into the cerebrum, cerebellum, and brainstem, but the interesting stuff lives at the intersection of these structures and in the white matter tracts connecting them. The cortex is six-layered gray matter folded into gyri and sulci. That folding increases surface area so you can fit about 2.5 square meters of cortical tissue inside a skull that barely holds it. Without the folds, you'd lose about two-thirds of your cortical neurons. This is why premature babies are born with smoother brains and gradually develop their characteristic ridges over the first year.
The deeper structures include the thalamus, which acts as a relay station for almost all sensory information except smell. It sits above the brainstem and sends processed signals outward to the appropriate cortical regions. Then there's the basal ganglia, a cluster of nuclei involved in motor control, habit formation, and reward processing. The hippocampus sits in the medial temporal lobe and is critical for forming new declarative memories. The amygdala processes emotional salience, particularly fear, and interfaces heavily with the hippocampus during stress responses. I spent weeks working through neuroanatomy textbooks before I could consistently identify every structure on an MRI slice. The problem is that textbooks show idealized diagrams. Real brains have individual variation, and pathologies make everything messier.
Functions Are Distributed, Not Localized
The most important thing people miss is that functional localization is far more nuanced than introductory courses suggest. Yes, Broca's area handles speech production and Wernicke's area handles comprehension. But these areas don't work alone. They communicate through the arcuate fasciculus, a white matter tract, and they coordinate with premotor cortex, supplementary motor area, and subcortical structures to produce even a simple sentence. Here's a counter-intuitive point: damage to a single small region rarely eliminates a function entirely because other circuits compensate over time. I once worked with someone who had a tumor removed from their left temporal lobe. Pre-surgery, they had moderate anomia trouble naming objects. Post-recovery, their naming scores improved to near-normal despite significant tissue loss. The right hemisphere had gradually taken over some of the lexical retrieval workload. This kind of plasticity is real but time-dependent. It works best in younger patients and degrades with age. Another thing beginners consistently get wrong is how the cerebellum works. It's not just for balance. It contains about 69 percent of the brain's neurons and is essential for timing, motor learning, and even cognitive sequencing. Players who only think of it as a coordination center are leaving a huge chunk of its function unexplained.
Get the Full Details

How The Vascular System Shapes What You Study
You cannot understand brain anatomy without understanding blood flow. The brain uses roughly 20 percent of the body's oxygen despite being only 2 percent of body weight. The circle of Willis provides redundant arterial supply, which is why some strokes are less devastating than they could be. But collateral circulation varies between individuals, and some people simply don't have a complete circle. I've seen cases where a routine angiogram revealed an incomplete posterior communicating artery, and that changed the entire surgical approach for an aneurysm repair. The blood-brain barrier is another structure that gets oversimplified. It's not a wall. It's a selective interface formed by tight junctions between endothelial cells in capillaries, supported by astrocyte foot processes. Some regions like the area postrema and the choroid plexus have fenestrated capillaries where the barrier is naturally thinner. This matters for drug delivery and for understanding why certain toxins affect the brain more readily than others.
Common Pitfalls When Studying This Material
The biggest mistake I see is treating neuroanatomy as a memorization exercise. Rote learning the names of cranial nerves without understanding their pathways leads to fragile knowledge. If you forget a detail under pressure, you have nothing to fall back on. Instead, trace pathways. Start with a sensory signal entering through a nerve and follow it all the way to its cortical destination. The pathway itself tells you more than any list of functions. A second pitfall is ignoring scale. Microscopic anatomy matters for clinical work. The difference between a glioblastoma and a meningioma isn't just a label. One invades surrounding tissue and follows white matter tracts. The other compresses the brain without crossing into it. Surgical resection strategies are completely different for each. I once spent three days trying to locate a lesion on a DWI scan that didn't match any textbook presentation. It turned out to be an unusual demyelinating plaque in the transition zone between the internal capsule and the thalamus. Standard atlases don't cover this well because individual anatomy varies. The workaround was pulling up a high-resolution histology atlas and cross-referencing fiber tract orientations. It took longer but saved me from misdiagnosing it as a lacunar infarct.
What The Current Research Actually Says
The connectome project mapped structural connections in the human brain, but mapping connections is not the same as mapping function. We still don't have a complete wiring diagram for any mammalian brain at synaptic resolution. New techniques like diffusion tensor imaging and functional MRI have improved things, but both have limitations. DTI infers white matter tracts from water diffusion patterns and can miss crossing fibers. fMRI measures blood oxygenation as a proxy for neural activity, and that proxy is indirect and noisy. The default mode network is another area where the literature has grown ahead of the evidence. It's a set of brain regions that activate during rest and deactivate during focused tasks. The term gets thrown around as if it explains consciousness or self-reference. It doesn't. It correlates with internally directed thought, and that's it. Don't let popular articles inflate what we actually know.
Practical Resources That Actually Help
Northuss Neuroanatomy Atlas is one of the better free resources online. It has interactive cross-sections that let you navigate through the brain systematically. For three-dimensional understanding, Complete Anatomy and Visible Body are useful, though they cost money. If you're studying for exams, Netter's Atlas of Neuroscience combined with Snell's Clinical Neuroanatomy covers the clinical correlations that most other atlases skip. The Gray's Anatomy Student Edition remains useful for gross anatomy, but don't rely on it for functional details. It predates much of what we've learned about networks and connectivity.
When This Knowledge Fails You
Even thorough anatomical study won't prepare you for every case. Personalized brain tumors, congenital malformations like Chiari malformations, and traumatic injuries often distort standard landmarks enough that textbook anatomy becomes unreliable. In those situations, you need intraoperative imaging and neuronavigation systems rather than relying on memory. No amount of reading replaces that kind of real-time spatial assessment. The same applies to functional recovery predictions. You can map every structure and still not know how well a patient will recover. Recovery depends on age, pre-injury cognition, rehabilitation intensity, and luck. The brain's adaptive capacity is real but unpredictable.
A Note On Terminology
Modern neuroanatomy has moved away from strict Brodmann area definitions toward network-based descriptions. If you're studying older materials, you'll see heavy reliance on Brodmann areas. They're still referenced, but the field treats them as approximate cytoarchitectonic zones rather than functional units. Keeping that distinction in mind prevents confusion when newer papers describe the same regions with different labels. The lateral ventricles, third ventricle, and fourth ventricle form the cerebrospinal fluid system. The ventricles aren't just empty spaces. They're lined with ependymal cells and connected by the cerebral aqueduct and foramina of Monro and Luschka. Obstruction anywhere in this system causes hydrocephalus, and the type of obstruction determines whether you're dealing with communicating or non-communicating hydrocephalus. That classification changes treatment entirely. If you're approaching this topic for the first time, start with the brainstem and work upward. The stem is evolutionarily older and its structures are more consistent across individuals. Building from there gives you a stable foundation before you tackle the highly variable cortical and subcortical regions.


