Working With Human Head Anatomy: What You Actually Need to Know
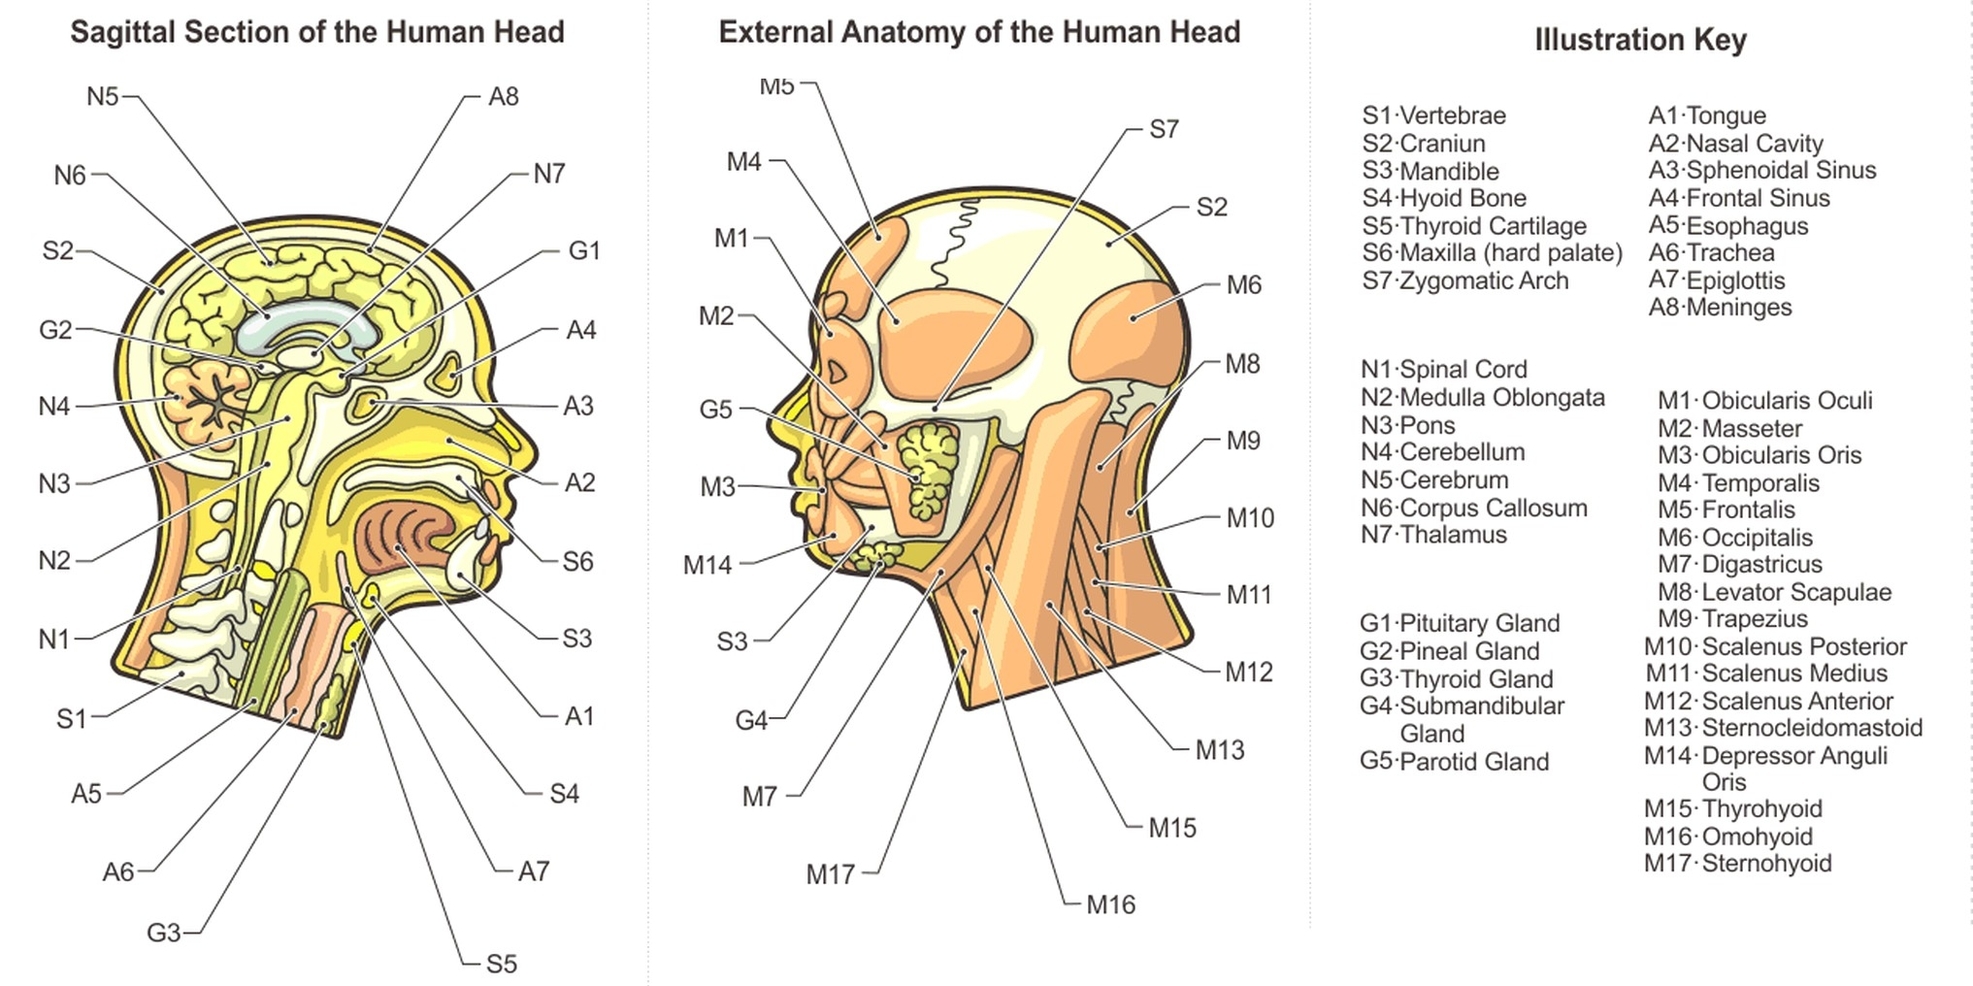
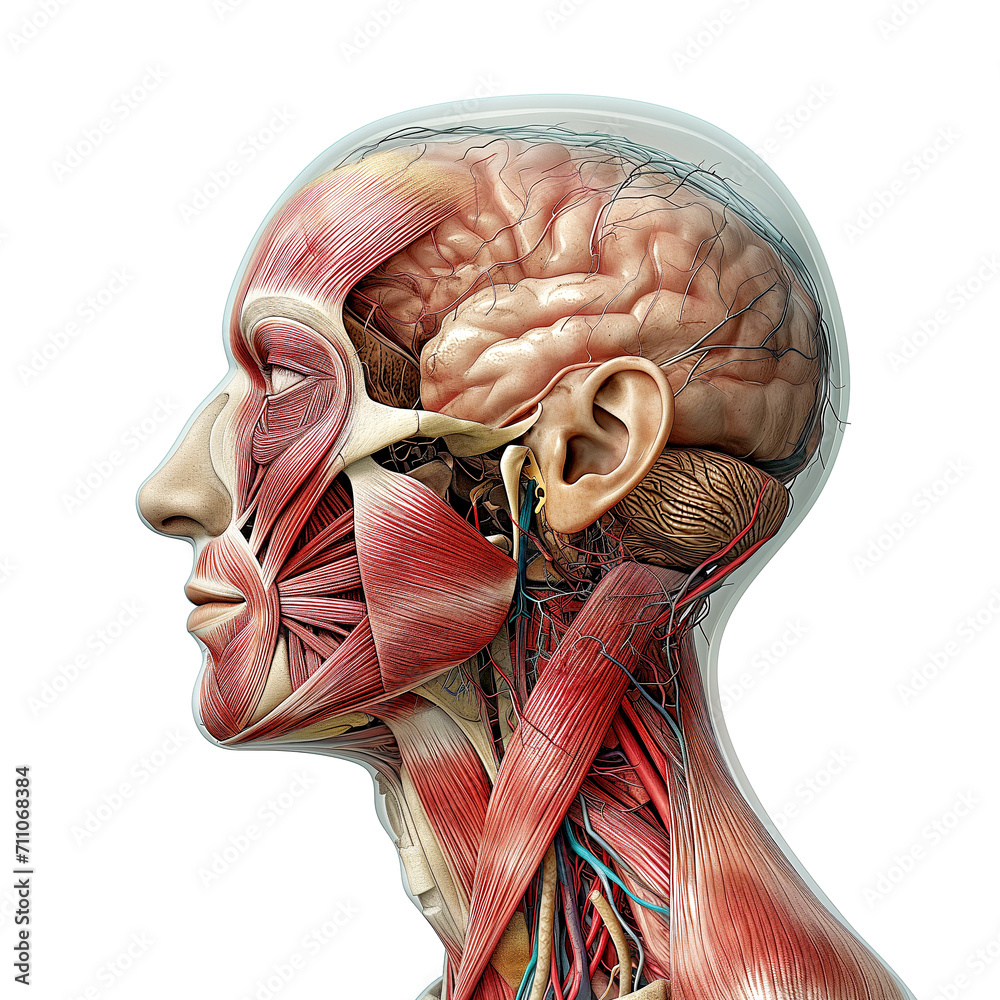
The human head is a compact assembly of twenty-six bones in the cranium, fourteen in the face, thirty-two teeth, six extraocular muscles per eye, and roughly fifty-four muscles of facial expression. That is not an exhaustive list but it gives you the scale of what you are dealing with when you actually open an anatomy reference or look at a CT scan. Most people encounter this subject through illustrations in textbooks or 3D model files online, and the illustrations are usually far cleaner than anything you will see in clinical practice. Start with the calvaria, the skull cap. It is made of eight bones: frontal, two parietal, two temporal, occipital, sphenoid, and ethmoid. The sutures between them interlock in irregular patterns. Sagittal suture runs anterior to posterior along the midline between the parietals. Coronal suture connects the frontal bone to both parietals. Lambdoid suture does the same posteriorly between the occipital and parietals. These are not decorative lines; they are growth zones in children and fusion points that radiologists read for trauma or pathological calcification. The facial skeleton consists of the maxillae, zygomatic bones, nasal bones, vomer, inferior nasal conchae, mandible, and the palatine bones. The mandible is the only mobile bone of the skull in a healthy adult. The temporomandibular joint sits about one centimeter anterior to the external auditory meatus and bears the brunt of chewing forces, which can reach 700 newtons at the molars in clenching.
The cranial fossae divide into anterior, middle, and posterior compartments. The anterior fossa houses the frontal lobes and supports the olfactory bulbs. The middle fossa is where the temporal lobes rest and contains the sella turcica, a saddle-shaped depression that holds the pituitary gland. The posterior fossa is the smallest compartment but contains the largest structure inside it: the cerebellum and brainstem. This compression is why posterior fossa bleeds are so dangerous even at small volumes. Blood supply comes primarily from the internal carotid arteries and the vertebral arteries, which join to form the basilar artery. The circle of Willis is an anastomotic ring at the base of the brain that provides collateral flow. About twenty percent of the population has an incomplete circle, meaning one vessel becomes the sole supply for a region. If you are studying vascular anatomy, do not assume completeness. Venous drainage is equally important and more easily damaged than arterial supply. The dural venous sinuses run between layers of the dura mater. The superior sagittal sinus follows the midline of the calvaria internally. The transverse sinuses sweep laterally from the confluence of sinuses at the internal occipital protuberance. These sinuses are valveless, which is why intracranial pressure changes anywhere in the system affect the whole network.
The trigeminal nerve (CN V) is the major sensory nerve and has three divisions: ophthalmic (V1), maxillary (V2), and mandibular (V3). V1 exits through the superior orbital fissure. V2 passes through the foramen rotundum. V3 exits via the foramen ovale. These foramina are landmark structures on CT scans and CT angiography. If you are reading imaging, memorizing the foramina speeds up identification considerably.
Get the Full Details
Practical Workflows for Studying or Using Head Anatomy
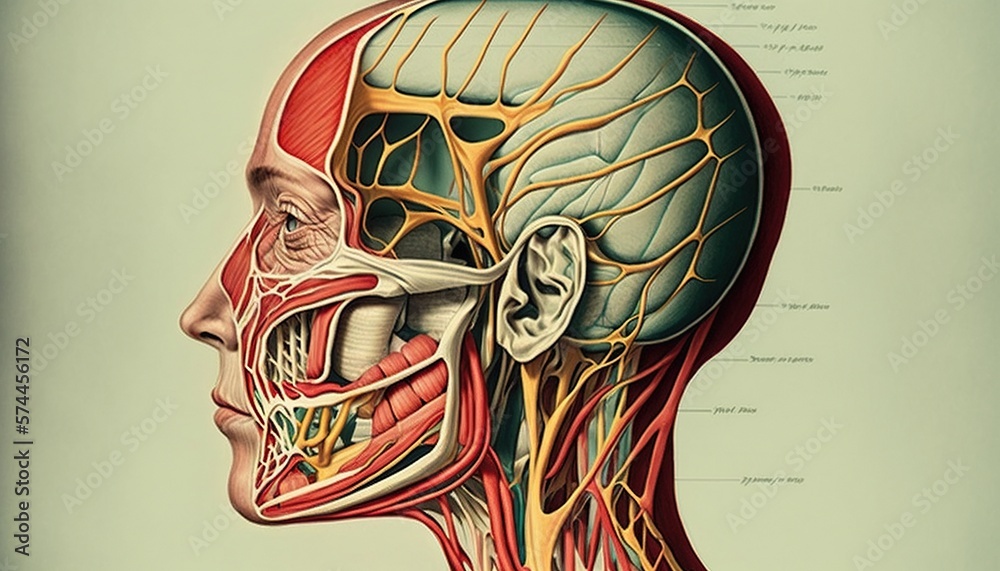
If you are building a 3D model from DICOM data, the first step is segmentation. Threshold the bone window at around 300 to 2000 Hounsfield units and the soft tissue window separately. Bone segmentation is relatively straightforward because the density range is wide and consistent. Soft tissue is harder. The brain parenchyma, meninges, and extracranial tissues overlap significantly in attenuation values. I spent three days trying to isolate the cavernous sinus from surrounding structures on a pediatric CT study. The lesion was an incidental finding near the suprasellar cistern, and the contrast timing was off, so the sinus enhancement was suboptimal. The workaround was to combine thin-slice axial reconstructions with coronal and sagittal MPR views, then use manual delineation only in the regions where the automated segmentation failed rather than redoing the entire volume. This cut the work from roughly six hours down to about forty-five minutes. For surgical planning, surface anatomy landmarks matter more than you might expect. The pterion, where the frontal, parietal, temporal, and sphenoid bones meet, is the thinnest part of the lateral skull. It sits approximately four centimeters above the zygomatic arch and two centimeters posterior to the frontozygomatic suture. The middle meningeal artery runs directly beneath it. A fracture at the pterion can lacerate that artery and cause an epidural hematoma within minutes. Surgeons palpate this landmark before making a pterional craniotomy flap.
Another landmark that is easy to misjudge is the internal occipital protuberance. It is the attachment point for the falx cerebri and the tentorium cerebelli. On external palpation it is obvious, but on imaging it can be obscured by artifact from the dental fillings if the slice thickness is too coarse. Use slices no thicker than one millimeter in the posterior fossa region and enable metal artifact reduction if your scanner has it. If you are studying this for medical purposes, cross-reference atlas imagery with actual radiological cases. Netter illustrations are clean but they suppress anatomical variation. Every human head has variation in sinus size, foramen configuration, and vascular branching. A radiology textbook like Grant's Atlas or the Radiopaedia case library will show you what typical variation actually looks like rather than the idealized version.
Common Mistakes and Where the Model Fails
The biggest issue people run into is treating the skull as a single rigid structure. It is not. The craniosacral rhythm, the micromotion at sutures, and the compliance of the meningeal layers all contribute to intracranial dynamics. If you are building a finite element model for impact simulation, fixing the entire skull as a single rigid body will give you inaccurate stress distributions. The sutures absorb energy, and ignoring them shifts load calculations toward the brain parenchyma in ways that do not reflect real trauma biomechanics. Another frequent error is overestimating the protective value of the skull in cervical spine injuries. The head weighs approximately four to five kilograms. During acceleration-deceleration events, that mass generates significant shear force at the atlanto-occipital junction. Whiplash injuries are not about the skull breaking; they are about the brain rotating inside the cranial cavity while the skull moves with the torso. Studies on this show that rotational acceleration above 3500 rad/s² is associated with diffuse axonal injury, regardless of skull integrity. When working with 3D printable models of the human head, resolution limits become a practical constraint. Standard FDM printers at 0.1mm layer height can reproduce the cranial sutures and major foramina, but the small structures like the cristae galli or the optic canal margins require SLA or DLP printing to render accurately. I had a student who printed a skull model on FDM and could not identify the optic canal because the printer merged it with the sphenoid body. Switching to resin printing resolved the issue entirely.
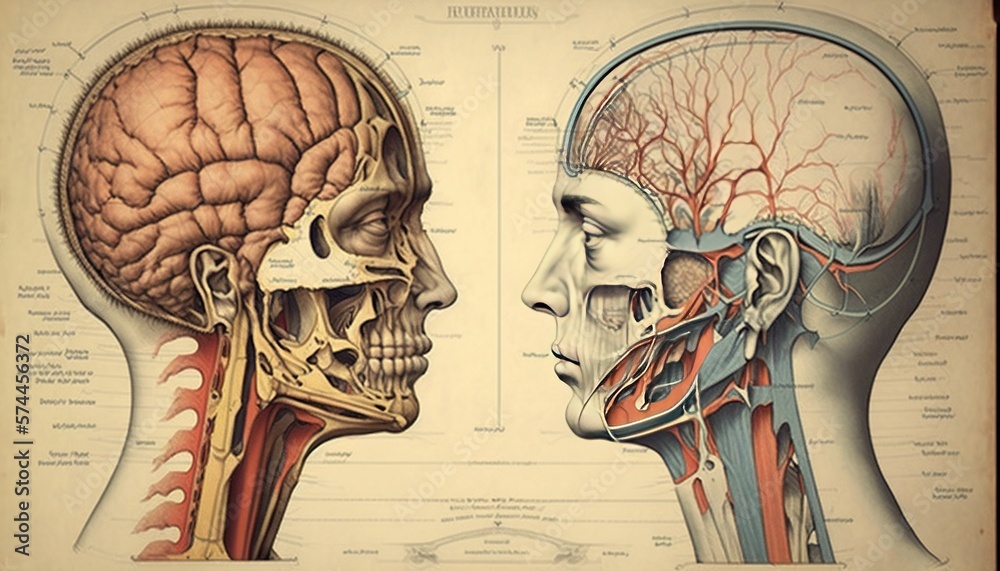
The anatomy of the paranasal sinuses also varies widely and most reference materials do not emphasize this enough. The frontal sinuses are absent in about five percent of adults. The sphenoid sinuses are asymmetric in nearly thirty percent of cases. If you are doing endoscopic sinus surgery planning, relying on standard diagrams without reviewing the individual CT scan will lead to errors. The septations within the sphenoid sinus can displace the carotid artery or optic nerve into the sinus wall, creating a direct surgical hazard that is invisible without cross-sectional imaging.
Resources That Are Actually Useful
Radiopaedia remains the best free resource for clinical correlation. The anatomy articles link directly to case examples showing the same structures in pathology. For interactive 3D work, the Visible Human Project data from the National Library of Medicine provides publicly available CT and MRI datasets that are far more realistic than any commercial model. The data is in DICOM format and can be loaded into software like 3D Slicer, which is free and handles segmentation well enough for educational use. If you need high-quality anatomical illustrations, Gray's Anatomy for Students has better clinical integration than the original Gray's, though it still presents an idealized view. The Netter collection is visually superior but historically less accurate on variation. For pure accuracy, the atlas by Klaus von Nolcken or the Thieme Atlas of Anatomy provide more detailed coverage of anatomical variability than most introductory texts. The discipline of studying the Anatomy Of Human Head is not a one-time effort. The structures do not change, but the tools for examining them do. Each new imaging modality reveals details that older references miss. Stereotactic neurosurgery, for instance, relies on frameless navigation systems that register CT data to the patient's actual anatomy in real time, and the accuracy of those systems depends entirely on how well the operator understands the underlying anatomy being navigated. A misplaced landmark by two millimeters in the anterior skull base can mean the difference between a clean resection and injury to the optic apparatus.
Take the time to understand the relationships between structures rather than memorizing isolated facts. The foramen ovale is not just a hole; it transmits the mandibular nerve, the accessory meningeal artery, and occasionally the lesser petrosal nerve. Knowing what passes through each foramen and every fissure tells you more about clinical presentations than any single structure name ever will.