The Crown
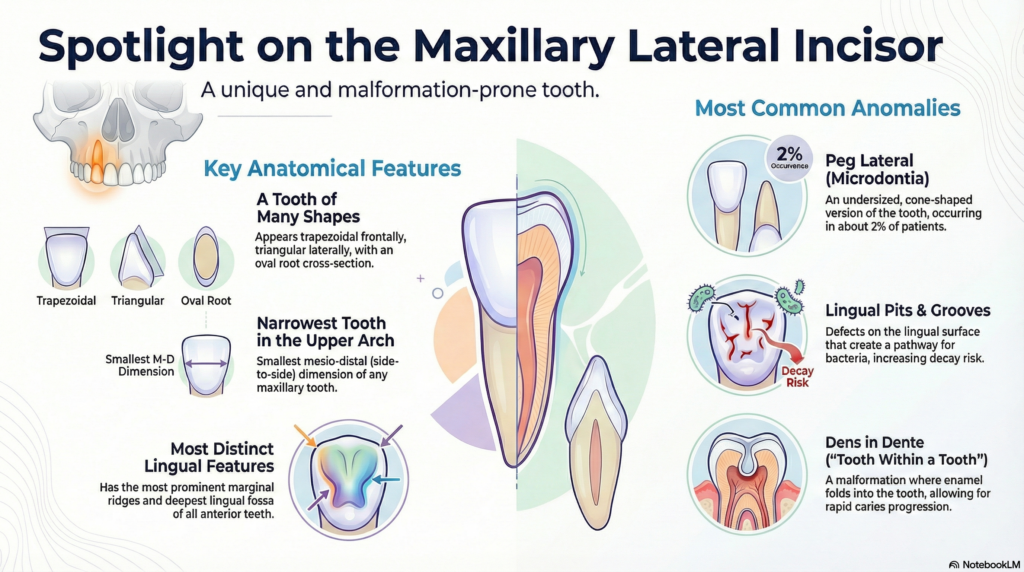
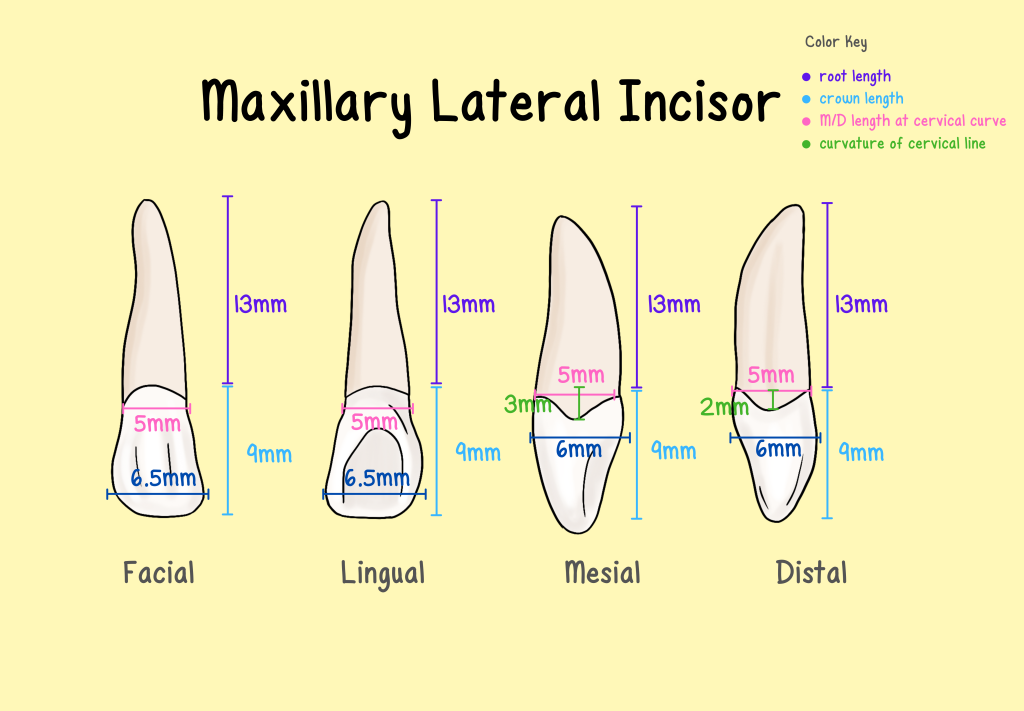
The maxillary lateral incisor crown is narrower mesiodistally than the central incisor, typically measuring around 5.5 to 6 mm compared to 8 to 11 mm for the central. The incisal edge slopes noticeably toward the distal, and the mesioincisal is sharper than the distoincisal. This asymmetry matters clinically because it determines how you orient the tooth in restorative cases. When you're building a pontic or preparing an abutment, getting the mesial-distal inclination wrong makes the restoration look like it was placed backward, which patients will notice immediately even if they can't articulate why. The labial surface is smooth with minimal developmental lobs compared to centrals. Cingum position is slightly distal to the long axis. This cingum offset is why you see more wear facets on the distolingual fossa area in bruxers. The proximal contacts sit near the incisal third on the mesial and at the junction of the incisal and middle thirds on the distal. That distal contact position creates a larger embrasure below it, which is where food impaction becomes a real problem if the interproximal restoration isn't contoured properly.
Root Configuration
The root of the lateral incisor is longer relative to crown length than the central, usually around 13 to 14 mm total root length with a crown of about 8 to 9 mm. The root tapers significantly toward the apex, and the cross-sectional shape changes from oval in the cervical third to more flattened or ribbon-like in the apical third. This flattening creates two distinct canal morphologies that endodontists deal with constantly: a broad flattened canal on the mesial and distal surfaces, and sometimes a true second canal in the apical portion. I've pulled laterals where the working length felt correct on the master cone but the tooth remained symptomatic, and the culprit turned out to be an isthmus connection between two canals in the middle third that I never negotiated. The solution was simpler than you'd think: using a larger taper file, say a .06 or .08 shape, to clean out that isthmus area, combined with aggressive irrigation with sodium hypochlorite and an ultrasonic activation step. It took me about six months of chasing phantom symptoms before I started routinely scoping lateral incisor canals with a microscope, and now I can't imagine doing them without one.
Common Anatomical Variations in the Anatomy Of Lateral Incisor
Peg-shaped laterals are the most common developmental variation, occurring in roughly 1 to 2 percent of the population. The crown is conical with a narrowed mesiodistal dimension throughout, and the root may be similarly reduced or normal sized. These teeth are notoriously difficult to restore predictably because the subgingival margins often extend into areas where isolation is problematic. I use a combination of ferrule-building with fiber posts in severe cases and rely heavily on moisture control with cotton rolls and saliva ejectors rather than rubber dam alone, since the retentive features for the clamp are minimal on peg laterals. Bifid roots occur in about 4 percent of lateral incisors. You'll see this on a periapical radiograph as a vertical radiolucent line running through the root, which can be mistaken for a fracture or a separate canal. On a CBCT scan it's immediately obvious, but not everyone has access to that. The practical implication is that you need to adjust your instrument selection: a single large file won't negotiate both canals adequately, and you're better off using sequential smaller files with a crown-down technique to maintain patency in both channels. Palato-gingival grooves are found on roughly 5 to 10 percent of lateral incisors and represent the most clinically significant anomaly. The groove runs vertically from the cingum down the lingual surface toward the apex, sometimes extending subgingivally several millimeters. It acts as a plaque trap that no amount of patient hygiene can fully clean, and it creates a narrow periodontal pocket that responds poorly to conventional therapy. I've seen cases where the groove extends 4 mm subgingivally, creating a deep isolated pocket that bleeds on probing but doesn't respond to scaling. The only predictable treatment in severe cases is surgical exposure with guided tissue regeneration or extraction if the defect extends too far apically.
Get the Full Details

Landmarks and Surface Anatomy
The three developmental lobes produce distinct marginal ridges on the lingual surface. The mesial marginal ridge is more prominent than the distal marginal ridge, which contributes to the asymmetric incisal edge wear pattern. The cingulum is well-developed in most laterals and serves as the primary lingual landmark for restorative margin placement. When you're preparing a porcelain jacket crown or an e-max veneer on a lateral, the cingulum depth determines how much space you need on the lingual aspect to avoid a bulky restoration that interferes with language function. The lingual fossa is deeper in laterals than in centrals relative to crown size, which means lingual occlusal contacts in patients with deep overbites tend to hit this area first. I've seen severe attrition patterns localized entirely to the lingual fossa of maxillary laterals in Class II division 2 patients, and the restoration challenge there is that you're working in a concavity with limited access for both the bur and the bonding agent. A silicone indexing stent made from the diagnostic wax-up saves considerable chair time because it tells you exactly how much reduction is needed before you start cutting.
Clinical Considerations
Endodontic access cavity preparation for lateral incisors follows the standard lingual approach, but the entry point is slightly more cervical than for centrals due to the smaller crown-to-root ratio. Over-instrumentation toward the labial wall is the most common error, and it creates a ledge that's nearly impossible to bypass without a microscope. The working length should be established at 0.5 to 1 mm short of the radiographic apex, and because the root canal is often wider labiolingually than mesiodistally, you need to angle your master cone vertically on the radiograph to confirm proper seating. Periodontal prognosis for lateral incisors is generally good unless a palato-gingival groove is present. The tooth's position in the arch makes it susceptible to trauma from occlusion, especially in patients with premature contacts. I've noted that laterals in patients with a midline diastema often carry excessive load during excursive movements because the centrals aren't providing the usual guidance. Splinting may be necessary in advanced cases, and I prefer a flexible fiber-reinforced composite bond over a rigid cast span because it allows micro-movement that reduces stress concentration on the periodontal ligament. Restorative case selection requires honest assessment of the tooth's structural integrity. Laterals with large existing restorations, particularly those with labio-lingual dimensions less than 4 mm, have a high fracture risk under functional load. The solution is usually a bonded indirect restoration with adequate coverage of the incisal edge rather than an onlay-only approach. Ceramic material choice matters here: feldspathic porcelain will chip on a lateral that carries heavy lateral loading, whereas lithium disilicate or zirconia-reinforced glass ceramic provides better fracture resistance without sacrificing aesthetics. I typically recommend e-max for anterior restorations unless the occlusion is severely compromised, in which case I shift to a layered zirconia with a translucent core.
Age-related changes affect lateral incisors the same way they affect other anterior teeth: secondary dentin deposition reduces pulp chamber volume, and the pulp horns recede apically over time. This is particularly relevant when preparing restorations on older patients because the risk of pulpal exposure during cavity preparation increases significantly. A lateral incisor that appears to have ample dentin on a 2D radiograph may have a pulp chamber that extends much closer to the labial surface than the projection suggests, since the buccolingual dimension is not captured on a standard periapical view.