What You Actually Need to Know About the Lateral Knee
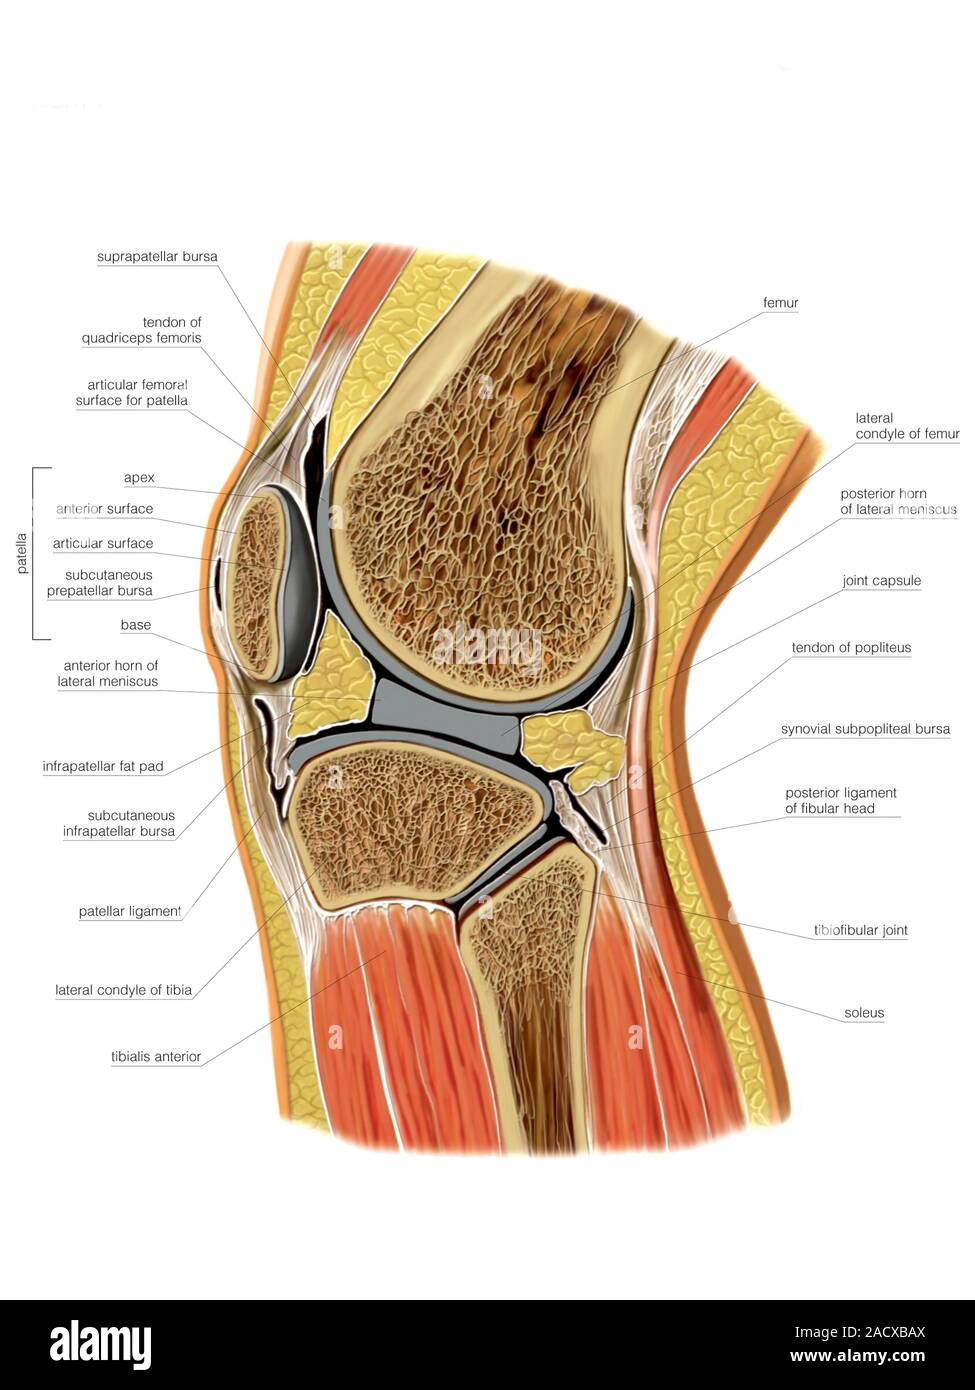
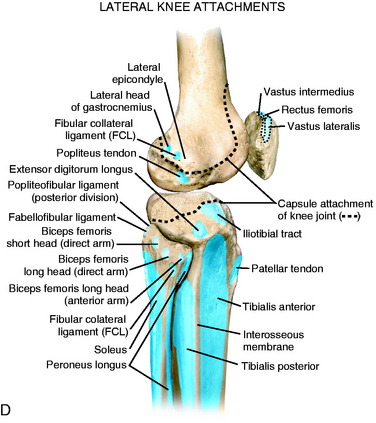
The lateral knee is one of those areas where most people stop at surface-level understanding. They learn the names of the ligaments from a diagram and think they understand the region. What they don't realize is that the lateral knee is structurally far more complex than the medial side, and the consequences of misunderstanding that complexity show up constantly in clinical practice. I've seen enough athletes come in with missed lateral knee pathology to know that the standard textbook approach leaves out a lot of what actually matters when you're dealing with a real patient or working through a rehabilitation program. The lateral collateral ligament, or LCL, is the most obvious structure. It runs from the lateral epicondyle of the femur to the head of the fibula. It's a cord-like structure, relatively simple in its job: resist valgus forces. When you see a direct blow to the medial side of the knee, the LCL takes the load. That much is standard. But the LCL doesn't work alone. It's part of a whole posterolateral corner, and that distinction matters more than most people give it credit for.
Anatomy Of Lateral Knee: Beyond the Basic Structures
The posterolateral corner includes the LCL, the popliteus tendon, the popliteofibular ligament, the lateral head of the gastrocnemius, the biceps femoris insertion, and the iliotibial band as it relates to the lateral joint line. Each of these structures contributes to rotational stability, and when one is compromised, the others compensate until they can't anymore. That's why isolated LCL injuries are less common than combined PLC injuries, and that's also why physical exam findings can be misleading if you're only testing for varus stress. The popliteus tendon is probably the most underappreciated structure here. It passes through the popliteus hiatus in the lateral meniscus and attaches to the posterior tibia. Its job is internal rotation of the tibia and posterior drawer control. When the PLC is injured, the popliteus often takes on additional load, and that's where lateral knee pain that doesn't match the expected ligament injury pattern usually comes from. I had a patient last year with a Grade II LCL sprain who complained of pain specifically during single-leg heel raises. The LCL wasn't the issue causing that pain. It was the popliteus trying to compensate for chronic rotational instability that had developed over months. Once we loaded the popliteus appropriately during rehab, the symptoms resolved in about three weeks. Testing only the LCL would have missed that entirely. The lateral meniscus deserves equal attention. It's attached to the capsule and to the LCL at its posterior horn, which means lateral meniscal tears often occur alongside PLC injuries. The attachment creates a constraint that a medial meniscal tear doesn't have, and that changes both the mechanism of injury and the surgical approach if repair is needed. Arthroscopic surgeons know this well. A lateral meniscus root tear in the setting of a PLC injury has a significantly worse prognosis for conservative management because the meniscus loses its posterior anchoring when the PLC is disrupted.
The fibular head is another structure that gets overlooked in basic discussions. It's not just a landing zone for the LCL and biceps femoris. The proximal tibiofibular joint itself can be a source of lateral knee pain, and trauma to the lateral knee can disrupt that joint. I've dealt with cases where the primary complaint was lateral knee pain after a sports injury, and the actual problem was a subluxed proximal tibiofibular joint that wasn't being addressed. Manipulation and taping resolved it within two sessions. Without understanding the fibular head's role in the lateral knee complex, you'd be treating soft tissue that wasn't the problem.
Get the Full Details

Assessment: How to Actually Test the Lateral Knee
Varus stress testing at 30 degrees of flexion is the standard exam maneuver for the LCL. You stabilize the thigh and apply a valgus force to the ankle, pushing the knee into varus. Gapping at the lateral joint line indicates LCL injury. But here's what most people don't do: they skip the dial test. The dial test is far more sensitive for overall PLC integrity than isolated varus stress testing. With the patient prone, you externally rotate the tibia at 30 degrees and 90 degrees of flexion and compare side to side. Increased external rotation at 30 degrees points to isolated PLC injury. Increased rotation at both 30 and 90 degrees suggests combined PLC and posterior cruciate ligament involvement. This distinction changes the entire treatment pathway. Another common pitfall is relying solely on imaging without correlating to the exam. MRI is useful, but it has a false negative rate for acute PLC injuries that's higher than most clinicians realize. The popliteofibular ligament is small and easily missed on standard sequences. I once reviewed an MRI report that called the PLC intact in a patient who had clear clinical signs of PLC insufficiency. The repeat MRI with a focused proton density sequence through the posterolateral corner at 1.5mm slices picked up a complete popliteofibular ligament tear that the initial study missed. If you're relying on a single MRI read for PLC status, you're flying partially blind. The push-off test is another bedside maneuver worth using. With the patient supine and the knee flexed to 90 degrees, you lift the foot off the table and observe the position of the fibular head. A lateral bump or posterior translation of the fibular head suggests PLC deficiency. It's a quick test that takes five seconds and adds meaningful information beyond what the varus stress test gives you.
Rehabilitation and Return to Activity
Conservative management is appropriate for Grade I and II LCL injuries and some isolated PLC sprains. The timeline depends on the grade. Grade I typically resolves in two to four weeks with brace protection and progressive loading. Grade II injuries take six to twelve weeks, and the return to sport protocol needs to include rotational stability work, not just frontal plane strength. Most rehab programs I see focus almost exclusively on quadriceps and hamstring strengthening. That's insufficient. The lateral knee needs proprioceptive training that challenges rotational control, and that usually means single-leg balance on unstable surfaces, cutting patterns, and deceleration exercises before full return is appropriate. Surgical intervention becomes the conversation for Grade III injuries, particularly when there's multistructure PLC involvement or when the injury is combined with ACL reconstruction. Isolated LCL repair or reconstruction can be done arthroscopically in some cases, but open techniques remain more common for multiligament PLC injuries. Recovery after surgical PLC reconstruction runs four to six months before return to cutting sports, and compliance with the brace protocol is non-negotiable. I've seen athletes come back too early from PLC surgery and re-injure the construct because they stopped using the brace at eight weeks instead of the required twelve. The graft is weakest around the eight to ten week mark during ligamentization, and that's exactly when people get careless. For athletes returning to contact sports, bracing continues to be a discussion point. A custom hinged brace with varus-un Varus-valgus supports is standard, but the brace doesn't restore proprioception. That has to be trained separately. An athlete wearing a brace who hasn't completed rotational stability work is still at elevated risk for re-injury, even if the structural integrity has healed.
When Lateral Knee Pain Isn't What You Think It Is
Illiotibial band syndrome is the most common misdiagnosis for lateral knee pain. The pain location is correct, but the structure involved is different. ITBS is an overuse condition affecting the periconnectival tissue beneath the IT band at the lateral femoral epicondyle, not a ligamentous or PLC issue. The treatment is completely different. Foam rolling the IT band itself is largely ineffective and sometimes aggravating. The evidence supports loading the hip abductors and external rotators, specifically the gluteus medius and maximus, because proximal weakness is the primary driver. I corrected an ITBS diagnosis in a runner by having her skip the foam rolling entirely and instead do single-leg bridge progressions and clamshells three times weekly. Her lateral knee pain dropped significantly within four weeks, and she returned to running at full volume eight weeks later without recurrence. Biceps femoris tendinopathy also mimics lateral knee pain. The biceps femoris inserts on the fibular head, and tendinopathy there produces localized tenderness that overlaps with LCL and proximal tibiofibular joint pain. The distinguishing factor is pain with resisted knee flexion and external rotation, which loads the biceps femoris specifically. MRI or ultrasound can confirm the diagnosis, but the clinical test is usually sufficient to differentiate it from true ligament pathology. Proximal tibiofibular joint dysfunction remains the one that trips people up the most. Pain is localized just anterior and inferior to the fibular head. Palpation reproduces the symptom. Range of motion is usually normal. The joint doesn't appear injured on imaging. It's a mechanical issue that responds to mobilization, but it's frequently overlooked because the clinical presentation doesn't fit a neat category. Understanding the Anatomy Of Lateral Knee at a level that includes the proximal tibiofibular joint prevents this kind of miss.

Limitations and What This Approach Doesn't Cover
The information above covers the majority of lateral knee presentations, but there are clear gaps. Chronic lateral knee pain in older patients with degenerative changes involves articular cartilage and bone marrow lesions that this framework doesn't address. Osteoarthritis of the lateral compartment follows a different logic entirely. Nerve-related pathology, particularly common peroneal nerve irritation near the fibular head, is another area where the structural approach falls short. Radial nerve compression at the fibular neck produces lateral knee and anterior leg symptoms that mimic musculoskeletal pathology. If the standard workup comes back negative and the pain has a burning or radiating quality, nerve involvement should be on the differential. There's also the question of congenital and developmental variants. Some people have a congenitally lax LCL or an anomalous biceps femoris insertion that predisposes them to lateral knee issues without a clear traumatic event. These variations aren't captured in standard assessment protocols, and they require a higher index of suspicion to identify correctly.