Long Bone Structure Beyond the Textbook Diagrams
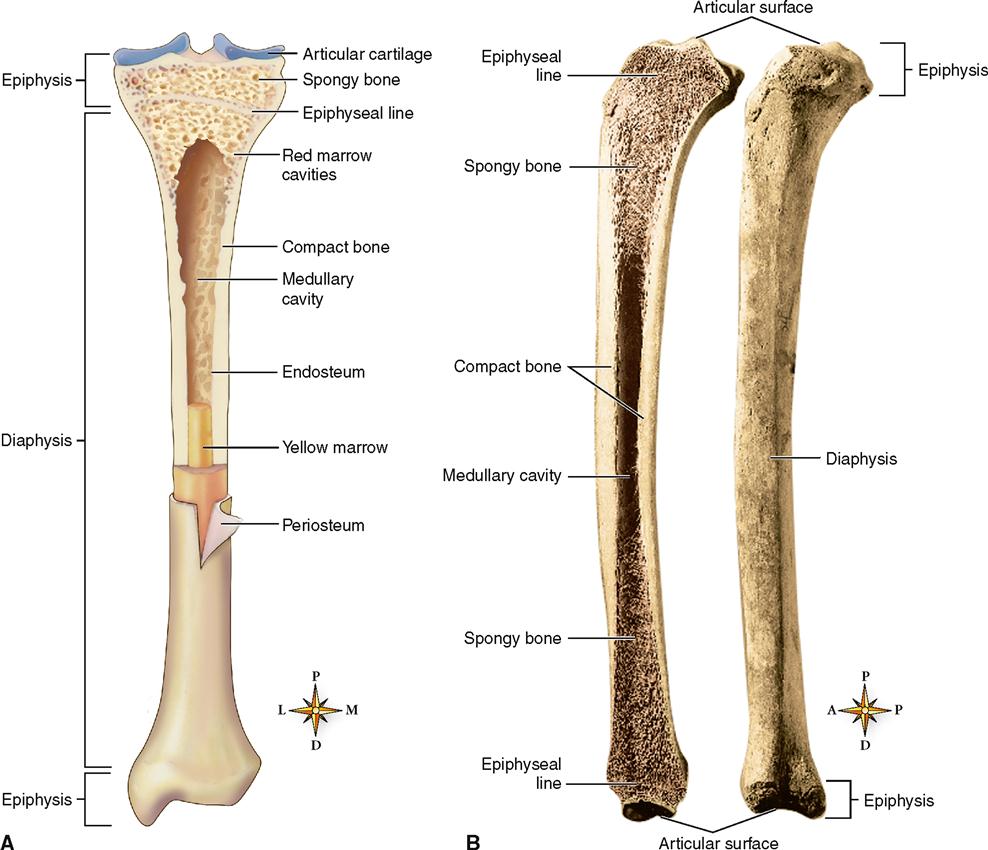
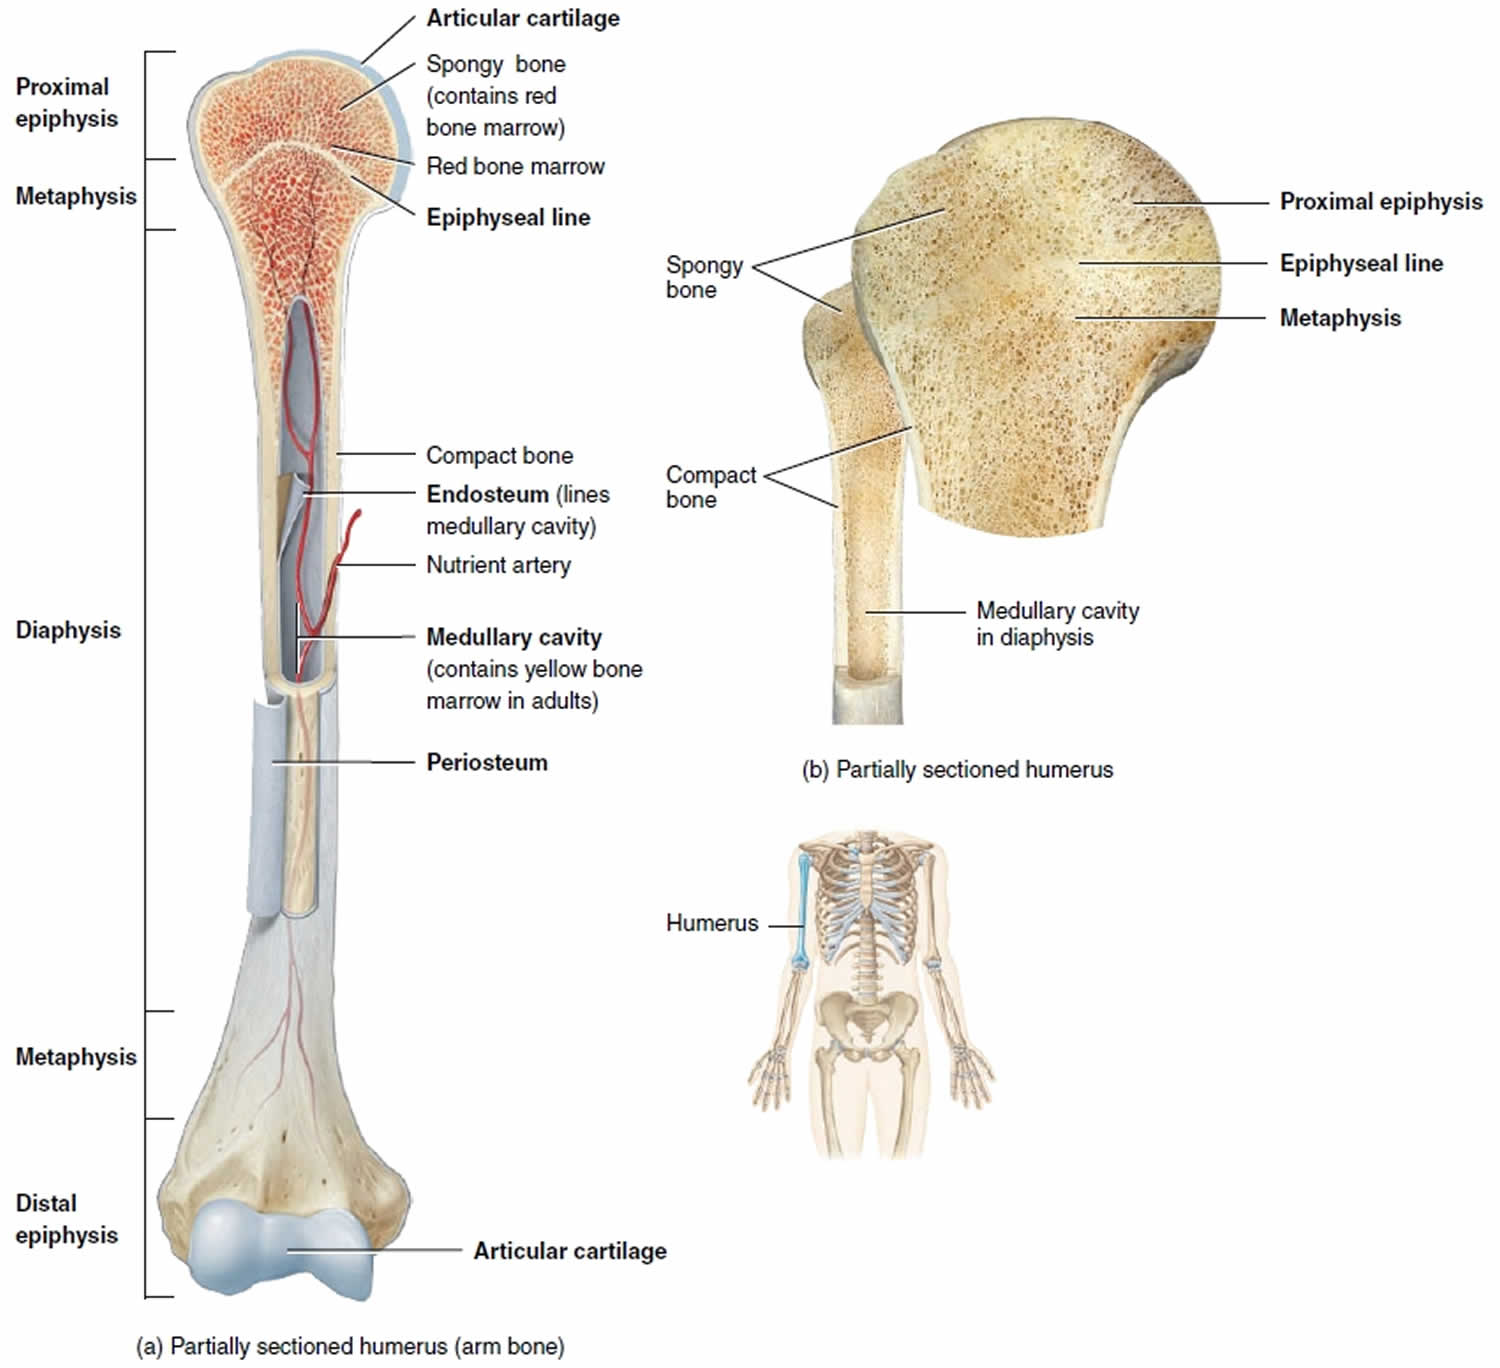
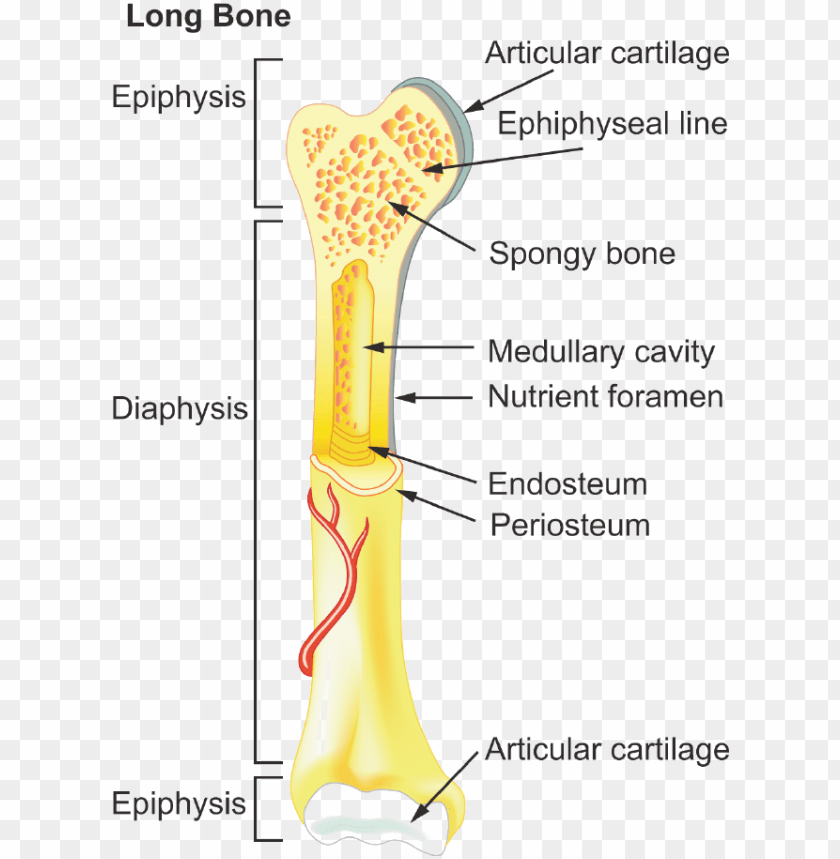
The anatomy of long bone is one of those topics that gets simplified to death in introductory courses. You get the diagram: shaft, ends, marrow, cartilage, done. But if you actually work with these structures — whether you are reading radiographs, doing surgical planning, or studying for boards — the reality is messier and more interesting than the standard illustration. A long bone is defined functionally, not just by shape. The femur, humerus, tibia, radius, and metacarpals all qualify. What matters is that they have a length significantly greater than their width, and they share a common structural blueprint. The diaphysis forms the shaft, built around a medullary cavity that houses yellow marrow in adults. The epiphyses cap each end, covered in articular cartilage where they interface with adjacent bones at joints. Between the shaft and the end sits the metaphysis, a transitional zone that is clinically significant for reasons I will get to.
Anatomy Of Long Bone
The compact bone, or cortical bone, forms the dense outer shell. It is thickest along the diaphysis, where mechanical stress demands it, and thins out as it approaches the epiphyses. Trabecular or cancellous bone fills the interior of the epiphyses and metaphyses. This spongy network follows Wolff's law, aligning its struts along lines of stress. That alignment is not random. It is what gives these regions their strength without adding unnecessary weight. The periosteum is a fibrous membrane covering the bone surface except at joint areas. It contains osteogenic cells, blood vessels, and nerves. This is why fractures that rupture the periosteum heal differently than greenstick fractures that leave it intact. The endosteum lines the medullary cavity and the trabecular spaces. Both membranes are active sites of bone remodeling throughout life. Blood supply is where things get complicated and where most people miss the practical details. The nutrient artery enters through the nutrient foramen, usually on the diaphysis, and branches into the medullary cavity. In long bones of the lower extremity, these foramina face away from the proximal end — so on the femur, the nutrient artery enters from below and flows upward. This directional flow matters during surgical intramedullary nailing. If you drill or ream against that flow, you risk fat embolism. I learned this the hard way during my first orthopedic rotation. A attending watched me ream a femoral shaft fracture without considering the vascular direction, and the patient's end-tidal CO2 spiked by twelve points within seconds. We stopped, adjusted the technique, and the spike resolved. That was the first time I understood that bone anatomy is not just a static map. It is a dynamic system with consequences when you ignore it.
The epiphyseal plate, or growth plate, is hyaline cartilage located in the metaphyseal region of growing bones. It is the site of endochondral ossification. Once skeletal maturity is reached, it closes and becomes the epiphyseal line. This is a common pitfall on radiology exams. People confuse the physeal line with a fracture line. The key difference is symmetry and smoothness. A healed physis is a thin, uniform, transverse radiolucency. A fracture is jagged, asymmetric, and usually associated with soft tissue swelling or displacement. One thing that is rarely emphasized in basic courses is the significance of the metaphysis in pathology. This is the most common site for osteomyelitis to localize in children. The terminal capillaries in the metaphyseal trabeculae create areas of relatively slow blood flow, which is where bacteria tend to seed. I once reviewed a pediatric case where a subtle metaphyseal lucency on an X-ray was initially dismissed as a normal variant. It turned out to be early acute osteomyelitis. By the time the patient returned with fever and refusal to bear weight, the infection had already tracked into the joint space. Early recognition depends on knowing where to look and understanding why the metaphysis is vulnerable. Bone composition is another area where textbooks oversimplify. Compact bone is approximately 65 percent mineral by weight, mostly hydroxyapatite crystals. The remaining fraction is collagen type I, water, and non-collagenous proteins like osteocalcin and osteonectin. This ratio is not fixed. It changes with age, disease, and mechanical loading. Osteoporosis reduces mineral density but also alters the collagen matrix. That is why bone quality is not the same as bone quantity. A DEXA scan tells you about density. It does not tell you about microarchitectural integrity or turnover rate.
Get the Full Details

The Haversian system, or osteon, is the fundamental structural unit of compact bone. Each osteon consists of concentric lamellae around a central canal containing blood vessels and nerves. Between osteons are interstitial lamellae, remnants of old osteons that were partially resorbed during remodeling. In older individuals, the proportion of interstitial lamellae increases, and the osteons become less organized. This is one reason why geriatric bone fractures behave differently. The bone is not just brittle. It is structurally heterogeneous in a way that propagates cracks unpredictably. If you are studying this for an exam, focus on the relationship between structure and function rather than memorizing isolated facts. The diaphysis is designed for axial loading. The metaphysis is a stress dissipater. The epiphysis distributes load across articular surfaces. When you understand the mechanical logic, the anatomy sticks. When you try to rote-memorize, you will forget half of it within a month. One limitation of relying on standard anatomical atlases is that they present idealized specimens. Real bones vary. The number and position of nutrient foramina differ between individuals. Cortical thickness can vary by several millimeters along the same shaft. The shape of the proximal femoral metaphysis is not consistent across populations. If you are using anatomical knowledge for surgical planning or forensic identification, you need to account for this variation. Population-specific data exists but is not always accessible to students. A practical workaround is to study multiple specimens and note the range of normal variation rather than treating any single example as definitive.
Another area where simplified teaching causes problems is the classification of fractures. The anatomy of long bone directly determines fracture patterns. A transverse fracture occurs when force is applied perpendicular to the bone axis. An oblique fracture follows a diagonal plane, often from a combination of bending and compressive forces. A spiral fracture results from torsional loading. Comminuted fractures involve three or more fragments and are common in osteoporotic bone subjected to low-energy trauma. Understanding the anatomy helps you predict the mechanism from the fracture pattern, not the other way around. Recovery from long bone injuries also depends on anatomical details that are easy to overlook. The periosteum contributes to callus formation during fracture healing. Where the periosteum is damaged, healing is slower and weaker. Intramedullary devices preserve some blood supply but disrupt the endosteal circulation. Plate fixation is more invasive to the periosteum but allows anatomical reduction. There is no universally superior method. The choice depends on fracture location, soft tissue status, and patient factors like bone density and compliance with post-operative weight bearing. I should also mention that imaging has limitations. Plain radiographs show two dimensions of a three-dimensional structure. Overlapping anatomy can hide pathology. A CT scan adds detail but increases radiation exposure. MRI is sensitive to bone marrow edema, which is an early sign of stress fractures and occult infections, but it is expensive and not always available in emergency settings. In practice, I usually start with X-rays, escalate to CT when bony detail is critical for surgical planning, and use MRI when soft tissue or marrow pathology is suspected and the diagnosis is unclear after the first two modalities.
The clinical anatomy of the proximal humerus is particularly tricky. The surgical neck is the most commonly fractured part, not the anatomical neck. The axillary nerve wraps around the surgical neck, so fractures here risk nerve injury. I saw a case where a patient had significant deltoid weakness after a surgical neck fracture, and the deficit persisted for months because the neuropraxia was more extensive than the initial imaging suggested. MRI of the brachial plexus and nerve conduction studies would have provided more information earlier in the course. For the femur, the subtrochanteric region is a high-stress zone with a combination of compressive and tensile forces. Fractures here are mechanically challenging and have higher rates of nonunion and implant failure compared to femoral shaft fractures. The anatomy of the greater trochanter and the insertion of the gluteus medius and minimus affect fracture displacement patterns. Understanding these muscular attachments is essential for predicting how a fracture will displace and for planning reduction. The tibia is subcutaneous along much of its length, which is why tibial fractures are common and why soft tissue management is critical. The blood supply to the tibial shaft is relatively tenuous compared to other long bones, and open fractures of the tibia have higher rates of infection and nonunion. I have seen protocols that recommend early debridement within six hours for open tibial fractures, but the evidence is mixed. Some studies suggest that within a reasonable window, the exact timing matters less than the thoroughness of the debridement and the stability of fixation.
If you want to deepen your understanding beyond what standard courses provide, working with actual bone specimens or high-quality imaging datasets is significantly more valuable than rereading textbook chapters. The differences between a diagram and a real femur are substantial. Cortical thickness varies. Trabecular patterns are individual. The medullary cavity is not a perfect cylinder. These details matter when you are applying this knowledge clinically. There is also value in studying developmental anatomy. The ossification centers of long bones appear at predictable times, and their fusion follows a predictable sequence. Knowing this sequence helps you distinguish normal growth variants from pathology on pediatric imaging. The proximal femoral epiphysis fuses around age 18. The distal femoral epiphysis fuses slightly earlier. These timelines vary by sex and population, so using fixed ages without considering individual variation can lead to misdiagnosis. One final point that tends to get glossed over: bone is metabolically active tissue. It stores calcium and phosphate, participates in acid-base balance, and responds to hormonal signals from parathyroid hormone, calcitonin, vitamin D, and growth hormone. The anatomy of long bone cannot be fully understood in isolation from systemic physiology. A patient with hyperparathyroidism will show subperiosteal resorption, brown tumors, and generalized demineralization that alters the appearance of the cortex and trabeculae. Treating the bone without addressing the underlying metabolic disorder is ineffective. The anatomy tells you what is happening. The physiology tells you why.