Breaking Down The Lower Leg
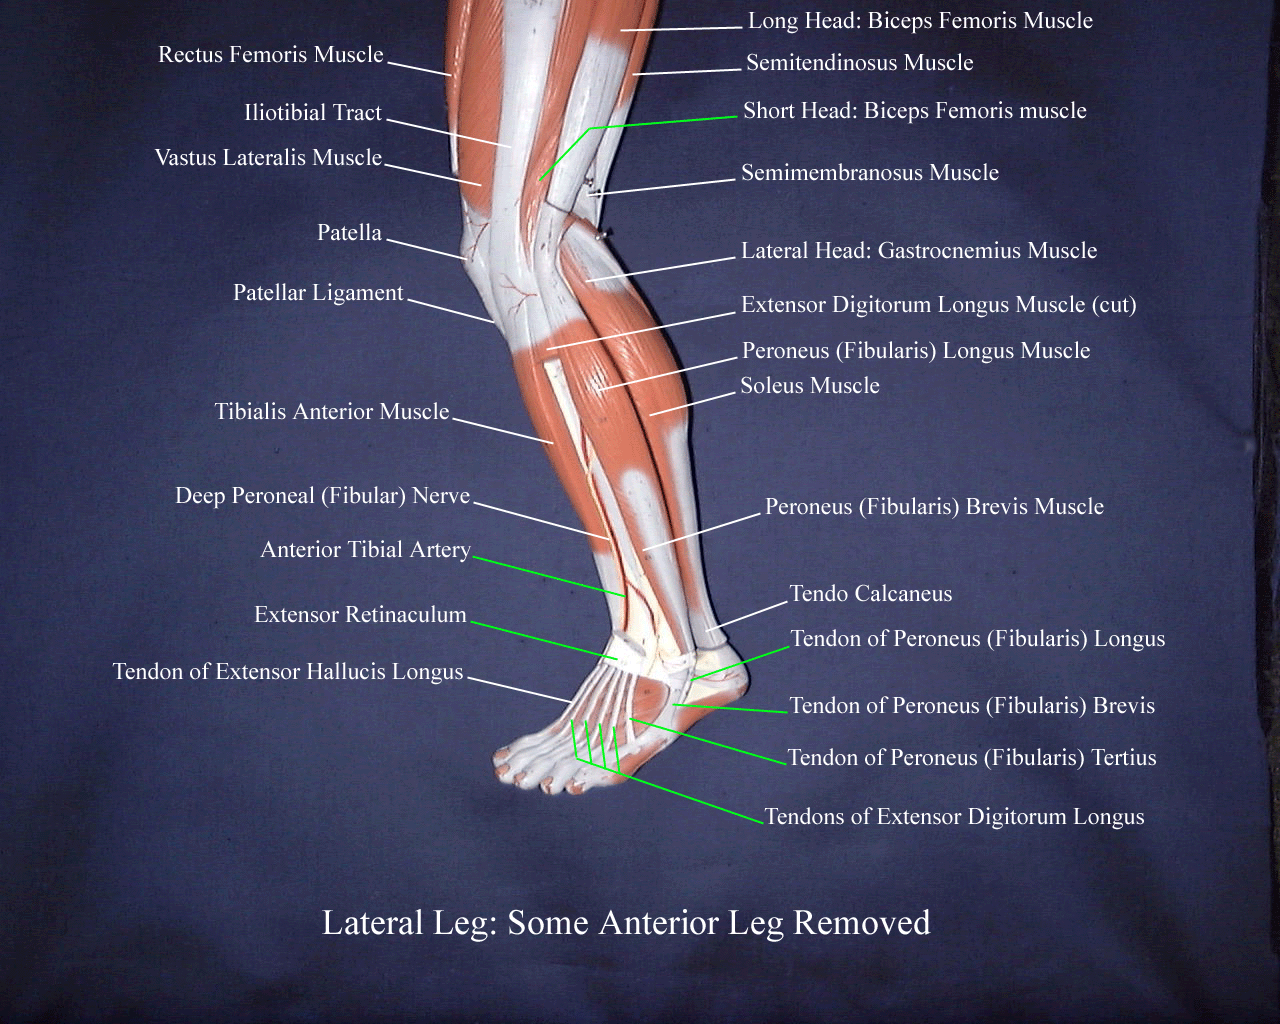
The lower leg sits between the knee and ankle, and most people think of it as just one solid bone. It is actually two bones—the tibia and the fibula—wrapped in three distinct muscle compartments that overlap and share fascia. If you are studying this for anatomy class or trying to understand why your calf hurts after running, you need to look past the surface and map out what is actually there. The tibia is the larger weight-bearing bone. It has a flat medial surface you can feel along the front of your shin, and its proximal end forms part of the knee joint. The fibula is thinner and sits lateral to the tibia. It does not bear significant weight but serves as an attachment point for muscles and contributes to the ankle joint. The space between these two bones is called the interosseous membrane, and it is where several muscles originate from. There are three compartments: anterior, lateral, and posterior. Each has its own neurovascular bundle, which matters a lot clinically.
The anterior compartment contains the tibialis anterior, extensor hallucis longus, extensor digitorum longus, and peroneus tertius. These muscles dorsiflex the ankle and extend the toes. The deep peroneal nerve and anterior tibial artery run through here. If you press into the front of your lower leg and point your foot upward, you can feel the tibialis anterior tendon engage near the ankle. The lateral compartment houses the peroneus longus and peroneus brevis. They evert the foot and assist in plantarflexion. The superficial peroneal nerve supplies them, along with contributions from the fibular artery branch. The posterior compartment splits into superficial and deep layers. The gastrocnemius, soleus, and plantaris make up the bulk of the calf. The tibialis posterior, flexor digitorum longus, and flexor hallucis longus lie deeper. The tibial nerve and posterior tibial artery travel through this space.
I spent weeks trying to reconcile the diagrams with actual cadaver dissections in med school, and the discrepancy was frustrating. Textbooks show clean separations between compartments, but in reality the fascia is variable, muscles merge into each other more than expected, and the neurovascular structures do not always follow the textbook path. One student in my lab couldn't find the deep peroneal nerve because it was running more anteriorly than usual—just a normal anatomical variant, but it threw off the entire dissection for twenty minutes until we located it by following the dorsalis pedis pulse instead of relying on the nerve's expected position. Blood supply comes mainly from the posterior tibial artery and the anterior tibial artery, which are branches of the popliteal artery behind the knee. The peroneal artery runs along the fibula and supplies the lateral compartment. Venous drainage follows the arteries with deep veins accompanied by the arteries and superficial veins like the great and small saphenous veins running under the skin. Lymphatic drainage moves toward the popliteal and inguinal nodes. If someone has an infection in the foot or lower leg, swelling often appears first in the popliteal area before reaching the groin.
Get the Full Details

One thing beginners consistently miss is the relationship between the tibial nerve and the neurovascular bundle in the posterior compartment. The nerve sits deep and medial, and when compartment syndrome develops, it is often the first structure compromised because it is trapped between the muscle bellies and the fascial floor. Pain out of proportion to injury, pain on passive stretch of the toes, and paresthesia are early signs. By the time weakness or paralysis sets in, irreversible damage may have already occurred. Another overlooked detail is how the flexor hallucis longus changes through the lower leg. Proximally it is a thick muscle belly, but distally it becomes a long tendon that passes behind the medial malleolus, through the tarsal tunnel, and inserts on the distal phalanx of the big toe. This tendon can develop tenosynovitis in dancers and runners, and it is easily confused with posterior ankle impingement on imaging because the FHL tendon sits right in the space where bony spurs form. The interosseous membrane is more than just a connector. It provides attachment surfaces for the tibialis posterior and flexor hallucis longus, and it acts as a load-sharing structure that distributes forces between the tibia and fibula during weight-bearing. Isolated fibular fractures without tibial involvement are less common than people assume because the membrane transfers force across both bones.
When assessing lower leg injuries clinically, palpating the dorsalis pedis pulse is useful but not foolproof. The pulse can be weak or absent in up to two percent of healthy people as a normal variant. Relying on pulse checks alone to assess perfusion in trauma cases is unreliable. Capillary refill and clinical context matter more. Compartment pressure monitoring is the gold standard for diagnosing compartment syndrome, but it is invasive and not always available in urgent settings. The clinical examination remains the primary diagnostic tool, though it is subjective and operator-dependent. If you suspect compartment syndrome and cannot get a pressure reading immediately, fasciotomy should not be delayed while waiting for confirmatory tests. MRI and ultrasound are helpful for evaluating soft tissue injuries, muscle tears, and tendon pathology, but they are expensive and time-consuming. For most lower leg complaints, a thorough physical exam combined with plain radiographs is sufficient to narrow the differential significantly before advanced imaging becomes necessary.
The anatomy here is straightforward if you accept that variation is the rule, not the exception. Memorizing the standard layout is useful, but understanding how things can shift around is what actually helps when you encounter a real case that does not match the diagram on page forty-two of Gray's.