Mapping the Maxillary Central Incisor: What You Actually Need to Know
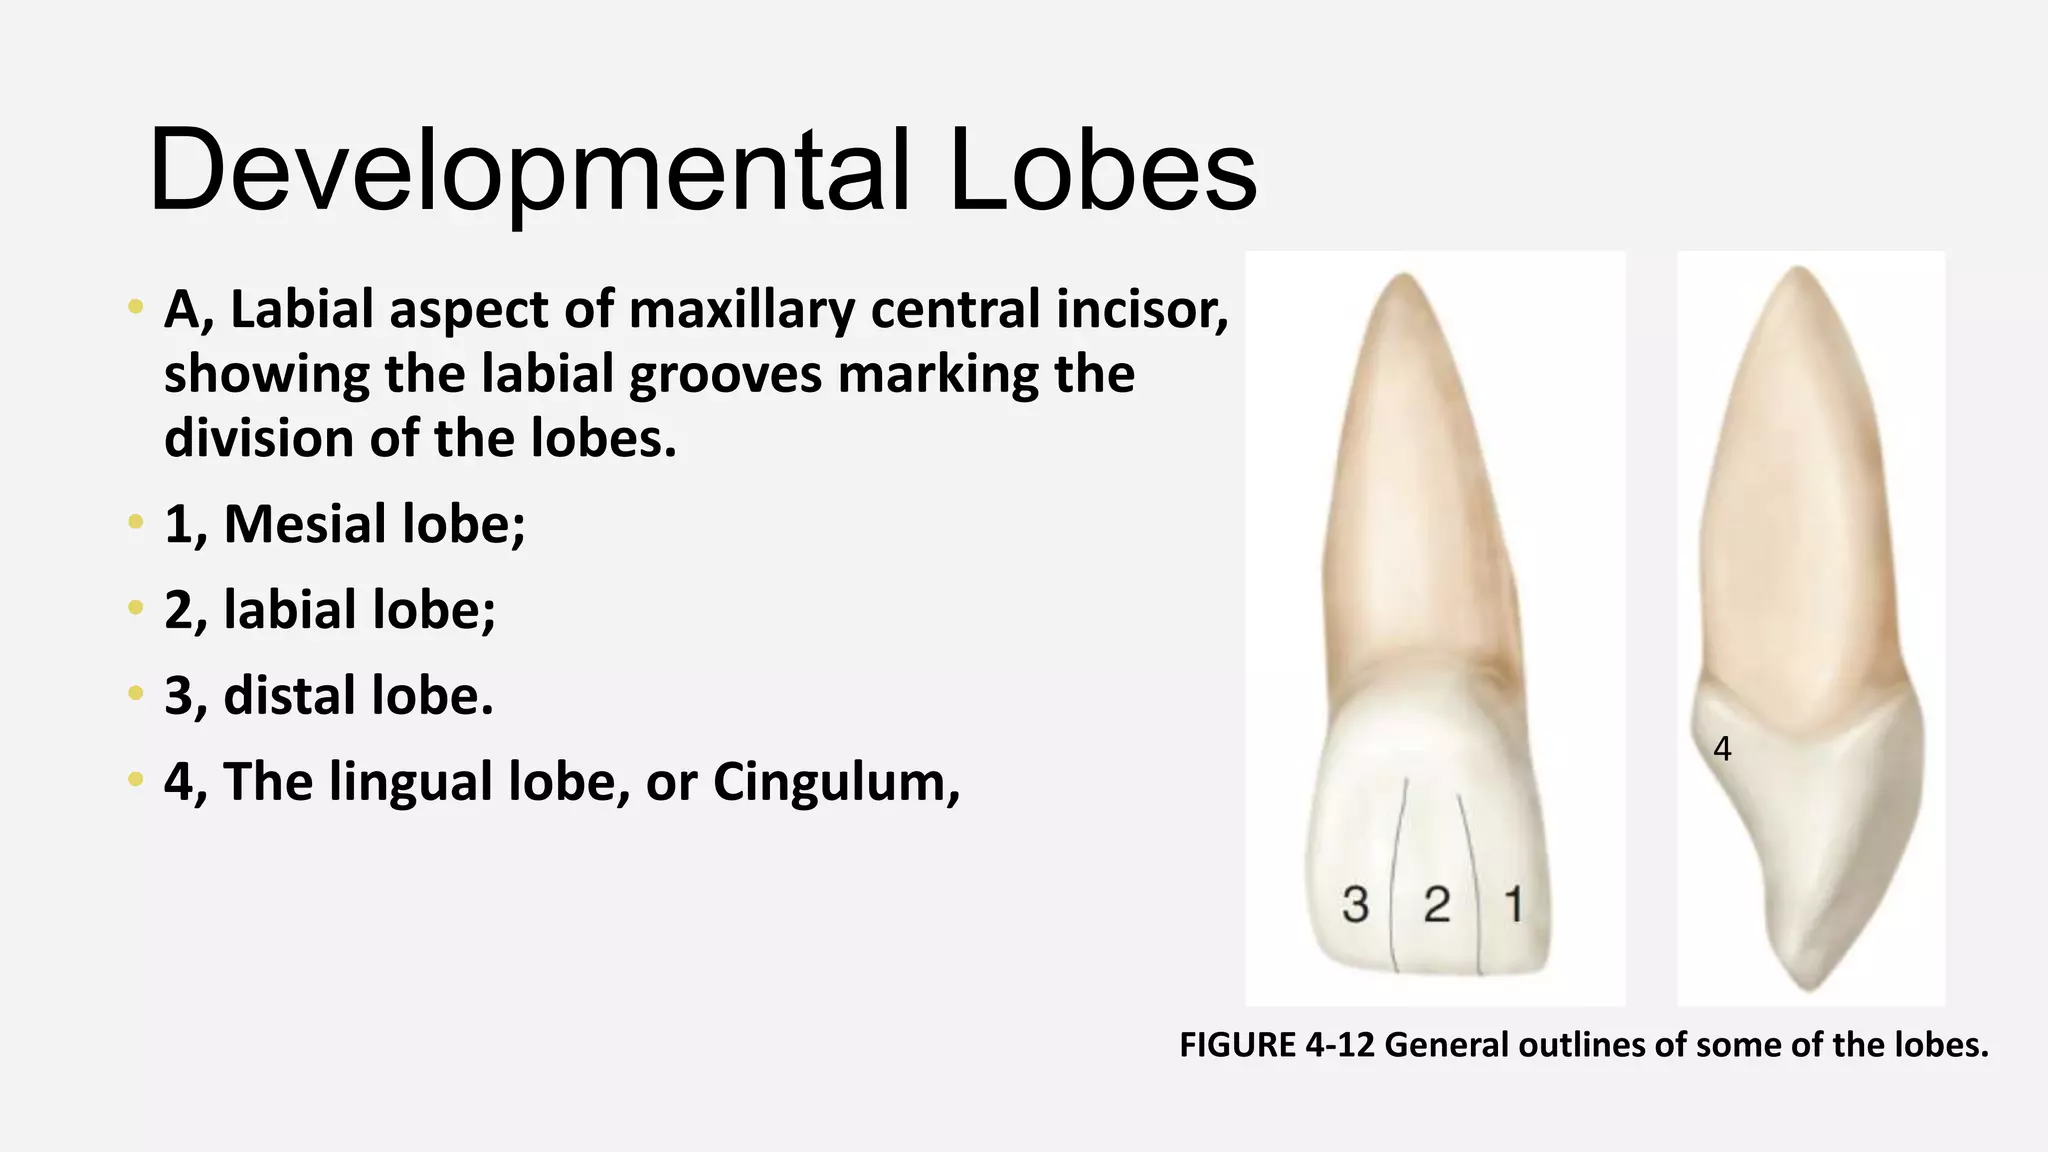
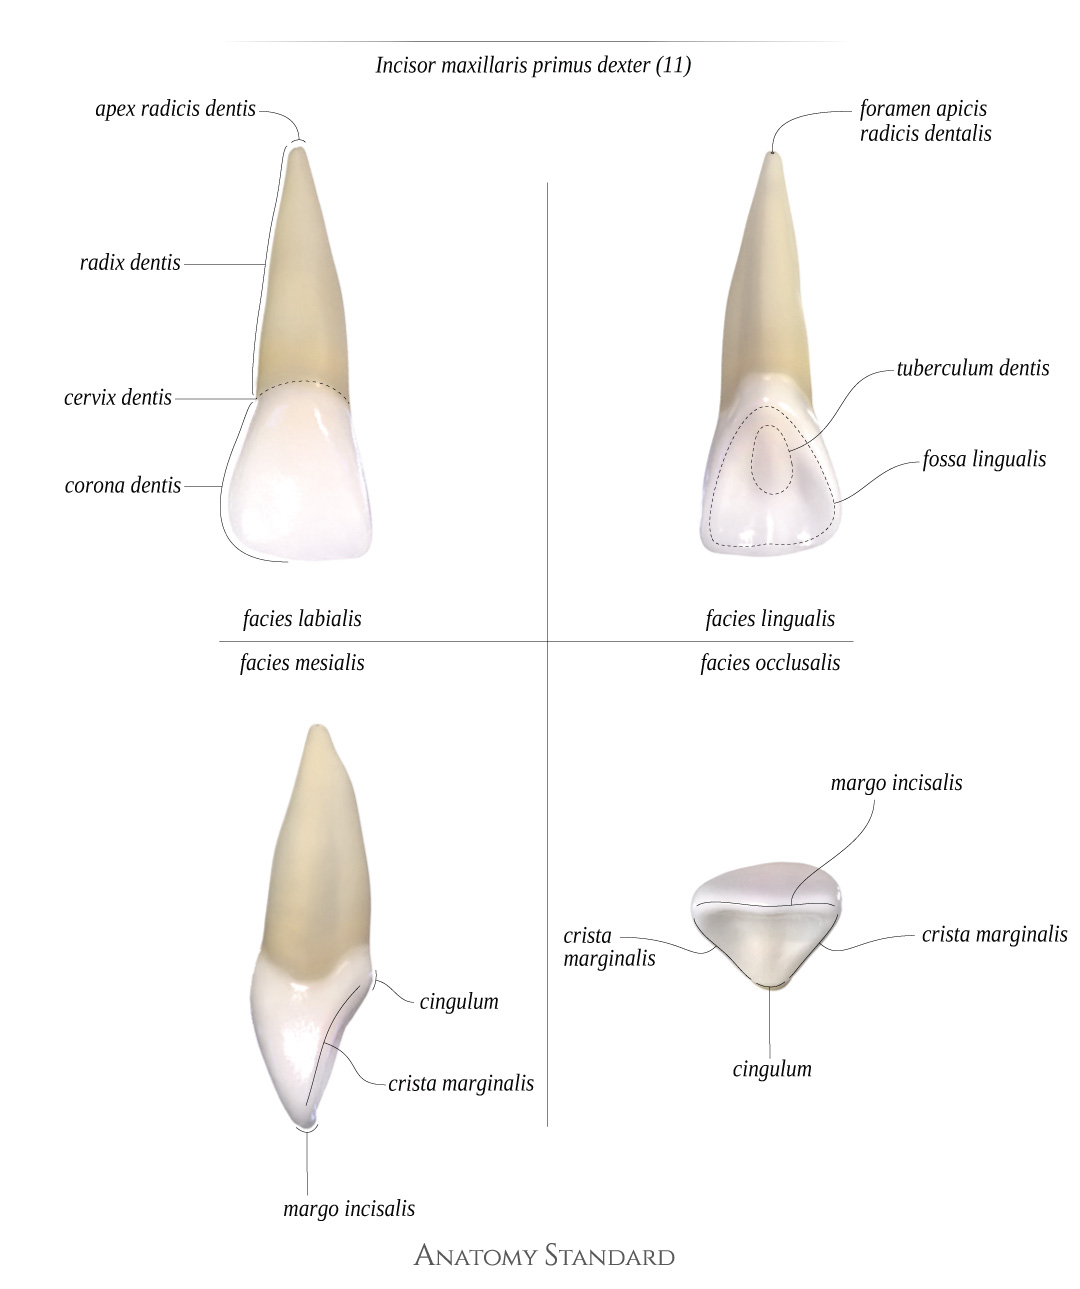
I spent years teaching operative dentistry, and almost every new student approaches crown prep or class IV restorations on that front tooth as if it were a simple block of ivory. It isn't. The Anatomy Of Maxillary Central Incisor hides a surprisingly complex set of contours that will dictate whether your margins seal or leak, whether your crown looks natural or like a slab of porcelain, and whether your endodontist finds every canal or leaves one behind. Start with the crown. It's the largest incisor in the permanent dentition, roughly 10.5 millimeters mesiodistally and about 9 millimeters cervico-incisally in adults. The labial surface is convex, smooth, and subtly divided into three developmental lobes — a midlobe that's larger than the two lateral ones. You can usually see this by looking at a fresh extraction specimen or even a well-prepped tooth under operatory light. The lobes create the mamelons on newly erupted teeth, which wear down relatively quickly through mastication and incising. The mesial marginal ridge is nearly straight and runs almost perpendicular to the long axis of the tooth. The distal marginal ridge is more curved and sits slightly more cervical. That difference matters because it changes how you approach proximal boxes in restorative work. If you mirror the mesial outline on the distal, your cavity will be anatomically wrong. The lingual surface is concave and bounded by the marginal ridges. The cingulum is prominent and offset slightly to the distal — a detail that affects both the incisal edge relationship and the guidance for tooth reduction in porcelain veneers.
Move to the root. It's the longest root in the entire anterior dentition, averaging around 13 millimeters. It's single, conical, and slightly flattened buccolingually. On a periapical radiograph it appears broadly oval because you're viewing the long axis en face. The cervical cross-section is roughly a reniform shape with the mesial concavity being the key feature. That mesial concavity is a trap for the unwary — it's where periodontal probes can slip into, creating false pockets if you're not careful, and it's also the area most vulnerable to root caries in older patients with gingival recession. The contact areas are textbook but frequently misunderstood. The mesial contact is in the incisal third, approximately at the junction of the incisal and middle thirds. The distal contact is more cervical, near the junction of the middle and cervical thirds. This means the interproximal embrasure on the mesial is smaller and more triangular, while the distal embrasure is larger and more open. When you're placing a matrix band for a Class V or Class IV, that asymmetry determines whether you get a tight contact or an overhang. Here's something most textbooks don't stress enough: the labiolingual tilt of the root apex. In most cases the apex is deviated slightly to the distal. That sounds minor, but it matters enormously if you're doing apicoectomy or surgical access. I've seen endodontic surgeons miss the apex by several millimeters because they approached straight from the labial without accounting for that distal inclination. The workaround is simple — take a CBCT slice or at minimum a second radiograph at a different horizontal angulation before you cut. It adds ten minutes and prevents a reoperation.
Common Pitfalls and What I've Learned the Hard Way
The biggest mistake I see students and general practitioners make is treating the maxillary central as symmetrical. It's not. The mesial outline is broader at the incisal edge and tapers gradually toward the cervical line. The distal outline is more rounded and the crown appears shorter from that side because of the cervical positioning of the contact. When I was running my own practice, I once prepared a porcelain veneer on a central incisor and the final crown looked slightly twisted in the patient's smile. It took me two hours under the scope to realize I had essentially mirrored the mesial contour preparation onto the distal. The patient could tell immediately, even though nobody in the office had flagged it. I remake that crown myself — it's a rule I stick to now. Another subtle issue involves the cervical line on the labial aspect. It curves incisally about 2 to 3 millimeters more on the mesial than on the distal. That's consistent across almost every specimen, but it's easily missed when you're looking at occlusal radiographs rather than facial views. If you're doing gingivectomy or crown lengthening, ignoring this curve will give you uneven biologic widths and compromised aesthetics. On the endodontic side, the canal anatomy is usually described as a single canalis, but the reality is more variable. Studies using micro-CT have shown that roughly 15 to 20 percent of maxillary central incisors have two separate canals or a bifurcated canal system. A significant portion of those cases present with two apical foramina. If you're relying solely on a working-length radiograph taken at 0 degrees, you will absolutely miss one. The workaround I use is to take a second radiograph at approximately 20 degrees mesially. The parallax effect — the Buccal Object Rule — shifts the canals relative to the root outline and usually reveals the second space. It takes an extra 30 seconds of exposure and processing time, but it's the difference between a clean fill and a retreatment six months later.
Get the Full Details
Functional Considerations That Affect Your Work
The incisal edge of the maxillary central incisor doesn't sit on the same plane as the lateral incisor. It's more incisal by about 1 to 2 millimeters, which creates the aesthetic step in the anterior guidance. When you're building up worn edges with composite, maintaining that 1-millimeter step is critical. Most restorations I've had to revise failed because the incisal step was flattened — the patient's anterior guidance changed, they developed a different bite pattern, and the restoration took abnormal forces it wasn't designed for. The lingual fossa depth varies considerably between individuals. In some mouths it's a shallow saucer; in others it's a deep concavity that extends close to the labial enamel. This depth directly affects how much tooth structure you preserve during preparation and how you design the occlusal wrap of an onlay or crown. Deep lingual fossae mean less labial enamel conservation is possible, which compromises the bonding surface area. I measure this clinically with a periodontal probe before I decide between a veneer, a prepless onlay, or a full crown. It takes two minutes and prevents about half of the preparation-related sensitivity cases I see. The root surface area of the maxillary central incisor is the largest of any anterior tooth, which makes it the most stable anchor in the arch. That's why it's frequently chosen as an abutment for fixed partial dentures, but it's also why the mesial concavity becomes a periodontal liability. I've treated more cases of localized mesial bone loss in this region than any other single root concavity. The anatomy creates a plaque trap that brushing simply doesn't clear, especially when the interdental papilla has receded. Antimicrobial rinses and specifically angled interdental brushes — the teardrop shape, not the round one — are what I recommend to my patients. The round brushes slide right past the concavity without contacting the root surface.
Limitations of Standard Models and When They Fail
The standard anatomical descriptions you find in textbooks and on dental model kits are based on averages. They're useful for learning but dangerous if you treat them as universal. The maxillary central incisor shows the most variation in the entire dentition when it comes to root configuration. I've encountered teeth with a single large canal, two canals with separate foramina, a loop-shaped canal, and even a three-canal configuration — yes, three — in one case. None of those variations would be predictable from a wax-up or a standard study model. The limitation is real: if you're relying only on 2D radiography, you're flying partially blind, particularly in the apical third where the canal configuration is most likely to diverge. Another limitation involves the developmental grooves on the labial surface. These are often visible as faint lines running vertically from the incisal edge toward the cervical third. In some teeth they're so subtle they're invisible until you dry the surface. These grooves represent the boundaries between the three developmental lobes, and they can be pathways for caries if they're deep enough and the patient has high caries risk. I've seen mesial and distal developmental grooves on the same tooth, creating a sort of triradate pattern that's impossible to capture on a standard diagram. The practical implication is that these grooves need to be sealed during preventive treatments — varnish, resin infiltration, or sealant material — rather than ignored until they become lesions. For restorative purposes, the cervical constriction — the narrowest part of the crown outline — is located at the cervical third on the labial and at the cervical line on the proximal aspects. This constriction creates a undercut that must be managed during crown preparation. If you don't account for it, your finish line will be inconsistent, and the impression material won't flow properly into the subgingival area. I use a finishing bur with a known diameter and take multiple reference points around the cervical perimeter. It's methodical and slow, but it eliminates the guesswork that leads to overcontoured crowns and periodontal irritation.
The color anatomy is also more complex than it appears. The incisal third is more translucent and less saturated, the middle third has the highest chroma, and the cingulum area is again more opaque and lighter. This layering matters for shade selection in restorative work. Picking a single shade from a chart based on the middle third will give you a restoration that looks flat and artificial. I match the incisal and cingulum zones separately and blend them during the build-up. The extra time is measurable — about 15 to 20 minutes per case — but the aesthetic result is qualitatively different, and patients notice immediately.

Practical Takeaways
The anatomy isn't abstract. Every contour I've described here translates directly into decisions about how you prepare, restore, or treat the tooth. The mesial concavity affects your probing technique and your periodontal maintenance protocol. The root apex inclination affects your surgical approach. The contact area asymmetry affects your matrix placement. The canal variation affects your endodontic prognosis. The developmental lobe structure affects your restorative bonding strategy. They're all connected, and the connections are what determine clinical outcomes. I've found that the most efficient way to internalize this anatomy is to hold an extraction specimen in your hand and trace each surface with a explorer while naming the structures out loud. Not the textbook names, but what you'd tell a patient or a colleague. "Here's the mesial contact, it's in the incisal third." "Here's the cingulum, it's offset distally." "Here's the mesial concavity, this is where the pocket forms." That kind of verbal mapping sticks better than repeated reading. I learned it from a professor who made us do it for every tooth in the mouth, and I still do it occasionally when I'm prepping a case that I'm unsure about. It takes about four minutes per tooth but resets your spatial understanding completely. If you're studying for boards or clinical exams, focus on the asymmetry. Examiners love to test whether you understand that the mesial and distal aspects aren't mirrors of each other. Every difference — contact location, marginal ridge curvature, cervical line curvature, root apex inclination, lobe prominence — is a potential exam question. Write them down as pairs of contrasts rather than isolated facts. The brain retains paired information better, and that's what you'll need under pressure.
For clinicians, the single most important takeaway is this: the maxillary central incisor is deceptively complex. Its simplicity is an aesthetic target, but its anatomy is anything but simple. The variations in root canal configuration, the mesial concavity, the developmental lobe grooves, the asymmetric contacts — these aren't edge cases. They're the norm. Planning your procedures around average anatomy rather than actual anatomy is what leads to the complications I've described. Take the time to see the tooth clearly before you touch it with a bur, an explorer, or an impression tray. The extra five minutes of observation saves hours of corrective work.