What You Actually Need to Know Before You Start Messing With Your Neck and Shoulders
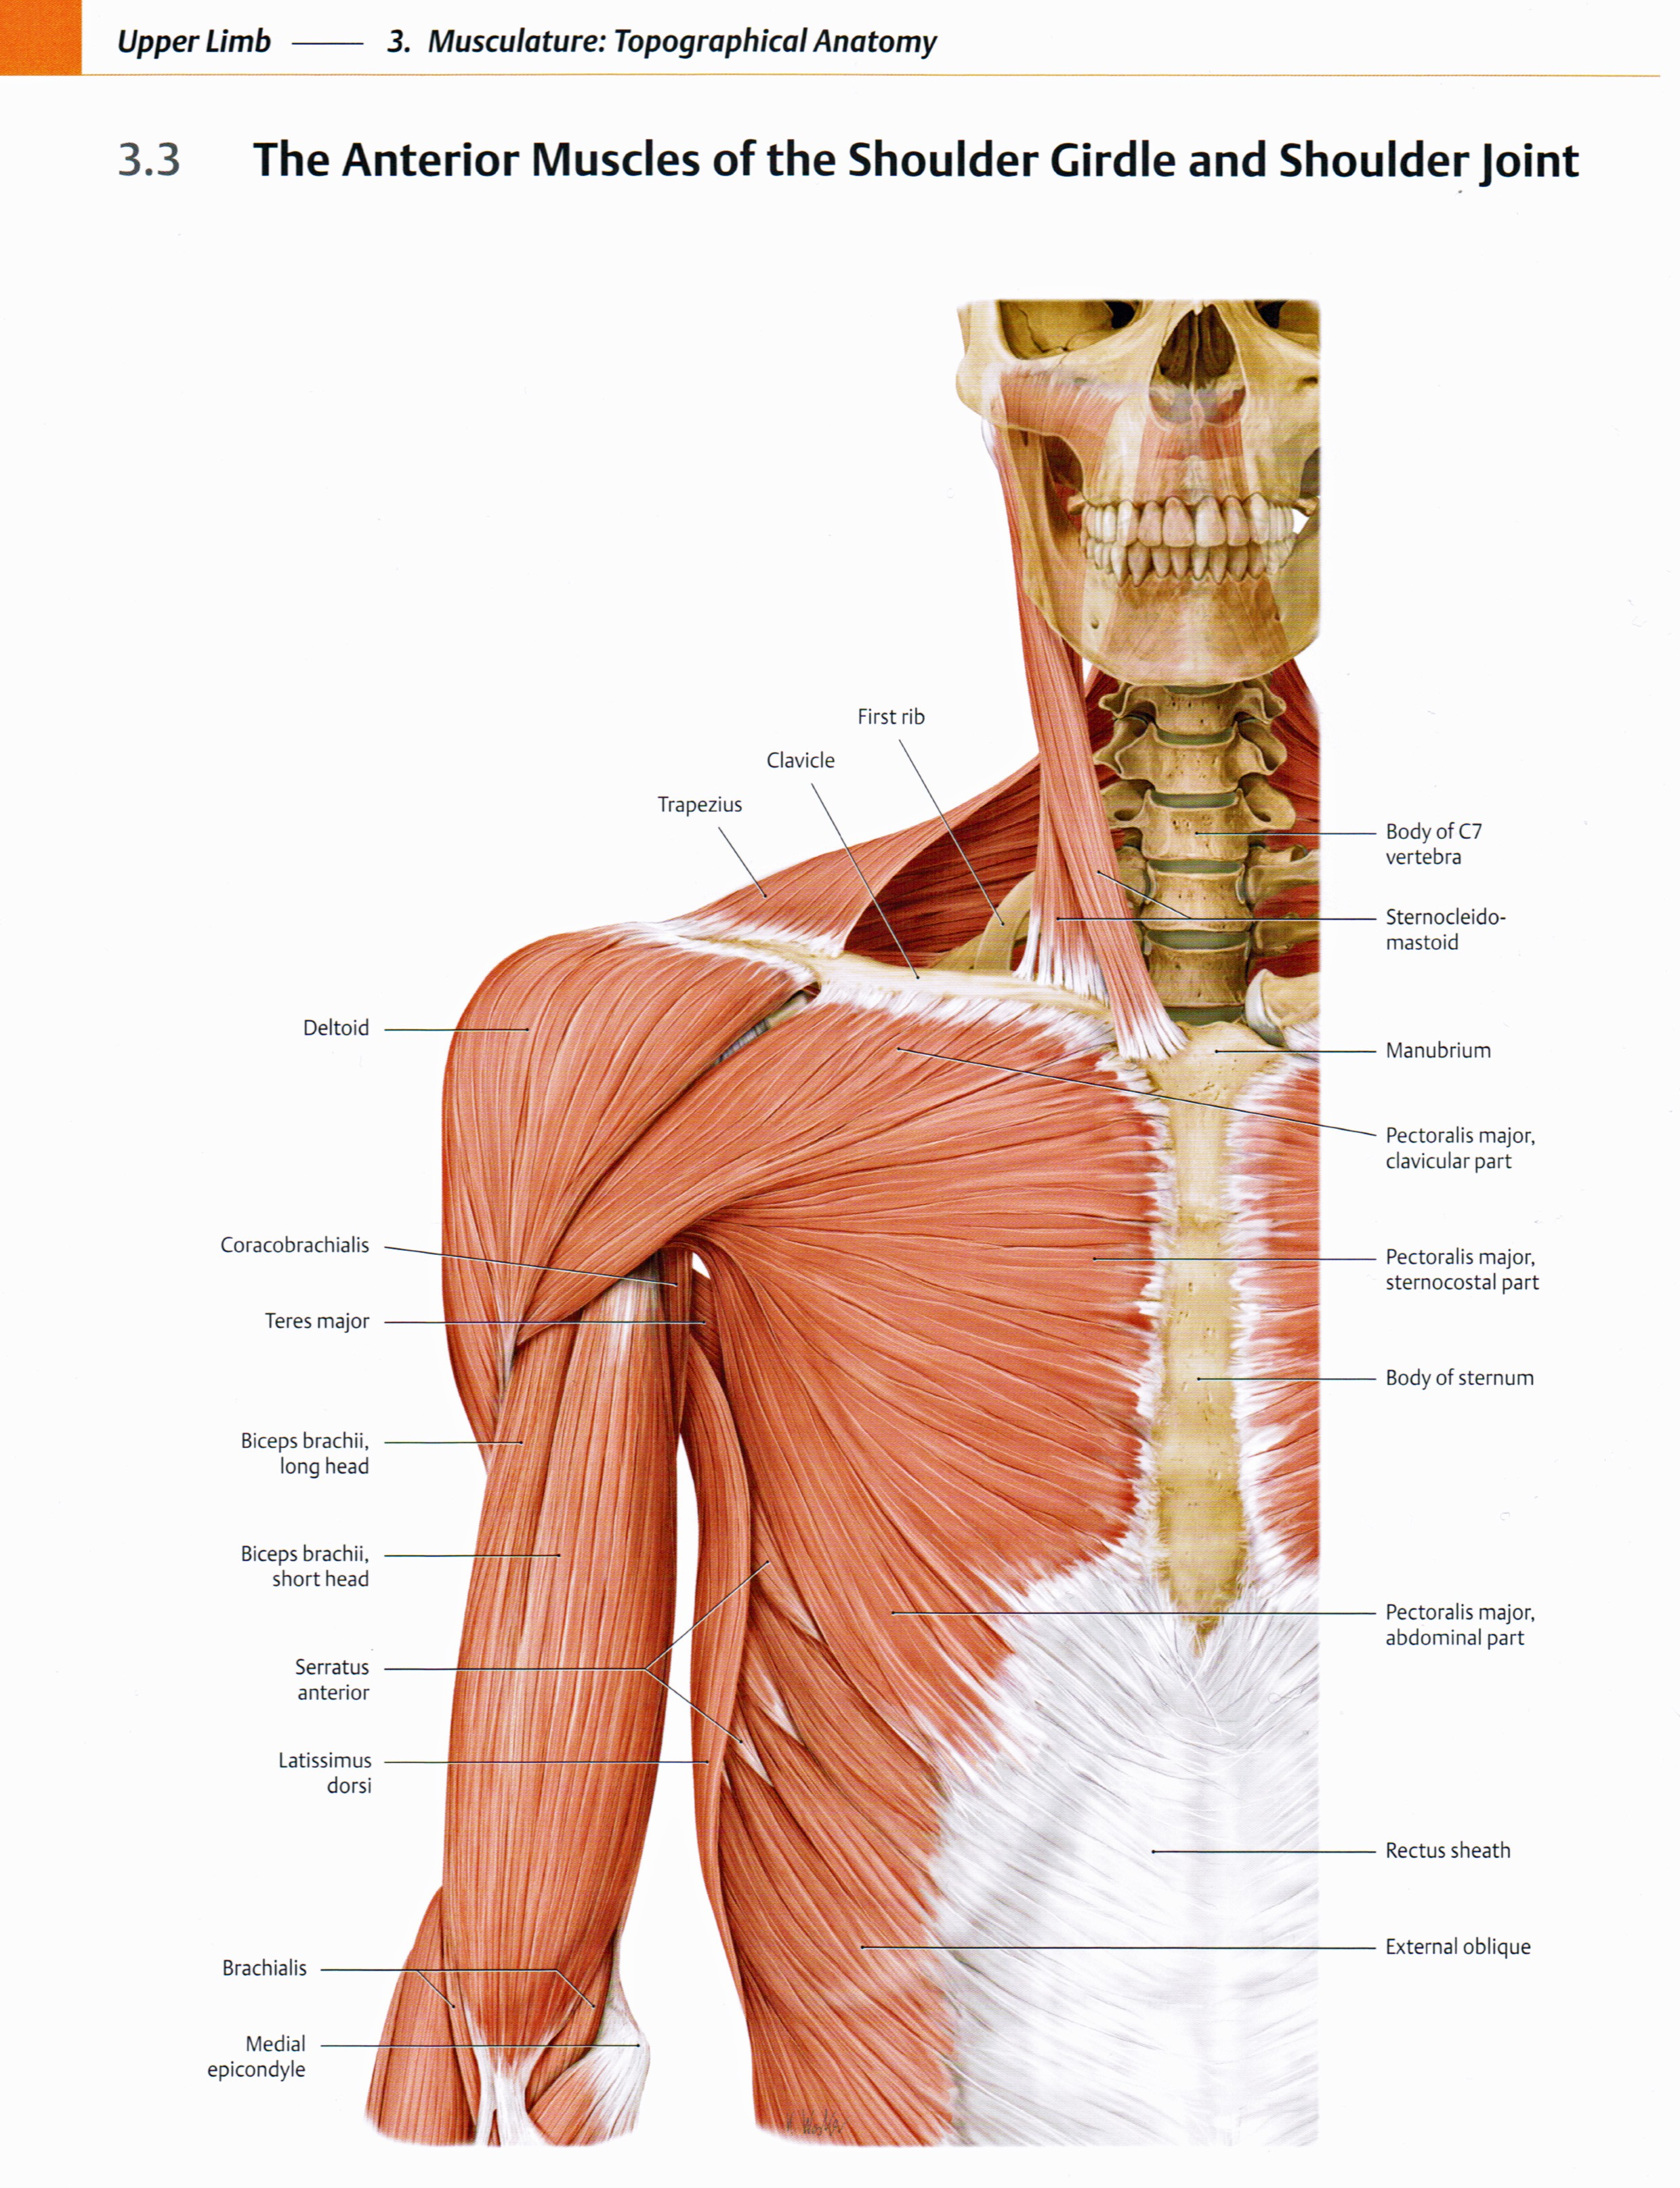
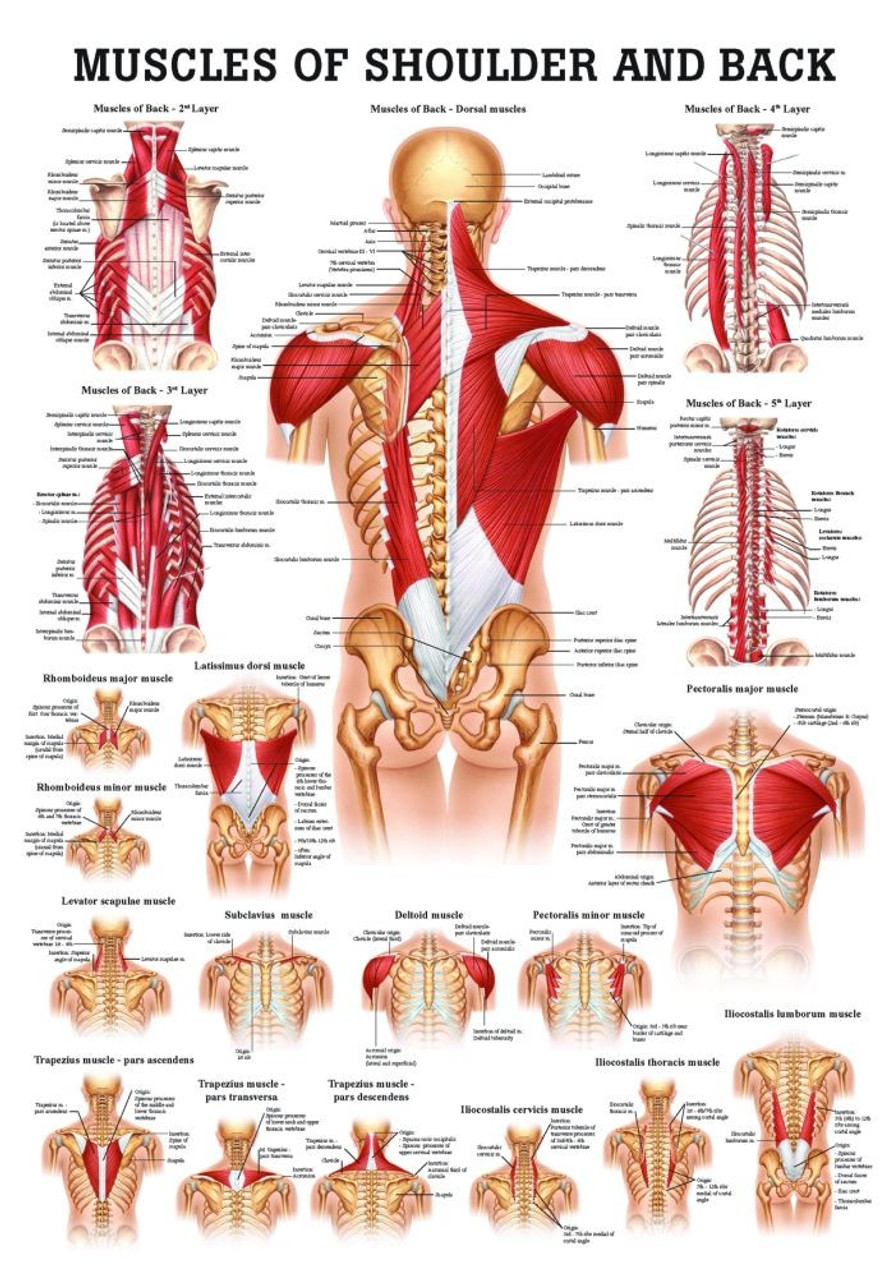
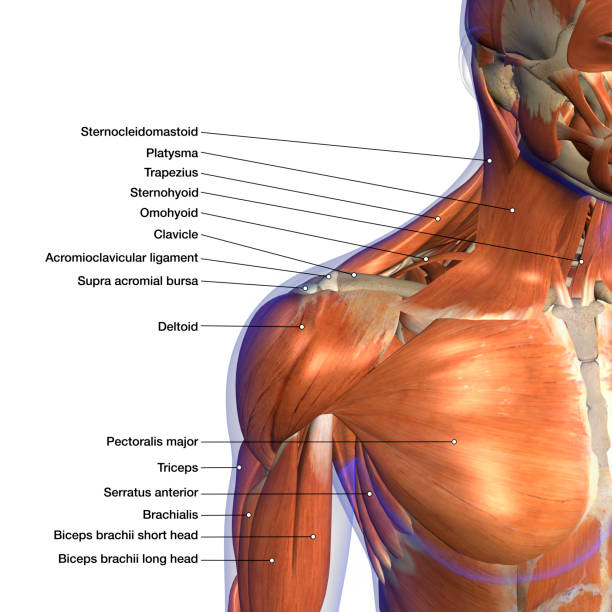
Most people google "neck and shoulder pain" and immediately start doing YouTube stretches they don't understand. That's usually fine for a sore trapezius after a long drive. It's not fine when you have nerve involvement or a disc issue. Before I dive into the anatomy, I want to mention something specific I dealt with last year. A guy came to me with chronic lateral neck pain that no amount of upper trap stretching relieved. We spent three sessions mapping out the actual structures involved. The problem wasn't his traps at all. It was his scalenes, specifically the middle scalene, which had adapted to a forward head posture he'd had for probably a decade. He'd been stretching the wrong muscle repeatedly, making the actual issue tighter because the compensatory pattern never changed. I ended up using direct compression with a small ball against the scalene band at the base of his neck while having him perform very gentle lateral flexion away from the side. It wasn't glamorous. It took about twenty minutes of focused work over two visits. He went from daily pain to manageable discomfort. The takeaway here is that anatomy isn't just a diagram on a wall. It's the difference between pressing on something and making it worse versus actually addressing what's contributing to the problem. The neck and shoulder complex works as a single kinetic chain. You can't really isolate one without the other affecting it. The primary movers and stabilizers include the sternocleidomastoid, the trapezius, the levator scapulae, the rhomboids, the rotator cuff muscles, and the scalene group. Each has a specific function, but they overlap constantly. When one adapts, others compensate. That's how you get the typical pattern where someone's shoulders are rolled forward, their neck is held stiffly, and they have tension headaches that never quite go away. The sternocleidomastoid runs from the sternum and clavicle up to the mastoid process behind the ear. It flexes the neck and rotates the head. When it's chronically shortened from looking down at a phone or screen all day, it pulls the head forward. This is one of the most common sources of tension headaches people mistake for stress. The trapezius is divided into upper, middle, and lower fibers. The upper fibers elevate the scapula and extend the neck. The middle fibers retract. The lower fibers depress. Most people have tight upper traps and weak lower traps. This imbalance pulls the shoulder blade upward and outward, creating that rounded shoulder appearance and contributing to impingement.
The levator scapulae attaches from the transverse processes of the upper cervical vertebrae to the superior angle of the scapula. Its job is to elevate the shoulder blade and rotate the neck. It's the muscle that gets tight when you carry a heavy bag on one shoulder or sleep in an awkward position. The rotator cuff consists of four muscles: supraspinatus, infraspinatus, teres minor, and subscapularis. They stabilize the humeral head within the glenoid fossa. Here's where people get it wrong. Rotator cuff issues aren't always about the cuff itself. Sometimes the problem originates from scapular dyskinesis, meaning the shoulder blade isn't moving correctly, which forces the rotator cuff to compensate. I've seen this repeatedly in people who do overhead pressing with poor scapular control. The cuff gets irritated not from the exercise itself but from the faulty movement pattern. The scalenes are often overlooked. They attach from the cervical vertebrae to the first and second ribs. They assist in neck flexion and elevation of the ribs during breathing. When they're tight, they can compress the brachial plexus, leading to symptoms that mimic other conditions. Numbness, tingling, or weakness traveling down the arm isn't always a cervical disc problem. Sometimes it's the scalenes. I've encountered this enough times now that I check them before I check anything else when someone presents with unilateral arm symptoms without a clear neurological sign.
How to Approach Release Work Without Making Things Worse
Start with the larger muscles before the smaller ones. If you begin by aggressively working the scalenes or the rotator cuff while the trapezius and sternocleidomastoid are still tight, the surrounding tissues will just pull back and the deeper work won't take. It's a basic principle but one that most people skip. The standard approach is to begin with the upper trapezius, then move to the levator scapulae, then the scalenes, and finish with the rotator cuff and deeper neck flexors if needed. For the upper trapezius, find the band between your neck and shoulder. Apply firm but tolerable pressure with your fingers or a tennis ball against a wall. Hold for thirty to sixty seconds while breathing slowly. The goal isn't to make it hurt as much as possible. The goal is to apply enough pressure to engage the tissue without triggering a defensive contraction. If the muscle tenses up under the pressure, you're going too hard. Ease off slightly. The muscle needs to feel safe enough to release. The levator scapulae is trickier because of its location. Rotate your head about forty-five degrees toward the side you're working, then tilt your chin down toward your armpit. This shortens the muscle. Apply pressure with your fingers just medial to the shoulder blade on the inner border. A partner can help here, but a small ball works too. I usually recommend a grapefruit-sized ball for the traps and a smaller ball, maybe the size of a lime, for the levator and scalenes. The bigger the surface area, the more diffuse the pressure, which is better for broader muscles. Smaller targets need more focused pressure.
Get the Full Details

When working the scalenes, be careful. They sit deep in the neck and there are major blood vessels and nerves nearby. Use light to moderate pressure. Lighter than you might expect. Place your fingers on the side of your neck, just anterior to the sternocleidomastoid. Apply gentle compression while performing slow neck rotations. The combination of compression and movement helps the tissue adapt more effectively than static pressure alone. This is the technique I used with the guy I mentioned earlier. The movement component was what allowed the scalene to let go after weeks of failed static stretching. For the rotator cuff, the supraspinatus is the most commonly problematic muscle. Lie on your side with a small folded towel under the affected arm. The elbow should be bent at about ninety degrees. Apply gentle pressure to the area just below the shoulder blade's acromion process. This is where the supraspinatus tendon passes through. Don't press directly on bone. Aim for the soft tissue just lateral to the acromion. Hold for thirty seconds. If you feel any sharp pain or numbness, stop immediately. That's not a good sign.
Common Mistakes and What to Do Instead
The biggest mistake I see is treating symptoms without understanding the root cause. Someone has shoulder pain, so they stretch their pecs and strengthen their upper back. That's reasonable for general posture issues. But if the pain is actually coming from cervical joint dysfunction or a rotator cuff tear, those exercises won't help and might make things worse. The neck and shoulder are connected through multiple neural pathways. Irritation in the C5-C6 region can refer pain directly into the shoulder. If you have shoulder pain that doesn't respond to standard soft tissue work after two or three weeks, get it checked. Don't just keep working the same muscles and hoping something changes. Another common error is overstretching the neck. Holding a deep lateral flexion stretch for two minutes doesn't necessarily do anything beneficial. In fact, sustained passive stretching can sometimes irritate the tissue further, especially if the muscle is already in a protective spasm. Shorter, active stretches are more effective. Move into the stretch range, hold for five to ten seconds, return to neutral, and repeat. This approach engages the muscle more actively and avoids the stretch reflex that can trigger tightening instead of release. Posture advice gets thrown around constantly, but most of it is useless without context. "Sit up straight" doesn't account for the fact that your desk setup, your monitor height, your chair, and your work habits all contribute to your posture. If you sit at a computer all day with the monitor too low, your head will be forward regardless of how "straight" you try to sit. Adjust the environment first. Raise the monitor so the top of the screen is at or slightly below eye level. This alone will reduce the load on your neck significantly. The head weighs about ten to twelve pounds in a neutral position. For every inch it moves forward, the effective load increases by roughly five pounds. At two inches forward, you're carrying an extra ten pounds of force on your cervical spine. That's not dramatic. That's just physics.
When Anatomy Work Won't Help
I need to be clear about the limitations here. This kind of self-directed anatomy and release work is useful for muscular tension, mild postural issues, and general maintenance. It will not fix a herniated disc. It will not reverse osteoarthritis. It will not repair a full-thickness rotator cuff tear. If you have persistent pain that radiates past the elbow, loss of grip strength, numbness that doesn't change with position, or pain that wakes you up at night, stop whatever you're doing and see a professional. These are red flags that require proper medical evaluation. Even within the scope of muscular issues, there are times when self-treatment hits a ceiling. If you've been working the same areas consistently for three weeks with no improvement, something else is going on. Maybe the source is different than you assumed. Maybe there's a joint issue contributing to the problem. Maybe your overall loading patterns need adjustment. I've had people come to me after months of self-treatment who had no progress. The issue turned out to be a combination of scapular dyskinesis and mild cervical facet irritation. Neither of those would have responded to isolated muscle work. The solution required a more comprehensive approach including mobility work, motor control retraining, and sometimes manual therapy from a qualified practitioner. One more thing worth noting: the relationship between breathing and neck tension. The scalenes and accessory respiratory muscles get recruited during shallow, rapid breathing. If you tend to breathe from your upper chest rather than your diaphragm, your neck muscles are working overtime with every breath. This is especially common in people who are stressed, anxious, or have been in pain for a long time. The pain creates tension, the tension affects breathing, the breathing pattern reinforces the tension. It's a cycle that doesn't break on its own. Practicing diaphragmatic breathing for ten minutes a day can reduce the chronic recruitment of the scalenes and upper trapezius. It's not a cure for everything, but it addresses a contributing factor that most people ignore.
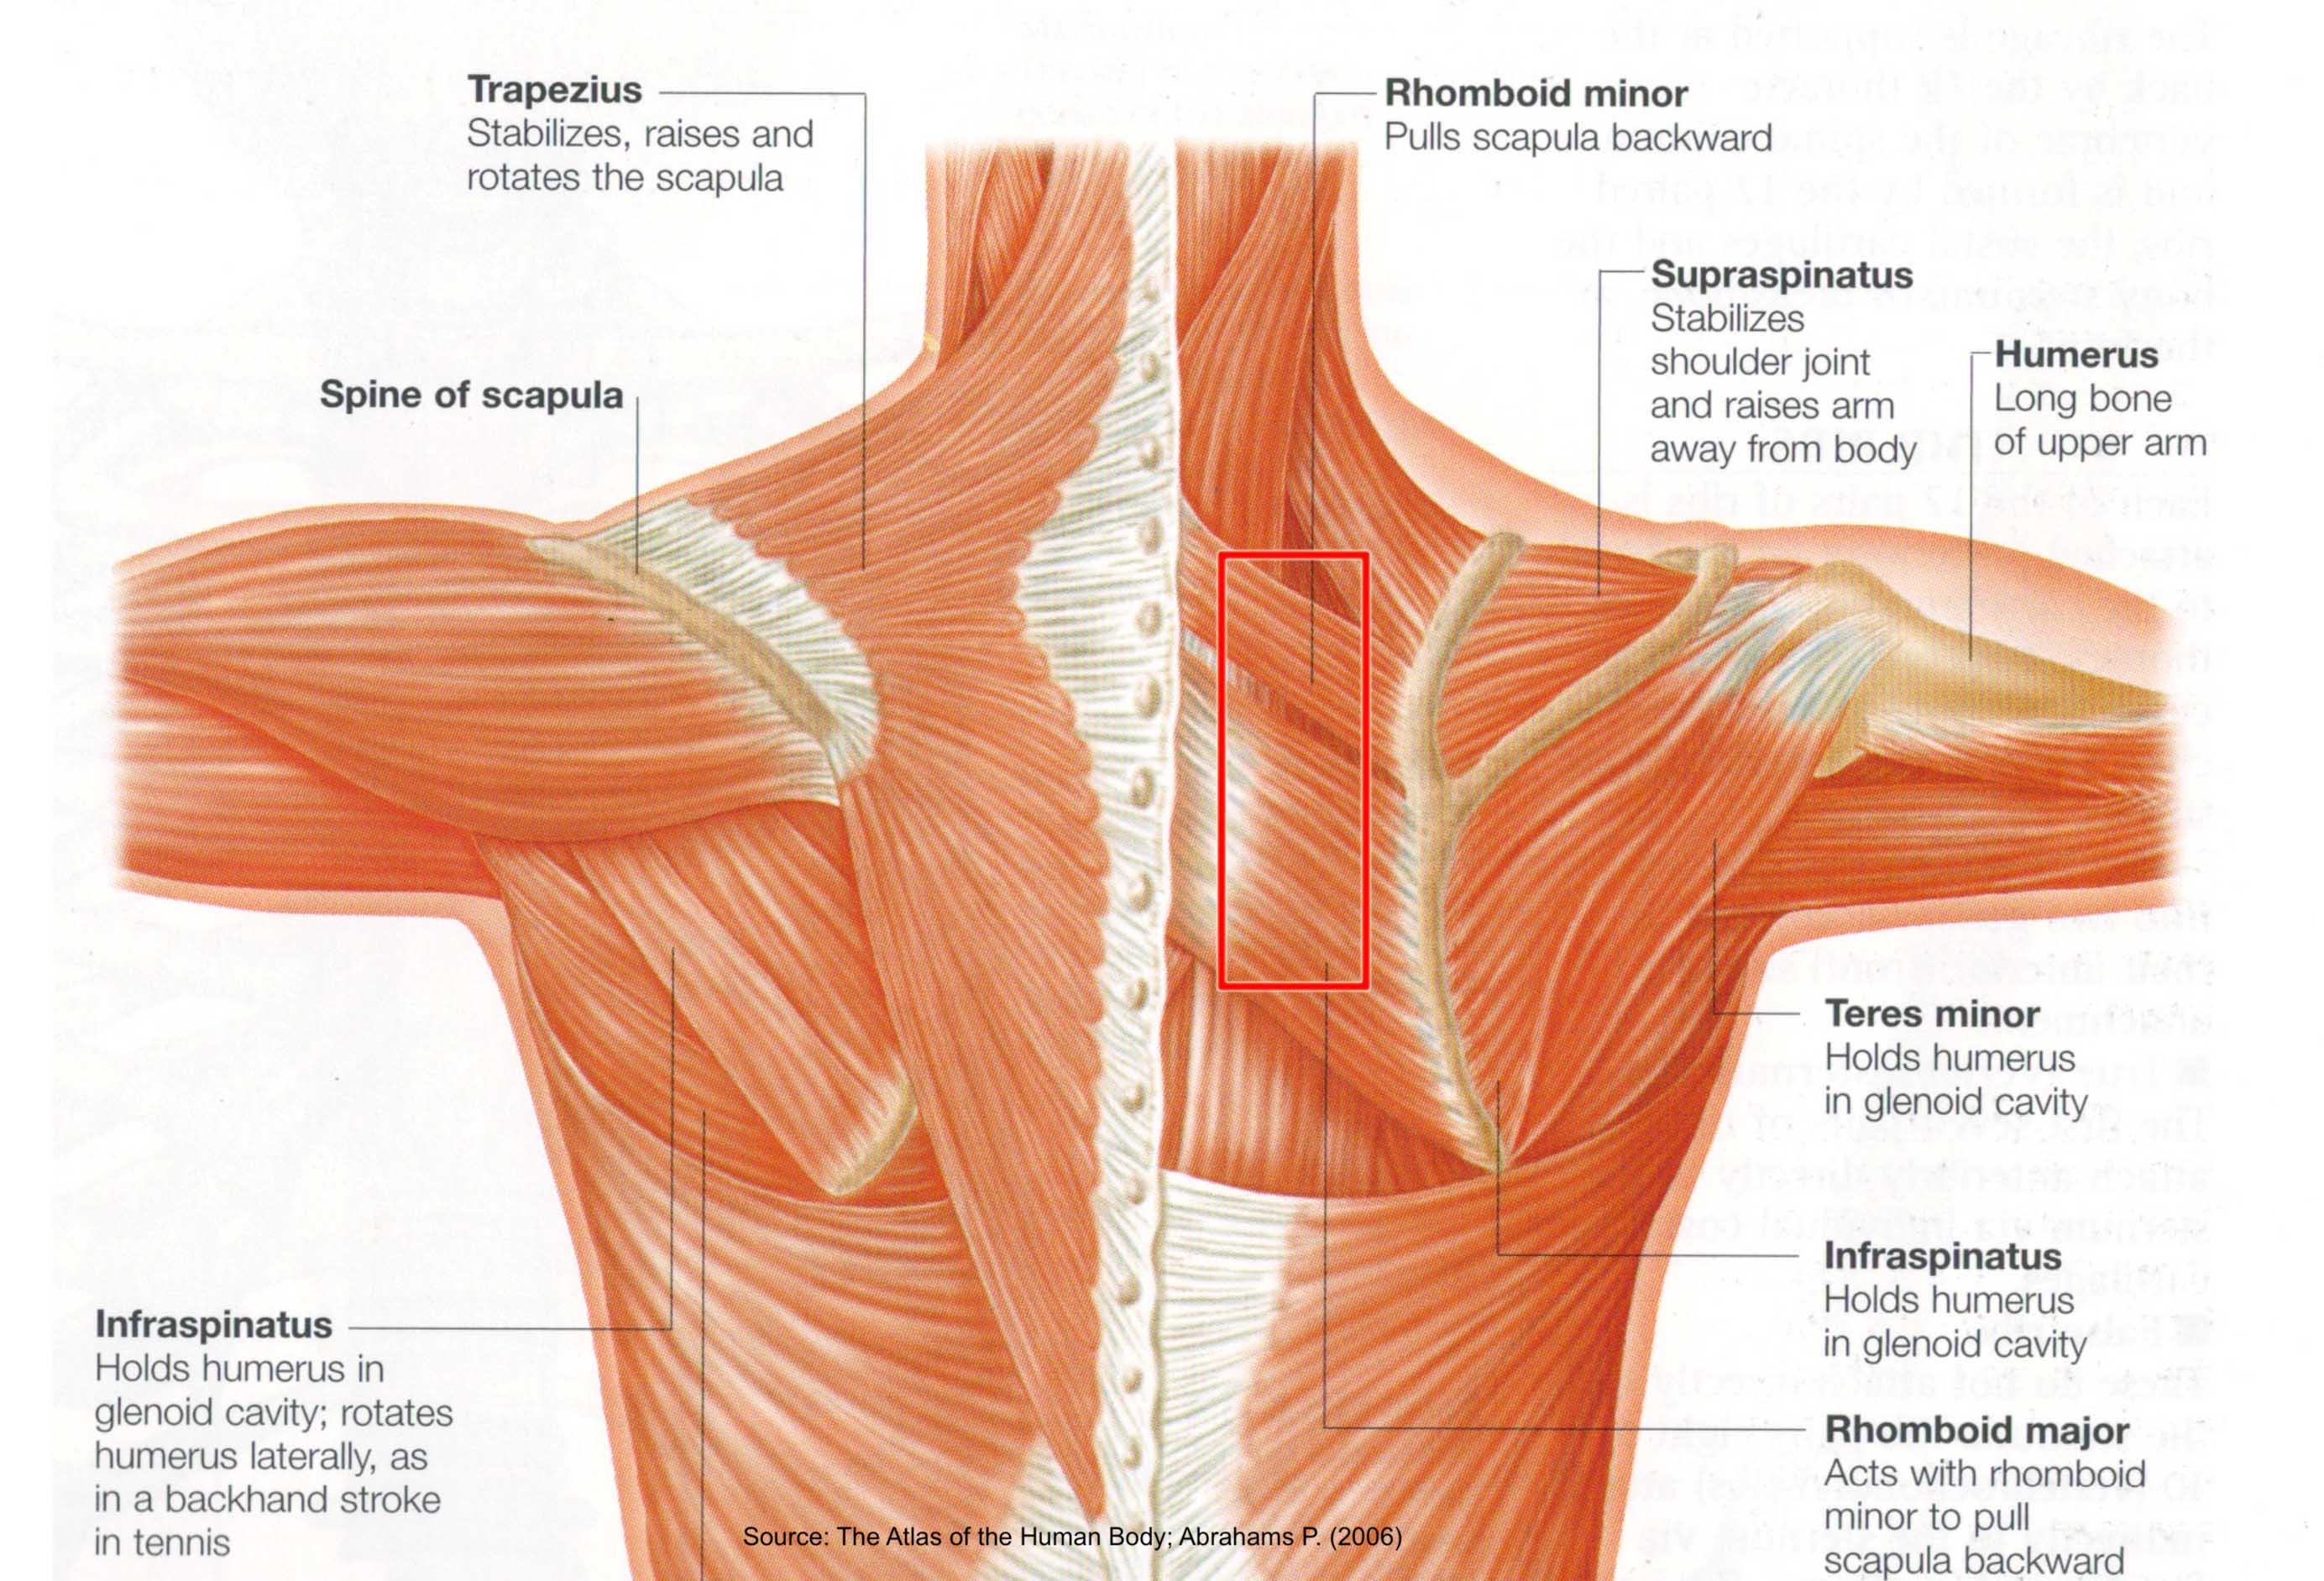
The anatomy of the neck and shoulder is complicated because it's complicated. It's not a simple problem with a simple solution. The structures are interdependent. The functions overlap. The compensations are real and they persist. Understanding how these muscles work together gives you a framework for approaching the area intelligently. It doesn't guarantee results, but it does give you a better chance of doing the right thing rather than the obvious thing. Start with the basics. Be patient. Pay attention to what your body tells you. And know when to step back and get help rather than pushing through something that isn't responding.