The Technical Reality Of Neck Dissection
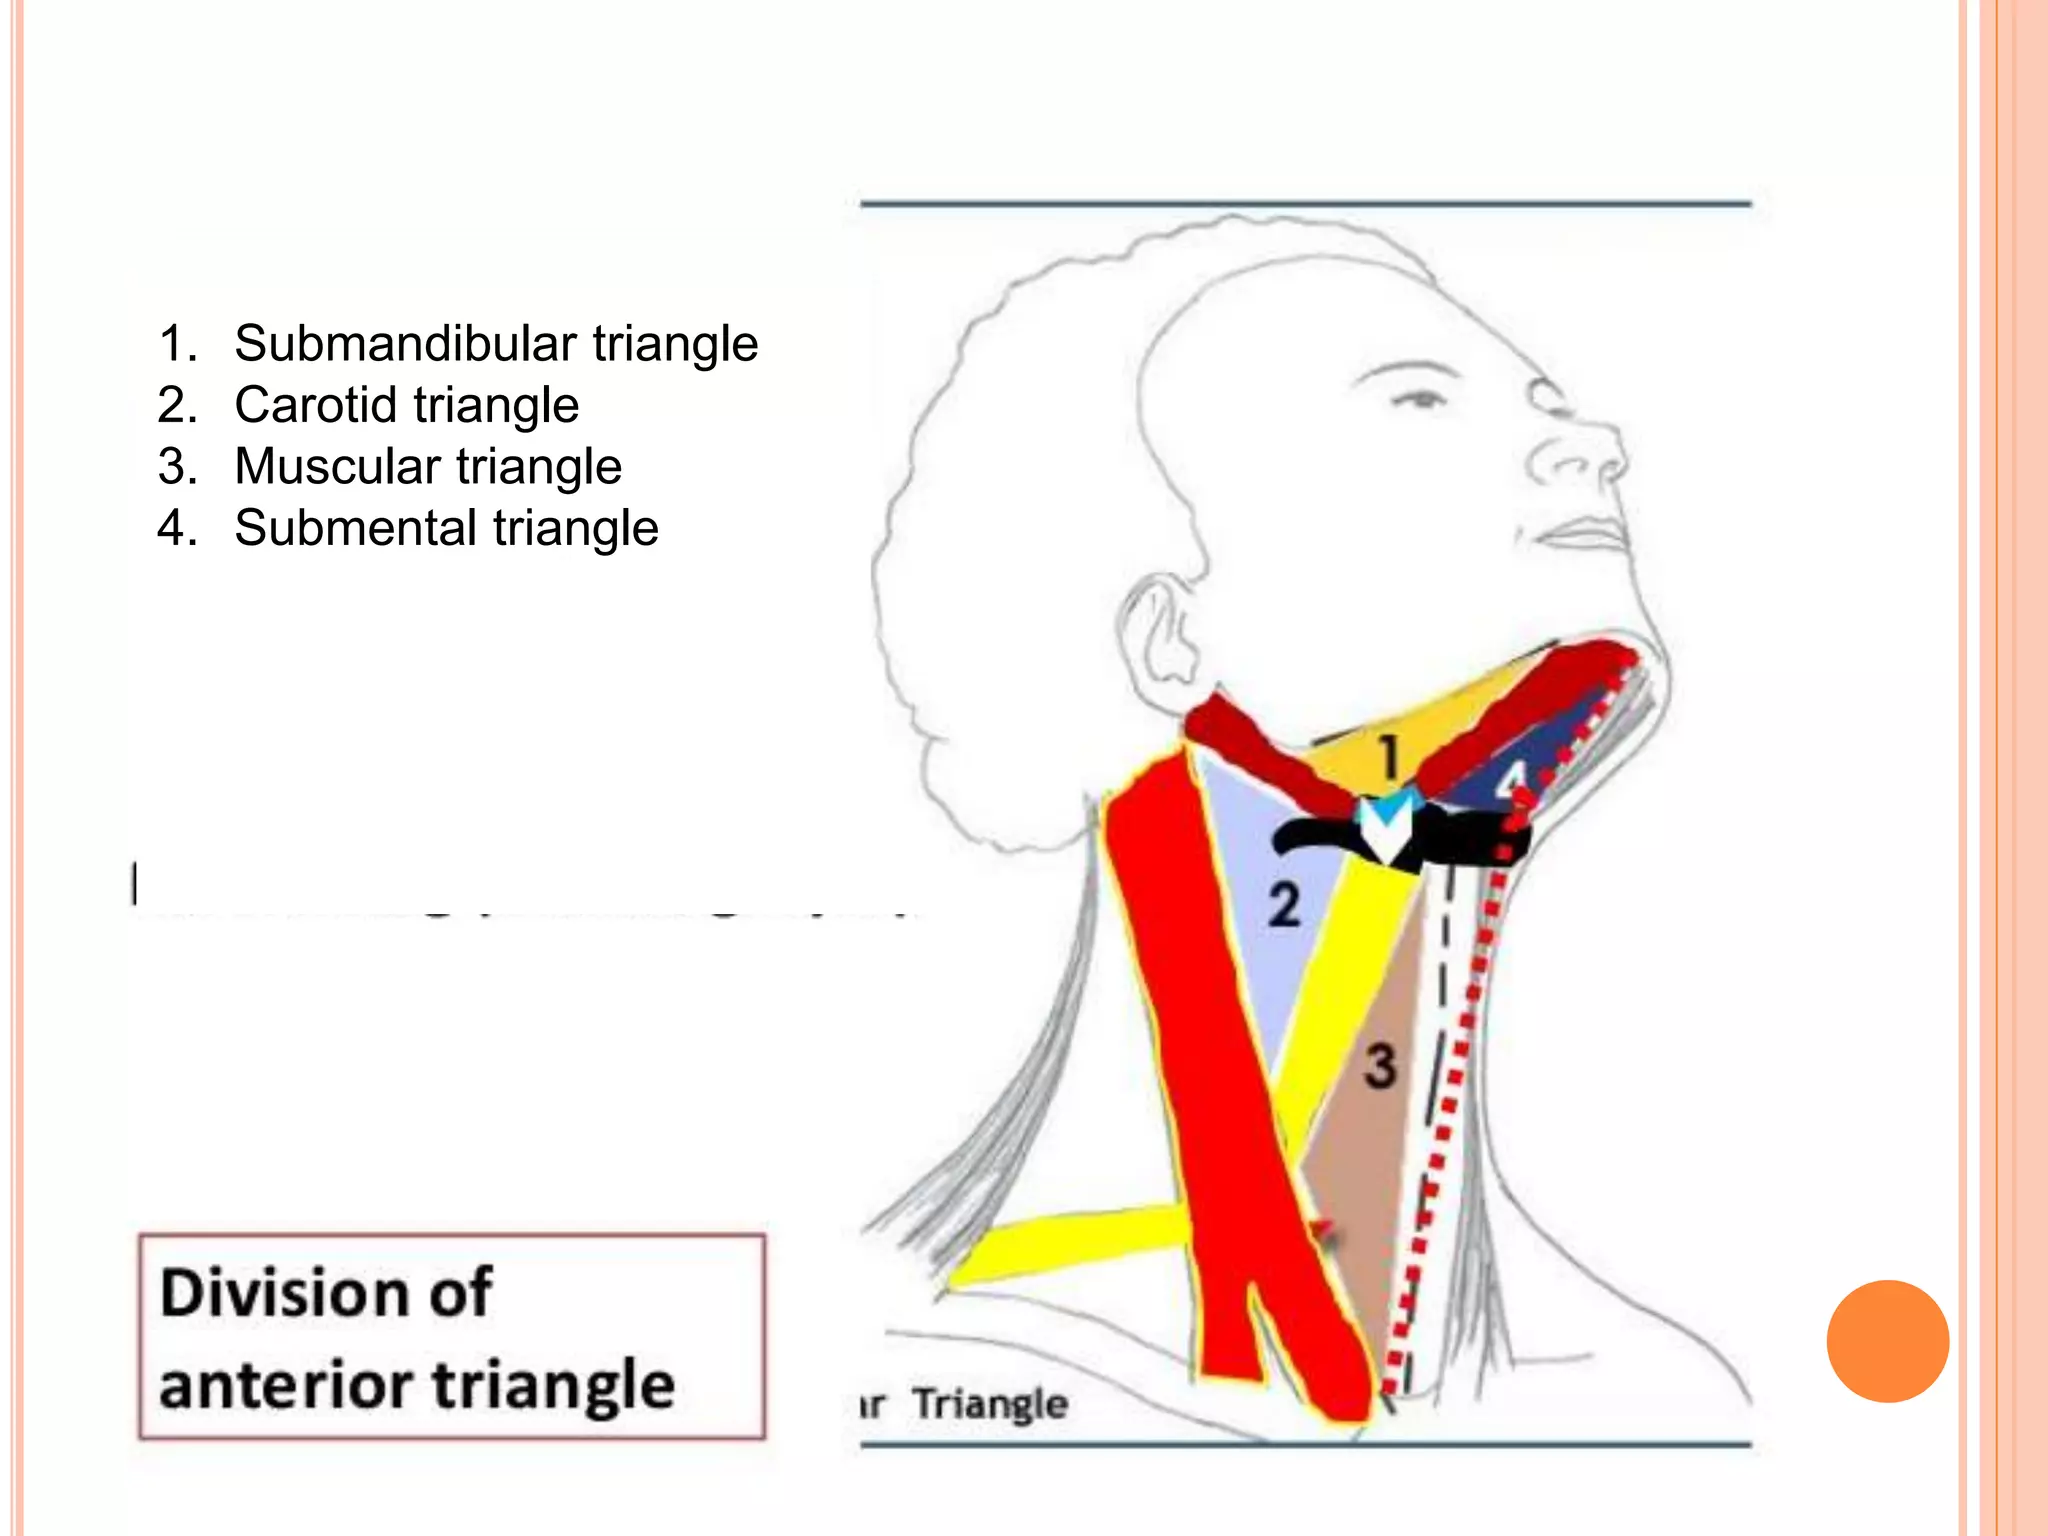
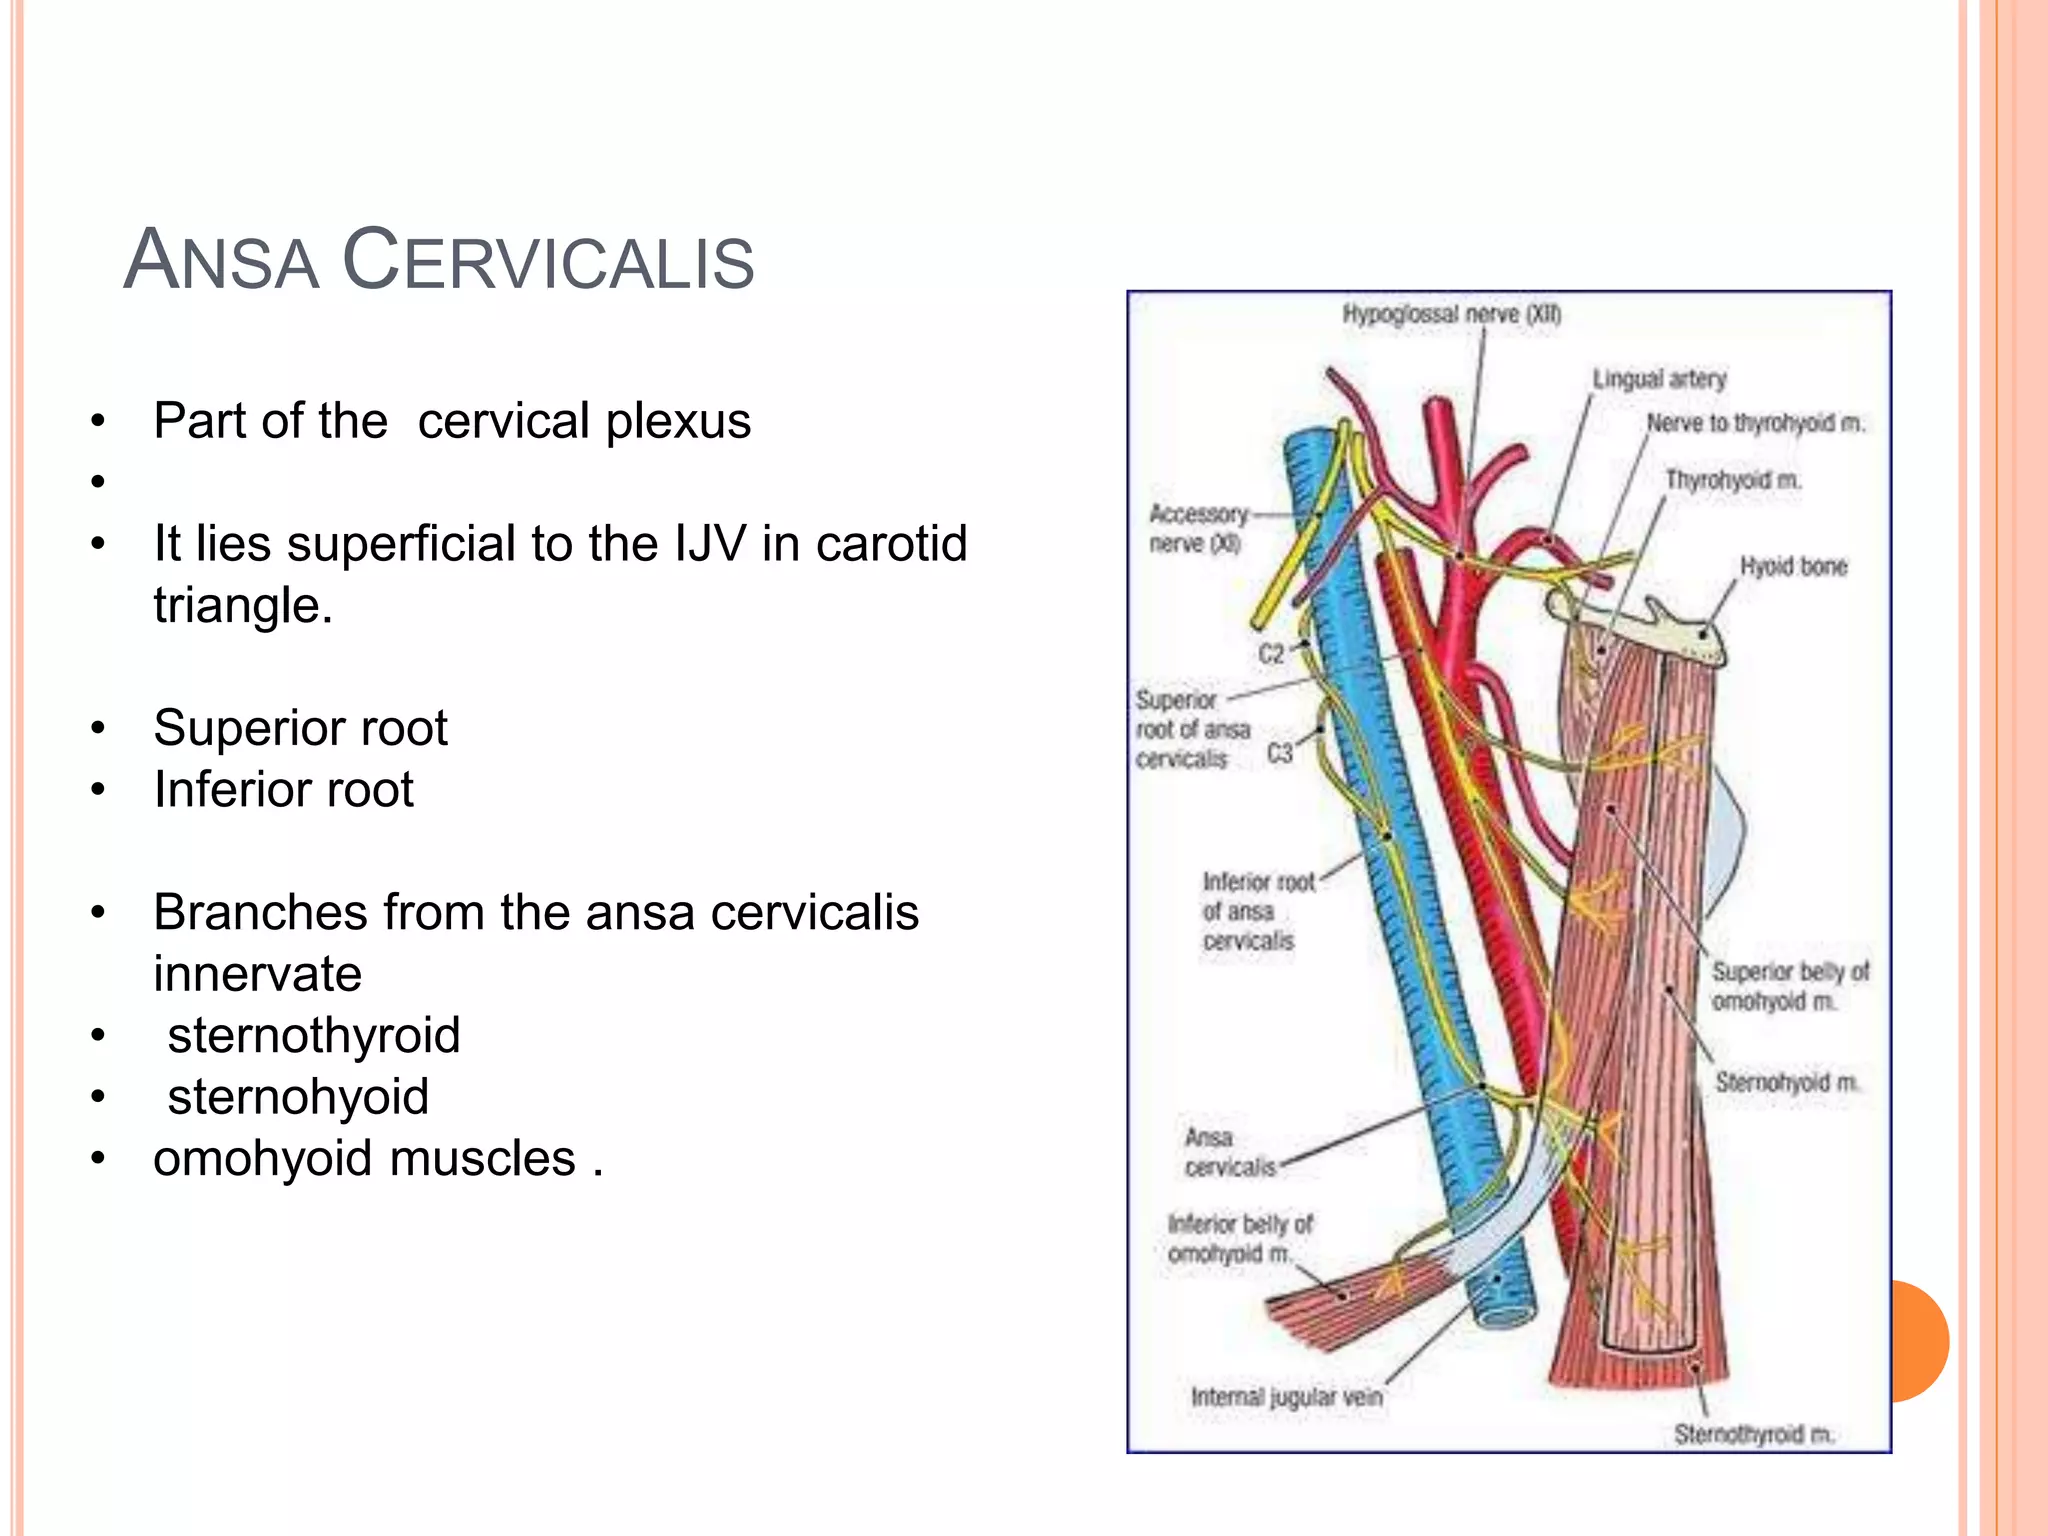
Most residents learn the layers in order — skin, subcutaneous tissue, platysma, deep cervical fascia — and they move on. But the actual Anatomy Of Neck Dissection matters far more than memorizing layers sequentially. You need to understand what happens when those layers don't behave like the textbook diagrams suggest.The neck is organized around fascial planes, and those planes are your roadmap. The investing layer of deep cervical fascia wraps everything. If you stay within that plane, you lose relatively little blood and you keep structures protected. If you drift out of it, you're running into the carotid sheath, the spinal accessory nerve, or the marginal mandibular branch of the facial nerve before you realize you've crossed a boundary. In practice, the most critical structures you're negotiating around are the sternocleidomastoid, the internal jugular vein, the common carotid artery, and the hypoglossal nerve. The spinal accessory nerve (CN XI) runs across the posterior triangle and is the single most commonly injured nerve in a neck dissection. Not because it's hard to see, but because it's easy to mistake for fibrofatty tissue when you're deep in the dissection and lighting isn't perfect. I've seen two separate cases in my first five years where the marginal mandibular branch was transected because the surgeon was working too aggressively near the angle of the mandible. This nerve loops downward and forward just below the mandible before ascending to innervate the depressor muscles of the lower lip. It's thin, it's pale, and it sits right on top of the facial artery at the border of the submandibular gland. If you don't identify it early and trace it, you will miss it until it's too late.
The parotid gland adds another layer of complexity. The facial nerve branches fan out through the gland in a predictable pattern, but the plane between the gland and the masseter varies from person to person. I worked a case once where the extracapsular dissection of the parotid was supposed to be straightforward, but the patient had significant periparotid fat that obscured the nerve branches entirely. I ended up doing a superficial lobectomy instead of a facial nerve-sparing extracapsular dissection because the anatomy just didn't permit safe identification of each branch. Took twenty minutes longer, but the patient woke up with intact facial movement.
What The Standard Models Miss
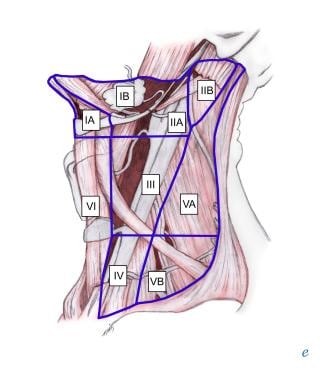
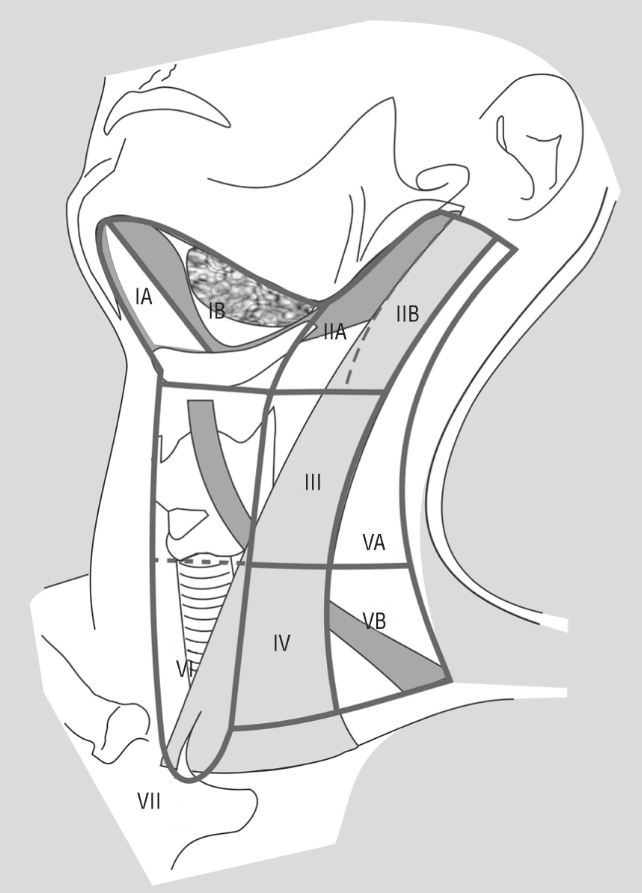
The typical cadaver dissection shows clean, obvious planes. In the living patient, those planes are obliterated by tumor infiltration, prior radiation fibrosis, or previous surgical scarring. A neck that has been irradiated doesn't have fascial planes anymore. It has scar tissue that sticks to everything. You can't just "follow the plane" because there is no plane. You're essentially doing sharp dissection through scarred tissue millimeter by millimeter, and the margin between safe and dangerous is a. Another thing nobody emphasizes enough: the level system used for neck dissections (levels I through V) is a simplification. The boundaries between levels aren't anatomical landmarks you can point to. They're arbitrary surgical convenience. Level II and Level III, for instance, are separated by the inferior border of the hyoid bone on paper, but in a real dissection that boundary is porous. Lymphatic drainage doesn't respect that line. I've removed what I thought was a level III node only to find it was actually a level II node that had migrated inferiorly due to a patient's chronic lymphedema from prior treatment. You have to think in terms of lymphatic basins, not just boxes on a diagram. The omohyoid muscle is one of those landmarks that is supposed to separate level III from level IV. In practice, it's often atrophic or absent in older patients or patients who have had prior surgery. If you wait for it to appear before you start dissecting toward level IV, you'll be waiting forever. The reliable landmark is actually the crossing of the internal jugular vein over the omohyoid, not the muscle itself.
Get the Full Details
A Practical Walkthrough
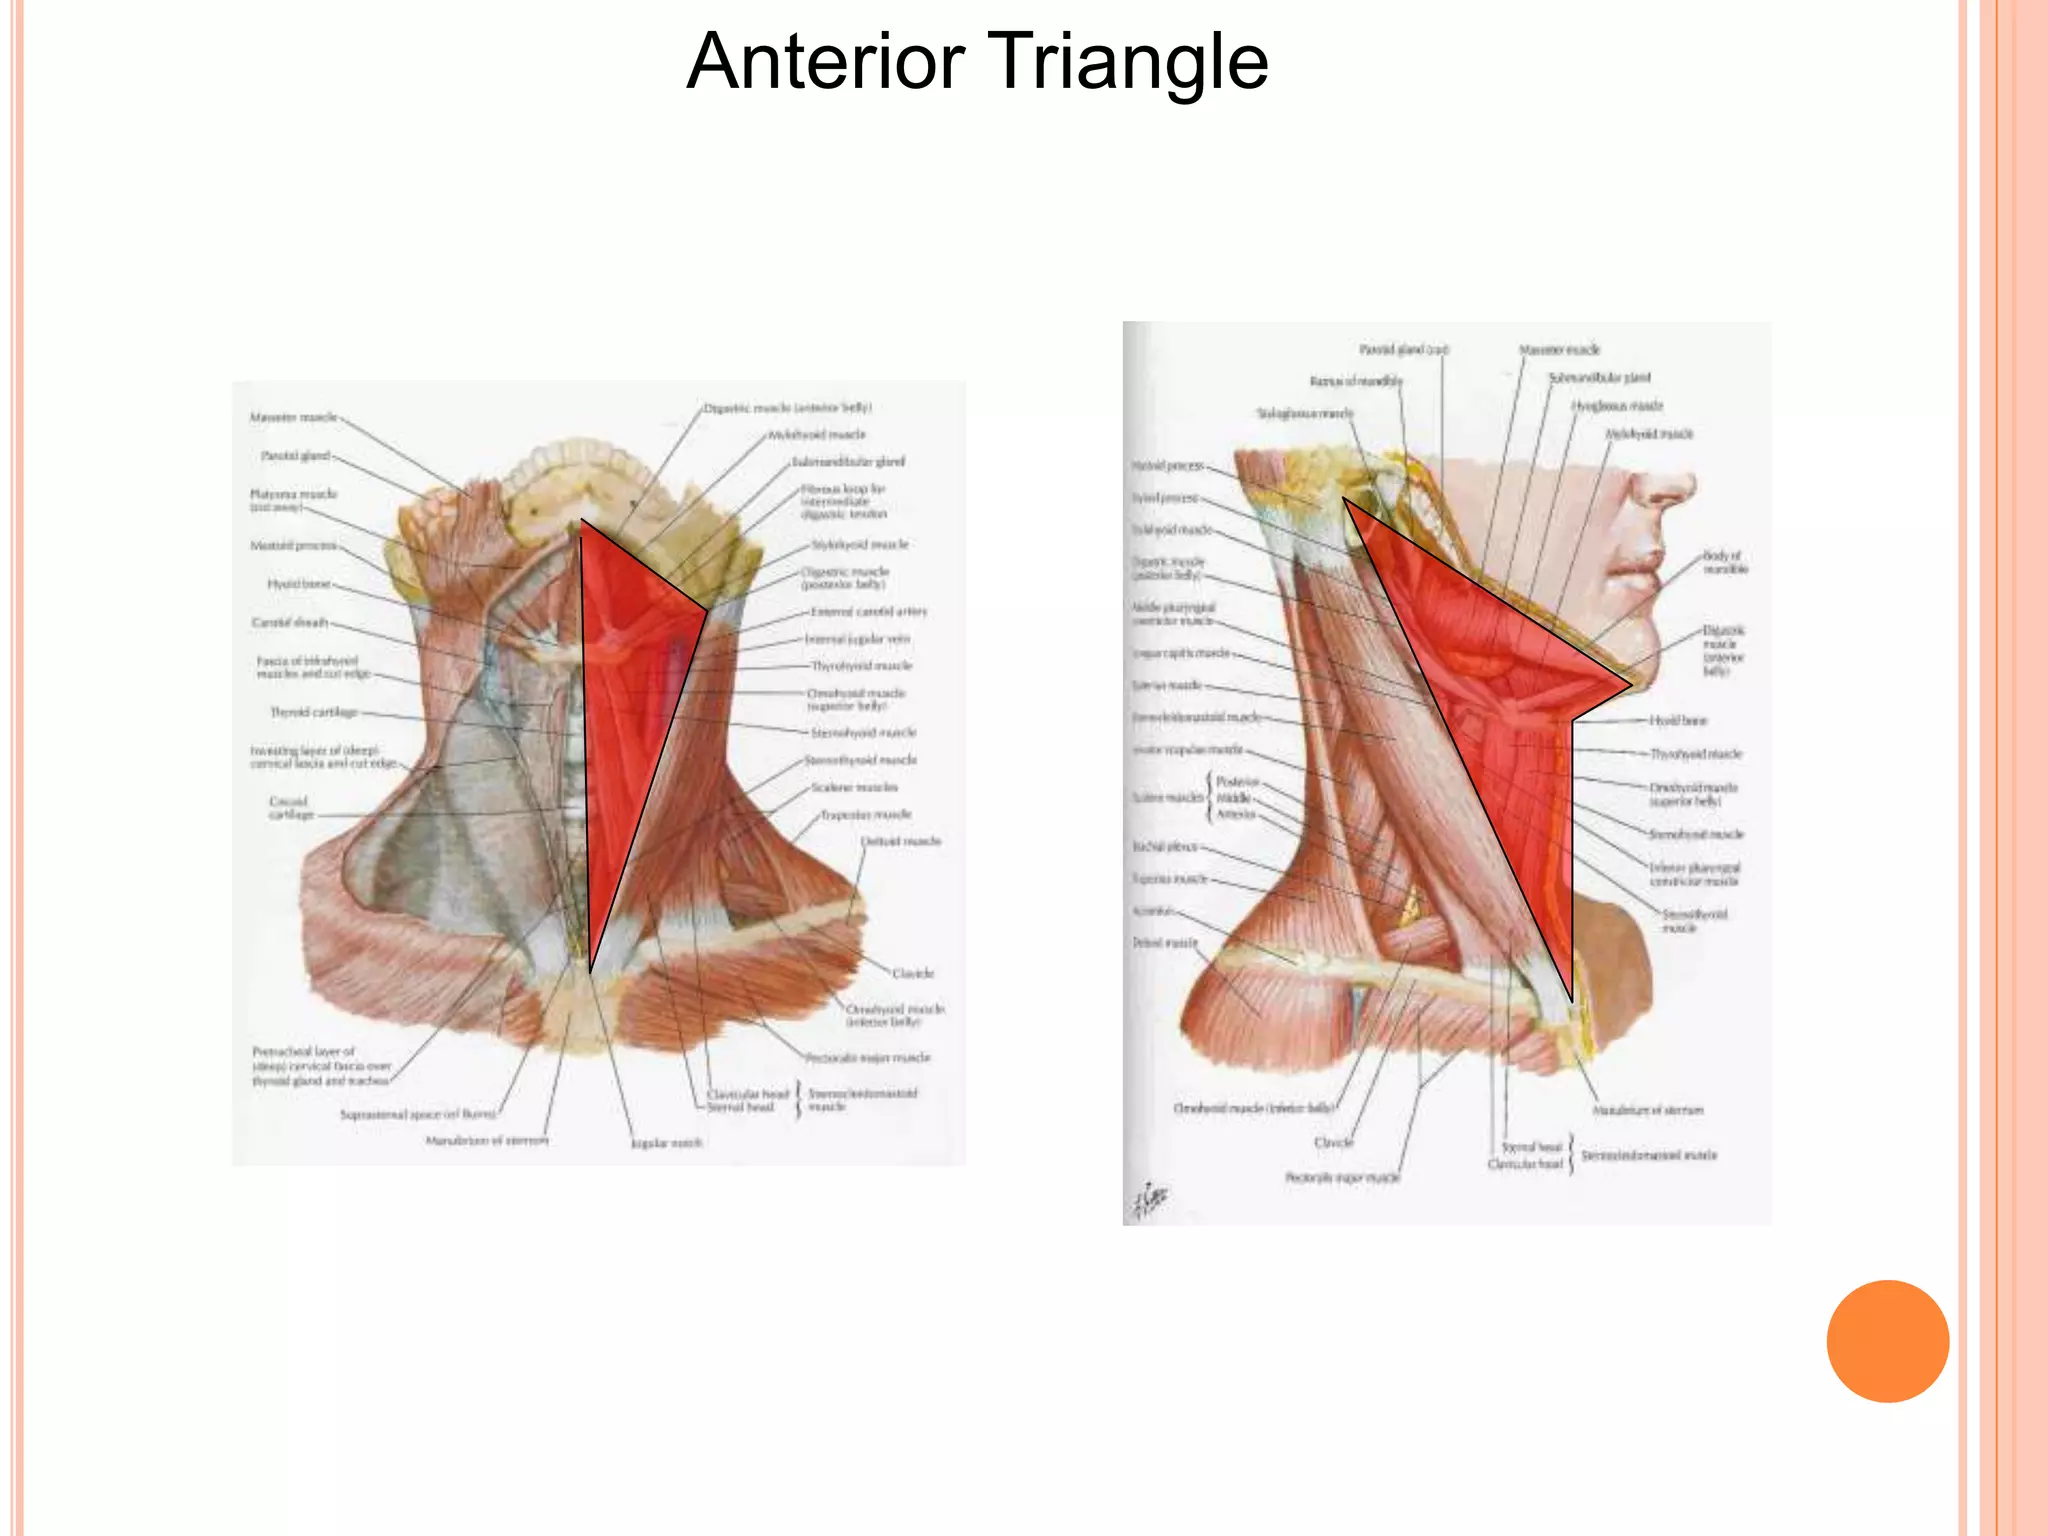
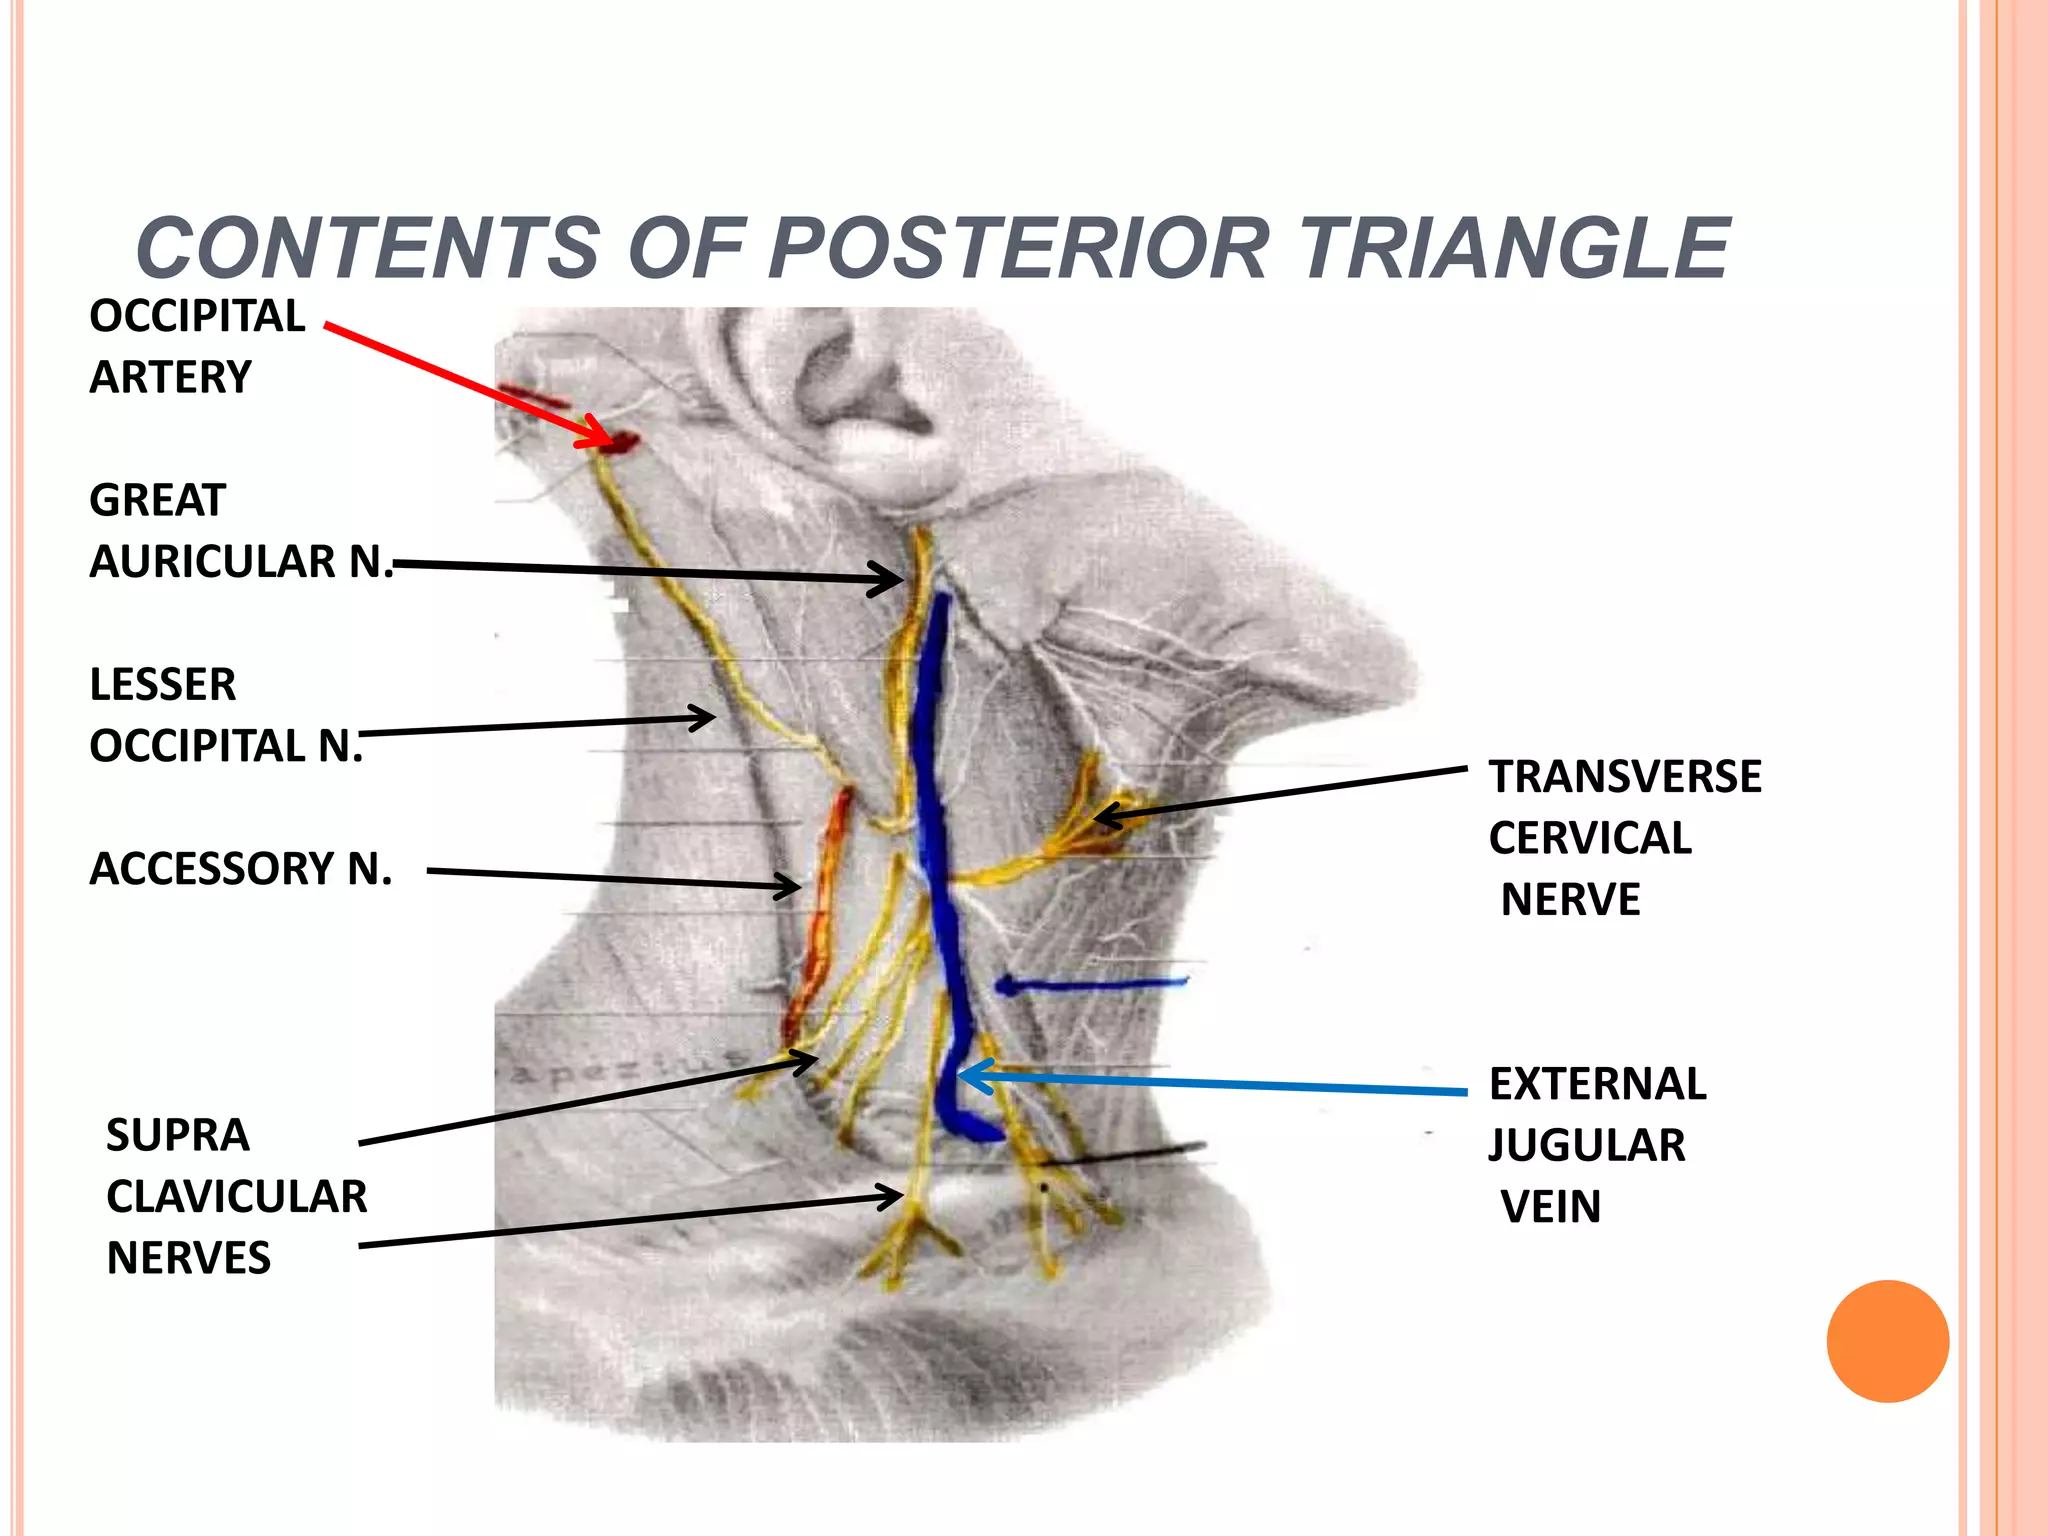
When you're performing a modified radical neck dissection, you start with the incision and the flap elevation. The plane here is subplatysmal. You want to stay above the platysma but below the subcutaneous fat. That sounds simple but the thickness of the subcutaneous layer varies enormously. In obese patients, the flap is thick and bloody because you're cutting through fat rather than along a clean plane. I usually switch to electrocautery at a lower setting and use blunt-tipped scissors for flap elevation in these cases. It takes longer but the bleeding is more manageable. Once the flap is elevated, you expose the sternocleidomastoid and reflect it. The next step is identifying the marginal mandibular nerve. The most reliable technique I use is to find the facial artery as it crosses the mandible at the anterior border of the masseter. The nerve lies just superficial to the artery at that point. Once you identify the artery and gently retract it inferiorly, the nerve is usually visible as a thin white cord running along its superior aspect. Trace it medially toward the corner of the mouth and you know exactly where your upper limit is. For the superior limit of a standard neck dissection, you're working near the skull base. The great auricular nerve and the auriculotemporal nerve are the main concerns here. The great auricular nerve emerges from behind the sternocleidomastoid about two centimeters below the earlobe and ascends toward the ear. It carries sensation to the skin over the parotid region and the ear itself. If you sacrifice it, the patient will have numbness in that area but no functional deficit. Most surgeons preserve it when possible, but if it's adherent to tumor, resection is acceptable. The trade-off is straightforward.
Level II nodes sit between the skull base and the posterior belly of the digastric. Level III nodes extend from there down to the inferior border of the hyoid. Level IV goes from the hyoid to the cricoid arch. Level V is the posterior triangle, bounded by the trapezius posteriorly, the sternocleidomastoid anteriorly, and the clavicle inferiorly. Level VI is the central compartment, anterior to the trachea and esophagus, and is the one most often accessed for thyroid cancer metastases.
When Things Go Wrong
The internal jugular vein is the structure most at risk of catastrophic bleeding during a neck dissection. It's thin-walled, it's under negative pressure, and when it's injured, air embolism is a real concern, especially if the patient is in a semi-sitting position. I've seen a small tear in the IJ lead to a venous air embolism that dropped the patient's end-tidal CO2 by fifteen percent in under thirty seconds. The fix was immediate — flood the field with saline, apply direct pressure, and lower the head of the bed. The anesthesia team can support with 100% oxygen and, in severe cases, aspiration through a central line. But preventing the injury in the first place is far preferable. Chyle leak is another complication that is easily underestimated. The thoracic duct, or its right-sided equivalent, can be injured during a left-sided neck dissection, particularly in level IV and level V dissections. The leak is often not obvious intraoperatively because the patient is under anesthesia and the pressure in the thoracic duct is low. The typical presentation is milky drainage from the wound on postoperative day two or three, especially after the patient starts eating. The standard management is conservative — pressure dressing, low-fat diet with medium-chain triglycerides, and octreotide. If that fails, surgical ligation or embolization is necessary. I've had one case where the conservative approach worked but it took six weeks of nearly nothing by mouth before the leak sealed. That patient was miserable.
The Lymph Node Classification System
The American Joint Committee on Cancer (AJCC) staging system for head and neck cancers uses the number, size, and laterality of involved lymph nodes to determine N stage. This is critical for prognosis and treatment planning. A single ipsilateral node less than three centimeters is N1. Two or more ipsilateral nodes less than six centimeters is N2b. Extranodal extension changes everything — it automatically upstages the disease regardless of node size or number. When you're doing the dissection, you need to collect at least twelve lymph nodes for adequate staging in most head and neck cancers. Fewer than that and you're potentially understaging the disease. I recently reviewed a pathology report where only seven nodes were retrieved from a neck dissection specimen. The attending pathologist flagged it as inadequate, and the oncology team recommended additional treatment despite what would have otherwise been a low-stage presentation. The lesson here is that the dissection isn't finished until the pathology report confirms adequate nodal yield. You can't assume you got everything just because the neck looks clean.
Lymphatic Mapping And Sentinel Nodes
The concept of a sentinel lymph node in head and neck cancer is still evolving. In melanoma and breast cancer, the sentinel node procedure is standard. In head and neck squamous cell carcinoma, it's more controversial. The lymphatic drainage patterns in the head and neck are complex and frequently skip-level, meaning a primary tumor in level II might drain directly to level IV, bypassing level III entirely. This makes the concept of a single sentinel node unreliable in most cases. That said, isotope-guided lymphatic mapping has shown promise in select cases, particularly for oral cavity cancers where the drainage is more predictable. I've used Technetium-99m sulfur colloid injected perioperatively around the primary tumor site to identify the draining node. It works about sixty to seventy percent of the time in my experience, and when it fails, it fails because the lymphatics are blocked by tumor or prior radiation. In those cases, you fall back to the modified radical neck dissection and hope for the best.
Postoperative Considerations
Shoulder dysfunction after neck dissection is incredibly common and often overlooked. The spinal accessory nerve controls the trapezius muscle, and even when the nerve is preserved, it can be neuropraxic from retraction or thermal injury. The result is shoulder pain, weakness, and restricted range of motion in up to fifty percent of patients. Early physical therapy is essential. I usually refer patients to physical therapy within the first postoperative week, focusing on gentle range-of-motion exercises. Waiting longer makes recovery significantly harder. Sensory changes from the great auricular nerve are almost universal. The nerve is frequently sacrificed during neck dissection, and the resulting numbness over the parotid region and ear is permanent. Patients sometimes find this more distressing than the shoulder issues because it affects sleep — lying on the numb side can feel strange, and some patients develop headaches from the altered sensation. Reassurance and time help, but the numbness doesn't go away. Jugular vein ligation is sometimes necessary when the vein is encased by tumor. The consequence depends largely on collateral circulation. Most patients tolerate unilateral IJ ligation without issue. Bilateral ligation is a different story — it can cause cerebral edema and increased intracranial pressure. If you're facing a bilateral dissection and both veins need to be sacrificed, you need a conversation with the anesthesia team about monitoring intracranial pressure and managing fluid balance carefully.