Understanding What Lies Behind Your Ribs and Lower Spine
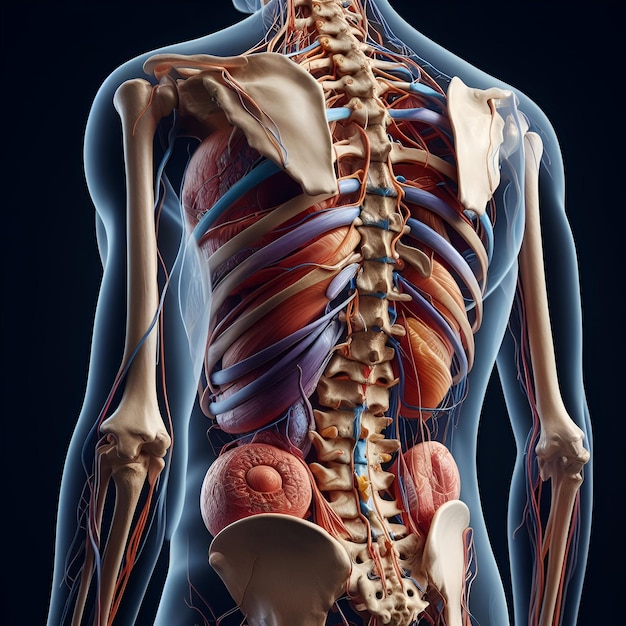
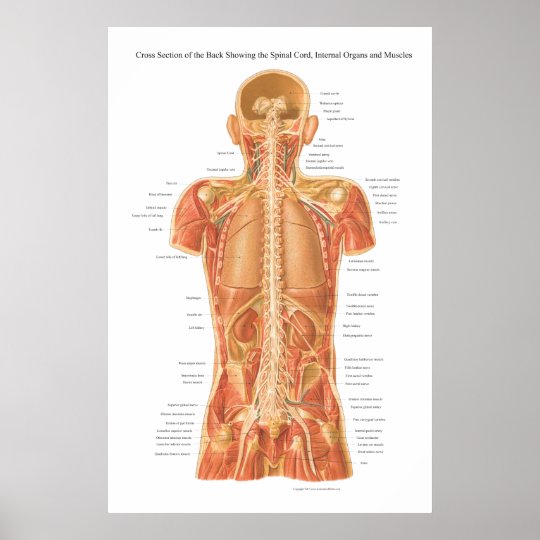
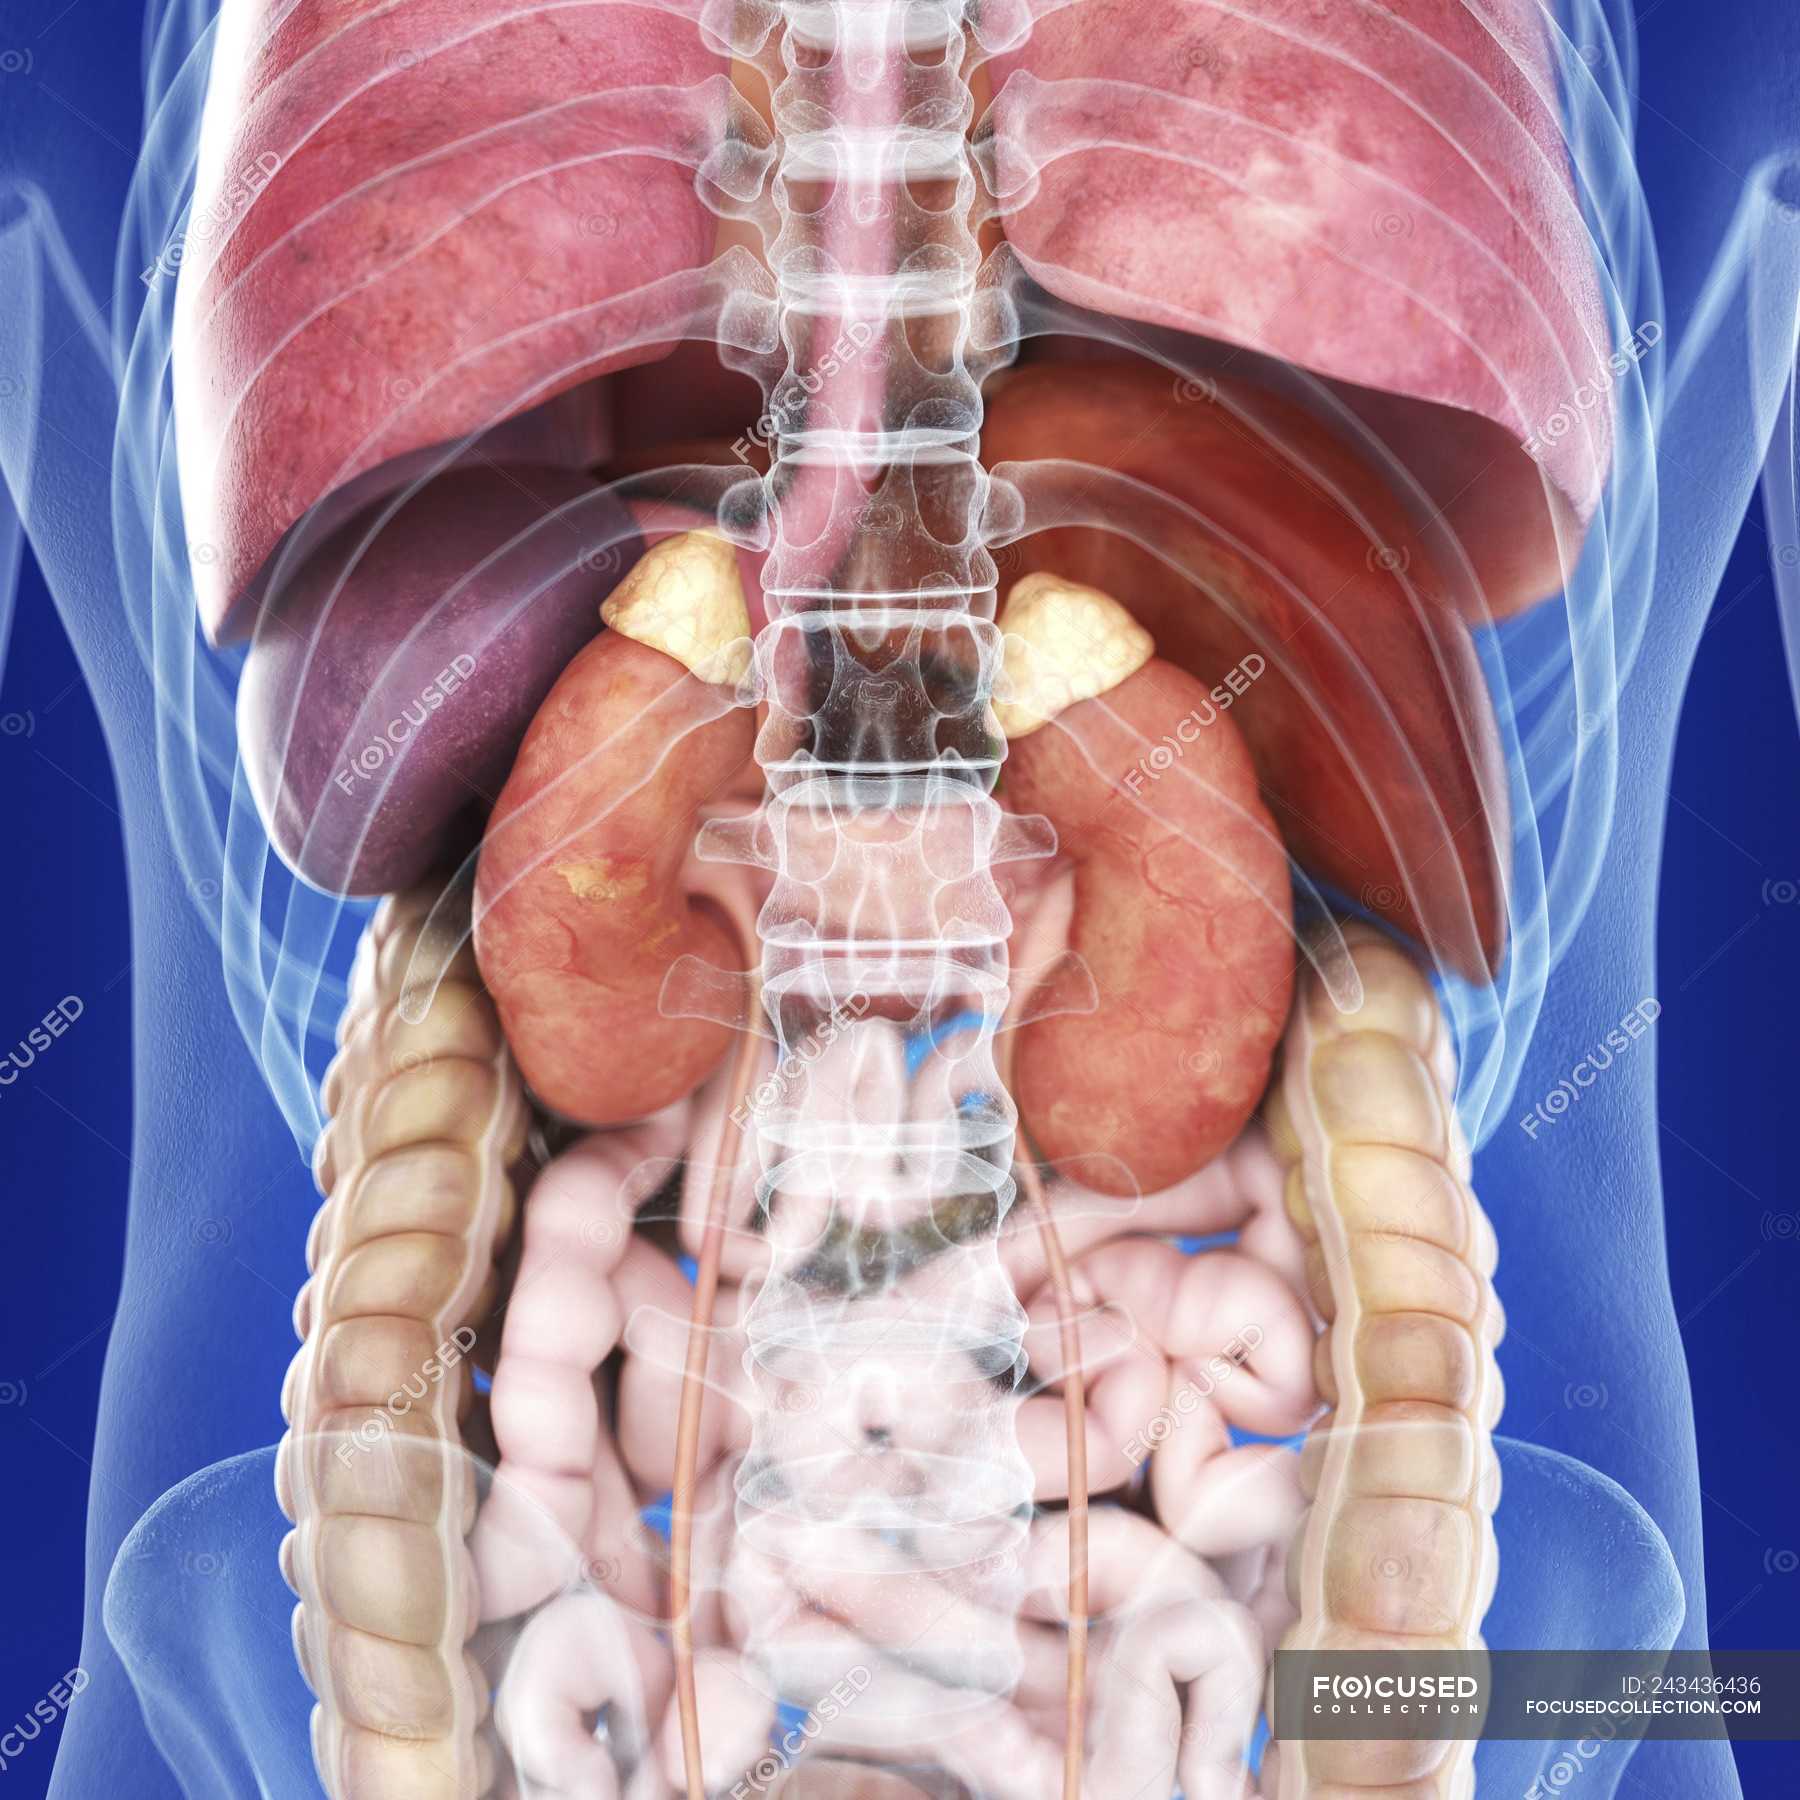
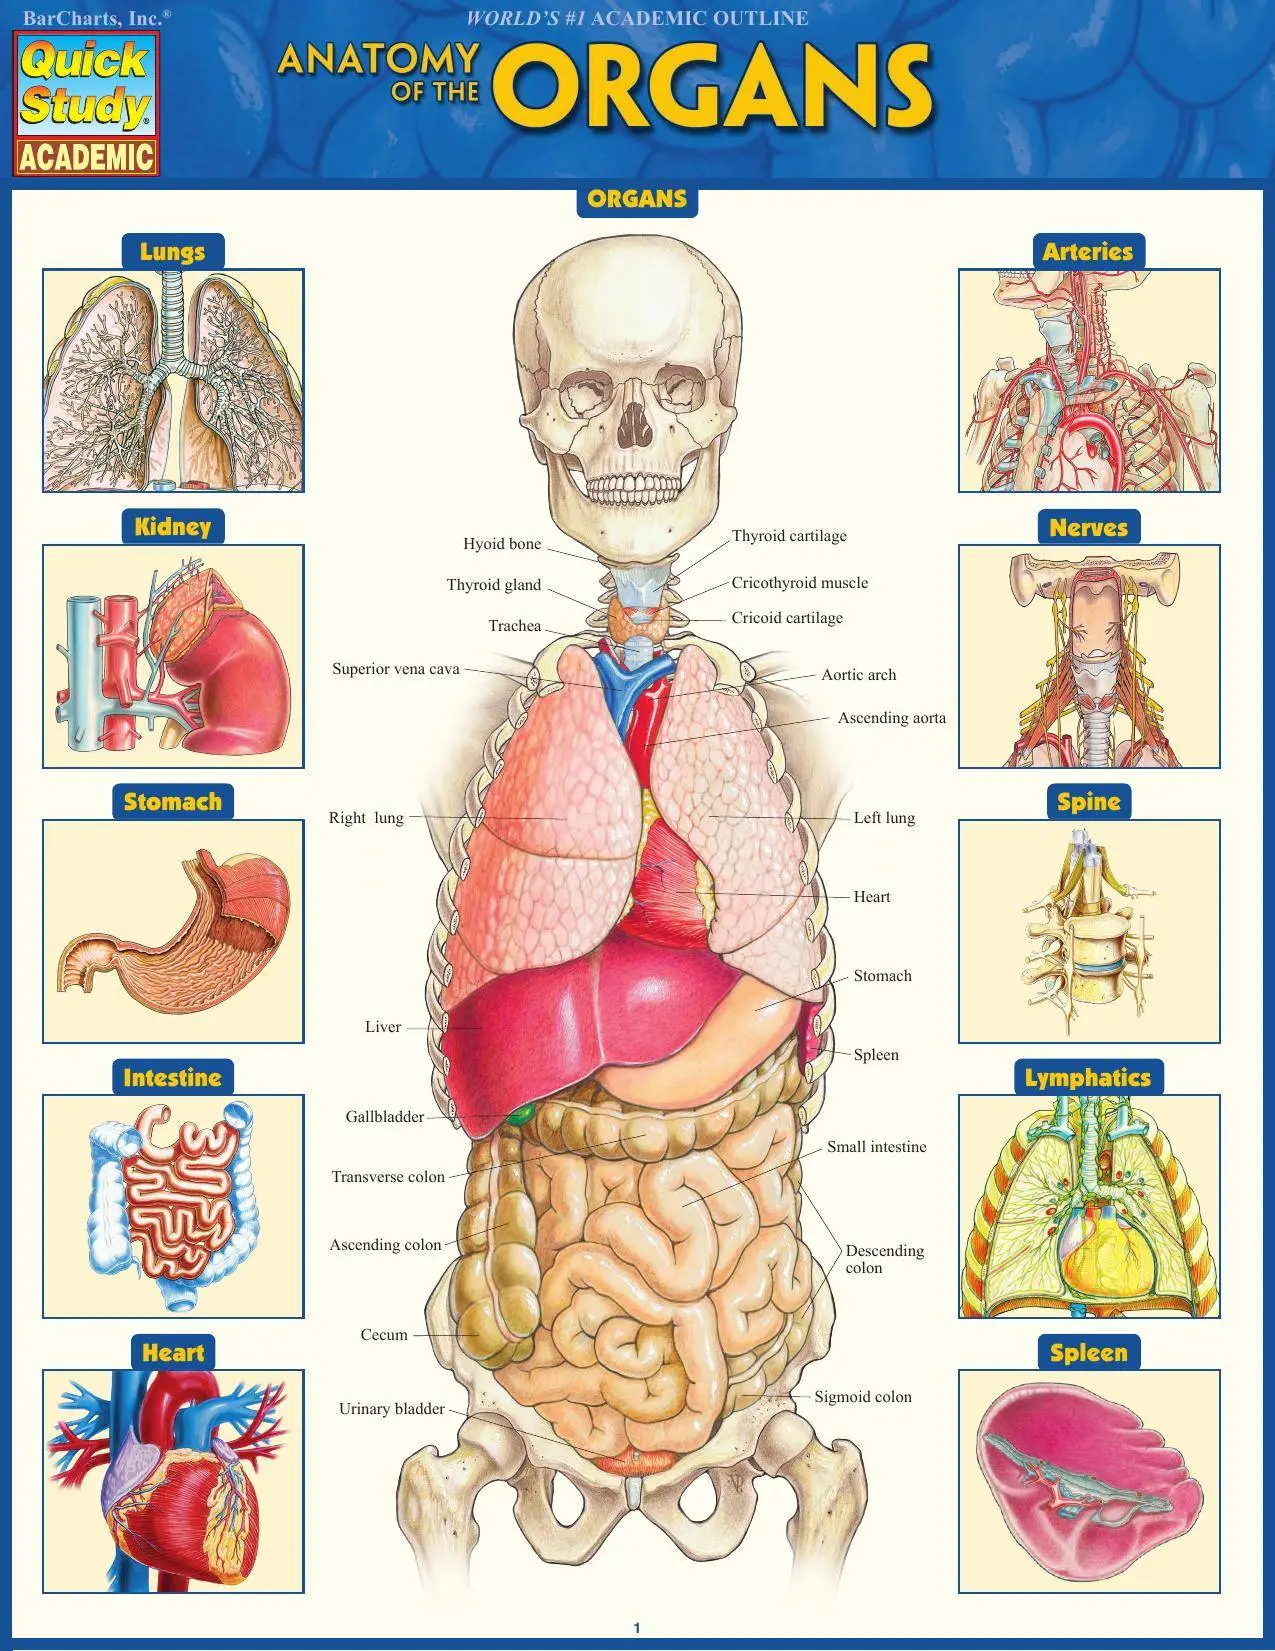
The back isn't just muscle and bone. It houses several vital organs, and knowing how they're arranged matters if you're studying anatomy, working in healthcare, or just trying to understand why pain in a specific area points to a specific problem. I've spent years reading cadavers and consulting radiology reports, and the anatomy here is more layered than most people realize. When people think about back anatomy, they immediately picture the erector spinae, the trapezius, maybe the latissimus dorsi. Those are surface-level structures. The organs sitting posteriorly or partially posteriorly in the torso are where things get interesting. The kidneys are the main ones, and they sit retroperitoneally, meaning behind the peritoneum that lines the abdominal cavity. They're not floating in the middle of your abdomen like your stomach or intestines. They're pressed up against the posterior abdominal wall, which is why kidney pain often refers to the back rather than the front. The right kidney sits slightly lower than the left because the liver occupies space above it. Both kidneys rest around the T12 to L3 vertebral level. The left kidney tends to sit a bit higher, near the 12th rib, which is relevant if you're palpating from the back or doing a posterior approach for a procedure. That 12th rib relationship is something I wish more students understood before they tried to locate the kidneys by touch.
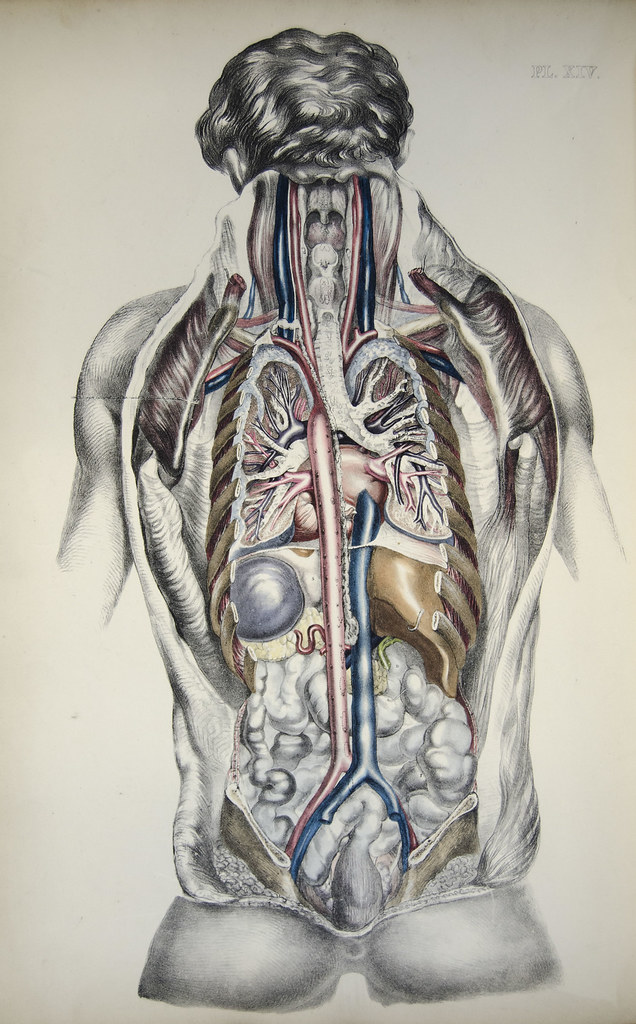
Beyond the kidneys, the pancreas has a retroperitoneal position too, except for its tail which dips into the peritoneal cavity. The head of the pancreas nests in the C-loop of the duodenum, and the body and tail extend toward the splenic hilum. It sits anterior to the spine but still counts as a posterior organ in most clinical classifications. The adrenal glands cap each kidney, sitting in their own perirenal fat capsule, and they're small but clinically massive when they malfunction. The aorta runs along the anterior aspect of the vertebral column, slightly to the left of midline. It passes through the diaphragm at the T12 level and gives off several branches before bifurcating around L4. The inferior vena cava sits to the right of the aorta and also crosses the diaphragm near T8. These major vessels are easily injured in penetrating trauma to the back, and their retroperitoneal location means bleeding from them can sequester a large volume of blood without obvious external signs.
Why Posterior Organ Anatomy Matters in Practice
I once had a patient who came in with what they described as a muscular backache after moving furniture. Standard presentation, right? Wrong. The pain was located more laterally than typical muscle strain, around the costovertebral angle on the left side. The kidneys weren't the first thing on my differential for back pain, but the radiation pattern and the specific tenderness there pointed toward a possible renal issue. An ultrasound confirmed a left renal calculus, and the pain had been referring posteriorly through the T10-L1 dermatomes. This is exactly the kind of case where knowing retroperitoneal anatomy saves you from misdiagnosing something serious as a simple muscle pull. Another practical angle: posterior approaches to these organs. A flank incision for nephrectomy takes a different route than an anterior abdominal approach, and the layers you traverse are not the same. You go through skin, subcutaneous tissue, the external oblique, internal oblique, and transversus abdominis in a different sequence than an anterior incision. The neurovascular bundles run between the muscle layers, and damaging them causes postoperative numbness or weakness that patients notice more than they'd like to admit. I've seen surgeons who skip detailed rehearsal of these posterior approaches and pay for it later. The spleen is another organ that relates to the posterior left back, though it's more lateral and superior. It sits against the 9th, 10th, and 11th ribs on the left side. Rib fractures in that area can lacerate the spleen, and the bleeding goes into the peritoneal cavity, but the pain often presents in the left shoulder via the phrenic nerve (Kehr's sign). This referred pain pattern is a classic anatomy trap. Students remember the sign but sometimes miss the underlying mechanism, which is irritation of the diaphragmatic peritoneum transmitting pain through C3-C5 nerve roots.
Get the Full Details
Common Misunderstandings About Posterior Organ Anatomy
One persistent misconception is that the lungs sit entirely in the chest and have nothing to do with the back. The posterior costophrenic recesses extend quite low, especially on the right side, and pleural effusions often collect there first because gravity pulls fluid to the most dependent portion when a patient is upright. A lateral decubitus X-ray can reveal effusions that a standard PA view misses entirely. I've read reports where radiologists called a chest X-ray "clear" and missed a small but clinically significant effusion simply because the patient was upright and the fluid settled posteriorly. Another thing people get wrong is assuming the liver is purely an anterior organ. The right lobe of the liver extends posteriorly to about the T10 level, pressing against the right kidney and the right hemidiaphragm. This posterior extension is why hepatomegaly can cause right-sided back pain, and it's also why liver biopsies are sometimes performed through a posterior intercostal approach rather than anterior. The posterior route avoids the intercostal neurovascular bundle running along the inferior margin of each rib, which reduces the risk of bleeding and nerve damage. The gallbladder sits on the visceral surface of the liver, but its fundus can project posteriorly in certain body habitus types. In thin individuals with a long, mobile gallbladder, the fundus can reach far enough back to cause pain that mimics renal or spinal pathology. This is rare but well-documented, and I've encountered at least two cases where the wrong organ was implicated before imaging clarified the source.
Palpation and Clinical Examination of Posterior Organs
Bimanual palpation is the standard technique for examining the kidneys from the front, but posterior palpation is equally valid and sometimes more effective. With the patient prone or in a side-lying position, you place one hand below the costal margin and the other on the back over the flank. The posterior hand lifts the kidney forward while the anterior hand presses down, attempting to catch the kidney between the two palms. A normal kidney is rarely palpable this way, but an enlarged or ptotic kidney can be felt easily. Costovertebral angle tenderness is the bedside test for renal pathology. You fist the patient's back sharply over the area where the 12th rib meets the vertebral column. Pain here suggests pyelonephritis or nephrolithiasis. It's a crude test with moderate sensitivity, but it's fast and requires no equipment. I've found that combining it with percussion tenderness mapping — tapping gently along the paraspinal muscles and noting where tenderness localizes — helps distinguish renal pain from muscular pain. Muscular tenderness tends to be more superficial and diffuse; renal tenderness is deeper and more focal. For the pancreas, posterior palpation is much less reliable. The pancreas lies deep and is usually impossible to feel unless it's significantly enlarged or mass-forming. CT and MRI are the practical tools here, not your hands. Same goes for the aorta. You can palpate the abdominal aorta from the front, but posterior palpation is limited by the vertebral column itself. What you can assess from the back is the paraspinal region for masses that might involve retroperitoneal lymph nodes or tumor extensions.
Imaging Considerations for Posterior Structures
CT scans are the workhorse for evaluating retroperitoneal organs, and the posterior approach to interpretation is often overlooked. Axial slices show the relationship between organs and the vertebral column clearly, but coronal and sagittal reconstructions are essential for understanding the vertical extent of pathology. A mass that looks small on axial views can span multiple vertebral levels in the coronal plane, which changes surgical planning dramatically. MRI provides better soft tissue contrast for posterior organ evaluation, particularly for adrenal masses and pancreatic lesions. The T2-weighted images show fluid-filled structures like the renal collecting system with high clarity, and contrast-enhanced sequences delineate vascular anatomy that CT sometimes obscures in patients with calcified vessels. I prefer MRI for adrenal workups because the chemical shift imaging can characterize adenomas without biopsy in most cases, which spares patients an invasive procedure. Ultrasound from a posterior approach is useful for renal assessment and can detect hydronephrosis, cysts, and solid masses. The advantage is that it's dynamic — you can watch peristalsis in the ureters and assess blood flow with Doppler. The limitation is body habitus. In patients with significant subcutaneous fat or bowel gas, posterior renal ultrasound quality drops substantially, and you'll need CT to fill the gaps.
Surgical and Procedural Implications
Posterior surgical access changes everything about how you approach these organs. Laparoscopic adrenalectomy through a posterior transperitoneal route takes about 90 minutes on average and involves less postoperative pain than the anterior approach because you're not disturbing the peritoneal cavity and its contents. The learning curve is steeper though. The landmarks are different, and there's less room for error when you're working between the kidney and the diaphragm. Open posterior nephrectomy requires mobilizing the kidney from its retroperitoneal position, which means dividing the lateral peritoneal reflection and carefully identifying the ureter before clamping the renal vessels. The renal artery is posterior to the renal vein in most anatomical variations, but about 15 percent of patients have an anteriorly positioned artery or an accessory vessel that can be easily damaged if you're not anticipating it. I've seen accessory renal arteries injured during laparoscopic procedures because the surgeon was following the standard textbook anatomy and didn't account for the variation. Vertebroplasty and kyphoplasty for spinal fractures are posterior approaches that interact with the same anatomical territory. The pedicles provide the entry point, and the cement tracks into the vertebral body. Complication here includes cement leakage into the epidural space or the retroperitoneum, which can compress the adjacent organs or nerves. Fluoroscopic guidance reduces this risk but doesn't eliminate it, and the operator needs to understand exactly how much cement can be injected before pressure forces extrusion.
What Most Sources Don't Tell You
The lymphatic drainage of retroperitoneal organs follows the blood supply back to the para-aortic and paracaval lymph nodes. This matters for staging malignancies. Renal cell carcinoma spreads to the ipsilateral para-aortic nodes first, while the right kidney can also drain to the paracaval nodes. Understanding this pathway determines whether you're doing a targeted lymph node dissection or a more extensive one during cancer surgery. Most introductory anatomy texts mention the drainage pattern but don't emphasize the surgical consequence, which is a gap I've noticed repeatedly in residents who know the anatomy but not its clinical application. The innervation of these posterior organs is another area where shortcuts lead to mistakes. The kidneys receive sympathetic input from T10-L1, which is why renal colic pain follows that dermatomal distribution. But the parasympathetic supply comes through the vagus nerve and the pelvic splanchnic nerves, and these don't contribute to pain sensation. Visceral pain from the kidneys is carried by sympathetic afferents that travel alongside the blood vessels back to the spinal cord. This is why cutting the sympathetic chain can relieve certain types of chronic renal pain, and it's also why renal denervation procedures are being explored for hypertension management. Finally, the relationship between the posterior organs and the spine is worth understanding beyond simple proximity. The psoas major muscle originates from the transverse processes and vertebral bodies of T12 through L5, and it passes posterior to the kidneys and great vessels. A psoas abscess can present as back pain with hip flexion limitation, and it often originates from tuberculosis or spread from adjacent spinal infections like Pott's disease. I once evaluated a patient with chronic lower back pain and fever who turned out to have a psoas abscess secondary to spinal TB. The kidney ultrasound was normal, and the initial focus on renal pathology delayed the correct diagnosis by several days. The lesson was straightforward: not all posterior back pain with systemic symptoms is renal, and the psoas deserves attention in the differential.