What You Actually Need to Know Before Looking at This
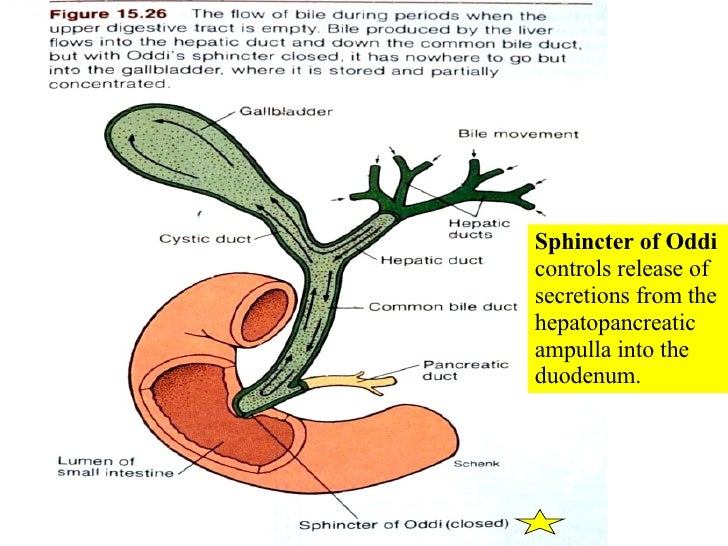
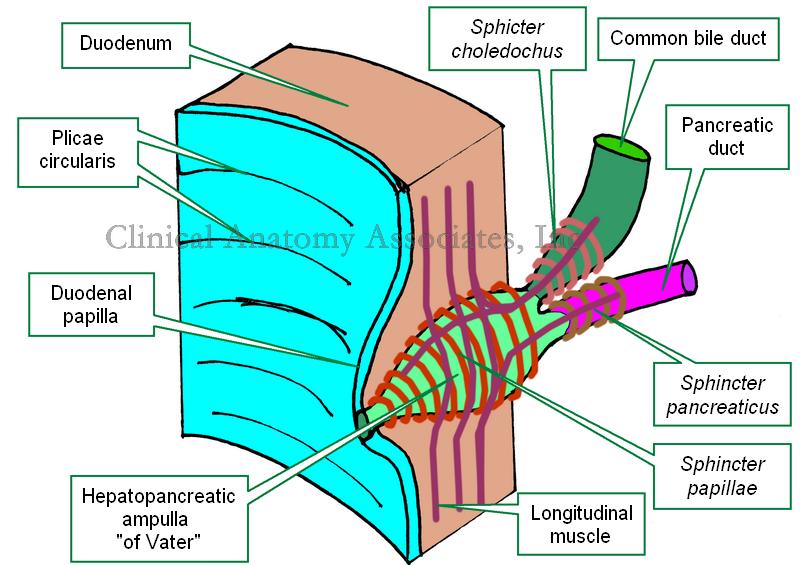
The sphincter of Oddi is not some singular muscle ring you can just point to and say "there it is." It is a composite of three distinct muscular components that together regulate flow from the common bile duct and pancreatic duct into the duodenum. If you are studying this for surgery, endoscopy, or radiology, you need to understand how those three parts interact under real conditions, not just what a diagram shows. I have spent years reviewing cholangiograms and ERCPs, and the first thing I notice is how often people miss the functional anatomy because they are too focused on the static structure. The sphincter of Oddi actually consists of three functionally distinct portions: the choledochal sphincter around the common bile duct, the pancreateicus sphincter around the pancreatic duct, and the common or terminal sphincter at the ampulla. These do not fire as one unit. That separation matters enormously when you are trying to understand biliary or pancreatic pathology. The choledochal component is the outermost layer. It sits at the distal common bile duct and is responsible for the majority of the basal pressure that keeps bile flowing in the right direction. In healthy adults, resting pressure in this zone sits roughly between 10 and 40 mmHg. That range varies with respiration, phase of digestion, and hormonal state. The pancreateicus portion wraps around the main pancreatic duct. It tends to have slightly lower baseline pressure, usually 8 to 32 mmHg, and its behavior is heavily modulated by secretin and CCK. Then there is the common terminal segment where the two ducts may join before entering the duodenum. Some people have a true ampulla of Vater with a shared terminal channel. Others do not. Anatomical variation here is far more common than most textbooks suggest.
One thing that consistently trips up residents and even attending physicians is assuming that manometry readings from one zone apply to the others. They do not. When I performed sphincter of Oddi manometry during ERCP procedures, I found that pressures measured in the choledochal zone could be completely discordant with what was happening in the pancreateicus zone. A patient might present with typical biliary pain and abnormal liver enzymes, look like a textbook case of sphincter of Oddi dysfunction on imaging, and then the manometry data tells a different story entirely. The dysfunction might be isolated to the pancreatic sphincter while the biliary portion is perfectly normal. I ran into a specific case where a patient had recurrent episodes of pancreatitis and abdominal pain. MRCP showed a mild dilated pancreatic duct. The working diagnosis was sphincter of Oddi dysfunction of the biliary type, so the team was preparing for a biliary sphincterotomy. But during diagnostic manometry, the biliary pressures were completely unremarkable. The pancreatic sphincter pressure, however, was elevated at 65 mmHg with abnormal phasic activity. We redirected the intervention. A pancreateicus sphincterotomy resolved the symptoms. If we had followed the initial assumption based on imaging alone, the procedure would have missed the actual problem and potentially caused unnecessary complications. The blood supply to this region comes primarily from the pancreaticoduodenal arteries, which form an anastomotic network between the superior mesenteric and celiac systems. Lymphatic drainage goes to the peripancreatic and portal nodes. The innervation involves both parasympathetic input from the vagus nerve and sympathetic fibers from the celiac plexus. This autonomic control is what mediates the relaxant response to cholecystokinin during a meal. When CCK is released from I cells in the duodenal mucosa, it acts on CCK1 receptors on the sphincter smooth muscle to cause relaxation. That is the physiological mechanism, but in practice it is more complicated because gastrin and secretin also modulate sphincter tone, and their effects are not always predictable.
There is a counter-intuitive finding that many clinicians overlook. Bile reflux into the pancreatic duct does not always require a structurally incompetent sphincter. Even with normal sphincter pressures, a significant pressure gradient between the bile duct and pancreatic duct at rest can drive bile retrograde into the pancreatic duct. This is particularly relevant in patients who have had a prior cholecystectomy. Without the gallbladder reservoir, bile flows continuously into the duodenum, and the pressure dynamics around the sphincter change. I have seen cases where post-cholecystectomy patients developed biliary-type pain that was not due to sphincter spasm at all. It was the altered flow pattern and pressure gradient causing micro-reflux and irritation. Manometry can help distinguish this, but you have to know to look for it. The histological structure is worth noting because it explains a lot about clinical behavior. The sphincter is composed of smooth muscle arranged in concentric and longitudinal layers. The innermost circular layer is the thickest and generates the tonically active contraction. There are no striated muscle fibers in the sphincter itself, only smooth muscle. The myenteric plexus of Auerbach runs adjacent to but not within the sphincter muscle bundles, which is why neuromodulators have such a variable effect on sphincter tone. Opioids, for example, cause contraction of the sphincter of Oddi through direct smooth muscle effects and through central nervous system pathways. This is why morphine and meperidine have different effects on sphincter pressure, and why this matters when you are managing acute abdominal pain in patients with known biliary disease. One practical limitation that everyone in this field needs to accept is that non-invasive imaging simply cannot assess sphincter function. MRCP shows anatomy. Endoscopic ultrasound shows anatomy. CT shows anatomy. None of them tell you whether the sphincter is dyskinetic or hypertensive. You need manometry for that, and manometry requires ERCP, which carries its own risks. The procedure-related pancreatitis rate after diagnostic manometry is somewhere around 5 to 10 percent, and it goes up significantly if you are also performing a sphincterotomy. This tradeoff means that manometry should not be used as a first-line test. It is reserved for cases where the diagnosis remains unclear after initial workup and where the result would change management.
Get the Full Details

If you are evaluating a patient with suspected sphincter of Oddi dysfunction, the current approach is more conservative than it used to be. The Rome IV criteria and subsequent guidelines have pushed the field away from aggressive manometry and sphincterotomy. The base rate of finding true manometric abnormalities in these patients is lower than historical series suggested, and many patients improve with medical management alone. I usually start with optimizing opioid use if the patient is on them, adding calcium channel blockers or nitrates for spasm, and considering tricyclic antidepressants for functional pain components. Intervention comes later, only after conservative measures fail and manometry confirms a clear abnormality in the relevant zone.