How Dental Tooth Numbering Actually Works In Practice
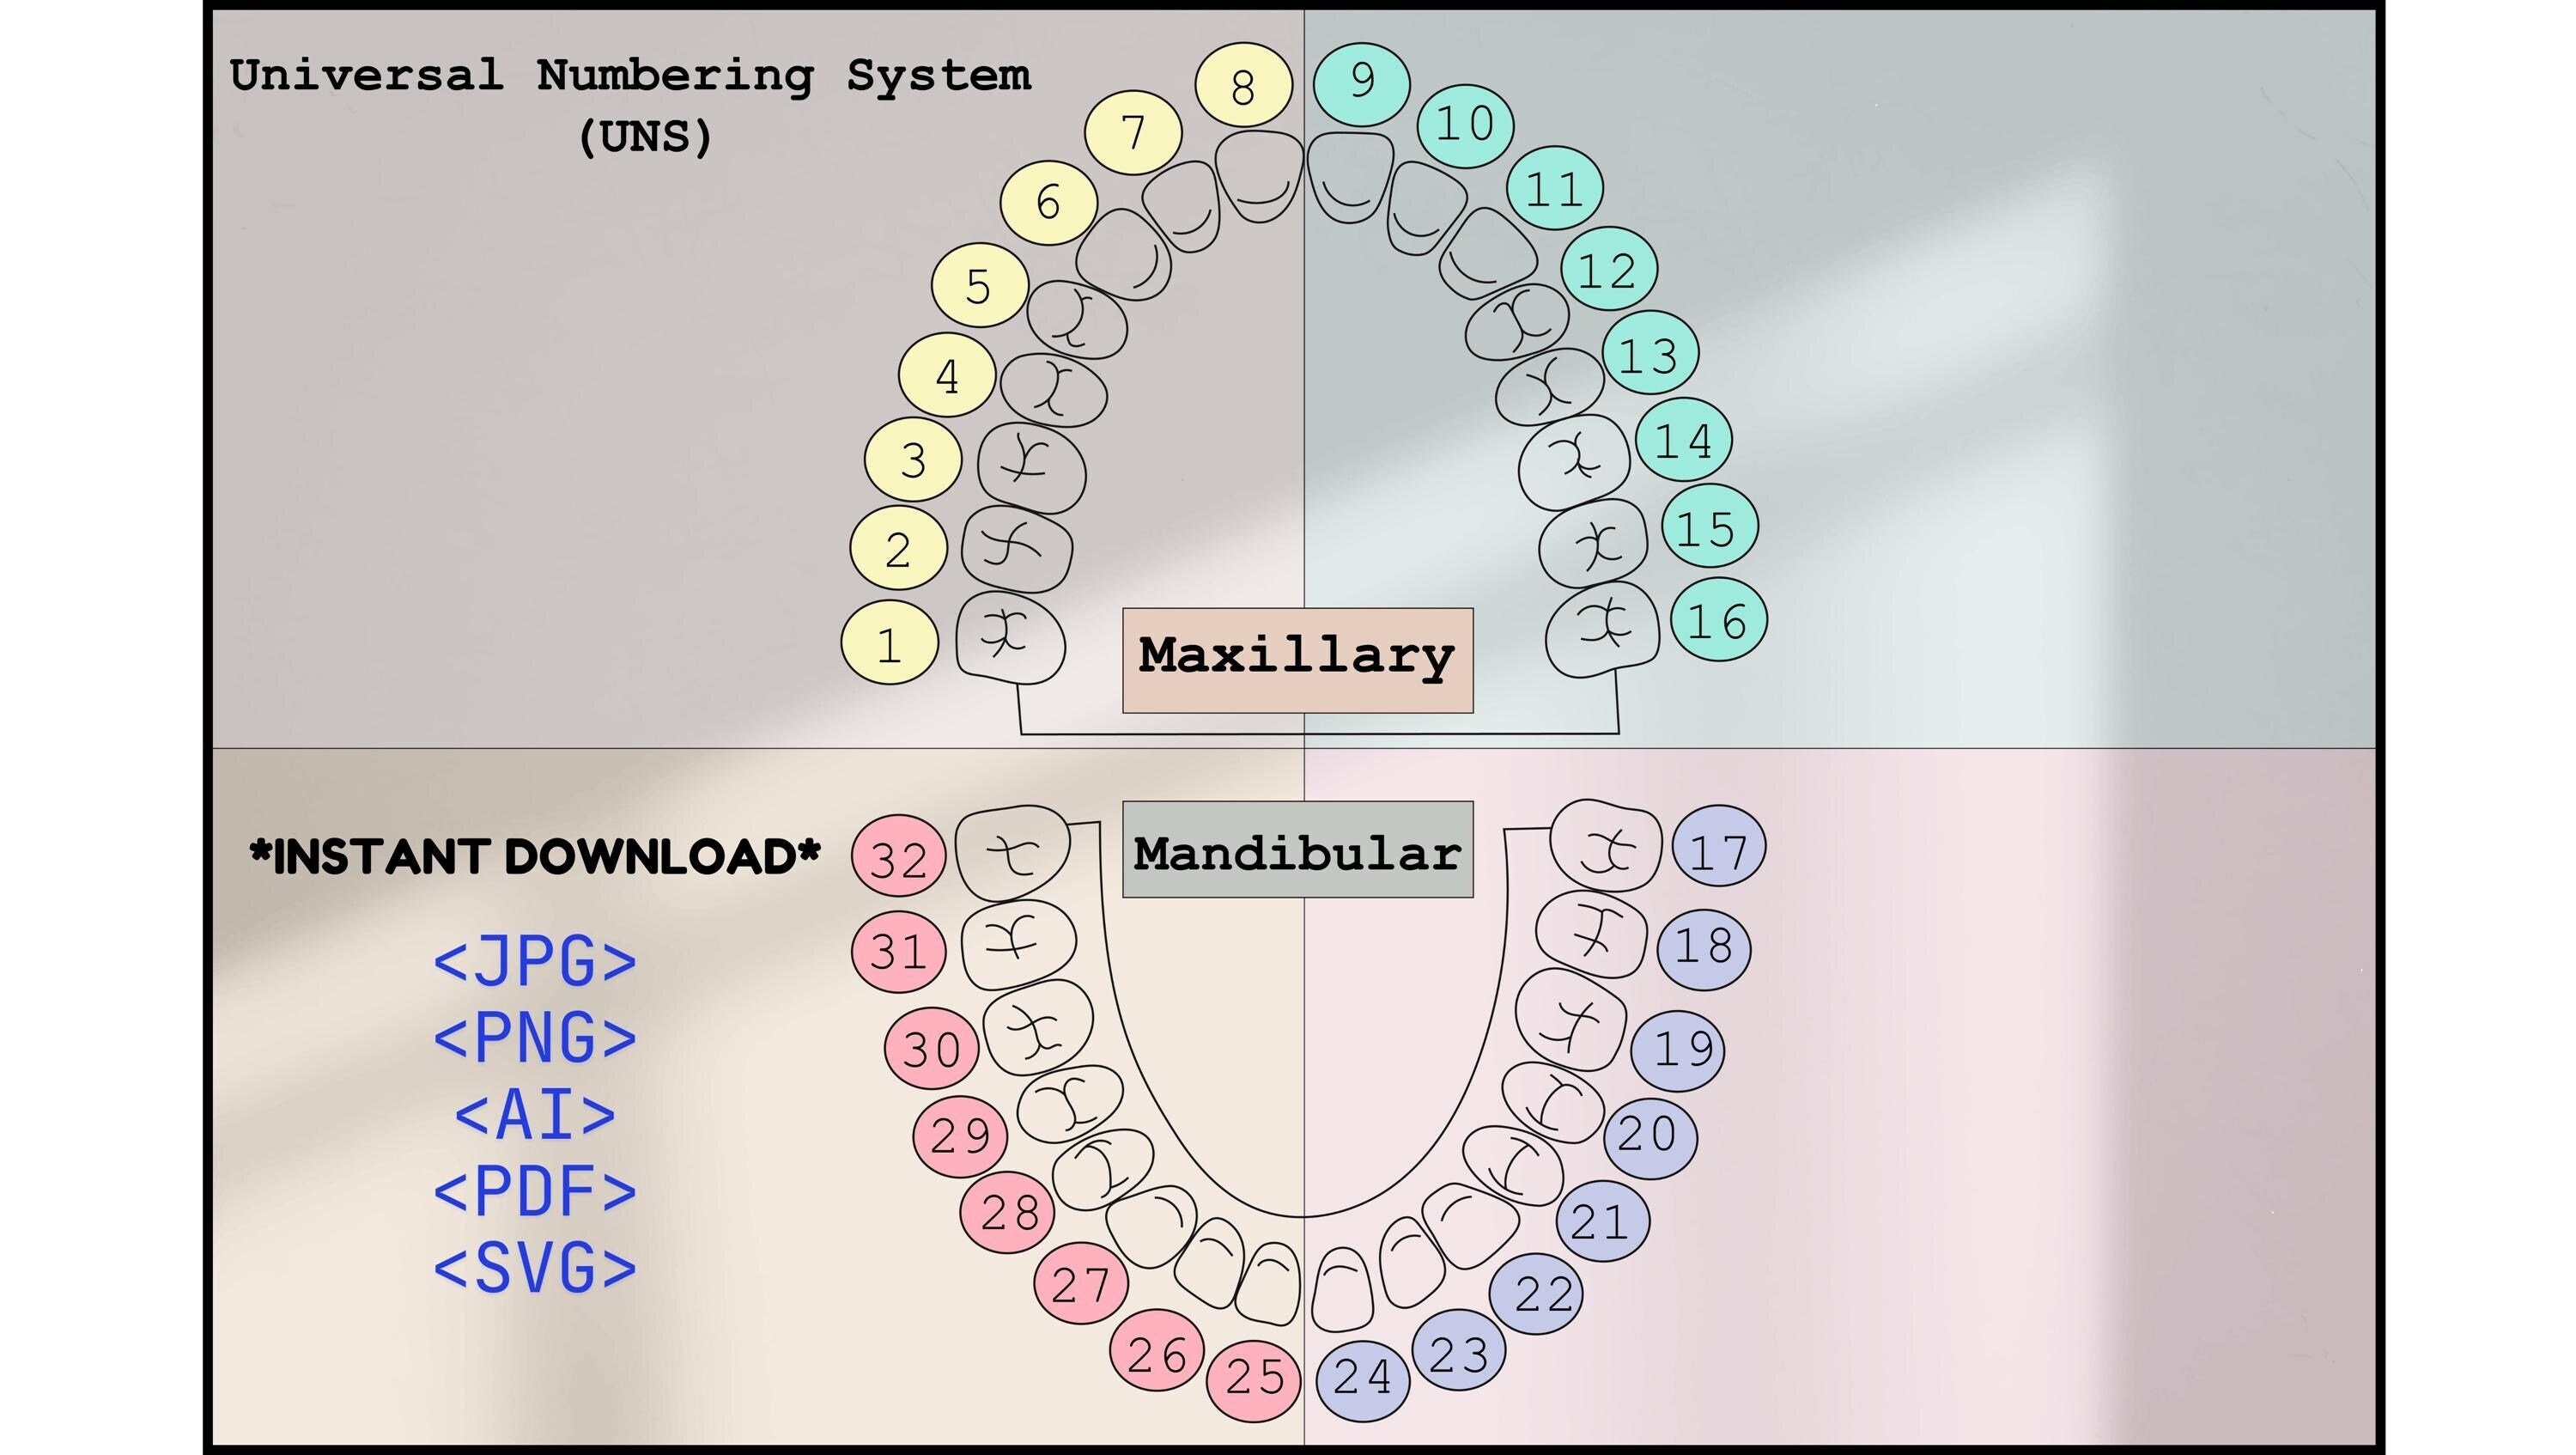
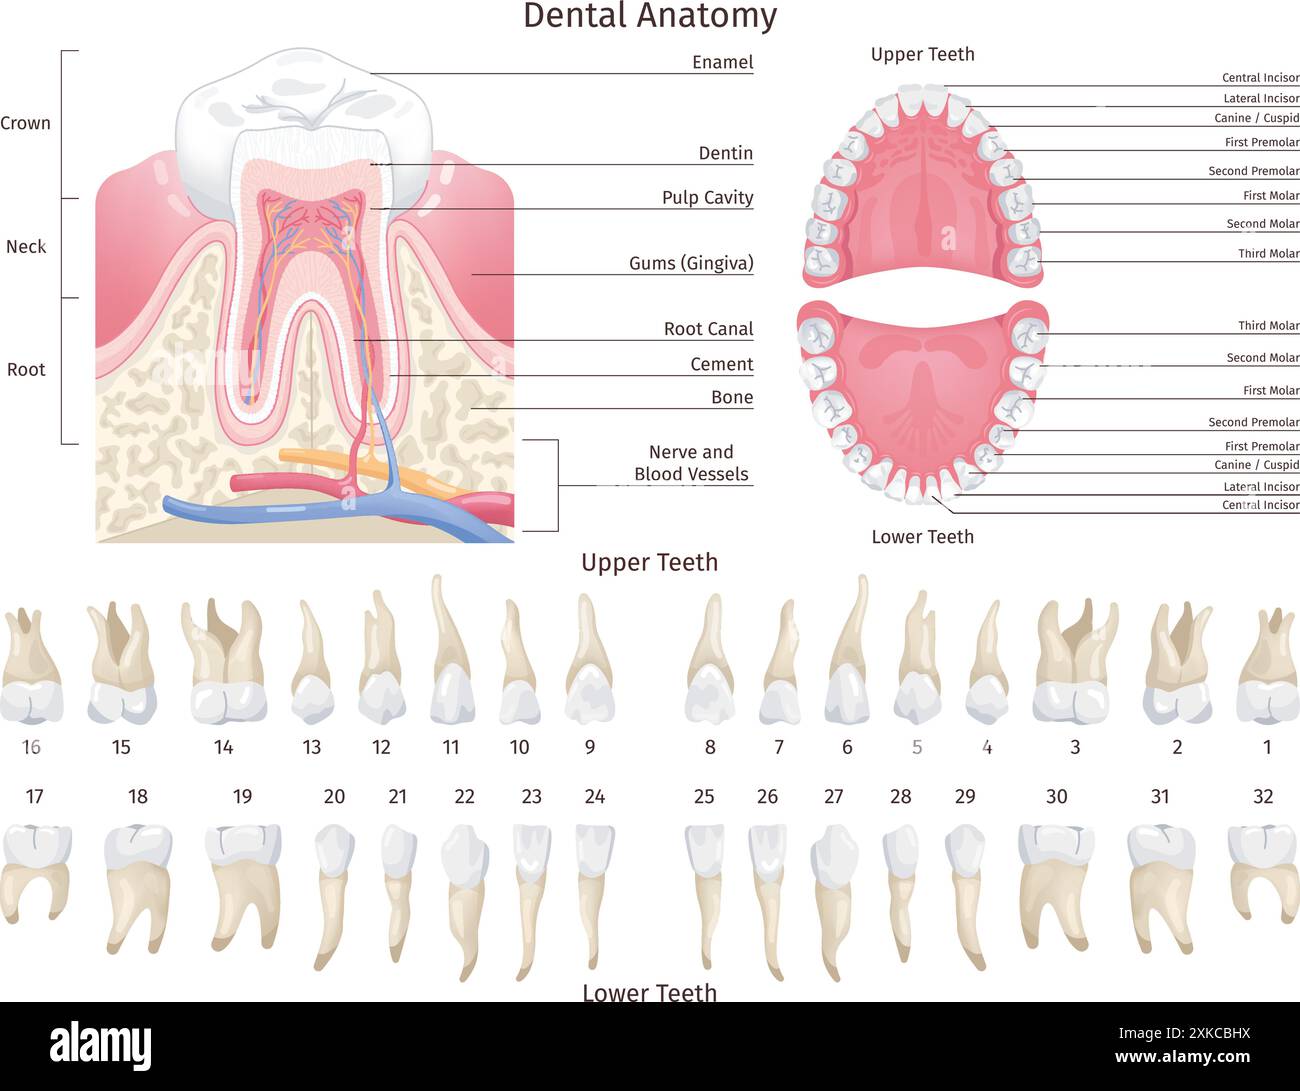
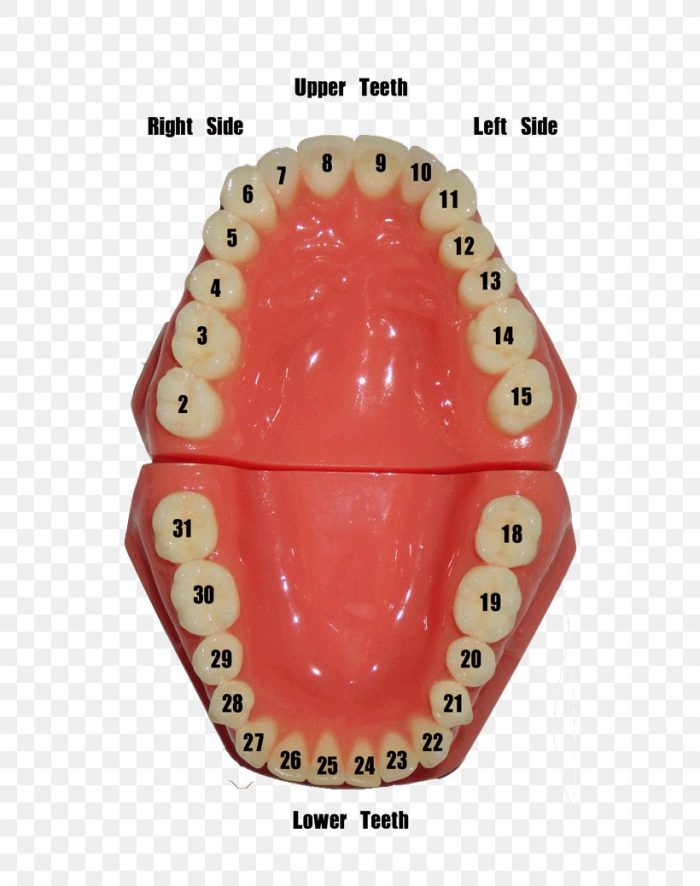
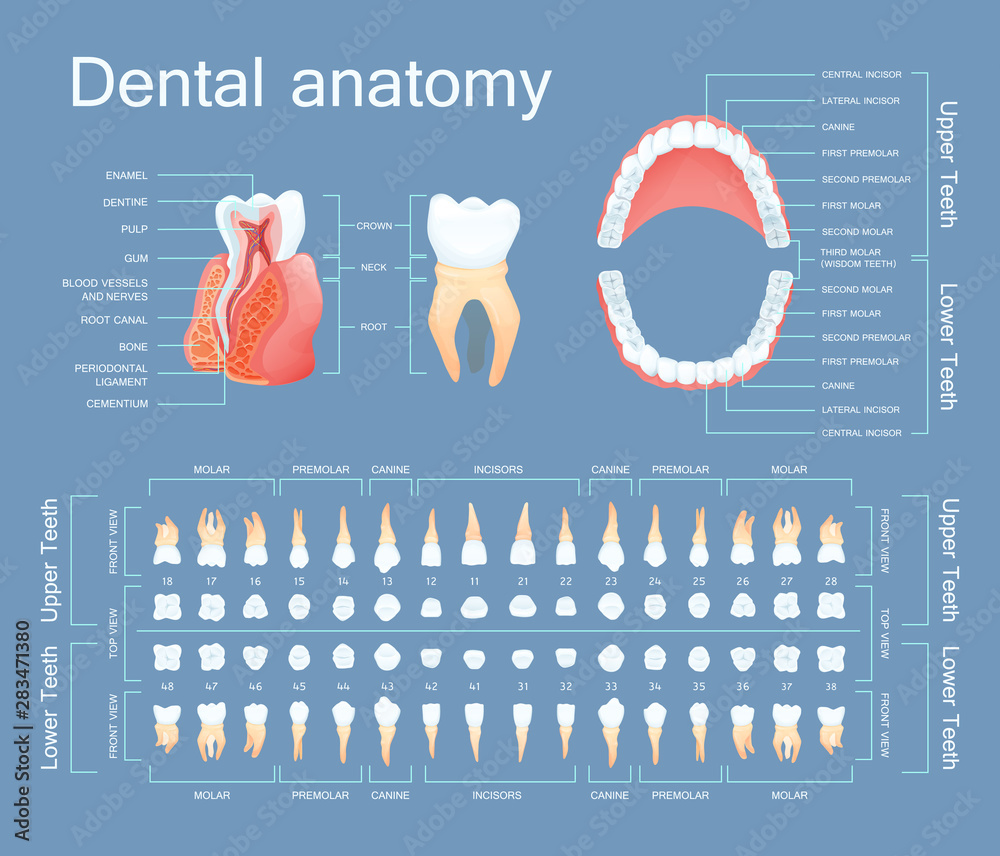
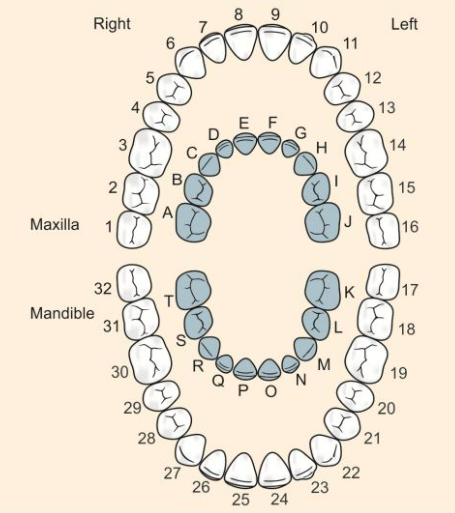
Dentists number teeth to save time and avoid confusion when discussing treatment plans with specialists, labs, or insurance companies. There are three main systems in use, and if you're not careful you'll mix them up at the worst possible moment. The universal system, which is what you'll see on the majority of American dental charts, numbers permanent teeth from 1 through 32 starting at the upper right back and going clockwise around to the upper left back. Deciduous teeth use letters A through T. The FDI system uses two digits where the first digit indicates the quadrant and the second digit indicates the tooth position within that quadrant. Quadrant 1 is the upper right, quadrant 2 is the upper left, quadrant 3 is the lower left, and quadrant 4 is the lower right for permanent teeth. Primary teeth use quadrants 5 through 8 instead. The reason this matters in day-to-day practice is that a misnumbered tooth can send a restoration to the wrong site. I once had a lab crown up a tooth 14 when the prescription said tooth 41. The clinician had written the FDI number on a Universal-charted prescription, and the ceramist followed the number literally. It took three weeks, an additional charge, and an awkward phone call to sort out. Since then I make sure both systems are noted on every referral I send, even though it adds about thirty seconds to the paperwork. Understanding tooth anatomy alongside the numbering system is what makes charting actually useful. The maxillary central incisor has a single broad root and a central ridge on the lingual surface that you can feel when exploring the cingulum. The maxillary first molar typically has three roots spread in a triangular pattern, and its occlusal surface carries four major cusps with a distinct oblique ridge running between the mesiolingual and distobuccal cusps. The mandibular first premolar often has a bifurcated root, which is relevant when you're considering extraction versus endodontic treatment. These anatomical details matter because they influence access cavity design, root canal configuration, and how crowns or bridges load under function.
Here is something beginners consistently miss: the numbering tells you position, but it does not tell you orientation. Tooth 3 is a maxillary canine with a prominent cusp and a long single root. Tooth 12 is also a canine but on the opposite side, and while it looks similar on paper the mirror-image anatomy affects how you prepare the tooth and how you section a block for CAD CAM machining. The same issue applies to premolars. The first premolar has a different crown outline and root trunk length than the second premolar, and on the mandibular arch the first premolar is uniquely concave on both the buccal and lingual aspects of the root, which changes how you approach periodontal probing and surgical access. If you only memorize numbers without internalizing the corresponding anatomy, you will make avoidable errors when moving from diagnosis to procedure.
When The Systems Break Down
The universal numbering system gets messy with partial dentitions and missing teeth. If a patient is missing their upper left second molar, you still chart around the gap using the same sequence, which works fine for documentation but becomes awkward when you are generating lab reports that pull data from an electronic health record. Some software platforms handle missing teeth by leaving the number blank, others shift subsequent numbers, and a few default back to FDI notation entirely. Pick one workflow and stick with it across your entire patient population, because switching mid-chart creates inconsistencies that show up during insurance audits. The FDI system handles missing teeth better since each tooth has a unique two-digit identifier that does not depend on adjacent teeth being present. The trade-off is that American-trained clinicians often need a moment to convert back and forth, and the two-digit format is harder to fit into narrow column headers on printed forms. I have seen it cause delays in busy clinics where the front desk is entering codes manually while the hygienist is already in the next operatory. Digital systems solve most of this, but only if they are configured to accept both notations without forcing a conversion that introduces rounding errors or transcription mistakes. A more serious limitation appears with supernumerary teeth and retained primary teeth that do not fit either numbering scheme cleanly. An added mesiodens between the central incisors has no standard number. An ectopic fourth molar behind tooth 1 is sometimes called tooth 1.5 or tooth 8W depending on the provider, and insurance systems usually reject both formats. In those cases I add a brief clinical note with the palatal or vestibular position and a small radiographic marker, because relying on the number alone will not get the claim through.
Get the Full Details
Practical Steps For Getting It Right
Start by picking one system as your default and one as your backup notation. I keep the universal system for routine charting and add the FDI equivalent in parentheses for every multi-tooth procedure. That takes about ten extra seconds per entry and eliminates almost all cross-referencing confusion later. Second, verify quadrant orientation before you begin any restorative work. Sit on the patient's right side when working on the right quadrants and on the left side for the left quadrants. It sounds obvious but I have watched experienced clinicians treat the wrong side because they approached from the unexpected position and momentarily misread the chart. Third, use a visual aid at the chairside. A simple tooth diagram posted on the wall or displayed on a tablet helps patients understand what you are explaining and gives them something to point at during informed consent discussions. When documenting for endodontic referrals, include pulp chamber shape and root canal configuration in addition to the tooth number. A maxillary first molar with a C-shaped canal or a mandibular incisor with two canals requires different instrumentation than a standard case. The number alone does not convey that information, and the receiving clinist will call you back to ask regardless of how clear the radiograph is. Spend the extra minute writing it down upfront and you will save twenty minutes of back-and-forth communication later. For implant planning and surgical guides, the numbering system is only the starting point. You need CBCT data, bone volume measurements, and proximal tooth relationships mapped to the same numbering framework. If your planning software uses one notation and your surgical guide fabricator uses another, the mismatch will not be apparent until the guide does not seat properly. I learned this the hard way when a lab returned a guide that was mirrored because the case files switched from Universal to FDI between the diagnostic wax-up and the surgical phase. The fix was simple in hindsight: enforce a single notation throughout the entire case from diagnosis through follow-up, and require a notation field in every exported file.
If you are looking for reference material, the ADA publishes a current charting guide and the FDI website has a free notation chart that covers both primary and permanent dentitions. Most dental schools also make quick-reference cards available to students, and those tend to be more practical for clinic use than the full textbooks because they fit on a pocket folder. Insurance portals generally accept both systems but may reject certain legacy codes for primary teeth, so check your payer's specification sheet before you submit a high-volume batch of claims. The bottom line is that tooth numbering is a communication tool, not a substitute for anatomical understanding. Learn the numbers, learn the teeth underneath them, and build a workflow that catches mistakes before they leave your operatory. Everything else is paperwork.