What The Temporal Artery Actually Looks Like In Practice
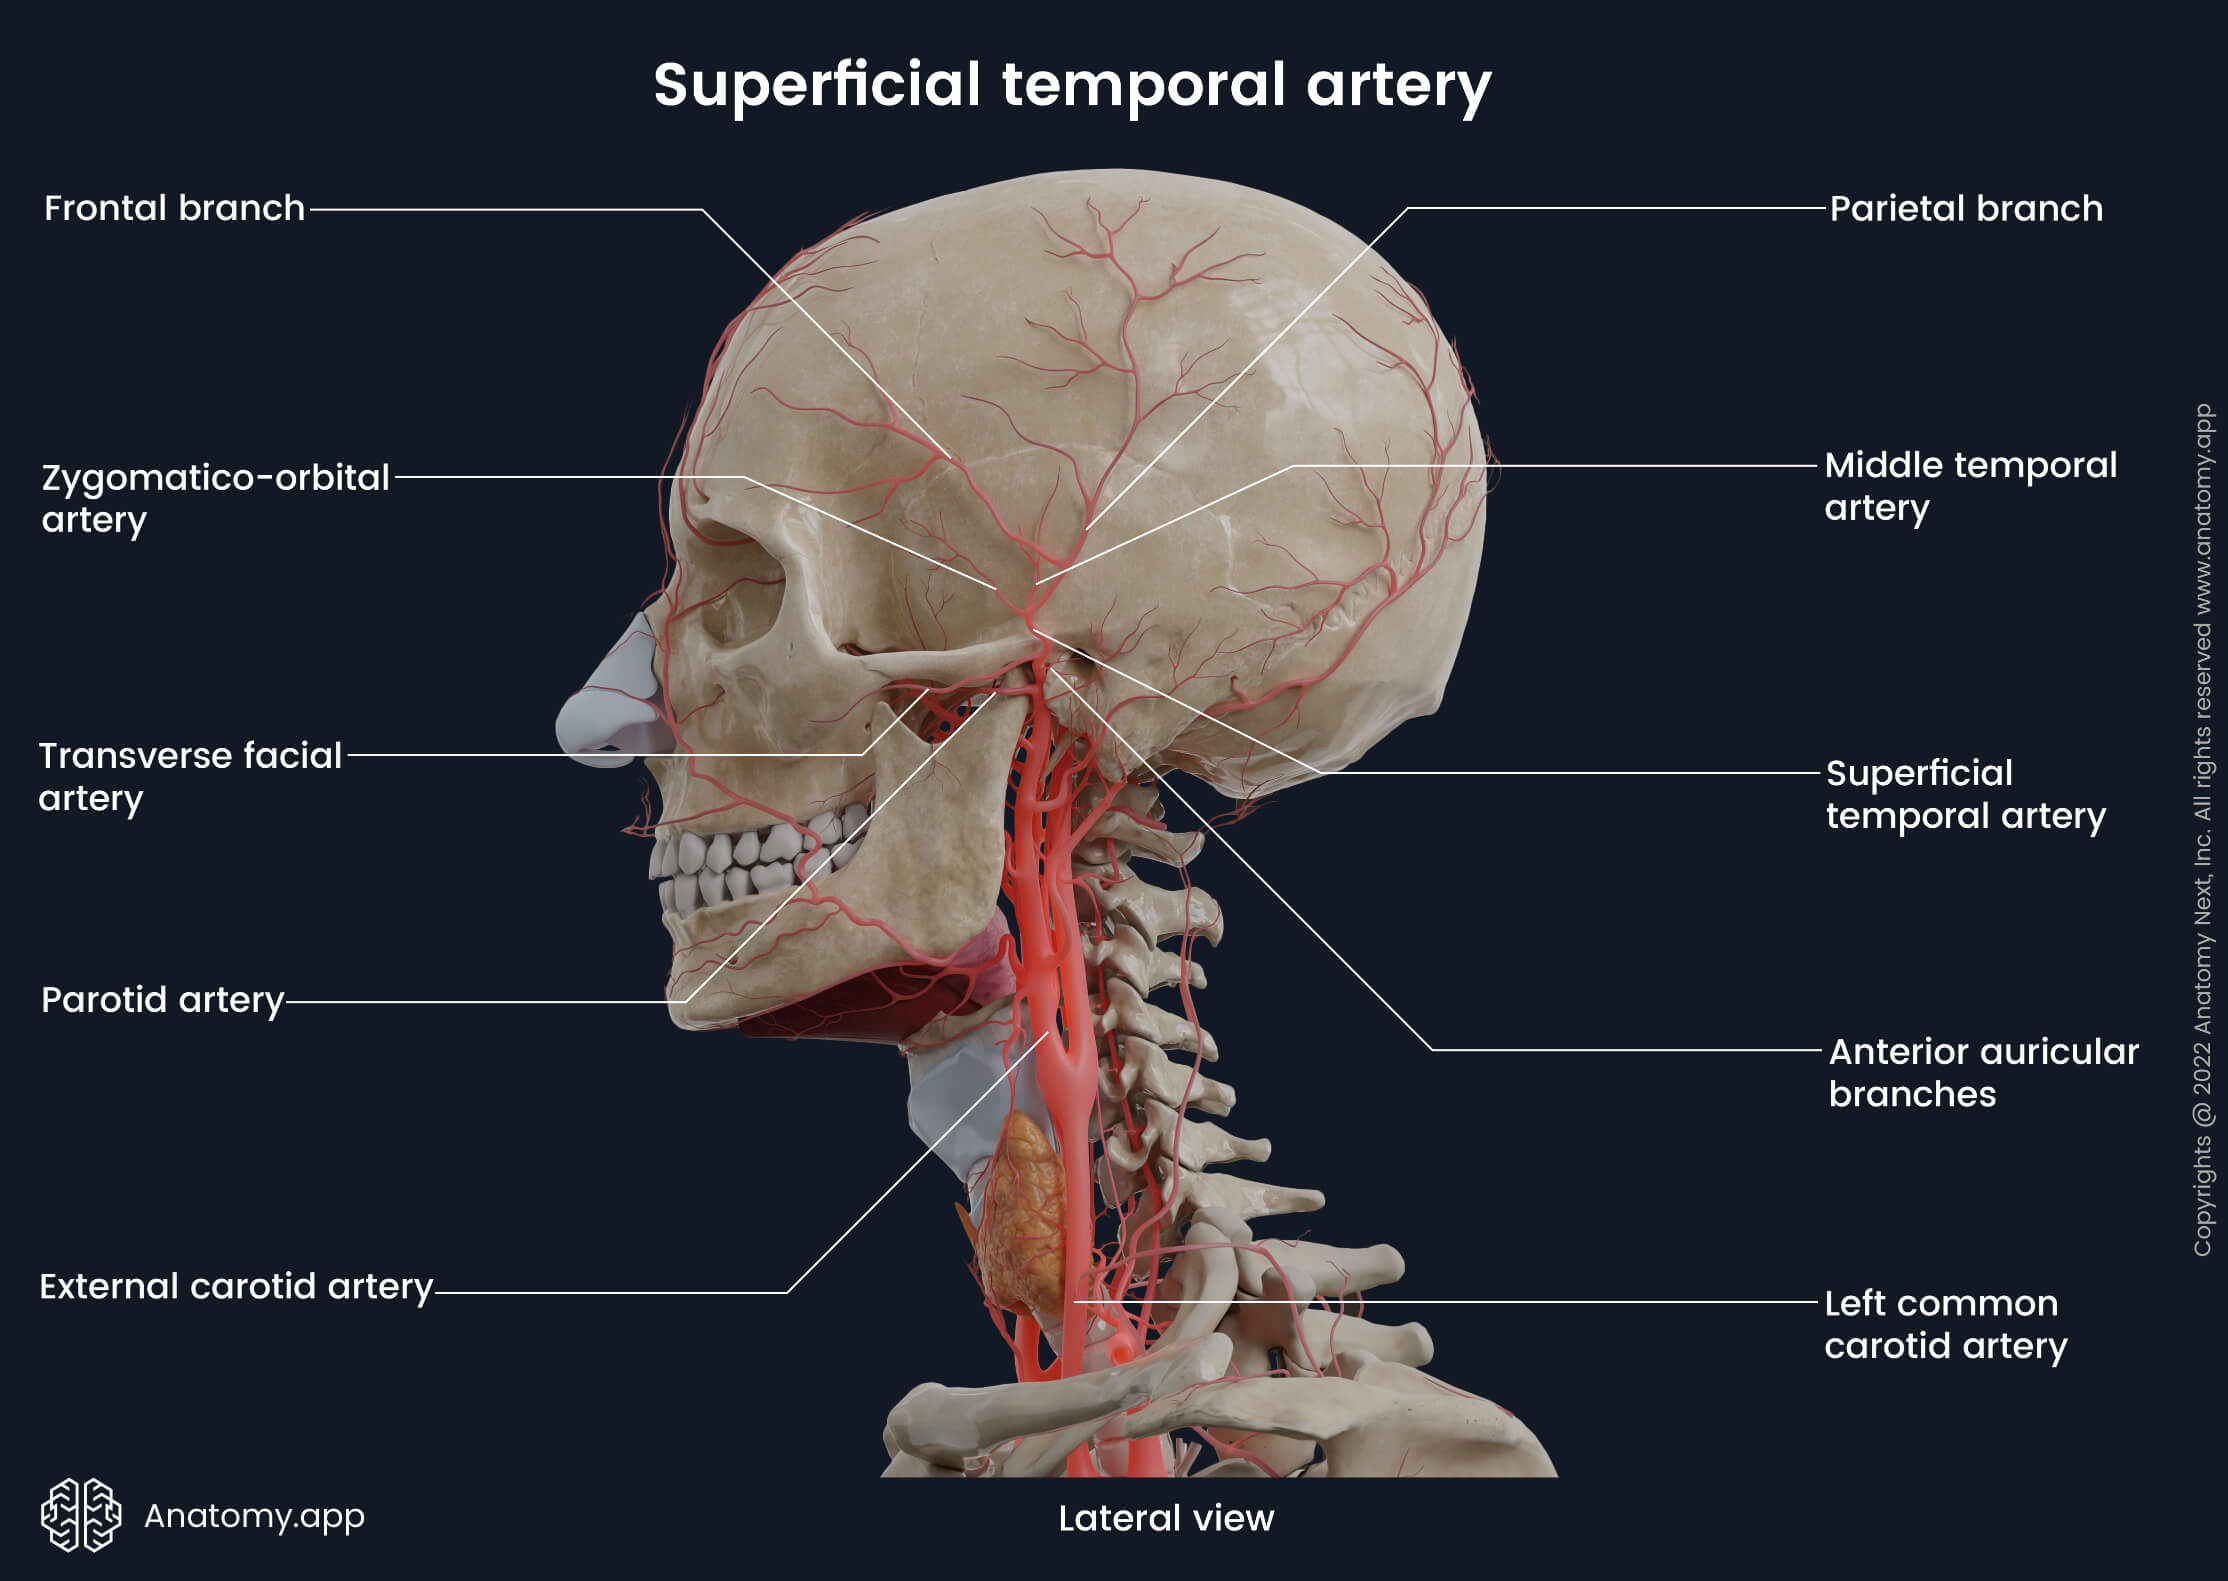
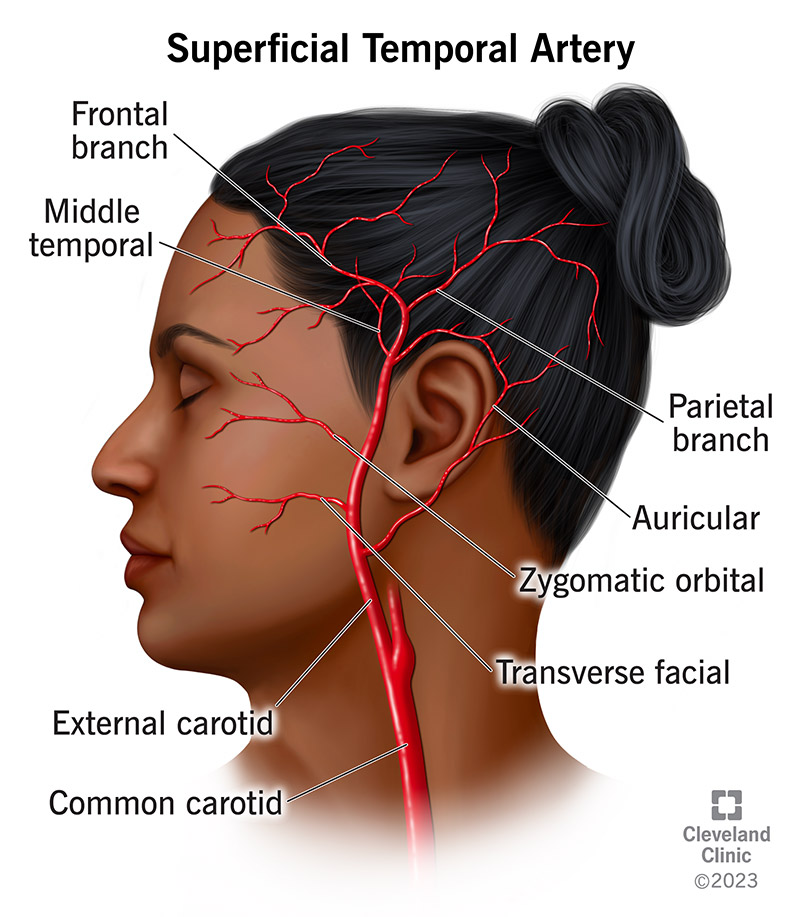
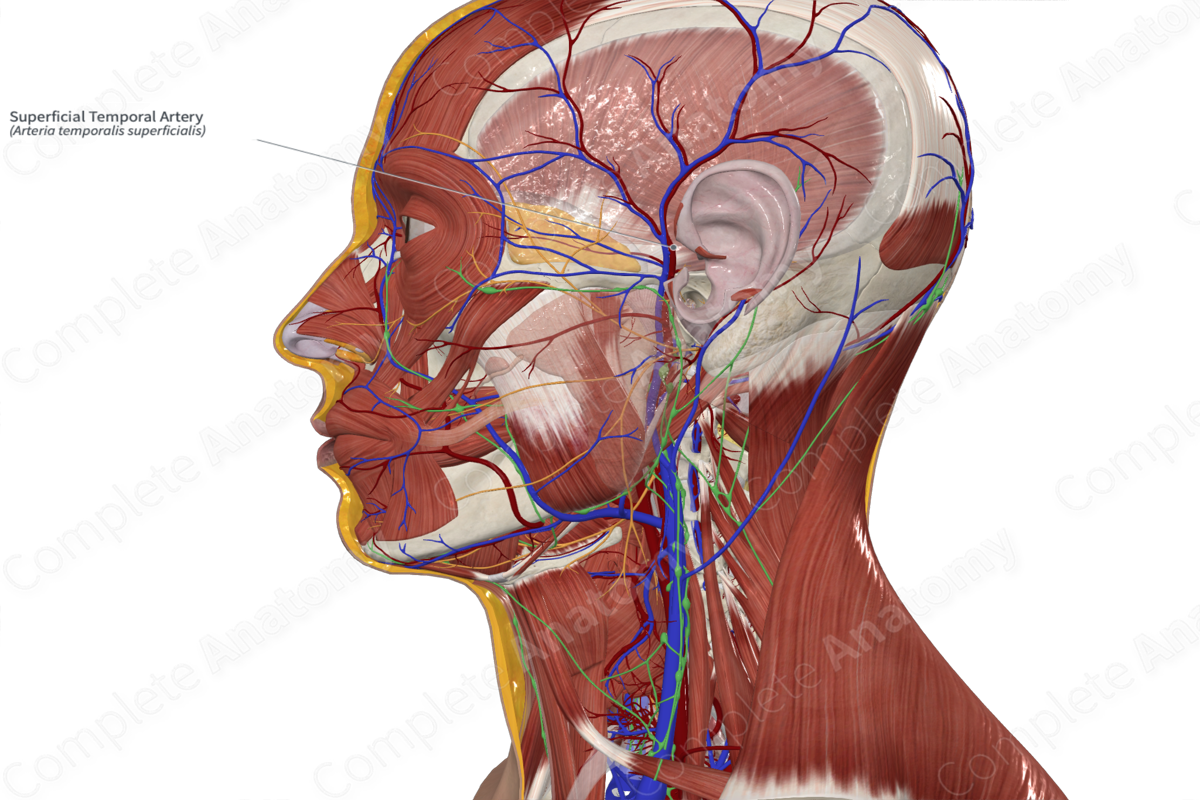
The superficial temporal artery runs just under the skin on the side of your head, roughly where a hairline might sit above the ear. It branches from the external carotid system and gives off several named branches before terminating near the top of the skull. When I first started doing temporal artery biopsies for giant cell arteritis workups, the biggest issue wasn't anatomy itself — it was that the vessel tends to be segmental, meaning disease can skip between segments and give you a false-negative read if you don't sample enough tissue. From proximal to distal, you typically encounter the maxillary branch, the middle temporal artery (which isn't always present), the transverse facial branch, the zygomaticoorbital branch, and finally the frontal and parietal terminal branches. The artery sits superficial to the temporalis fascia but deep to the temporoparietal fascia in most people. That's why you can palpate it as a pulse above the zygomatic arch, though in older patients with calcified vessels the pulse can be threadlike or completely absent despite significant stenosis. I learned this the hard way during a vasculitis clinic rotation. A patient had classic symptoms — jaw claudication, scalp tenderness, elevated ESR — but the temporal artery was non-palpable bilaterally. We still proceeded with the biopsy because ultrasound showed the characteristic halo sign, and sure enough the histology confirmed giant cell arteritis. The takeaway: absence of a palpable pulse doesn't rule out disease, and palpation should never be the sole determinant for whether you image or biopsy.
Why This Anatomy Matters Clinically
Temporal artery biopsy remains the gold standard for diagnosing giant cell arteritis, and knowing the anatomy directly affects yield. The artery is often affected in a patchy, skip-lesion pattern. If you take a 1-centimeter sample, you might hit an unaffected segment and miss the diagnosis entirely. That's why most guidelines recommend a minimum sample length of 1 to 2 centimeters, with some experts pushing for up to 3 centimeters to improve sensitivity from roughly 85 percent to over 95 percent. Another practical consideration is the relationship between the artery and the facial nerve branches. The temporal branch of the facial nerve runs superficial to the superficial temporal artery in the temple region. During a biopsy, you're supposed to place the incision carefully to avoid transecting or stretching those nerve fibers, which can cause temporary or permanent frontalis weakness. I've seen complications where the nerve was damaged because the surgeon was working too laterally without accounting for individual anatomical variation. The nerve typically crosses about 1 to 1.5 centimeters above the tragus, but that distance varies significantly between patients.
Imaging Considerations
Doppler ultrasound has become increasingly important in the diagnostic pathway. The halo sign — a hypoechoic circumferential thickening around the artery lumen — correlates well with granulomatous inflammation on histology. However, operator dependence is real. A study I came across showed sensitivity ranging from 70 to 90 percent depending on sonographer experience, which means a negative ultrasound doesn't definitively exclude disease if clinical suspicion remains high. The limitation here is that calcified vessels, common in elderly patients, can produce acoustic shadowing that mimics or obscures the halo sign. In those cases, compression ultrasound or MRI may add value, though neither is universally available in community settings. I usually default to biopsy when the clinical picture is strong, regardless of imaging results, because the consequences of missed giant cell arteritis — particularly vision loss — are severe enough to justify the procedural risk.
Get the Full Details
Tips For Working With This Anatomy
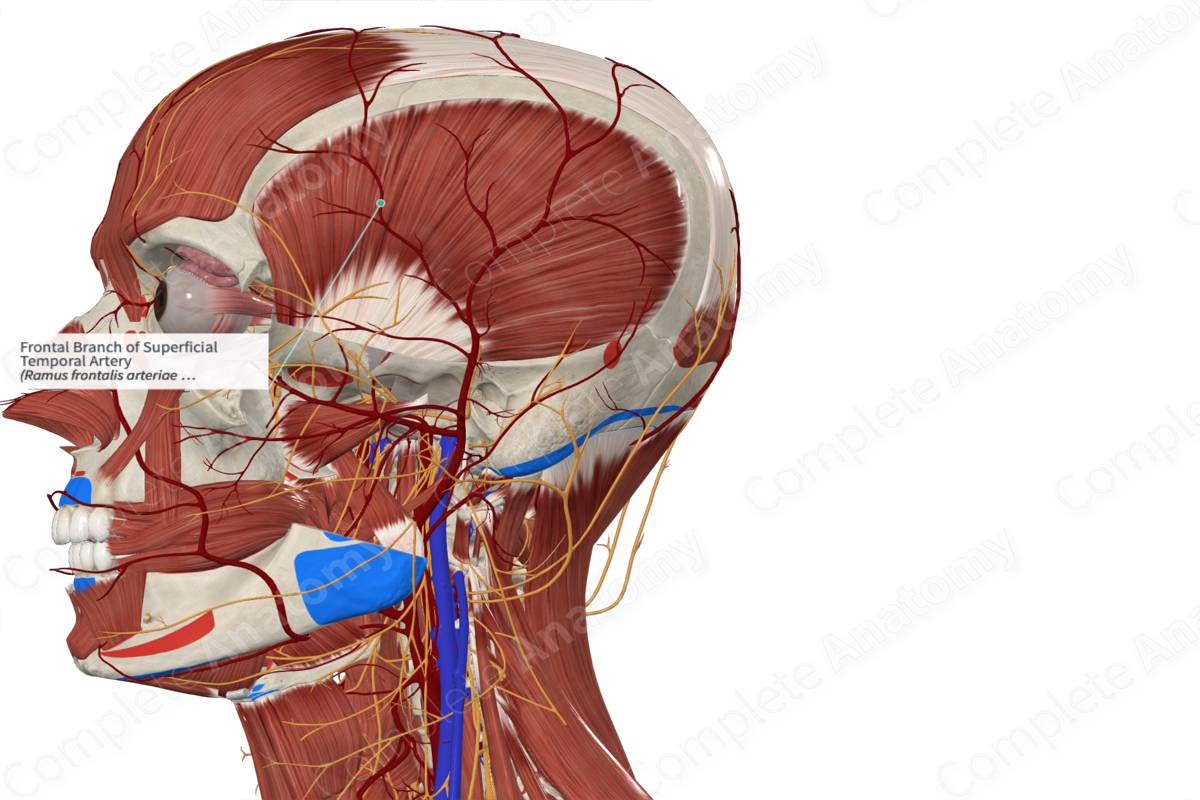
When doing temporal artery interventions or biopsies, use a marker to outline the pulse track before prep. The artery can wander medially or laterally more than textbooks suggest, especially in patients with significant temporal wasting from age or chronic disease. Map both sides — asymmetry can be clinically useful. If you're studying this for exam purposes, don't just memorize branches. Understand why the collateral circulation matters. The external carotid system anastomoses extensively with the internal carotid territory through orbital and nasal branches, which is why temporal artery occlusion rarely causes scalp necrosis but can contribute to ischemic complications in adjacent distributions. The artery wall thickness increases with age even in the absence of vasculitis. Some labs report normal outer diameter up to 4 millimeters in patients over sixty, so cut-off values should be age-adjusted if your institution uses sonographic criteria for diagnosis.