Understanding How Sound Gets From Your Ear To Your Brain
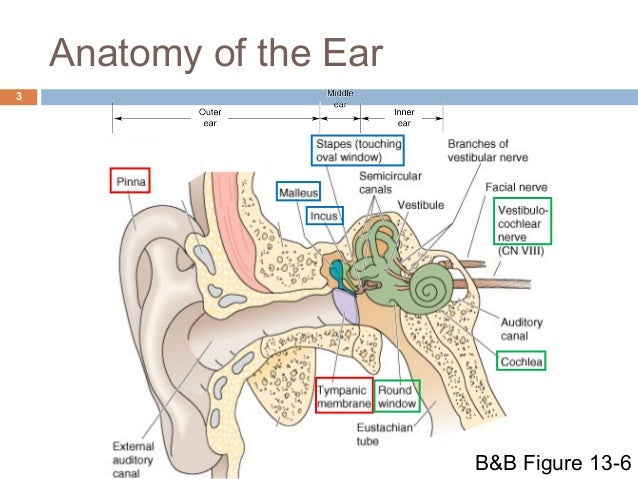
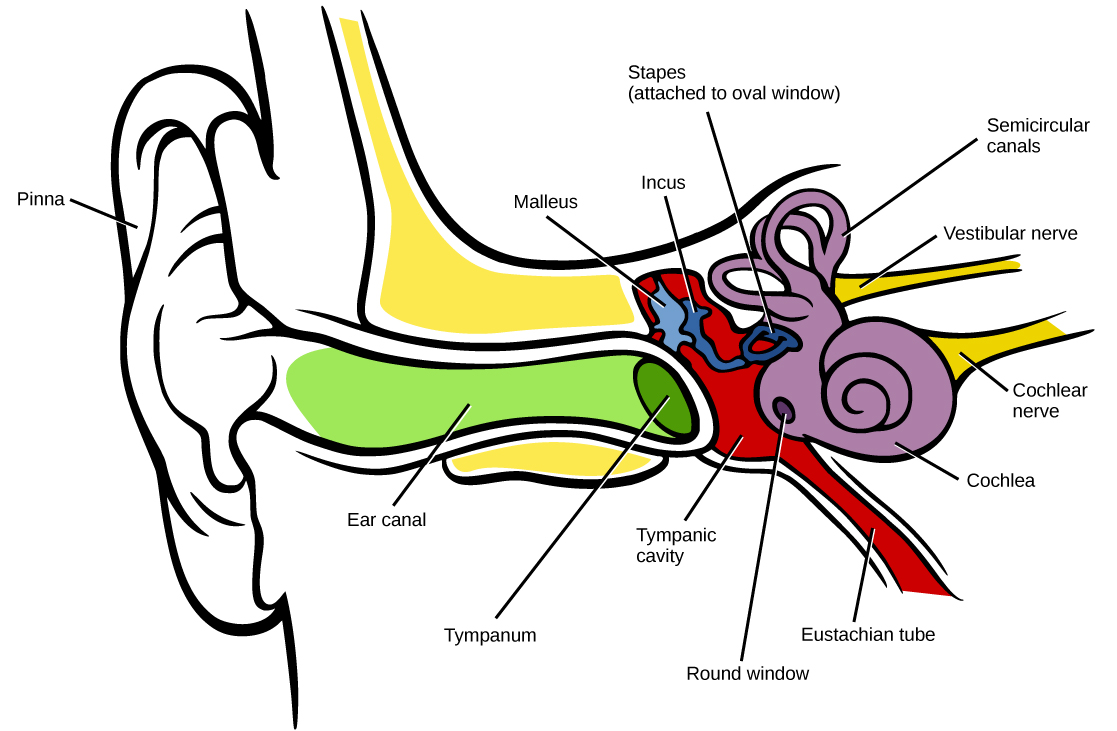
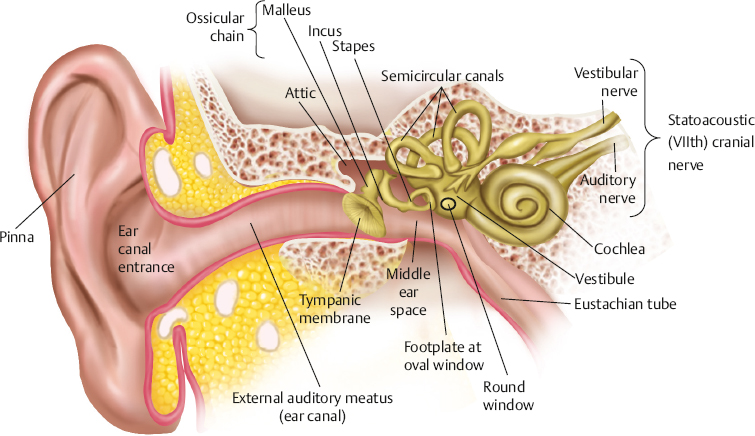
The auditory system is one of those things most people don't think about until it breaks. I spent three years working in audiology research, and let me tell you - the real Anatomy Of The Auditory System isn't some clean textbook diagram. It's messy, interconnected, and full of compensatory pathways that make it surprisingly resilient until suddenly it isn't. When sound enters your outer ear, it travels through the ear canal and hits the eardrum. That's the simple version. The actual version involves the ossicles - three tiny bones called the malleus, incus, and stapes - amplifying vibrations by about 22 times before they reach the fluid-filled cochlea. The cochlea itself is a coiled structure roughly 35 millimeters long in adults, lined with hair cells that convert mechanical vibrations into electrical signals.
Anatomy Of The Auditory System: The Parts That Matter
The outer ear captures sound waves. The middle ear transmits and amplifies them. The inner ear converts them to neural signals. The auditory nerve carries those signals to the brainstem. The temporal lobe processes them into something you recognize as speech, music, or whatever noise you're paying attention to right now. Most people miss the brainstem part. The cochlear nucleus, superior olivary complex, lateral lemniscus, and inferior colliculus all do heavy lifting before signals ever reach your cortex. This is where direction-finding happens, where your brain calculates which ear heard the sound first to determine where it came from. The superior olivary complex alone has specialized neurons for detecting microsecond-level timing differences between ears.
What Actually Goes Wrong
I've seen more hearing loss cases caused by misdiagnosis than by actual pathology. The most common mistake people make is assuming all hearing loss is the same. It's not. Sensorineural hearing loss affects the inner ear or auditory nerve. Conductive hearing loss blocks sound from reaching the cochlea. They require completely different interventions. Here's what nobody tells you: high-frequency hearing loss often develops gradually over decades. You adapt without realizing it. People with mild high-frequency loss will nod along in conversation while actually missing consonant sounds like "s," "f," and "th." They hear "thick" as "ick" or "free" as "ree." The brain compensates using context clues until the gap becomes too large to bridge. During my research work, I encountered a case where a patient had normal audiogram results but couldn't understand speech in noise. Standard hearing tests measure ability in quiet environments. Real-world listening requires processing sound against background noise - a completely different neural challenge. The workaround was directional microphone testing combined with computational auditory scene analysis. This revealed hidden deficits that a pure-tone audiogram completely missed.
Get the Full Details

How to Maintain Your Auditory System
Protection is straightforward but people ignore it. Sound pressure level matters more than duration. Exposure to 85 decibels for eight hours daily causes damage. But a single exposure to 120 decibels - like a gunshot or fireworks close by - can cause immediate, permanent harm. The hair cells in your cochlea don't regenerate. Once they're dead, they're gone. Earwax impaction is the most common reversible cause of hearing loss, yet people treat it with cotton swabs. Cotton swabs push wax deeper, creating impaction. The ear is self-cleaning - jaw movement during chewing helps expel wax naturally. If you suspect impaction, use warm water irrigation or visit a professional. Self-surgery with tools causes more damage than the original problem. Nighttime tinnitus - ringing in the ears when it's quiet - affects roughly 50 million Americans. Most cases are benign. But sudden onset tinnitus accompanied by hearing loss or dizziness requires immediate medical attention. This combination can indicate Meniere's disease, acoustic neuroma, or vascular problems that need prompt diagnosis.
Advanced Diagnostics
Audiograms measure threshold sensitivity across frequencies. That's the baseline. Auditory brainstem response testing measures neural activity from the cochlea through the brainstem. It takes 30-45 minutes, requires no conscious response from the patient, and can detect retrocochlear pathology that standard testing misses. OTOEM - otoacoustic emissions - tests measure sounds generated by healthy outer hair cells in the cochlea. These emissions travel back through the middle ear and can be detected with a sensitive microphone in the ear canal. This test takes 10-15 minutes and is the standard newborn hearing screening method. Absent emissions indicate cochlear dysfunction even when the auditory nerve is intact. The limitation most clinicians overlook: aging affects temporal processing before it affects threshold sensitivity. Older adults may have normal audiograms but struggle with rapid speech or simultaneous conversations. This isn't attention deficit - it's genuine neural timing degradation that compounds across decades of exposure.
When to Seek Help
Sudden hearing loss in one ear requires emergency evaluation within 72 hours. Steroid treatment can restore hearing if administered promptly. After that window, the prognosis drops dramatically. I've seen patients delay because they thought it would resolve spontaneously. It doesn't. Asymmetric hearing loss - significant difference between ears - always warrants imaging. The differential diagnosis includes acoustic neuroma, vascular malformation, and demyelinating disease. MRI with gadolinium contrast is the gold standard. This typically reveals pathology that pure-tone testing cannot detect. Children with recurrent ear infections need monitoring for conductive hearing loss. Chronic otitis media with effusion affects 90% of children by age three. Most resolve spontaneously, but persistent fluid behind the eardrum for more than three months can impact speech development. Tympanostomy tubes relieve pressure and restore hearing immediately, though they don't address the underlying Eustachian tube dysfunction.