Understanding The Human Thorax: A Practical Overview
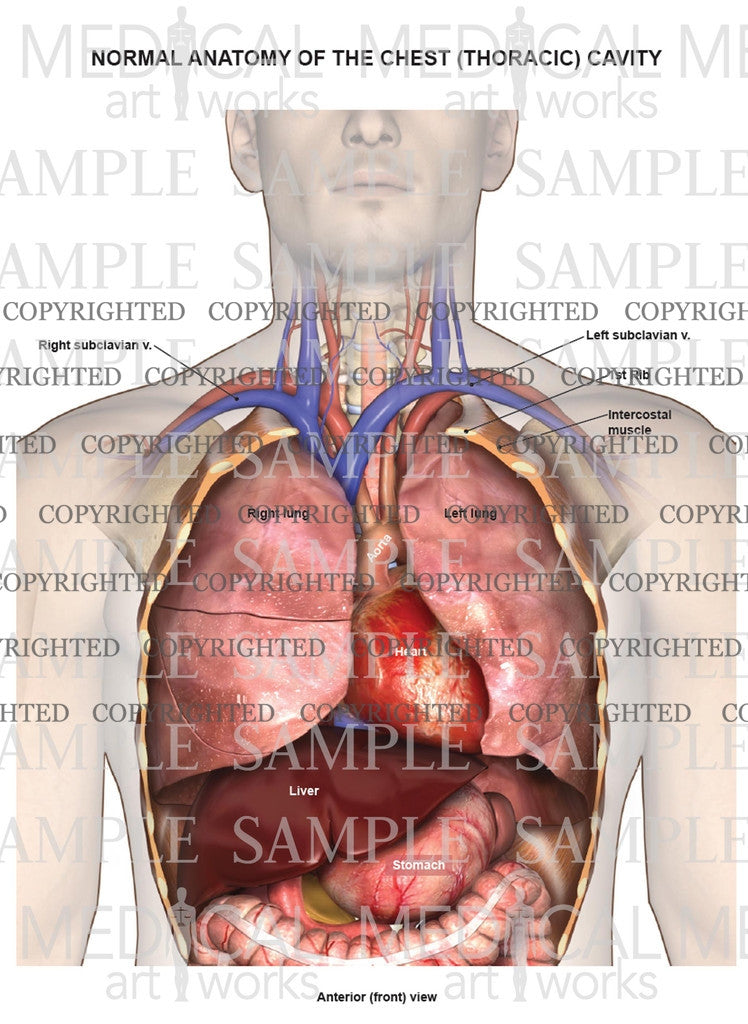
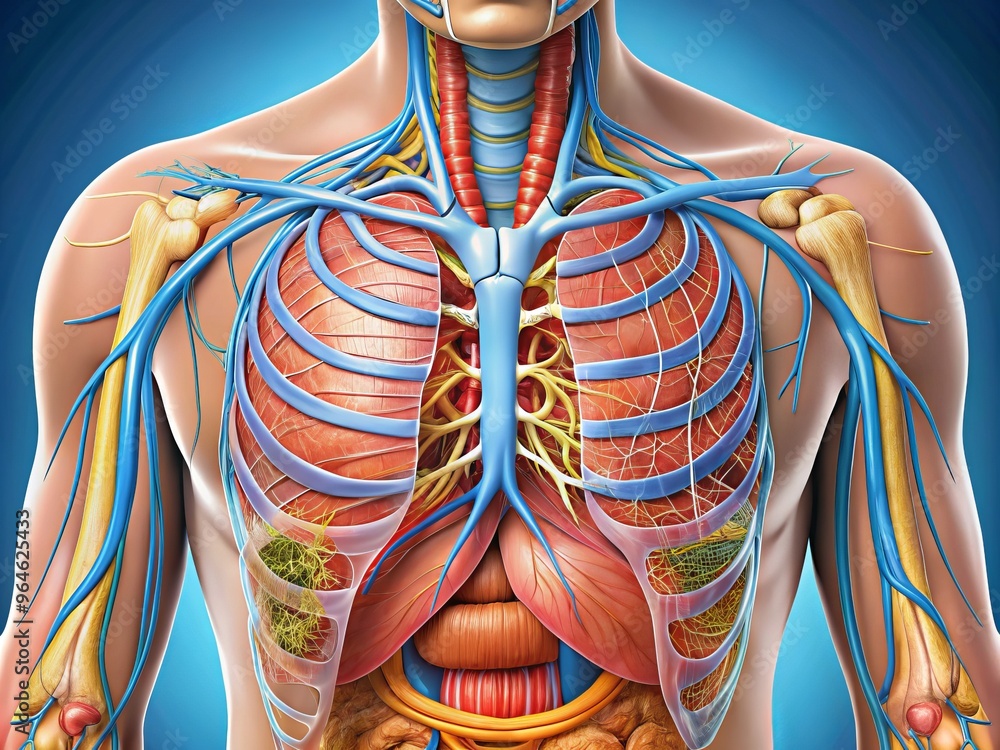
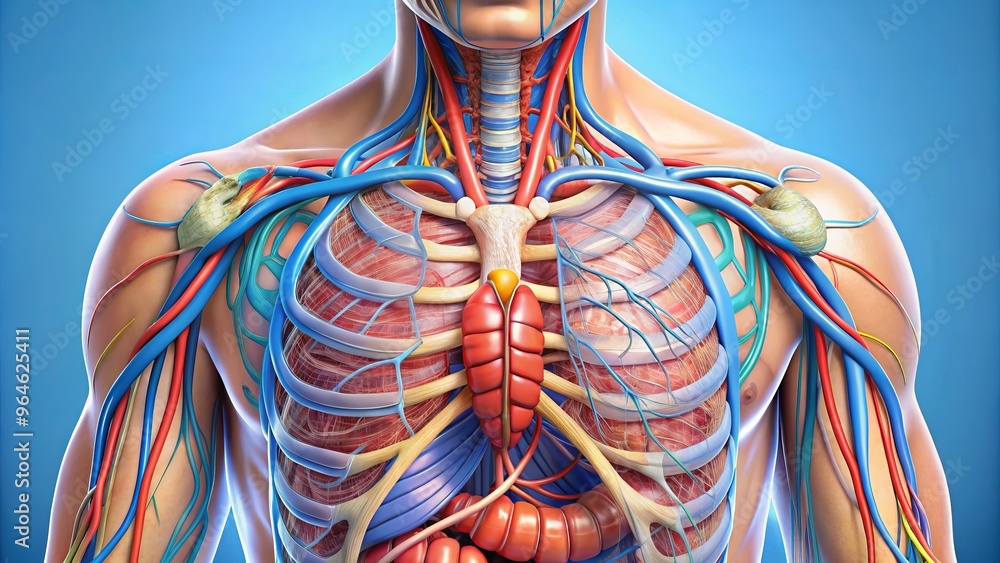
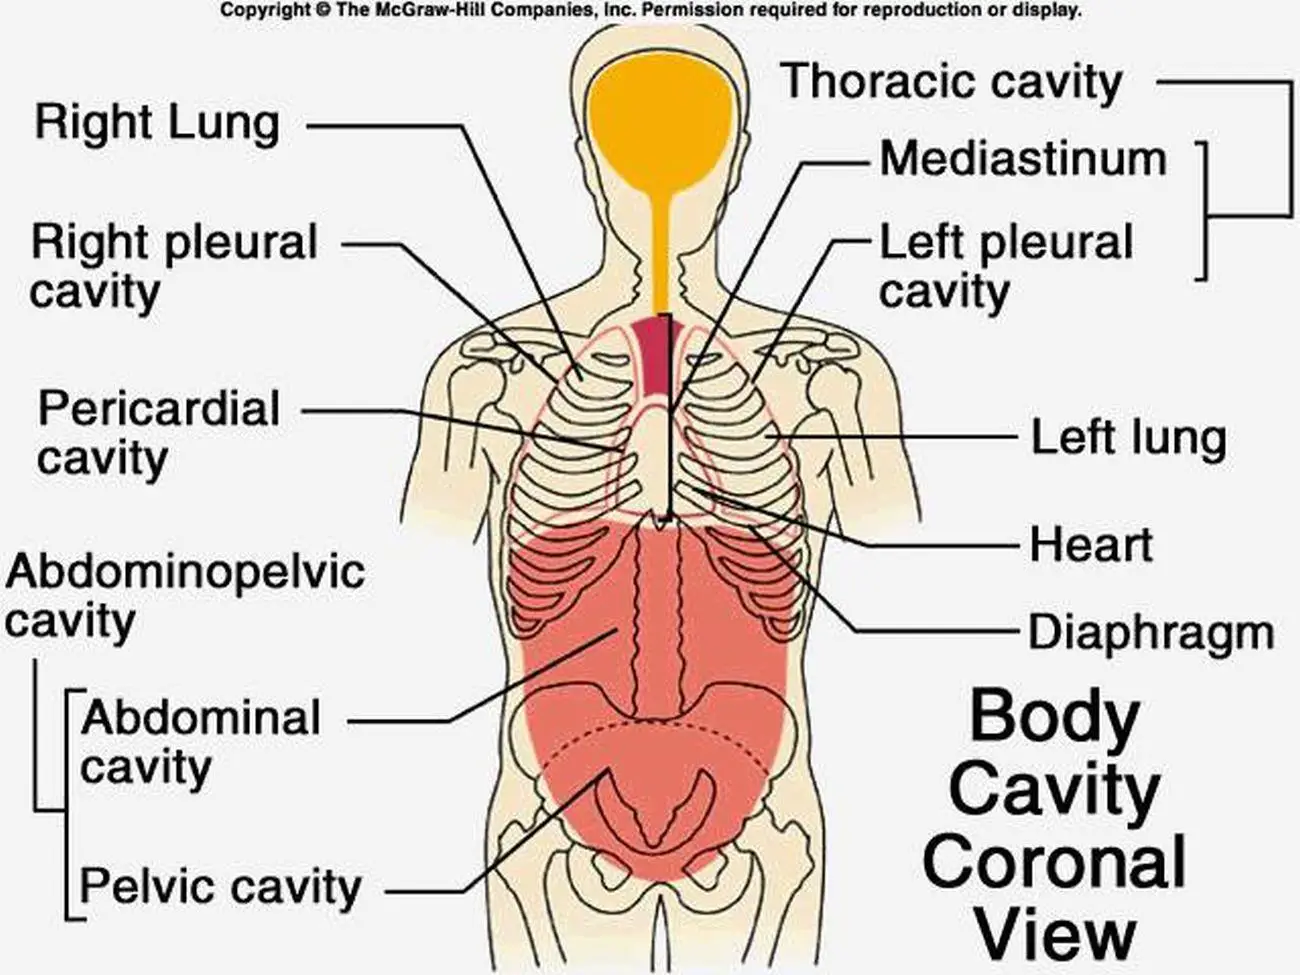
The chest cavity, or thoracic cavity, is one of those anatomical regions that sounds simple until you actually need to work with it clinically or in a forensic context. It is bounded by the rib cage, the sternum anteriorly, the thoracic vertebrae posteriorly, and the diaphragm inferiorly. Everything above the diaphragm in that space is what we are talking about. Lungs, heart, great vessels, esophagus, trachea, thymus remnants—all packed into a relatively tight space with very little room for error. I have spent years reading imaging studies and reviewing autopsy findings, and the thing I notice most is how poorly people understand the compartmentalization. The mediastinum is not one uniform space. It is divided into anterior, middle, and posterior compartments, and knowing which compartment a mass sits in narrows the differential diagnosis dramatically. A lymph node in the anterior mediastinum points to entirely different pathology than one in the paratracheal region.Anatomy Of The Chest Cavity And Its Clinical Relevance
The pleural cavities house the lungs. Each lung has its own pleural sac, and between the two layers—the visceral and parietal pleura—is a thin film of fluid that creates surface tension. That is how the lungs expand when the diaphragm contracts. The intrapleural pressure is normally negative, around -5 cm H2O at rest. When that pressure equalizes with atmospheric pressure because of a puncture wound or a ruptured bleb, you get a pneumothorax. The lung collapses. This is not theoretical. I once spent six hours on the phone with a rural ER doctor trying to help him distinguish a tension pneumothorax from a large pleural effusion on a portable X-ray because they did not have CT access. The key was looking at the mediastinal shift. The trachea was deviated away from the affected side, which confirmed tension physiology and bought them time to insert a needle decompression before the patient coded.
The heart sits in the middle mediastinum, encased in the pericardium. The pericardial sac has two layers: the fibrous pericardium and the serous pericardium. Between them is the pericardial cavity with about 15 to 50 mL of lubricating fluid. Cardiac tamponade occurs when fluid accumulates faster than the pericardium can stretch, compressing the heart and preventing adequate diastolic filling. Beck's triad—hypotension, distended neck veins, and muffled heart sounds—is the classic presentation, but it only appears in about 40 to 50 percent of cases. Relying on the full triad will make you miss a lot of tamponades.
The aorta runs through the posterior mediastinum before passing through the diaphragm at the aortic hiatus at T12. This is a critical landmark. Anything above the aortic arch is in the superior mediastinum, and the structures there include the brachiocephalic veins, the superior vena cava, the arch of the aorta and its branches, the trachea, the esophagus, the thoracic duct, and the vagus and phrenic nerves. Aortic dissections typically start near the ascending aorta and propagate distally. The Stanford classification separates Type A (involving the ascending aorta) from Type B (descending only), and this distinction is everything because Type A requires surgical intervention while Type B is often managed medically. One thing that consistently trips people up is the relationship between the esophagus and the trachea. The esophagus lies directly posterior to the trachea and the left atrium. This is why esophageal ruptures—Boerhaave syndrome—are so dangerous. The leak tracks into the mediastinum, causing fulminant mediastinitis. Mortality climbs sharply after 24 hours without source control. I reviewed a case where a patient presented with subcutaneous emphysema after violent retching, and the initial team attributed it to a Mallory-Weiss tear. They missed the CT finding of a tiny extraluminal air pocket adjacent to the distal esophagus. The patient died from septic shock. It should not have happened. The diaphragm deserves more attention than it gets. It is not just a flat muscle that separates the thorax from the abdomen. It has three major openings, each at a specific vertebral level. The caval opening is at T8 and transmits the inferior vena cava and right phrenic nerve. The esophageal hiatus is at T10 and transmits the esophagus along with the vagal trunks and esophageal branches of the left gastric vessels. The aortic hiatus is at T12 and transmits the aorta, thoracic duct, and azygos vein. Notably, the aortic hiatus is not a muscular opening—it is behind the diaphragm, anterior to the vertebral body. This is why traumatic aortic rupture at the ligamentum arteriosum is such a devastating injury; the aorta is relatively fixed at this point, and deceleration forces create a shearing effect. Lymphatic drainage of the chest cavity follows predictable patterns but has important clinical implications. The right lymphatic duct drains the right upper quadrant—right side of the head, right arm, right thorax—while the thoracic duct drains everything else and empties into the left subclavian vein near its junction with the internal jugular. This is why pancreatic cancer metastases can show up in the supraclavicular nodes, and why chest wall tumors can spread along intercostal spaces. Knowing the drainage pathways changes how you stage disease and plan biopsies. Nerve supply is another area where practical knowledge matters. The phrenic nerve (C3-C5) innervates the diaphragm and also carries sensory fibers from the central diaphragm and pericardium. Irritation of the phrenic nerve can refer pain to the shoulder via the supraclavicular nerves. I had a patient post-cardiac surgery who complained of shoulder pain for weeks. The surgical team dismissed it as musculoskeletal. It turned out to be phrenic nerve neuropraxia from retraction during the procedure. It resolved on its own, but recognizing the pattern would have prevented unnecessary orthopedic referrals and MRIs. The intercostal neurovascular bundle runs along the inferior margin of each rib, protected by the costal groove. This is why chest tubes are inserted just above the rib, not through the middle of it. Going through the rib risks damaging the neurovascular bundle and causing significant bleeding or neuropathic pain. Standard teaching is to place the tube in the "safe triangle" of the chest—bounded by the lateral edge of the pectoralis major, the lateral edge of the latissimus dorsi, the nipple line superiorly, and the diaphragm inferiorly. But this assumes normal anatomy. In patients with prior surgery, trauma, or congenital variations, relying solely on surface landmarks is risky. Ultrasound guidance has become standard for a reason. Blood supply to the chest wall itself comes from multiple sources. The anterior intercostal arteries branch from the internal thoracic (mammary) artery, which arises from the subclavian. The posterior intercostal arteries come directly from the aorta. This collateral network is clinically relevant during coronary artery bypass grafting when the internal thoracic artery is harvested as a conduit. Surgeons need to confirm adequate collateral flow through the lateral thoracic and intercostal branches before sacrificing the ITA, or they risk ischemic damage to the anterior chest wall. I worked with a vascular team that lost a patient to chest wall necrosis after a mastectomy combined with ITA harvest. The collateral circulation was insufficient, and nobody checked preoperatively with a Doppler study.
The thoracic spine itself forms the posterior boundary. The vertebral bodies from T1 to T12 articulate with the ribs via the costovertebral and costotransverse joints. Degenerative changes here are common and often incidental on imaging, but they can compress nearby structures. A large osteophyte from T4-T5 can theoretically compress the esophagus and cause dysphagia, though this is rare. More commonly, spinal pathology in this region presents as radicular pain wrapping around the chest, which mimics cardiac or pulmonary pathology and leads to unnecessary workups. For anyone studying this region, I would recommend starting with cross-sectional anatomy rather than cadaveric dissection alone. CT and MRI give you the spatial relationships that diagrams flatten out. Spend time looking at axial slices at the level of the aortic arch, the pulmonary artery bifurcation, and the diaphragmatic domes. Correlate each structure with its position in the mediastinal compartments. It will make every chest X-ray and every clinical scenario infinitely clearer.Get the Full Details