
Breaking Down What You Actually Need to Know
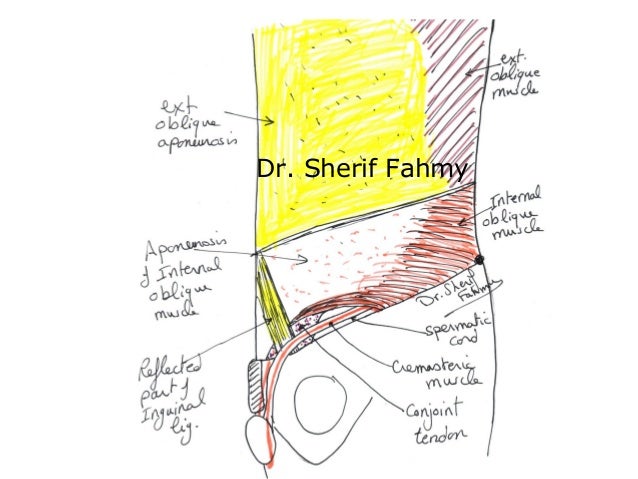
Most people trying to learn the Anatomy Of The Groin Area approach it backwards. They start with a diagram, memorize twelve Latin names, and then get confused when they try to apply that knowledge to something real like a training assessment or a rehab protocol. I spent years watching physio students and strength coaches struggle with the same problem, so let me walk you through how this actually works in practice. The groin is not one thing. It is a junction where the abdominal wall meets the thigh, and that creates a complex overlap of structures that is easy to misread on a flat image. From the outside in, you have skin and subcutaneous tissue, then the superficial fascia which splits into two layers — the more superficial Camper's fascia made of fat, and the deeper Scarpa's fascia which is more fibrous. Below that sits the external oblique aponeurosis forming the inguinal ligament, and underneath that are the internal oblique and transversus abdominis fibers arching over the top. The hip flexors run through here too. The iliopsoas is the big one — it emerges from the lateral border of the psoas major and the iliac fossa, passes under the inguinal ligament, and inserts on the lesser trochanter of the femur. That is why hip flexion weakness or tightness often presents as anterior groin pain rather than pain you'd expect in the thigh itself. Then there are the adductors: longus, brevis, magnus, gracilis, and pectineus. They all originate from the pubic bone and fan out along the femur. When someone says their groin hurts, the adductors are the first thing you check because they take the brunt of most loading errors.
I once worked with a boxer who had chronic medial thigh pain that no one could pin down. We were going through standard adductor stretching protocols for weeks with zero improvement. The issue turned out to be the pectineus — it was being overloaded because his stance width in the ring had shifted due to a minor ankle mobility limitation on the left side. Every time he pivoted, the pectineus was compensating for lack of ankle dorsifiction. Fixing the ankle mobility through targeted mobilization dropped the groin pain by roughly seventy percent in three weeks. The adductor stretching was a red herring.
Functional Considerations That Diagrams Miss
One thing that comes up constantly and most resources gloss over is the relationship between the abdominal wall and the hip capsule. The iliopsoas bursa sits between the iliopsoas tendon and the hip joint capsule, and inflammation here — iliopsoas bursitis — mimics almost everything else in the region. Patients describe deep anterior pain that worsens with hip extension and sometimes even with sitting for extended periods. Without a clinical ultrasound or MRI, it is nearly indistinguishable from an adductor strain at first glance. Another counter-intuitive point: the obturator externus and internus, which are deep hip rotators, can refer pain into the groin area that feels identical to a sports hernia. I've seen multiple cases where athletes underwent surgery for a presumed sports hernia and the post-op result was no better because the actual driver was obturator tendinopathy. A careful manual assessment where you resist internal and external rotation while palpating the obturator region can sometimes separate these two conditions without needing imaging right away. There is also the matter of nerve entrapment. The ilioinguinal nerve, the genitofemoral nerve, and the lateral femoral cutaneous nerve all pass through or near the groin. The lateral femoral cutaneous nerve specifically is prone to compression under the inguinal ligament — that is meralgia paresthetica. People describe it as burning or tingling on the outer thigh, but the pain referral pattern often includes the anterior groin. Tight clothing, weight gain, or even prolonged standing can trigger it. If someone has pure sensory symptoms without any motor weakness or structural pain, think nerve before you think muscle.
Get the Full Details
Practical Assessment Approach
When you are evaluating someone's groin anatomy in a functional context, start with observation. Look for asymmetry in the inguinal region, any visible bulging that suggests a hernia, and Muscle balance between the adductors and abductors. Then move to palpation. The adductor longus insertion on the pubis is a common site of tendinopathy — press just medial to the pubic tubercle and ask the patient to resist gentle adduction. If that reproduces the pain, you have your target. From there, test range of motion in isolation. Hip flexion against gravity, then resisted. Abduction and adduction through the full available range. The Thomas test for hip flexor tightness is still useful despite being old — if the thigh cannot drop flat to the table with the opposite hip flexed, the iliopsoas or rectus femoris is shortened. For adductor length, the modified Ober test with the patient supine and the leg abducted and externally rotated gives you a cleaner read than the standing version. A note on imaging: ultrasound is superior to MRI for dynamic assessment of soft tissue in the groin because you can watch the tendons slide in real time. Static MRI is fine for ruling out structural damage like a complete tear or stress fracture, but if you need to see if the adductor longus is subluxing or if the iliopsoas tendon is snapping over the ilipectineal eminence, you need a live ultrasound with movement. That is something I learned the hard way after referring a client for an MRI that came back normal while she was still having audible clicks and pain during daily movement.
Common Mistakes and Where This Framework Falls Short
The biggest mistake I see is treating the groin as a collection of isolated muscles when it functions as a kinetic chain. You will get far better results addressing the lumbar spine, the hip capsule, and the foot mechanics before you ever touch the adductors directly. But this approach requires a solid foundational understanding of regional anatomy, which means it does not work well in quick-fix environments where the expectation is a ten-minute solution. If someone walks in expecting a stretching routine to solve chronic groin pain, you need to be honest that it might take four to eight weeks of integrated work to see meaningful change, assuming the issue is soft tissue related and not structural. Another limitation: this framework is less reliable for identifying inguinal hernias. Palpation can detect bulging, but occult hernias — the kind that only appear with Valsalva — often require a dynamic ultrasound or even diagnostic laparoscopy. Do not pretend that manual assessment alone can rule those out. If there is any suspicion, refer out. For the self-assessment crowd, start by learning the bony landmarks. The pubic symphysis is the midline reference point. The anterior superior iliac spine on each side marks the lateral boundary. The adductor tubercle on the medial femur is the distal anchor. Everything else lives between those points. Once you can reliably identify those landmarks by touch, the rest of the Anatomy Of The Groin Area becomes significantly easier to map onto actual movement and actual pain patterns.
")


