The structural breakdown most textbooks get wrong about
When you look at the Anatomy Of The Kidney under a microscope, the first thing that hits you is how repetitive everything is. The nephron is the working unit, and each kidney contains roughly 5 to 6 million of them, give or take based on body size and ancestry. They are not all identical. That difference matters more than most people realize. I spent years reading cross-sections and tracing tubules through serial blocks, and what I kept running into was a consistent gap between what the diagrams show and what the tissue actually does. The classic textbook rendering makes the kidney look like a clean assembly line. It isn't. The proximal tubule alone reclaims about 65% of filtered sodium and water, and it does this without any visible segmentation in most standard H&E stains. You have to use specific markers like megalin or brush border enzyme stains to actually see where the reabsorption effort concentrates.
Understanding the Anatomy Of The Kidney Through Functional Units
The nephron consists of the renal corpuscle, the proximal tubule, the loop of Henle, the distal tubule, and the collecting duct. That list sounds straightforward until you try to trace individual segments in a live tissue sample. The loop of Henle dips into the medulla at varying depths depending on whether the nephron is cortical or juxtamedullary. Cortical nephrons, which make up roughly 85% of the total, have short loops that barely enter the outer medulla. Juxtamedullary nephrons, only about 15%, send their loops deep into the inner medulla. This depth distinction is what enables urine concentration, and it is also why certain toxins and ischemic injuries affect the two populations differently. Here is where the standard description starts to fail you. The glomerulus sits inside Bowman's capsule, and the filtration barrier is made of three layers: the fenestrated endothelium, the glomerular basement membrane, and the podocyte foot processes. Most people stop there. What they miss is that the afferent arteriole entering the glomerulus is consistently larger in diameter than the efferent arteriole leaving it. This size difference is not decorative. It creates the hydrostatic pressure gradient that drives filtration in the first place. If that gradient shifts even slightly, GFR changes rapidly and there is no local mechanism to correct it other than tubuloglomerular feedback through the macula densa. I ran into a case once where a patient had normal creatinine but abnormal protein excretion, and every standard imaging study came back clean. The issue was microscopic: early diabetic changes in the podocytes that did not show up on light microscopy at all. You need electron microscopy or at least specific immunofluorescence staining to see the foot process effacement that was causing the leak. Standard gross anatomy descriptions of the kidney will never prepare you for that kind of disconnect between structure and function.
What the renal cortex and medulla actually do
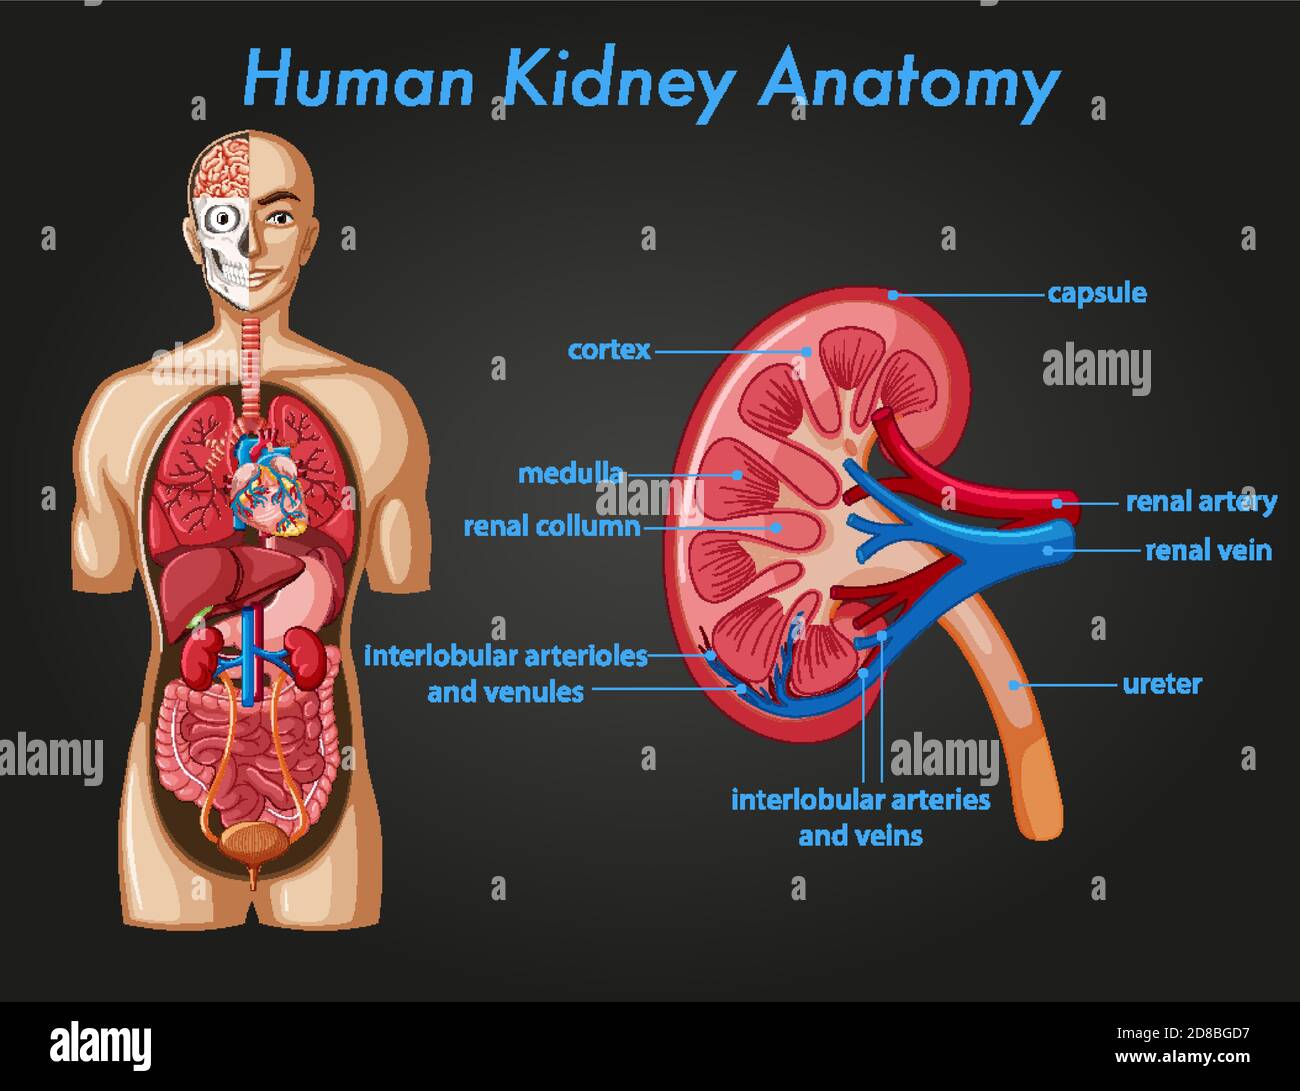
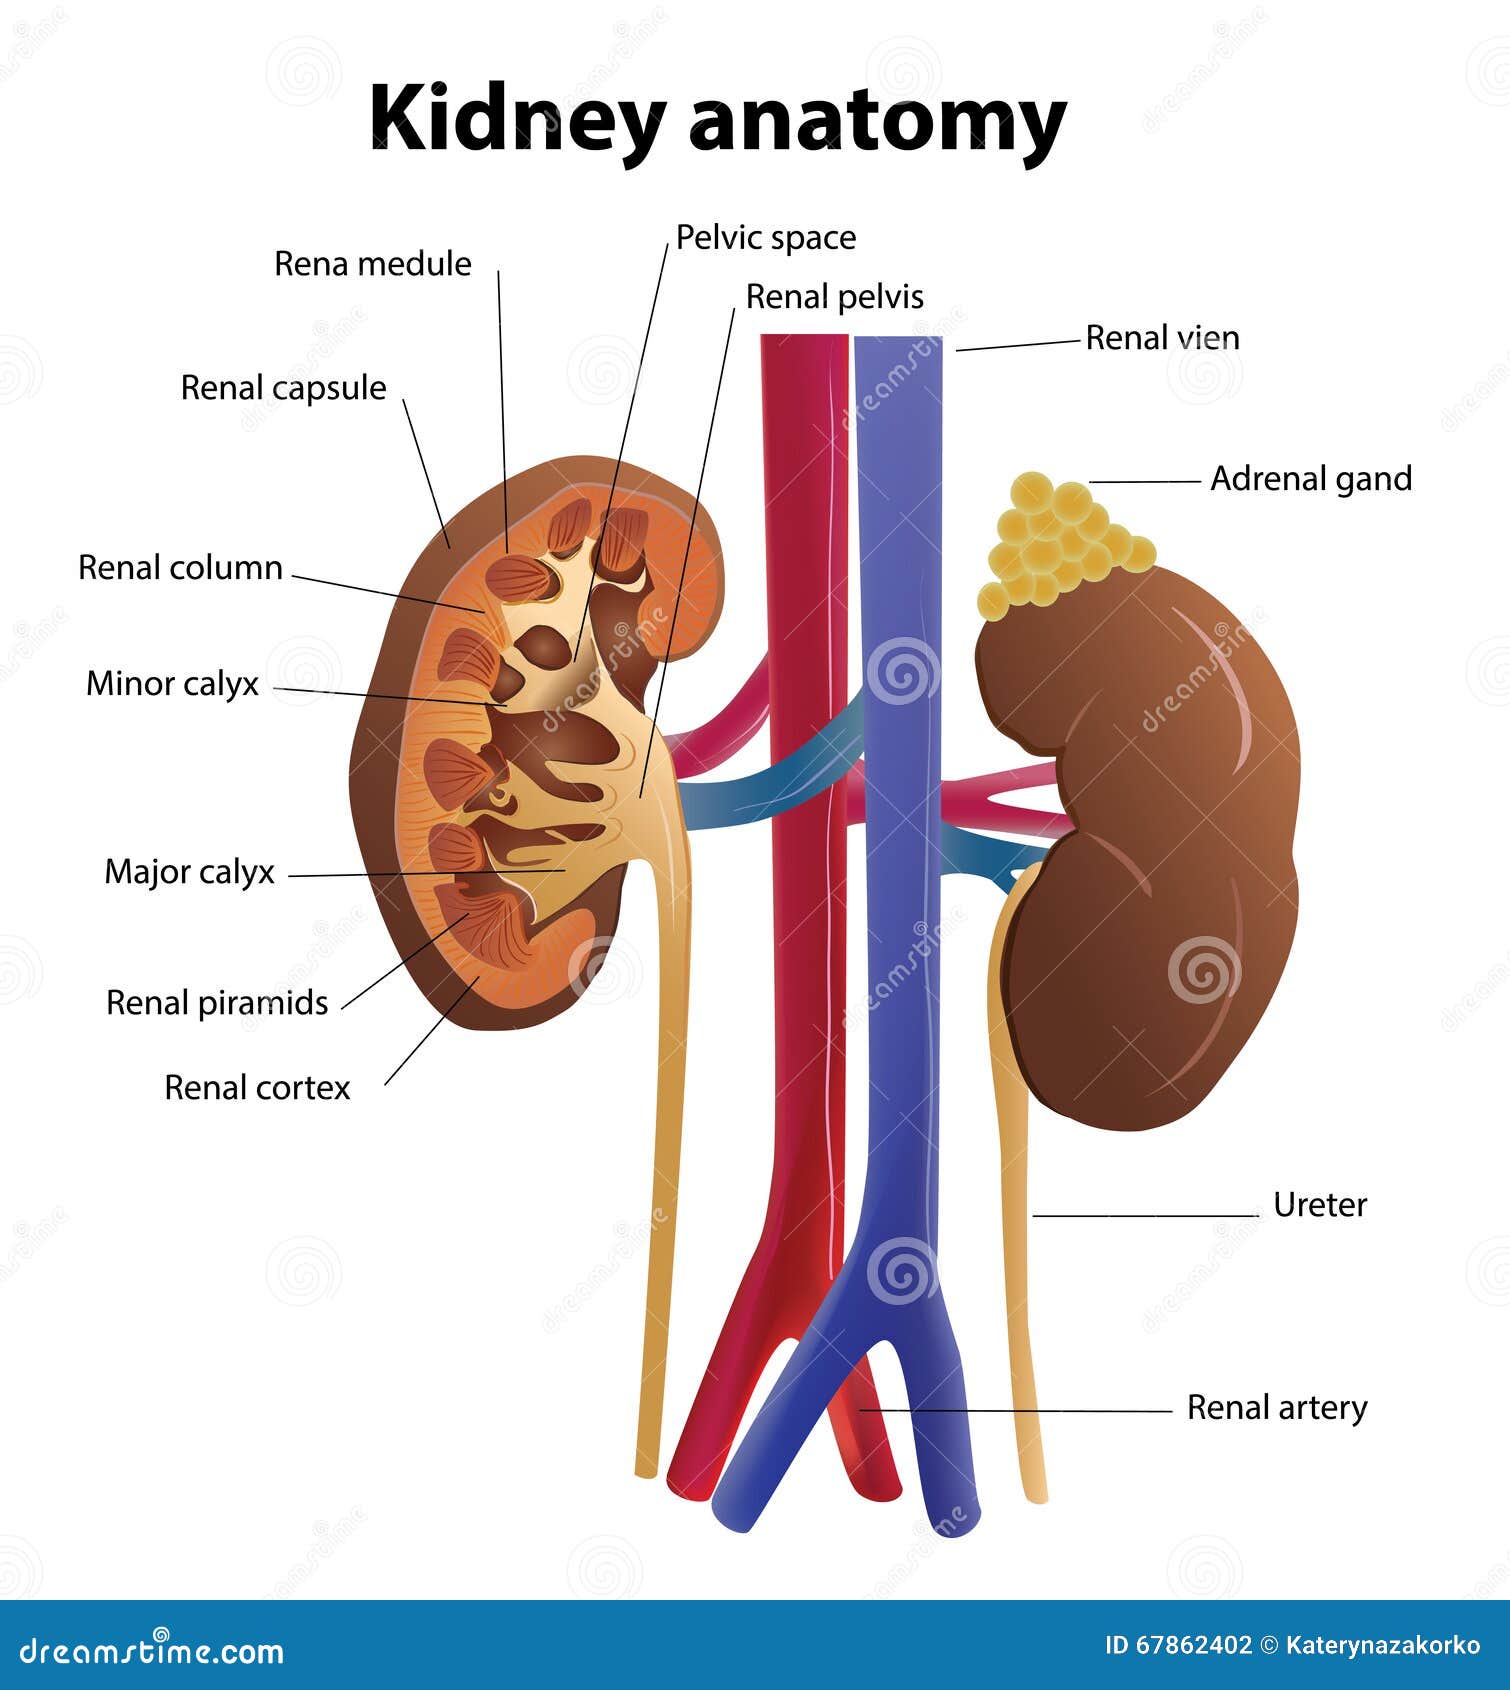
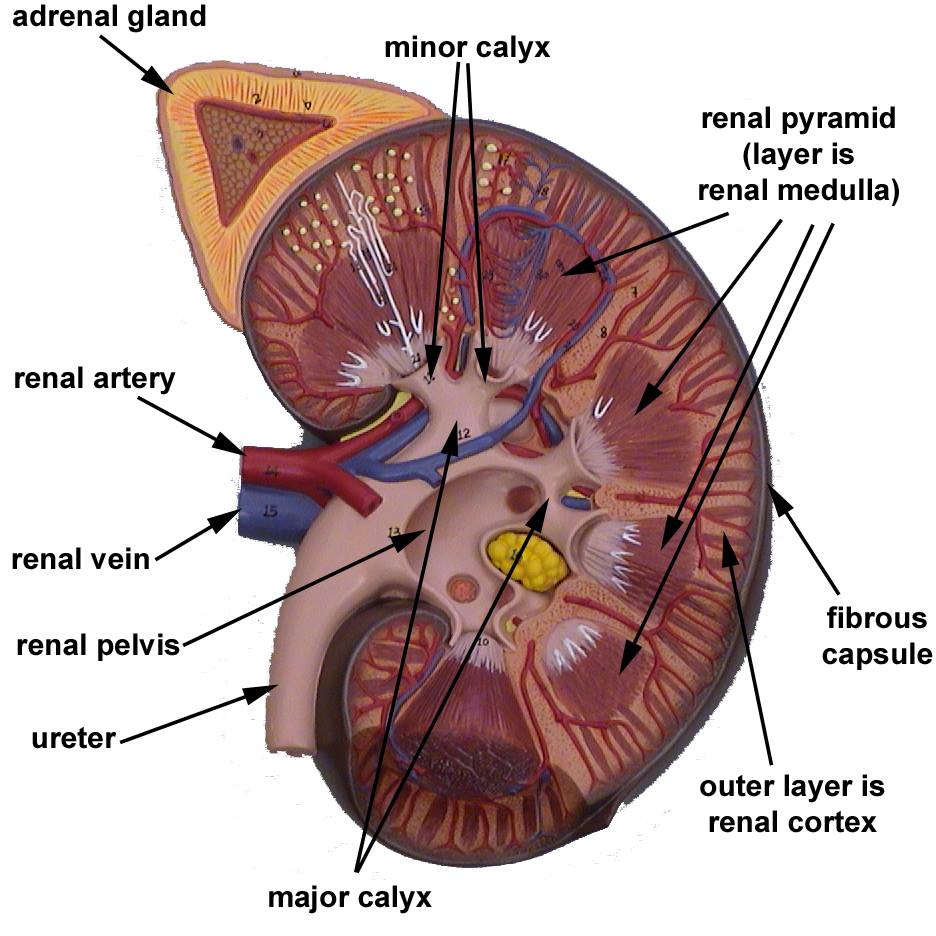
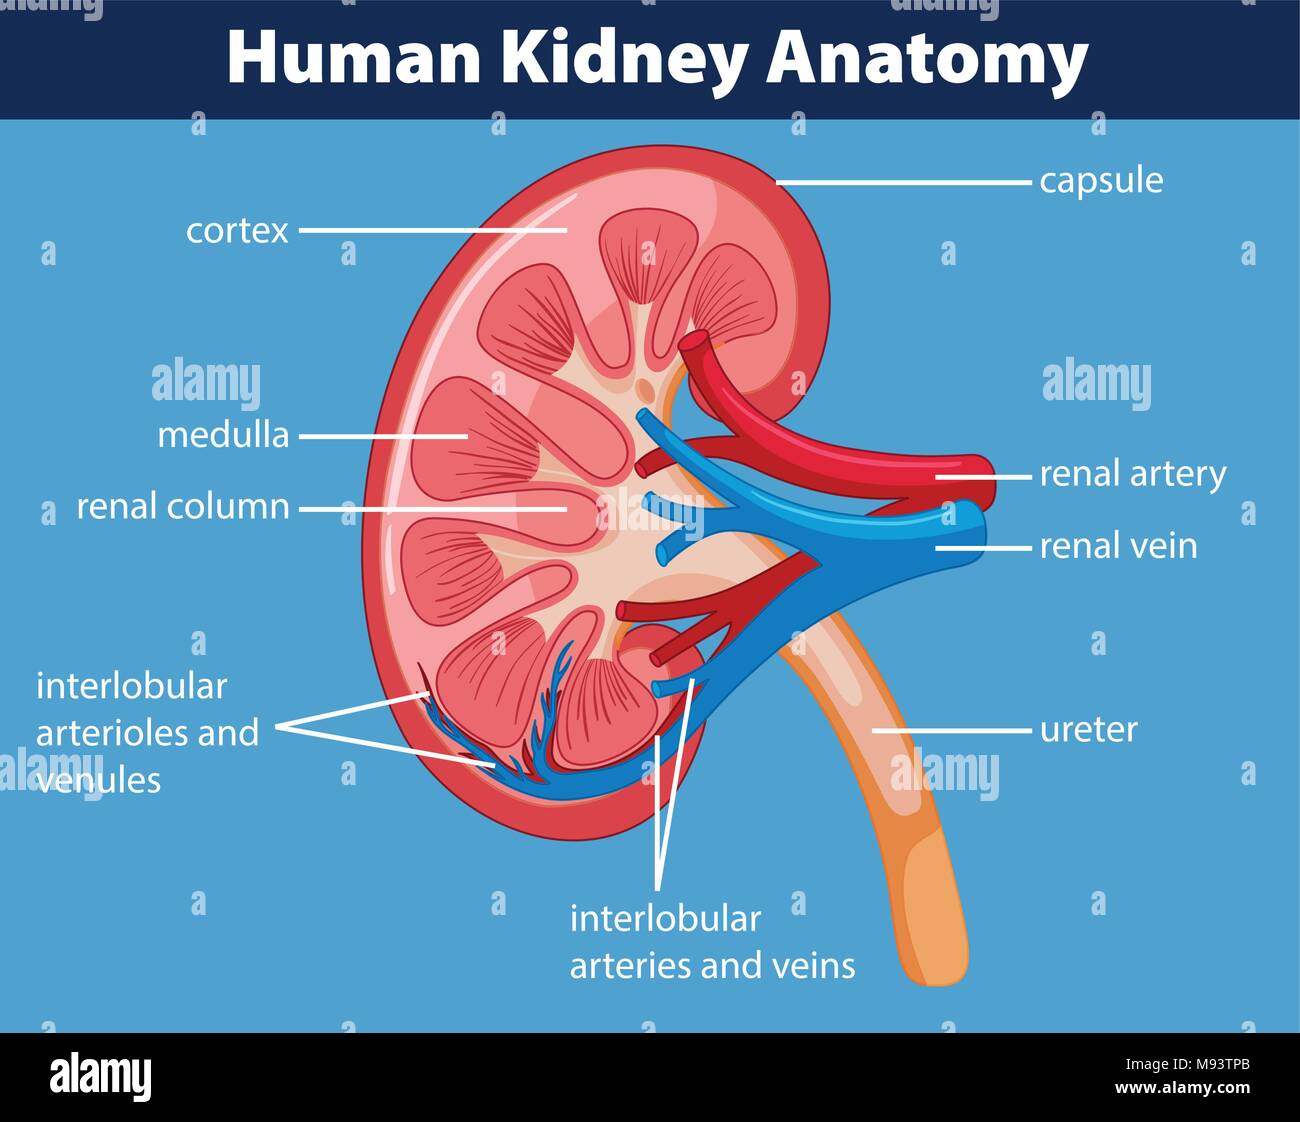
The cortex contains the renal corpuscles and the convoluted portions of the tubules. The medulla contains the loops of Henle and the collecting ducts arranged in parallel bundles called medullary rays. The boundary between them is not a hard line. It is a gradient, and the osmolarity changes continuously from cortex to inner medulla, rising from about 300 mOsm to over 1200 mOsm in healthy adults. The juxtamedullary nephrons are the ones that matter for this gradient. Their efferent arterioles form the vasa recta, long capillary loops that run parallel to the loops of Henle. These vessels act as countercurrent exchangers, preserving the medullary osmotic gradient rather than washing it away. If the vasa recta are damaged, the gradient collapses and concentrating ability drops dramatically. This is one reason why renal vascular disease often presents with concentrated urine defects before serum markers like creatinine become abnormal. The renal pelvis funnels urine into the ureter, and the calyces are the intermediate chambers. This drainage system is lined by transitional epithelium, which is designed to stretch. When you have obstruction, the calyces dilate first, and that dilation shows up on imaging well before the parenchyma starts losing function. I have seen patients whose imaging looked relatively normal despite significant underlying damage because the collection system had not yet dilated enough to be obvious.
Get the Full Details
The blood supply and why it breaks down in practice
The renal artery branches into segmental arteries, then interlobar arteries that run between the pyramids, arcuate arteries that arch along the corticomedullary junction, and finally interlobular arteries that feed the cortical circulation. From there, the afferent arterioles supply the glomeruli. The entire system operates under high flow relative to organ size. The kidneys receive roughly 20 to 25% of cardiac output, which translates to about 1 to 1.2 liters per minute in a resting adult. That volume is necessary because filtration happens constantly and the kidney cannot store blood the way other organs can. Any interruption in flow causes rapid damage to the tubular epithelium, particularly in the proximal convoluted tubule and the thick ascending limb, which have the highest metabolic demands. Ischemic injury here is dose-dependent and time-dependent. After about 30 to 60 minutes of complete ischemia, acute tubular necrosis becomes likely. The cortex shows the earliest signs, and those signs are patchy, not uniform. I once reviewed a series of post-mortem samples from patients who had survived prolonged shock before dying. The kidney sections showed a consistent pattern: the outer stripe of the outer medulla was almost always the first zone to show coagulative necrosis, even when cortical involvement was minimal. Standard Anatomy Of The Kidney courses emphasize the glomerulus and the tubules as the primary structures, but they rarely stress how vulnerable the medullary transition zones are to hypoperfusion. That blind spot matters clinically because it explains why some patients develop concentrating defects after sepsis or major surgery before their creatinine rises at all.
The peritubular capillaries surrounding the proximal and distal tubules are where reabsorption and secretion actually exchange with the blood. The vasa recta handle the same job in the medulla but with different hemodynamics due to the low-flow, high-osmolarity environment. Both systems depend on intact endothelial function, and both are compromised early in conditions like vasculitis or malignant hypertension. The glomerulus gets all the attention, but the microcirculation around the tubules is where most chronic kidney disease progression actually plays out.
What nobody tells you about histological variation
Nephron numbers vary between individuals. Some people have fewer than 400,000 per kidney, others exceed 1 million. This variation is largely set before birth and does not change afterward. When nephron loss occurs later in life, the remaining nephrons hypertrophy to compensate, but that compensation has limits. Hyperfiltration in surviving units eventually damages the glomerular capillaries, creating a vicious cycle that standard laboratory tests catch too late. The juxtaglomerular apparatus sits at the vascular pole of the renal corpuscle where the distal tubule contacts the afferent and efferent arterioles. It contains three cell types with distinct roles: the macula densa cells sense sodium chloride concentration in the tubular fluid, the juxtaglomerular cells in the afferent arteriole wall produce renin, and the extraglomerular mesangial cells provide structural and signaling support. This apparatus is the local regulator of glomerular filtration rate, and it responds to changes in tubular flow within seconds. It is also easy to overlook in routine histology because it occupies a tiny region and requires specific staining to distinguish clearly. The renal sinus is the central cavity that contains the renal pelvis, calyces, blood vessels, nerves, and fat. The fat is not inert packing material. It provides structural support and serves as a conduit for vessels and nerves entering and exiting the parenchyma. Excessive sinus fat, which occurs with aging and obesity, can compress the collecting system and contribute to obstructive uropathy even without a discrete stone. This is another structural detail that Anatomy Of The Kidney discussions routinely skip over.
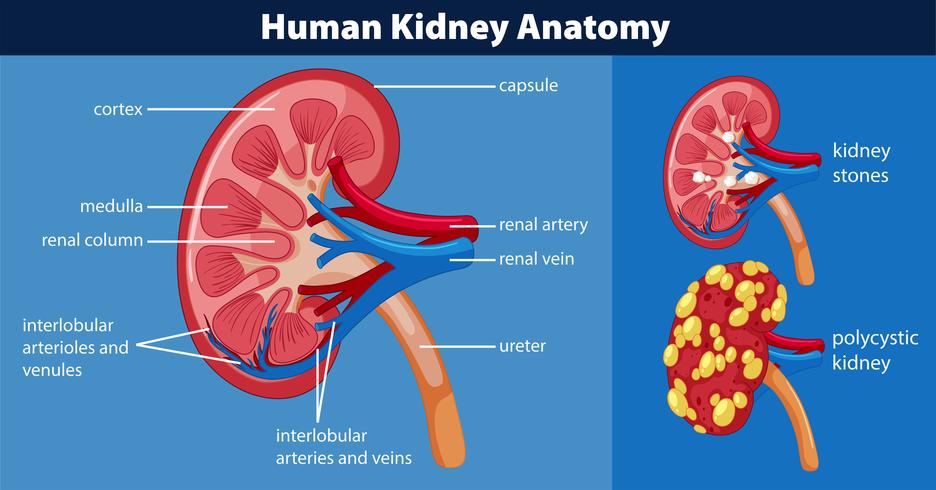
The capsule surrounding the kidney is a tough fibrous layer that adheres closely to the parenchyma. It provides mechanical protection and helps maintain shape, but it is not elastic. When the kidney swells from inflammation or obstruction, the capsule resists expansion, which increases intrarenal pressure and reduces perfusion. This is one reason why rapidly progressive glomerulonephritis can cause severe pain: the capsule stretches against its limited compliance. If you are studying this for clinical purposes, focus less on memorizing the named segments and more on understanding the relationships between blood flow, tubular function, and tissue vulnerability. The structure is consistent, but the functional implications are where the real complexity lives. Knowing that the proximal tubule reabsorbs glucose completely under normal conditions is useful. Knowing that this reabsorption capacity saturates at a specific plasma glucose threshold and that the saturation point varies between individuals is what actually affects patient care. Same with the countercurrent multiplier system. Understanding the mechanism is one thing. Understanding why it fails in specific disease states is another. The kidney does not forgive poor perfusion, and it does not regenerate lost nephrons. The structural details matter because they determine which parts fail first, which functions decline earliest, and which interventions actually address the root problem rather than just the lab values. That is the practical side of studying the Anatomy Of The Kidney that most resources do not cover adequately.