Why the Lower Eyelid Keeps Giving Surgeons Trouble
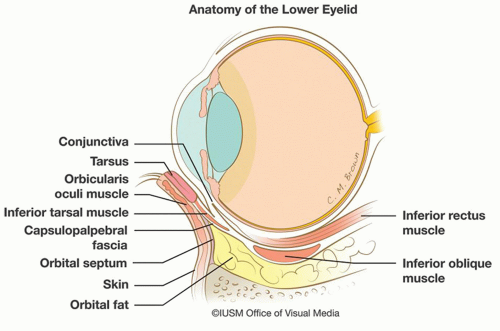
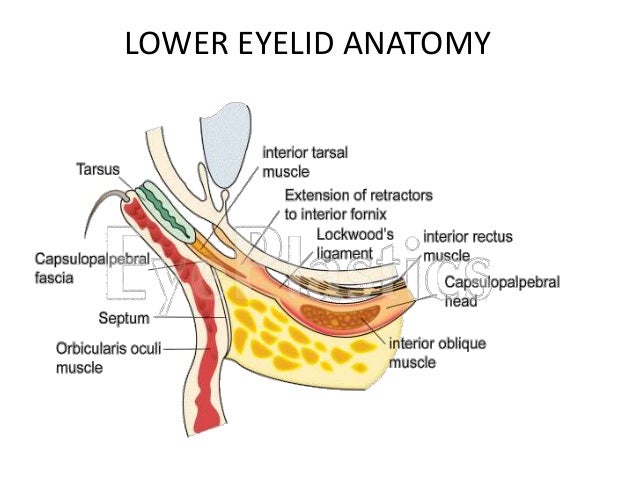
The lower eyelid is a deceptively thin structure. It looks like a simple flap of skin on the face, but underneath you are dealing with multiple layered tissues, small muscles, ligaments, and vascular networks that do not forgive sloppy technique. I have seen more complications from lower eyelid procedures than almost anything else, and most of them came down to one thing: not understanding the Anatomy Of The Lower Eyelid well enough before making the first incision. Starting from the outside moving inward, the skin of the lower lid is the thinnest on the entire body, averaging about 0.5 millimeters. Right beneath that sits the orbicularis oculi muscle, which has a pretarsal portion, a preseptal portion, and a preseptal portion that blends into the orbital component. Many people think these three parts are separate. They are not. They are continuous, and understanding how they overlap matters more than memorizing their names. Beneath the muscle is the orbital septum, a fibrous membrane that acts as a barrier between the eyelid tissues and the orbit itself. When you see fat herniation under the eyes, that is usually the septum weakening or tearing, allowing orbital fat to push forward. Behind the septum lie the three main orbital fat pads: medial, central, and lateral. These are not random blobs of tissue. Each pad is enclosed in its own capsule and sits in a specific compartment, and each one drains into a distinct venous system.
The tarsal plate is the rigid structural element of the eyelid. In the lower lid it is roughly 4 millimeters wide and extends from the medial canthus to the lateral canthus. Directly beneath the tarsal plate is the conjunctiva, a mucous membrane that lines the inner surface and reflects onto the globe as the bulbar conjunctiva. The tear meniscus sits right at the junction between the tarsal plate and the eyelash margin, and problems there often get blamed on dry eye when the actual issue is lid malposition.
A Practical Walkthrough of Lower Eyelid Surgery
I work mostly in oculoplastic surgery, and lower blepharoplasty is where I spend most of my time. The standard transconjunctival approach for lower lid fat repositioning or removal gives you direct access to the orbital fat pads without any external incision. Here is how it typically goes. You start with the patient sitting upright so you can assess lid position, fat prominence, and skin quality under gravitational influence. Marking is done with the patient in this position because things shift when they lie down. Then you administer local anesthetic with epinephrine, usually 1 percent lidocaine with 1:100,000 epinephrine, and wait five to seven minutes for the vasoconstriction to take effect before making any cuts. The transconjunctival incision is placed about 2 millimeters below the inferior border of the tarsal plate. You go through the conjunctiva and the lower head of the orbicularis muscle, then dissect bluntly in the subperiosteal plane to reach the orbital rim. This is where your knowledge of the Anatomy Of The Lower Eyelid becomes critical because you are working blind in a very small space. The periorbita is thin and tears easily. Once you open the periorbita over the fat pad, you can assess whether to excise, reposition, or leave the fat alone. Most modern surgeons favor repositioning fat into the tear trough defect rather than simply removing it, because removal creates hollowing that ages the face further.
Get the Full Details
The lateral canthal tendon is the anchor point for lower lid stability. If you are doing a lower lid lift or canthopexy, you need to access the inferior crus of the lateral canthal tendon, which inserts onto the inner surface of the lateral orbital rim about 2 millimeters above and 2 millimeters behind the lateral orbital tubercle. I have lost count of the number of times I have seen this landmark missed during surgery, leading to recurrent ectropion or lid laxity down the line.
A Specific Problem I Encountered
About three years ago, I had a patient who presented for a revision lower blepharoplasty after a previous surgeon had removed too much medial fat. The result was a significant hollow deformity in the tear trough area, but what made it worse was that the medial fat pad had actually atrophied further over time, creating a cascading that was harder to correct than the original problem. I solved it by harvesting autologous fat from the abdomen using a micro-cannula technique, processing it through low-speed centrifugation at 3000 rpm for three minutes, and injecting it in serial fanning passes along the subperiosteal and supraperiosteal planes. It took about forty-five minutes of additional operative time, and the correction held well over the next eighteen months. But it was a reminder that the lower eyelid has very limited reserve when tissue is removed, and the Anatomy Of The Lower Eyelid demands that you preserve more than you take out. The biggest mistake I see is treating the lower eyelid as a single unit. It is not. The medial third, central third, and lateral third each behave differently and respond differently to surgical manipulation. The medial third is supported by the medial canthal tendon and the capsulopalpebral fascia. The central third is where the fat pads live and where most complications occur. The lateral third is where lateral canthal support determines long-term lid position. Another counter-intuitive point is that more fat removal does not equal a better result. In fact, aggressive fat excision is one of the leading causes of late-stage lower lid retraction and scleral show. The fat pads serve as structural fillers that maintain the smooth contour between the lid and the cheek. Removing too much creates a hard edge between the eyelid and the infraorbital region, which looks artificial and ages the patient further.
A third pitfall involves the skin pinch. Some surgeons measure skin excision based on how much skin they think looks redundant when the patient is supine. But skin behavior changes dramatically between supine and upright positions. I typically have the patient sit up and lean forward, then evaluate skin redundancy under natural tension. This usually results in less skin being removed than initially estimated, which is exactly what you want because you cannot put skin back once it is gone.
Laser Resurfacing vs. Surgical Revision
There is a common assumption that laser resurfacing can fix lower eyelid concerns without surgery. For mild skin texture issues, fractional lasers or CO2 resurfacing can help, but they do not address fat herniation, muscle laxity, or canthal malposition. I had a patient who spent four thousand dollars on three rounds of laser treatment for what she thought was puffiness under her eyes. When she finally came to me, the puffiness was entirely due to fat protrusion through a weakened septum. Lasers were never going to fix that. She needed a transconjunctival blepharoplasty with fat repositioning, which I performed in about thirty minutes under local anesthesia. The recovery was two weeks of visible bruising and swelling, and the result was immediate and stable. The blood supply to the lower eyelid comes primarily from the angular artery medially and the facial artery laterally, with contributions from the infraorbital artery through the infraorbital foramen. The infraorbital nerve provides sensory innervation to the lower lid and upper lip area. During dissection, staying in the correct plane minimizes bleeding and reduces the risk of nerve injury. The zygomatic branch of the facial nerve runs just deep to the orbicularis muscle in the lateral third of the lid, and careless dissection in that area can cause temporary or permanent weakness of the lower lip depressors. One thing that is rarely emphasized in textbooks is the role of the inferior labial branch of the facial artery in lower lid perfusion. If you undermine too aggressively during a lower lid lift, you can compromise this supply and increase the risk of skin necrosis, particularly in patients who smoke or have peripheral vascular disease. I always ask about smoking history and stop nicotine use at least four weeks before any elective lower eyelid procedure. It is a small thing that prevents catastrophic complications.
What Happens When Everything Goes Wrong
Lower eyelid complications tend to cluster into three categories: ectropion, entropion, and scleral show. Ectropion is the most common and usually results from vertical lid shortening, excessive skin removal, or weakness of the lateral canthal tendon. Entropion is rarer in lower lid surgery but can occur if the pretarsal orbicularis is over-resected or if scarring pulls the lid margin inward. Scleral show is what happens when the lower lid sits too low, exposing the white of the eye, and it is often a combination of vertical shortening and fat over-resection. The worst case I dealt with involved a patient who developed a full-thickness lower lid notch after a revision procedure. The notch was about six millimeters wide at the margin and required a full-thickness wedge resection with reapproximation of the tarsus, conjunctiva, and orbicularis, plus a Tarsoconjunctival flap from the upper lid to resurface the defect. It was a long surgery, about two hours, and the final aesthetic result was acceptable but not perfect. She was unhappy with the residual notching even two years later. That case taught me something I carry into every lower lid procedure now: never attempt a complex revision on a lid that has already been operated on without a very clear plan and conservative tissue handling.
A Note on Non-Surgical Options
Filler injections in the tear trough area have become extremely popular, and they can work well for the right candidate. Hyaluronic acid fillers placed in the subperiosteal plane along the infraorbital rim can camouflage mild fat herniation and improve the lid-cheek junction. But filler is not a substitute for understanding the Anatomy Of The Lower Eyelid. Placing filler too superficially leads to the Tyndall effect, where the area looks blue under the thin skin. Injecting into the wrong plane can cause vascular occlusion, which in rare cases can lead to blindness. I have seen both complications, and neither is something you recover from easily. Botox in the lower lid is another option some patients pursue, but it carries its own risks. Paralyzing the pretarsal orbicularis can cause temporary lid drooping and worsen tearing because the lacrimal pump mechanism depends on orbicularis function. I generally avoid lower lid Botox unless there is a very specific indication, and even then I use minimal doses of two to four units spread across multiple injection points. The lower eyelid remains one of the most technically demanding areas in facial surgery because it combines aesthetic significance with functional importance. Every millimeter of tissue you move matters, and every structure you disrupt has downstream consequences. Good outcomes come from careful preoperative planning, respect for the underlying anatomy, and a willingness to do less rather than more when the situation is uncertain.