Building A Respiratory System Review Sheet That Actually Works
I spent three years teaching A&P at a community college before moving into clinical documentation, and I can tell you that most students' respiratory system review sheets are garbage. They copy Wikipedia entries, highlight everything, and then freeze when they see a question about the bohr effect on an exam. The ones who pass are the ones who build sheets that mirror how the material actually gets tested. Here's the structure I use. Start with the anatomical landmarks, then layer in physiology, then add the clinical correlations. Don't do it backwards. Students who start with diseases like COPD before understanding normal ventilation mechanics end up confused about whether symptoms come from the disease or from their own misunderstanding of baseline function.
Anatomy Of The Respiratory System Review Sheet Structure
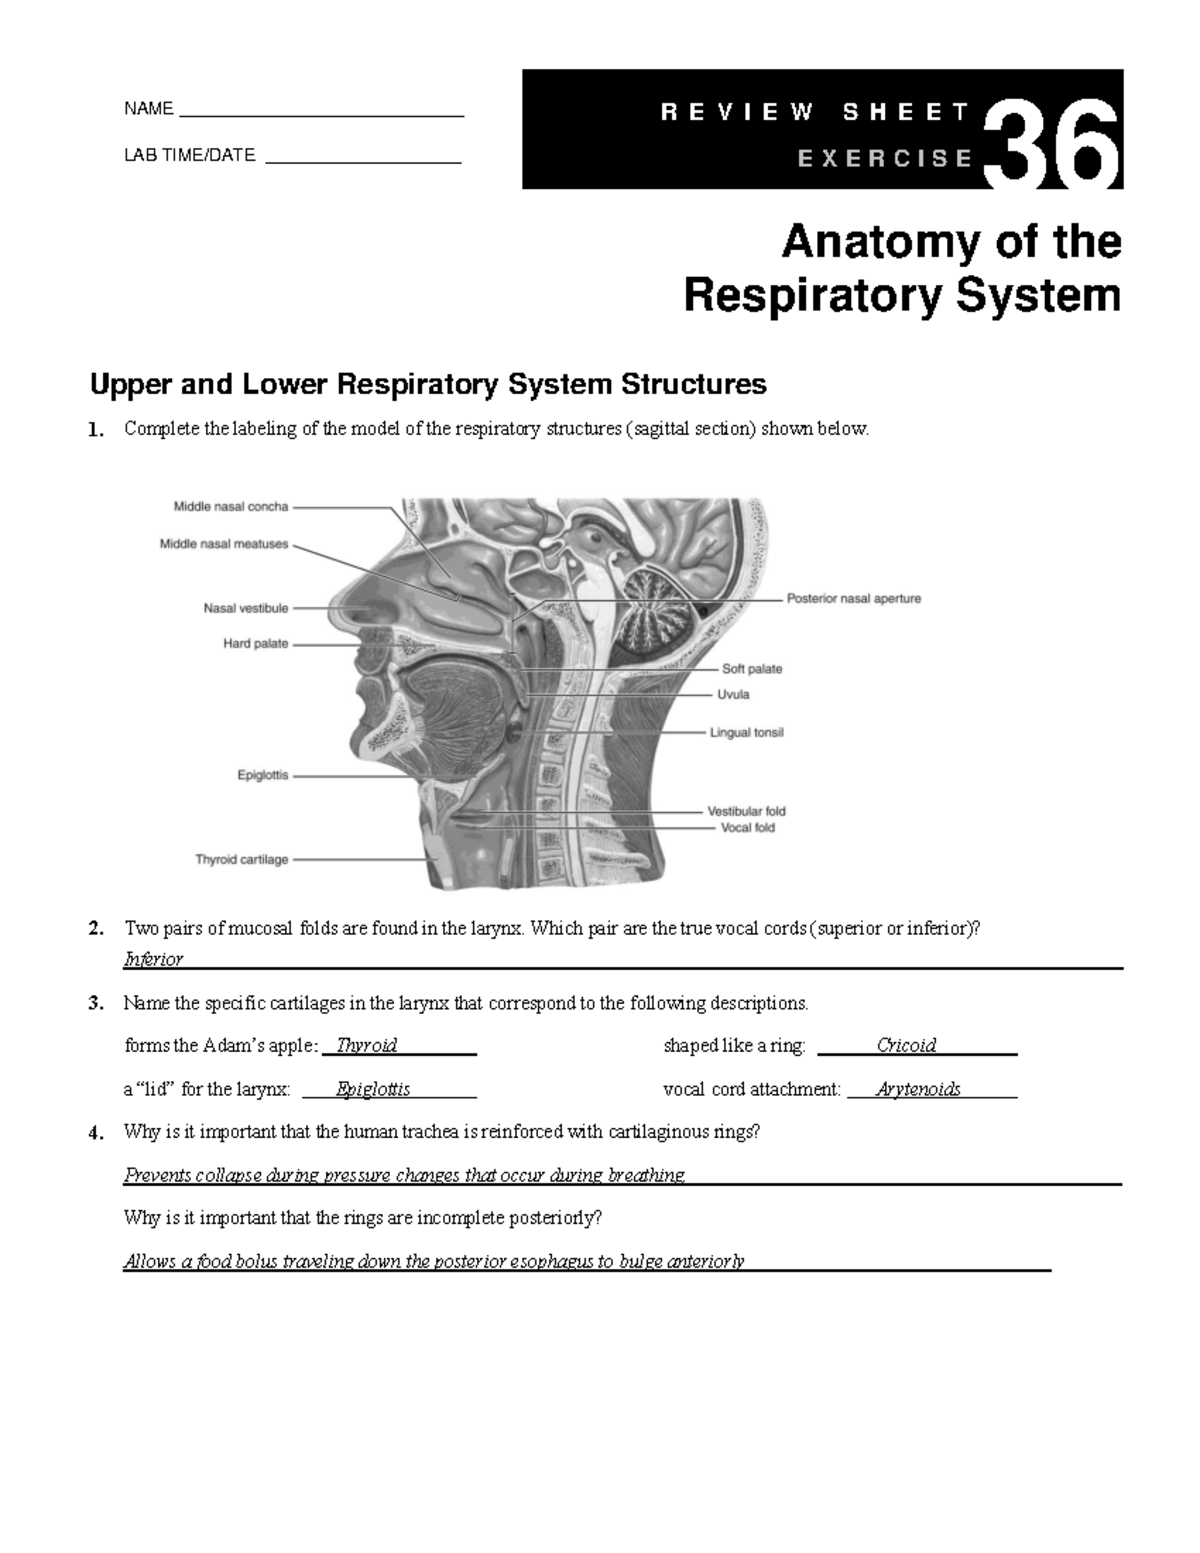
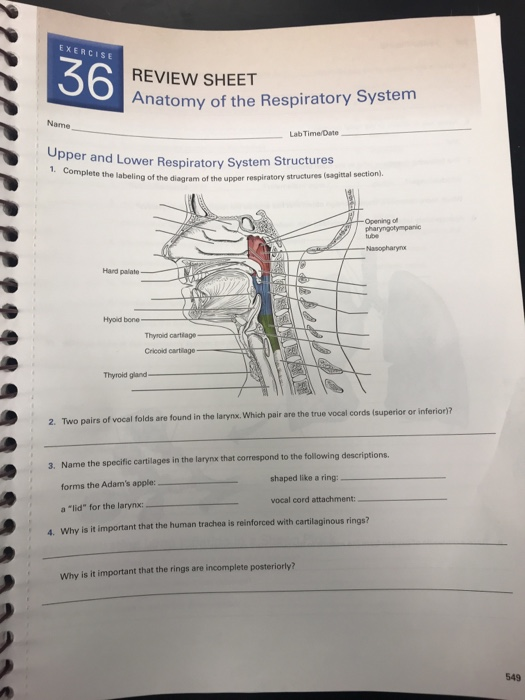
Your first section should be the conducting zone versus the respiratory zone breakdown. This isn't just memorization - it's the framework everything else hangs on. The conducting zone includes the nasal cavity, pharynx, larynx, trachea, bronchi, and bronchioles down to about one millimeter. The respiratory zone starts at the respiratory bronchioles and goes through alveolar ducts to alveoli. If you mix these up on an exam, you'll lose points on questions about gas exchange surface area. The pharynx triad - nasopharynx, oropharynx, laryngopharynx - needs exact boundaries. I had a student once who couldn't distinguish where the nasopharynx ends because her sheet just said "behind the nose." That's not precise enough. The nasopharynx extends from the skull base to the soft palate, roughly the level of C1 to C2. The oropharynx runs from the soft palate to the epiglottis, and the laryngopharynx sits below that down to the esophageal inlet at C6. Write those vertebral levels. They show up on practical exams. The larynx cartilages are another minefield. Thyroid, cricoid, and the three paired cartilages - arytenoid, corniculate, cuneiform. The thyroid cartilage forms the anterior prominence, that's the Adam's apple. The cricoid is the complete ring below it, the only complete cartilaginous ring in the airway. If you're doing intubation or tracheostomy, that cricoid landmark matters. I've seen students lose points for calling it the "cricoid cartilage" without specifying it's inferior to the thyroid, which makes you sound like you're guessing.
Pulmonary Physiology - The Parts People Skip
Volumes and capacities. Tidal volume, inspiratory reserve volume, expiratory reserve volume, residual volume. Total lung capacity equals all four added together. Vital capacity is everything except residual. Students memorize the formulas but can't draw the spirogram. Your review sheet should have a labeled spirogram with each volume annotated. I always include a note about how residual volume prevents alveolar collapse - without it, you'd have to fully exhale to zero, which is physiologically impossible and would cause lung tissue to stick together. Mechanics of breathing. Diaphragm contraction flattens, external intercostals lift the rib cage, intrathoracic pressure drops, air flows in. Exhalation at rest is passive - elastic recoil does the work. Forced exhalation recruits abdominal muscles and internal intercostals. Write that distinction. Exam questions love to trick you into saying exhalation is always active. The bohr effect and haldane effect belong in the gas transport section. Increased CO2 and decreased pH shift the oxygen dissociation curve right, unloading more oxygen to tissues. That's the bohr effect. The haldane effect is the reverse - oxygenated hemoglobin carries less CO2, facilitating CO2 unloading in the lungs. I include both on my sheets with a clinical example: why fever and exercise increase oxygen delivery. The elevated temperature and acidity at active tissues trigger the bohr effect, and that's not theoretical - it's why you gasp harder during a workout.
Get the Full Details

Clinical Correlations Worth Including
Pneumothorax. Air in the pleural space eliminates the negative pressure, the lung collapses via elastic recoil, and you get diminished breath sounds on the affected side. Tension pneumothorax shifts the mediastinum and compresses the vena cava, causing hypotension. That's the emergency version. I had a trauma patient once where the resident missed the unilateral absent breath sounds because they were distracted by the obvious chest wall trauma. The sheet should have a note about checking posterior lung fields too - anterior-only auscultation misses lower lobe pathology. COPD classification. Chronic bronchitis is productive cough for three months in two consecutive years. Emphysema is alveolar wall destruction with loss of elastic recoil. They often coexist but the physiology differs. Bronchitis creates mucus plugging and ventilation-perfusion mismatch. Emphysema creates air trapping and reduced surface area for gas exchange. Your review sheet should separate these mechanisms, not lump them under one heading. Asthma pathophysiology. Bronchial hyperresponsiveness, smooth muscle contraction, mucosal edema, mucus production. The airway narrowing is reversible, unlike COPD. Peak flow measurements track severity. I include a note about status asthmaticus - that's the non-responsive emergency where standard bronchodilators fail and you need systemic steroids and possibly intubation. Students who only memorize "wheezing and shortness of breath" miss the clinical urgency.
Gas Exchange Mechanics - The Advanced Stuff
Poiseuille's law applies to airflow resistance. Resistance is inversely proportional to the fourth power of the radius. Halve the airway radius and resistance increases sixteenfold. That's why bronchoconstriction in asthma is so dangerous - small changes in diameter create massive resistance increases. Include this calculation on your sheet. It explains why inhalers work the way they do and why airway diameter is the primary determinant of resistance in healthy lungs. The alveolar gas equation. PAO2 equals FiO2 times atmospheric pressure minus arterial CO2 divided by the respiratory quotient. At sea level breathing room air, that gives you an alveolar oxygen pressure around 100 mmHg. The A-a gradient - alveolar minus arterial - should be less than ten to twenty depending on age. An elevated gradient points to V/Q mismatch, shunt, or diffusion impairment. This is advanced material but it separates students who understand gas exchange from those who just memorized numbers. Surfactant. Type II alveolar cells produce it. It reduces surface tension, prevents alveolar collapse, and increases lung compliance. Without it, you'd need dramatically higher transpulmonary pressures to keep alveoli open. Neonatal respiratory distress syndrome comes from surfactant deficiency. I include a note about how premature infants benefit from exogenous surfactant administration and positive pressure ventilation. That connection between basic science and clinical treatment shows up on case-based exams.
How I Format My Review Sheets For Retention
I use two columns. Left side has structures and definitions. Right side has functions and clinical significance. The visual separation forces you to connect anatomy to physiology instead of treating them as independent facts. I also include a small diagram section - lung lobes with bronchopulmonary segments, the diaphragm attachment points, the larynx in sagittal view. Drawing them yourself beats copying anyone else's. Color coding helps. Red for oxygenated blood paths, blue for deoxygenated. Yellow highlights for high-yield exam facts like the cricoid being the only complete ring. I keep marginal notes about common mistakes I see students make - things like confusing the right and left main bronchus angles, or thinking the trachea bifurcates at the sternal angle when it's actually at T4-T5. The sheet should fit on two pages maximum. If it's longer, you're including noise. Every line should earn its place. I strip out anything I can answer without looking - things like "the trachea has C-shaped cartilage rings" unless there's a specific reason to include it, like knowing the esophagus sits posterior to the trachea and can be compressed by a goiter.

Resources And References
OpenStax Anatomy and Physiology has solid respiratory chapters with free access. LabCE's respiratory system module includes interactive quizzes that test the same material differently than your textbook. I also recommend reading through the American Thoracic Society patient education materials - they're written for clinicians but the physiology explanations are accurate and sometimes clearer than what textbooks produce. For the review sheet itself, I suggest building it progressively. Start with the anatomical framework, add physiology as you understand it, then insert clinical correlations once you've completed the pathophysiology units. Trying to write a comprehensive sheet in one sitting usually produces something disorganized and incomplete. The version you build over weeks of study will serve you better on exam day. I keep a running list of questions I get wrong during practice quizzes and add those to the sheet with corrections. That targeted approach - focusing on your actual weaknesses rather than reinforcing what you already know - is faster and more effective than re-reading highlighted textbook passages. Your review sheet should evolve as your understanding deepens, not stay static after the first draft.