Shoulder Anatomy Breakdown
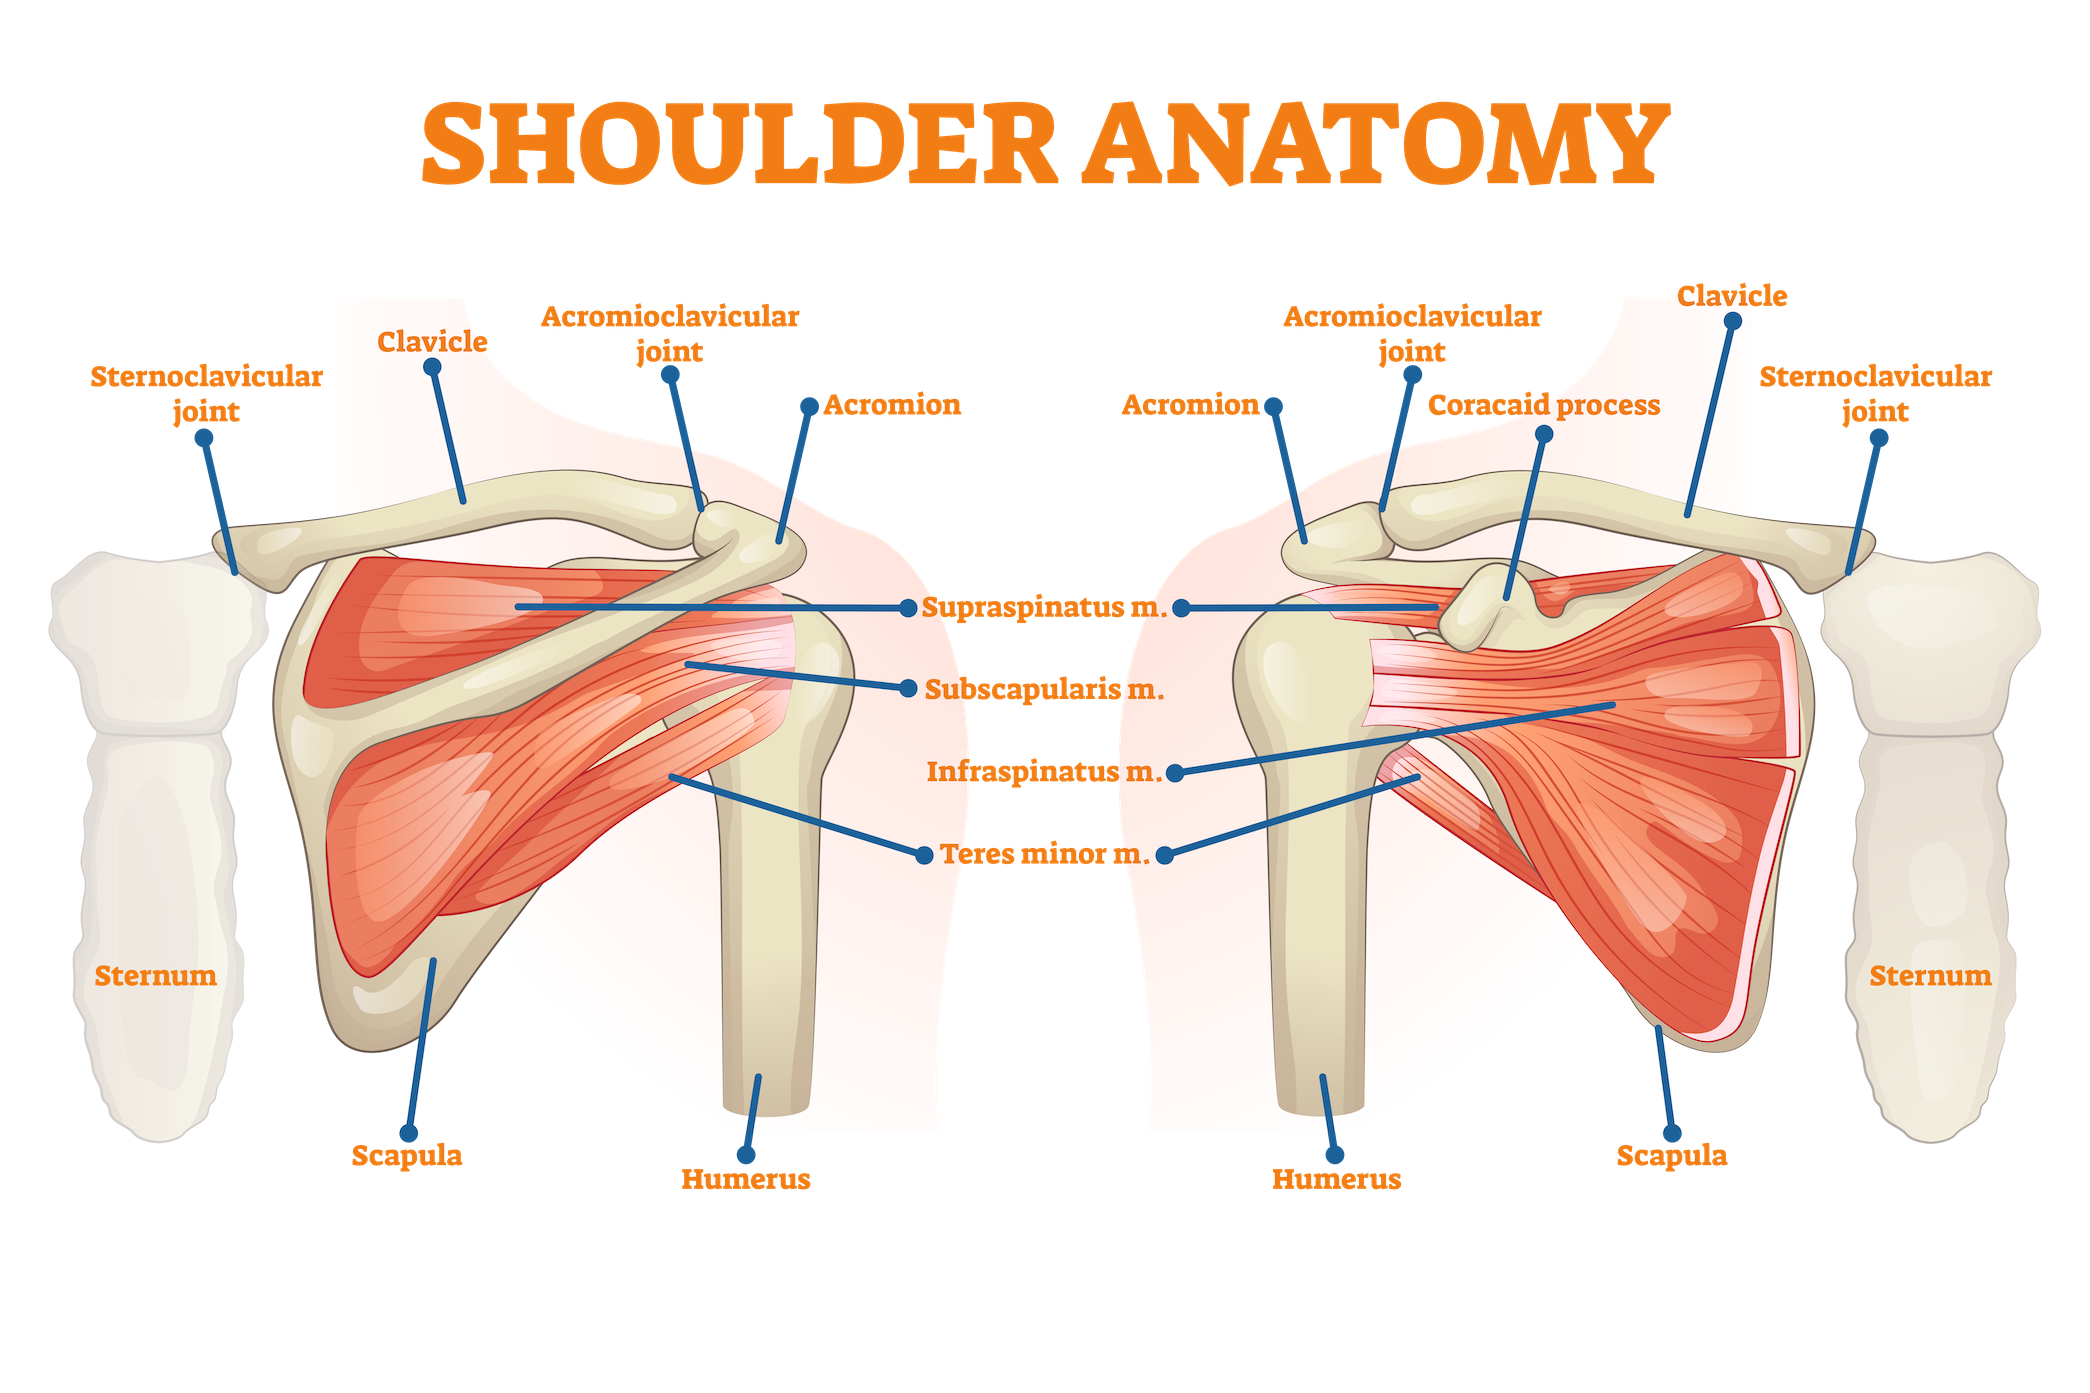
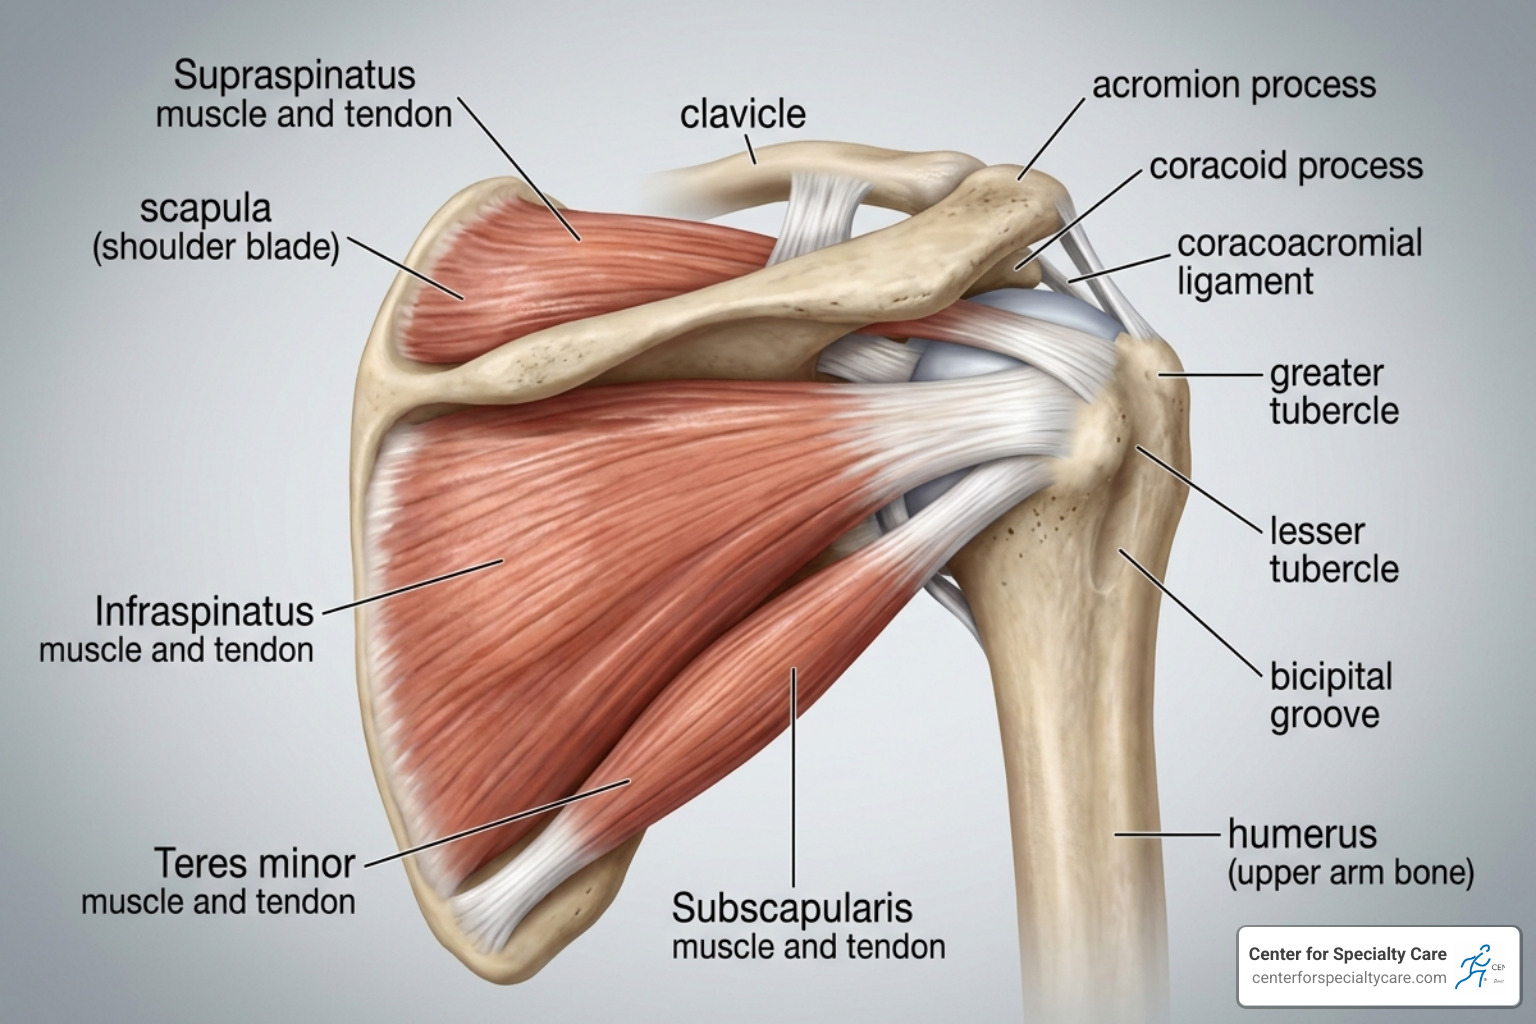
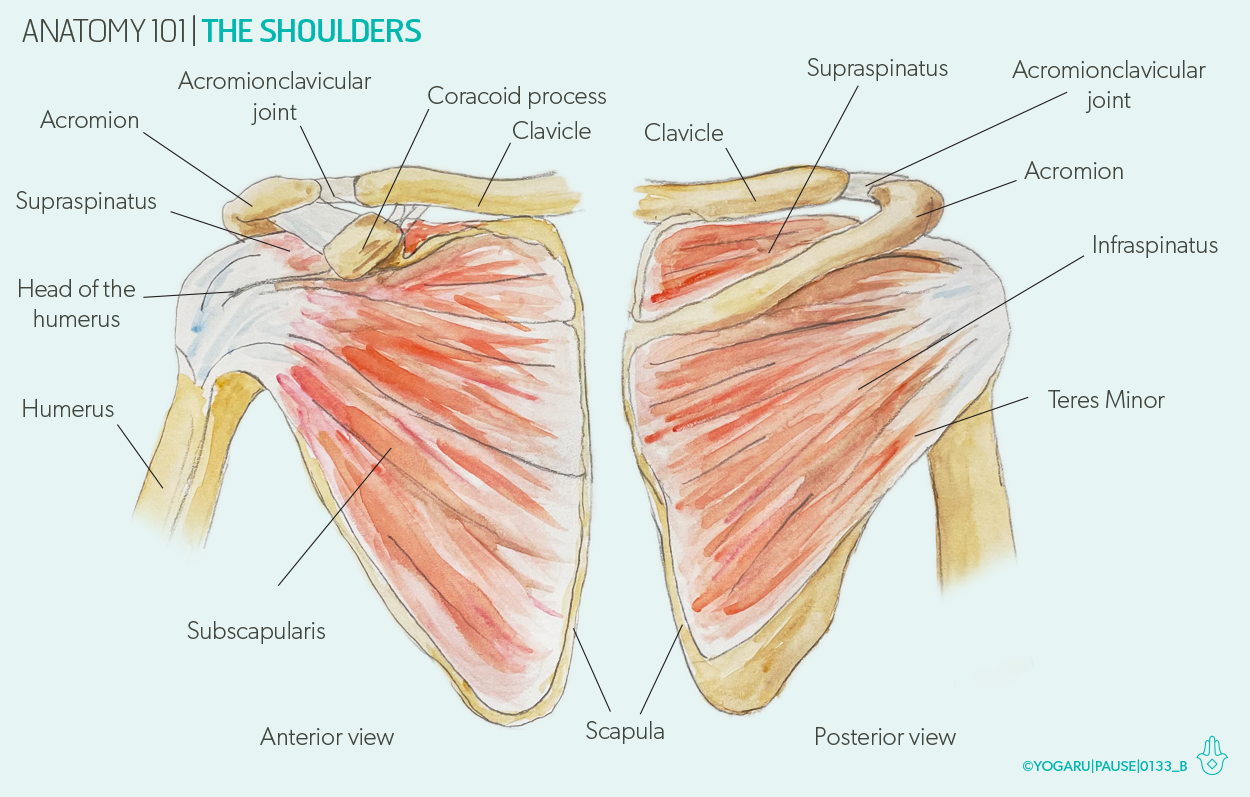
The right shoulder is one of the most complex joints in the human body, and honestly, it's easy to overcomplicate when you're studying it. Most people focus on the ball-and-socket of the glenohumeral joint, but that's only part of the picture. The shoulder girdle actually involves four joints working together: the glenohumeral joint, acromioclavicular joint, sternoclavicular joint, and scapulothoracic articulation. When any one of these moves incorrectly, the whole chain takes a hit. I've spent years working through cadaver dissections and clinical cases, and the thing most people get wrong about the rotator cuff is assuming it's primarily a shoulder stabilizer. It's not. The rotator cuff's main job is depressing the humeral head during arm elevation. Without that downward force, the deltoid would simply drive the humeral head upward into the acromion every time you lifted your arm. I saw this firsthand when a patient with a massive supraspinatus tear could still abduct to 90 degrees but couldn't raise their arm beyond that point due to impingement mechanics. Simple enough once you understand the force couple. The deltoid muscle itself has three distinct heads—anterior, middle, and posterior—each with different fiber orientations and functions. The anterior deltoid originates from the lateral third of the clavicle and inserts on the deltoid tuberosity of the humerus. It handles flexion and internal rotation. The middle (lateral) head originates from the acromion and handles abduction, especially from 15 to 90 degrees. The posterior head originates from the spine of the scapula and handles extension and external rotation. All three converge on the same insertion point, which is why shoulder pain often refers there regardless of which head is the culprit.
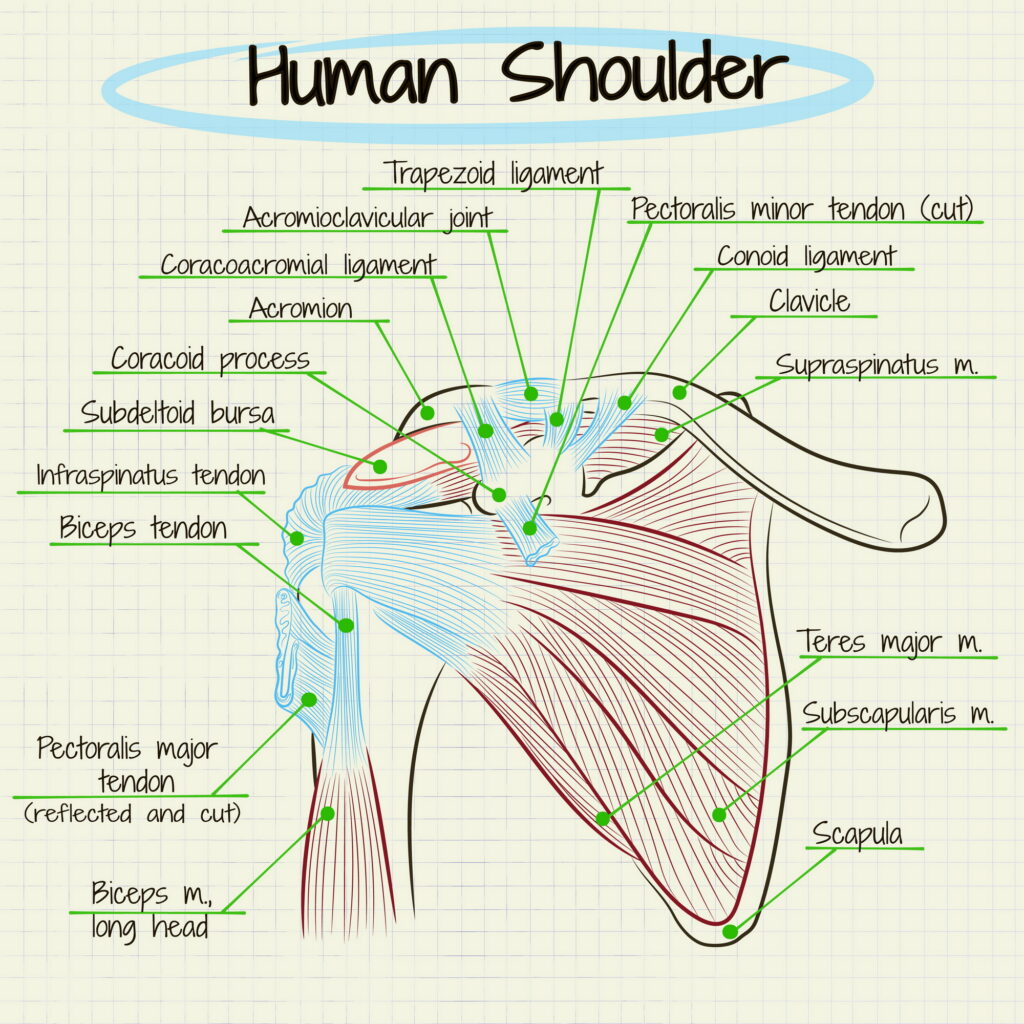
Beneath the deltoid and superficial to the glenohumeral joint sits the subacromial-subdeltoid bursa. This fluid-filled sac reduces friction between the deltoid above and the rotator cuff tendons below. When it becomes inflamed, you get what's clinically called subacromial bursitis, and it mimics rotator cuff pathology almost identically. I've lost count of the number of cases where imaging showed bursitis but everyone assumed it was a tendon tear. The difference usually comes down to response to treatment: bursitis responds to rest and NSAIDs within two weeks, while a full-thickness tear doesn't. The bony anatomy deserves more attention than it gets. The humeral head is roughly two-thirds the size of the glenoid fossa, which means the shoulder sacrifices stability for range of motion. The glenoid labrum, a ring of fibrocartilage, deepens the socket by about 50 percent. Without it, the shoulder would dislocate with minimal movement. The labrum also serves as the attachment point for the long head of the biceps tendon superiorly and the glenohumeral ligaments inferiorly. A SLAP tear—superior labrum anterior to posterior—is one of the most common injuries in overhead athletes, and it's notoriously difficult to diagnose without arthroscopy. Nerve supply to the shoulder region comes from multiple sources. The axillary nerve (C5-C6) wraps around the surgical neck of the humerus and innervates the deltoid and teres minor. This is why fractures of the surgical neck frequently cause axillary nerve damage, resulting in weakness of abduction and a sensory deficit over the lateral shoulder. The suprascapular nerve (C5-C6) passes through the suprascapular notch and innervates the supraspinatus and infraspinatus. A entrapment here can happen from ganglion cysts at the transverse scapular ligament, and it produces a very specific pattern of weakness that doesn't match any single root.
Blood supply to the shoulder joint is surprisingly rich. The circumflex humeral arteries (anterior and posterior) form an anastomotic ring around the surgical neck, which is why isolated surgical neck fractures rarely cause avascular necrosis of the humeral head. That preservation of blood supply matters more than most textbooks suggest when you're evaluating treatment options for proximal humerus fractures.
Get the Full Details
Practical Assessment Approach
When I'm evaluating shoulder anatomy clinically, I start with the Yergason's test for biceps pathology before moving to the shoulder itself. The biceps tendon runs through the intertubercular groove and stabilizes the humeral head. If it's unstable or inflamed, everything else becomes harder to assess accurately. I then check Neer and Hawkins-Kennedy impingement signs, followed by the empty can test for supraspinatus integrity. The drop arm test is critical for identifying full-thickness tears—patients who can't slowly lower their arm from abduction are showing a clear mechanical failure. MRI interpretation of the shoulder has its own set of pitfalls. Grade III signal within the supraspinatus tendon on MRI doesn't always mean a tear. Studies show that up to 40 percent of asymptomatic individuals over age 60 show some degree of rotator cuff pathology on MRI without any symptoms. Clinical correlation is essential. I once treated a patient for months thinking they had a massive rotator cuff tear based on MRI alone, only to discover the real issue was cervical radiculopathy from C5-C6. The MRI findings were real but incidental. The scapular dyskinesis assessment is another area where beginners miss critical details. Watch the patient perform a full forward elevation. The scapula should upwardly rotate, posteriorly tilt, and externally rotate throughout the movement. Any winging, anterior tilting, or excessive upward translation suggests underlying dysfunction. I've seen this repeatedly in patients with no apparent shoulder pain who developed symptoms after correcting their scapular mechanics. The shoulder doesn't work in isolation, and the thoracic spine, core, and scapular stabilizers all contribute to shoulder health.
Common Mistakes In Study And Application
The biggest error I see students make is treating shoulder anatomy as a static memorization exercise rather than a dynamic system. You need to understand how the structures relate to each other during movement, not just their anatomical position in cadaveric dissection. The coracoacromial arch—formed by the coracoid process, acromion, and coracoacromial ligament—creates a rigid tunnel that the supraspinatus tendon passes through. During overhead motion, this space narrows by approximately 1.5 millimeters. In someone with pre-existing inflammation or bony spurs, that narrowing can be the difference between pain-free movement and chronic impingement syndrome. Another counter-intuitive point: the greater tuberosity of the humerus, where the supraspinatus, infraspinatus, and teres minor insert, is the most commonly fractured part of the proximal humerus. Not the surgical neck, not the anatomical neck. The greater tuberosity fracture occurs when the rotator cuff muscles contract forcefully against a resistance or when a fall lands on an adducted arm. The pull of the rotator cuff displaces the fragment, and without anatomical reduction, you get permanent weakness and limited external rotation. When learning the brachial plexus relationships to the shoulder, remember that the posterior cord gives rise to the radial nerve, axillary nerve, and upper and lower subscapular nerves, plus the thoracodorsal nerve. The axillary nerve is the most commonly injured nerve in shoulder dislocations, affecting roughly 40 percent of anterior dislocations. The posterior cord sits directly posterior to the axillary artery and behind the humeral head, making it vulnerable during posterior dislocations, which are less common but often missed on initial presentation.
I also want to address the limitations of surface anatomy landmarks for shoulder procedures. The deltoid deltopectoral approach uses the interval between the clavicular and acromial heads of the deltoid and the pectoralis major. This landmark approach works well in thin patients but becomes unreliable in obese individuals or those with significant muscle mass. In those cases, I've found that intraoperative nerve monitoring or ultrasound guidance significantly reduces the risk of axillary nerve injury, which can occur if dissection extends too far laterally. Finally, the anatomy textbooks don't always emphasize how much individual variation exists in shoulder musculature. The pectoralis major can have an anomalous sternal head insertion, the latissimus dorsi can fuse with the teres major in varying degrees, and the coracobrachialis can have an accessory head. These variations are clinically significant when you're planning surgical approaches or interpreting electrophysiological studies. Don't assume the textbook diagram represents the standard anatomical presentation you'll encounter in practice.