Understanding The Spine Without Overcomplicating It
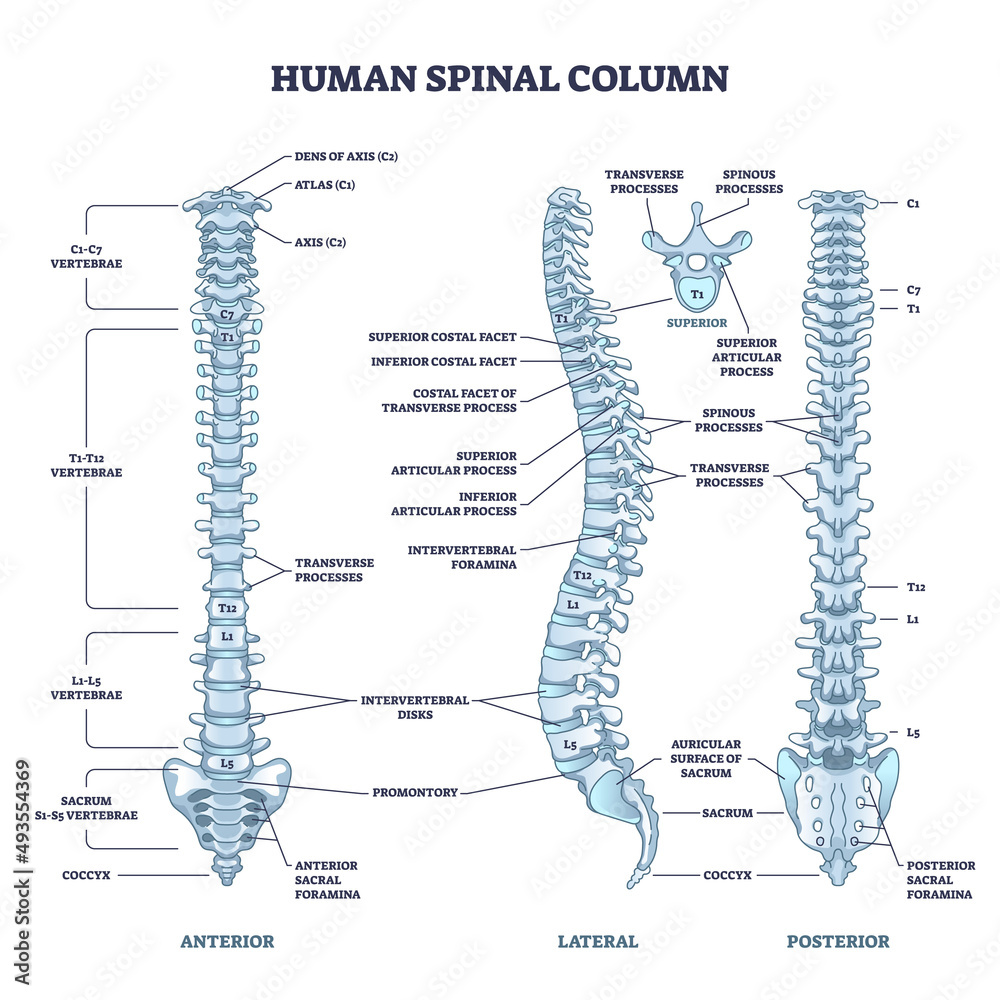
The spine is a stack of thirty-three vertebrae interspersed with intervertebral discs, and the spinal cord runs through the protective vertebral canal inside that stack. Most people online will give you a list of bones and call it a day. That works if you just need to pass a basic quiz. But if you actually need to understand how this system functions under real conditions — pain, imaging findings, clinical decision-making — you have to go a bit deeper than regiting C1 through L5. I spent years reading MRI reports and correlating them with actual patient presentations, and the gap between textbook anatomy and clinical reality is wider than most resources admit. A disc bulge on paper doesn't always equal pain. A clean scan doesn't guarantee someone is fine. Here is how I approach Anatomy Of The Spine And Spinal Cord when I need to actually use the information instead of just memorizing it.
Anatomy Of The Spinal Cord And Vertebral Column In Practice
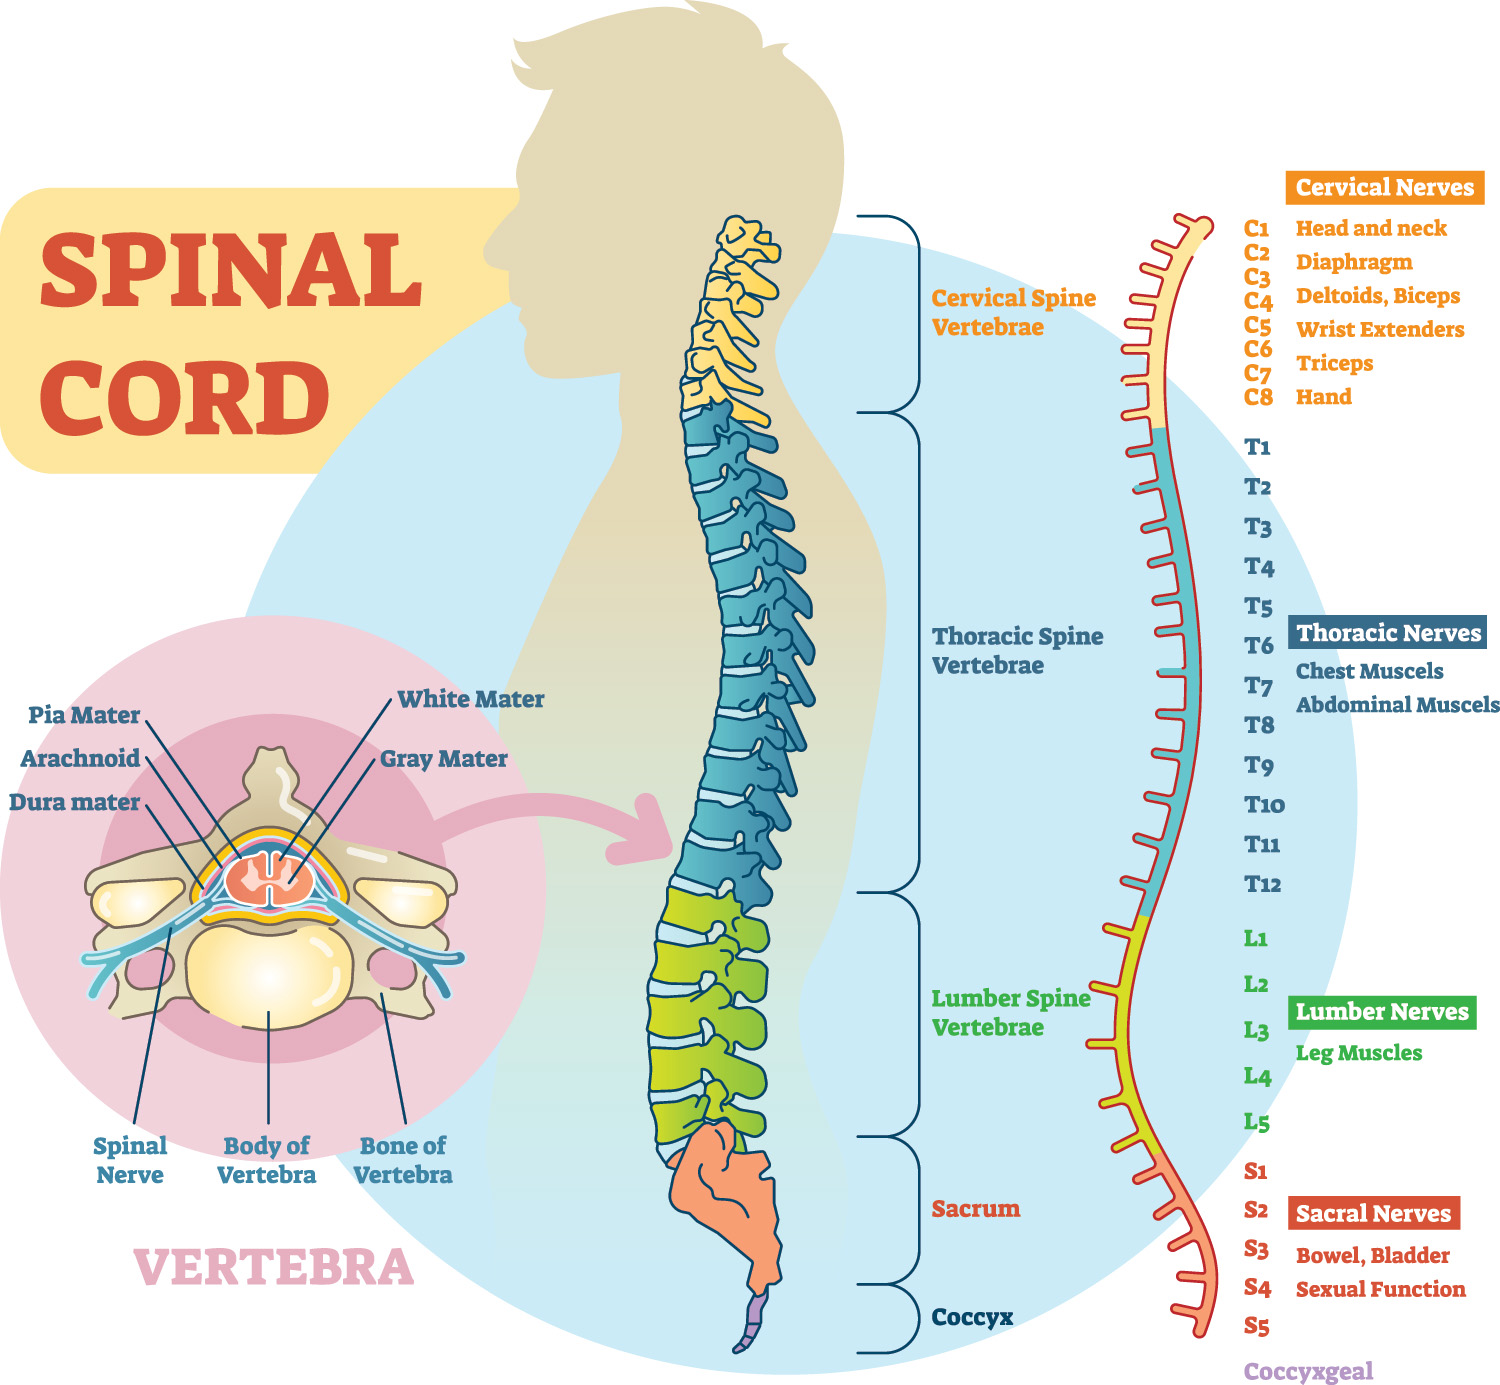
Let me start with something that tripped me up early and still catches people off guard: the spinal cord does not extend the full length of the vertebral column. In adults, the cord typically ends around the L1 to L2 vertebral level, forming what is called the conus medullaris. Below that, you have the cauda equina — a bundle of individual nerve roots dangling through the lumbar canal like a horse's tail, which is literally where the name comes from. This matters enormously for procedures and for interpreting pathology. When I was doing early consults, I once read a report that described a "central cord lesion at L3" and immediately flagged it as anatomically impossible. The cord simply isn't there at L3 in an adult. What was actually happening was compression of the cauda equina nerve roots, which can present with similar lower extremity symptoms but requires a completely different surgical approach and urgency assessment. Misidentifying the structure under compression changes everything about treatment timing and technique. The vertebral column itself has five regional curvatures. The cervical and lumbar regions are lordotic — curving inward. The thoracic and sacral regions are kyphotic — curving outward. These are not accidents. The S-shaped curve acts as a biological spring, absorbing mechanical load during standing and locomotion. When people lose their lumbar lordosis due to chronic muscle guarding or degenerative changes, they are essentially removing a key shock-absorption mechanism, and the adjacent segments take on extra stress. That is why you see accelerated disc degeneration two levels above or below a fusion site — the biomechanics shift entirely.
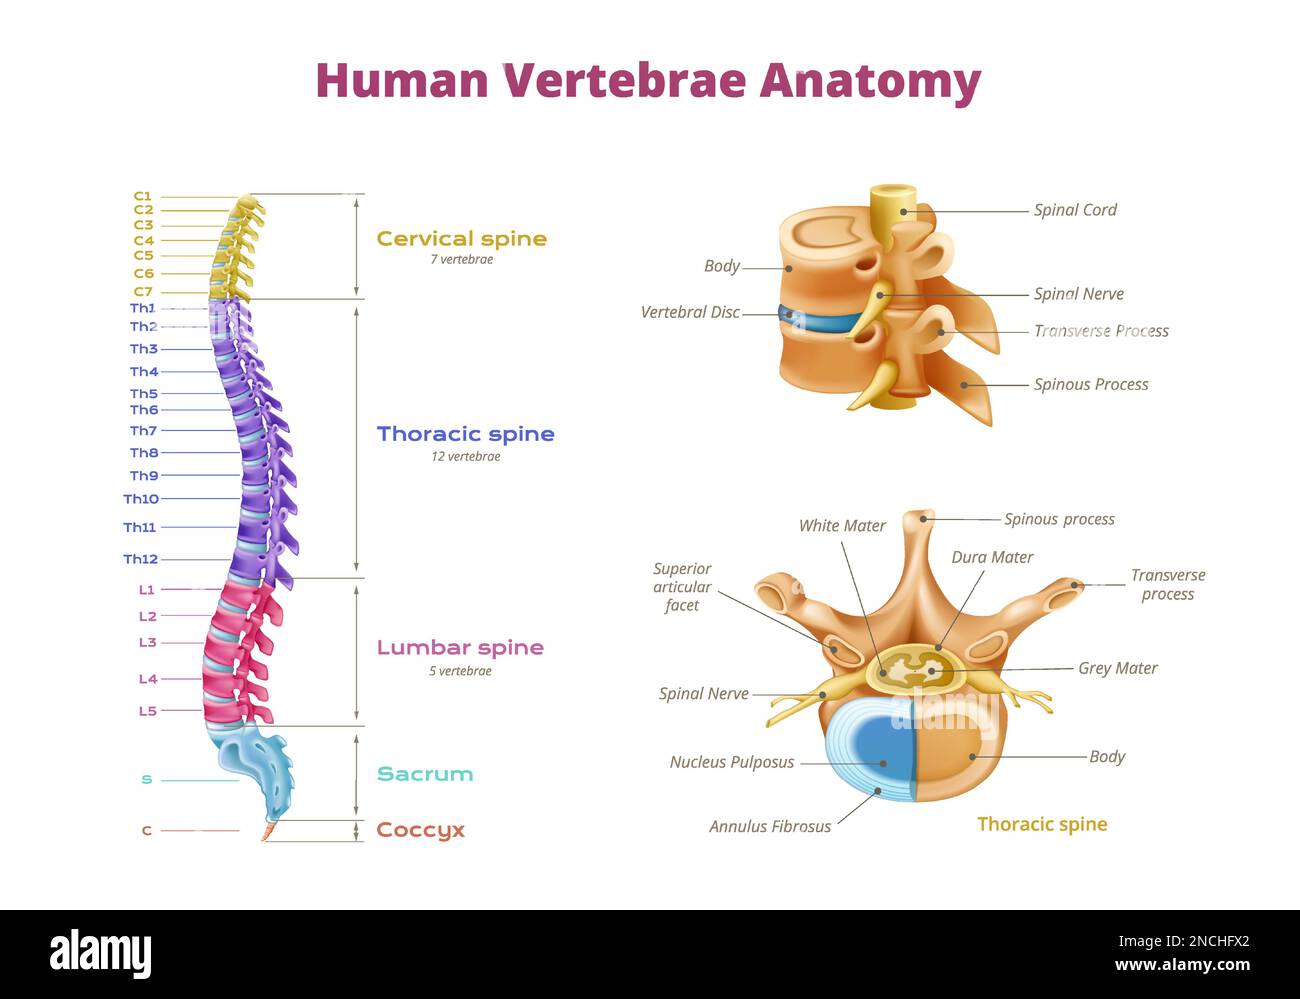
Each vertebra consists of a body anteriorly and a neural arch posteriorly. The body bears the compressive load. The neural arch protects the cord and forms the lateral boundaries of the intervertebral foramina — the openings where nerve roots exit. The size and shape of those foramina vary significantly by region. Cervical foramina are wider and more circular, which is why cervical radiculopathy often presents with more dramatic dermatomal symptoms. Lumbar foramina are taller and more oval, and they narrows significantly with extension and disc height loss. I have seen patients with moderate disc degeneration who are asymptomatic sitting down but develop severe leg pain the moment they stand upright or walk — the foramen closes down under load and the nerve root gets pinched. Here is a practical detail most guides skip: the epidural space is not a uniform tube. It is largest posteriorly and smallest laterally in the lumbar region. That asymmetry is exactly why a posterior midline approach for epidural anesthesia or lumbar puncture is standard — you are going through the path of least resistance. When I perform or review procedures, I always check whether the needle trajectory accounts for the patient's degree of scoliosis or prior surgery, because scar tissue alters the epidural space geometry enough to make a standard approach miss the target zone entirely.
Get the Full Details

Discs, Ligaments, And The Structures That Actually Fail
The intervertebral discs are fibrocartilaginous structures with an outer annulus fibrosus and an inner nucleus pulposus. The annulus contains roughly 60 percent water in a healthy young adult and drops to around 40 percent by age sixty. That dehydration is not just a number — it changes the disc's ability to distribute load evenly, which pushes more stress onto the annular fibers and accelerates fissuring. I have tracked patients whose disc degeneration progressed from grade 1 to grade 3 over roughly four years, and in almost every case, the initial trigger was a combination of sustained flexion loading and repeated microtrauma rather than a single acute injury. Three ligaments are clinically relevant here. The anterior longitudinal ligament runs along the anterior vertebral bodies and is broad and strong — it resists hyperextension. The posterior longitudinal ligament runs along the posterior bodies inside the canal and is narrower, especially in the lumbar spine where it occupies only the central third of the vertebral body width. That narrowing is significant because it leaves the lateral recesses relatively unprotected, which is why lateral disc herniations are common in the lumbar region and why the PLL does not prevent herniations the way some simplified diagrams suggest. The ligamentum flavum connects the laminae of adjacent vertebrae and is highly elastic. It helps maintain upright posture passively, but with age or repeated stretching, it can undergo hypertrophy and contribute to central canal stenosis independently of any disc disease. I encountered a case last year involving a patient with severe neurogenic claudication who had minimal disc herniation on MRI but significant ligamentum flavum hypertrophy. Standard treatment algorithms for lumbar stenosis focus heavily on discectomy, but in this case the bulk of the compression was posterior, not anterior. We adjusted the surgical plan to focus on laminectomy with flavectomy rather than a discectomy-first approach, and the clinical improvement was substantial. Recognizing which structure is the primary compressor rather than the secondary one is the difference between a good outcome and a revision surgery.
Neuroanatomy That Actually Determines Treatment
The spinal cord contains approximately 31 segments corresponding to the nerve root pairs. Cervical segments C1 through C8, thoracic T1 through T12, lumbar L1 through L5, sacral S1 through S5, and the coccygeal segment. Each segment gives rise to a pair of nerve roots that exit through the corresponding intervertebral foramen. A key anatomical detail: the cervical nerve roots exit ABOVE the corresponding vertebra, but below C7, the nerve roots exit BELOW the corresponding vertebra. So C8 exits between C7 and T1. This is a frequent source of error when correlating imaging levels with clinical symptoms. The spinothalamic tract carries pain and temperature sensation and crosses to the opposite side within one or two segments of entry. The dorsal column carries fine touch and proprioception and ascends ipsilaterally before crossing in the medulla. When you see a patient with a complete cord transection, you get loss of all sensation and motor function below the level. But with incomplete syndromes like central cord syndrome — often from hyperextension injuries in older patients with pre-existing stenosis — you get disproportionate upper extremity weakness compared to the lower extremities. This happens because the cervical tract organization places the arms medial and the legs lateral within the corticospinal tract, and central lesions hit the medial fibers first. I reviewed a case where a patient presented with bilateral hand weakness and preserved leg strength after a minor fall. Initial imaging showed no fracture, and the attending physician was leaning toward a peripheral neuropathy workup. But the segmental pattern — C6 through C8 bilaterally with relative sparing of L2 and below — pointed directly to a central cord syndrome from cord contusion at the cervical level. An MRI confirmed edema at C5-C6 without compression. The treatment was conservative with close monitoring rather than surgical decompression, and the patient recovered significantly over six weeks. Had we chased peripheral causes, we would have delayed the correct diagnosis and management by weeks.
Imaging And The Limits Of What You Can See
MRI is the gold standard for soft tissue evaluation of the spine. T1-weighted images show anatomy well with fat appearing bright and water dark. T2-weighted images highlight fluid and edema, making them essential for detecting disc pathology, cord signal changes, and nerve root compression. A normal disc is bright on T2 because of its high water content. A degenerated disc loses that brightness. But loss of disc height signal on MRI correlates only modestly with pain — some of my patients with frankly desiccated discs report no symptoms, while others with mild signal changes have debilitating pain. The imaging finds the anatomy, but it does not tell you which anatomical finding is the pain generator. CT myelography remains useful when MRI is contraindicated or when bony detail is critical. I rely on CT myelography when assessing patients with metallic implants that cause significant artifact on MRI, or when evaluating suspected bony stenosis from ligamentum flavum ossification. The tradeoff is radiation exposure and the need for lumbar puncture to inject contrast, so it is not a first-line tool. X-rays remain clinically indispensable for dynamic assessment. Flexion-extension views reveal instability that static MRI or CT will miss entirely. I once followed a patient with chronic neck pain and normal MRI findings. The flexion-extension X-rays showed 4mm of anterior translation at C5-C6, confirming segmental instability. The treatment plan shifted from conservative management to surgical stabilization, and the patient's symptoms improved markedly afterward. Static imaging alone would have left that instability undetected.

Common Clinical Scenarios And How To Approach Them
For lumbar disc herniation with radiculopathy, the majority of cases resolve without surgery within six to eight weeks. Conservative management includes activity modification, NSAIDs, and targeted physical therapy. Epidural steroid injections can provide shorter-term relief for severe radicular pain and may help patients engage more effectively in rehabilitation. Surgery becomes a consideration when there is progressive neurological deficit, cauda equina syndrome, or persistent disabling pain beyond the expected timeframe. The absolute indications for urgent surgical consultation are bowel or bladder dysfunction, saddle anesthesia, and progressive motor weakness — those are red flags that should not be managed conservatively. Lumbar spinal stenosis typically presents with neurogenic claudication — leg pain or heaviness that worsens with walking and standing and improves with sitting or forward flexion. The forward flexion opens the canal and foramina, reducing compression. I ask patients to describe whether they can ride a bicycle without symptoms but cannot walk block without stopping. That functional difference helps distinguish vascular claudication from neurogenic claudication, though both can coexist in older patients with peripheral artery disease and spinal stenosis simultaneously. Cervical spondylotic myelopathy is the most common cause of spinal cord dysfunction in adults over fifty. It develops from a combination of disc herniation, osteophyte formation, and ligamentum flavum hypertrophy converging to compress the cord. Early symptoms include hand clumsiness, gait imbalance, and hyperreflexia. By the time bladder dysfunction appears, the cord damage is often significant and irreversible. Early recognition through careful neurological examination and prompt MRI referral is critical. There is no consensus on a single optimal surgical approach — decompression alone versus decompression with fusion depends on cervical alignment, number of levels involved, and surgeon judgment.
What Textbooks Leave Out
Vertebral artery compromise during cervical manipulation is a rare but serious risk. The vertebral arteries course through the transverse foramina from C6 upward, but the anatomical relationship between the artery and the lateral mass varies considerably between individuals. Some people have the artery anterior to the mass at certain levels, which dramatically increases the risk of injury during aggressive manipulation. I have reviewed case reports where vertebral artery dissection led to posterior circulation stroke after what appeared to be routine spinal manipulation. The incidence is low, perhaps one in several hundred thousand manipulations, but the consequences are severe enough that screening for vascular anomalies and avoiding high-velocity techniques in at-risk patients is standard practice now. The sympathetic chain lies anterior to the vertebral bodies and can be affected by pathology that does not directly involve neural structures. A large anterior osteophyte from the cervical spine can irritate the sympathetic chain and produce symptoms that mimic cardiac or gastrointestinal pathology. I had a patient who presented with recurrent chest pain and negative cardiac workup. The final diagnosis was a massive C5-C6 osteophyte compressing the sympathetic ganglia. Treating the spine resolved the chest pain entirely. This is an uncommon presentation, but it illustrates why a thorough understanding of adjacent structure relationships matters in clinical practice. Blood supply to the spinal cord comes from three longitudinal arteries — one anterior and two posterior — reinforced by segmental radicular arteries that enter through the intervertebral foramina. The artery of Adamkiewicz, a major radicular artery that typically arises between T9 and L2 on the left side, supplies the anterior spinal cord in the thoracolumbar region. Surgical procedures in that zone carry a risk of ischemic cord injury if this artery is compromised. Preoperative vascular imaging is sometimes warranted before extensive spinal surgery in this region, particularly when vertebral artery variants or anomalous anatomy are suspected.
Understanding the spine requires moving beyond static anatomy into biomechanics, neurovascular relationships, and the gap between radiological findings and clinical symptoms. The structures are interdependent, and a problem in one component rarely stays isolated. I find that the most reliable approach is to start with the patient's symptoms, map them to anatomical structures, verify with appropriate imaging, and then reassess whether the identified pathology actually explains the full clinical picture. When it does not — and that happens more often than the literature suggests — you go back and look harder.