What You Actually Need To Know About Torso Structure
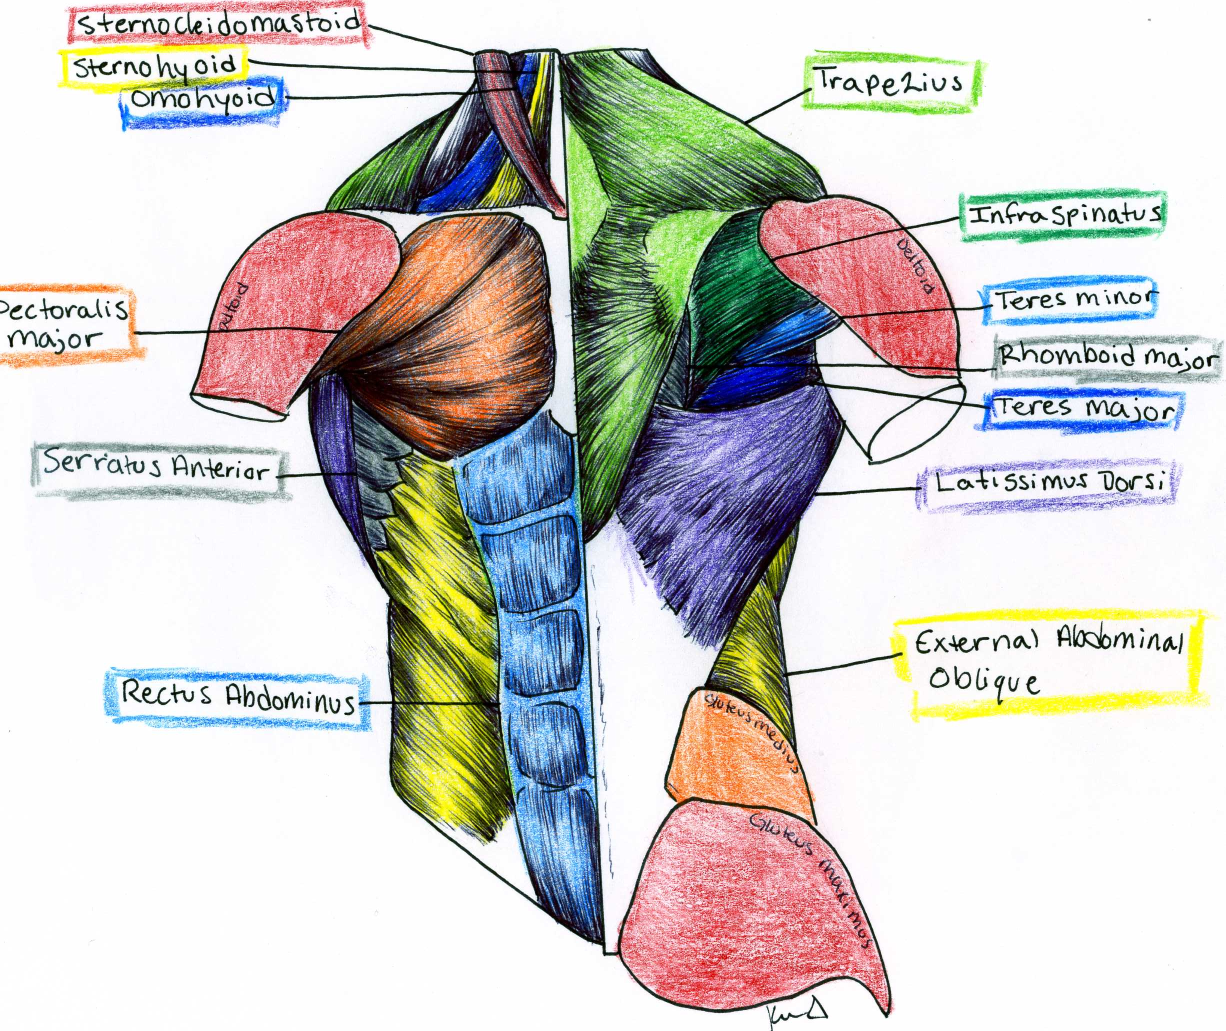
The torso isn't just a box with limbs attached. I spent three years in an art school figure drawing program before I stopped treating the ribcage and pelvis as separate objects and started seeing them as interlocking mechanical forms. Most beginners draw the ribs like a birdcage and the pelvis like a separate basin. That's wrong. They're connected by the lumbar spine, which has a forward curve that changes everything about how the torso sits on the hips. Here's the core geometry: two ovoids (ribcage and pelvis) connected by the spinal column, with the diaphragm acting as a functional boundary between them. The ribcage sits at roughly a 30-degree angle from horizontal when standing. The pelvis tilts about 45 degrees. This torsion between the two forms is what gives the torso its character in any pose. The serratus anterior muscle covers the lateral ribcage and attaches to the scapula. Most reference books show this as a separate "wing-like" structure. In practice, it's more like a series of fingers wrapping around the ribs. When someone rotates their shoulder forward, you see three to five distinct digitations become visible on the mid-axillary line. When they're relaxed, those flatten out almost completely.
I ran into a specific problem once while building a reference dataset for a medical visualization project. The standard anatomical illustrations showed the rectus abdominis as six distinct segments separated by tendinous intersections. Real cadaver dissection revealed something different. The intersections aren't consistent. Two-thirds of the population has three, but the positioning varies. In some specimens, the upper intersection sits at the xiphoid process level. In others, it's two centimeters lower. If you're building a 3D model and snapping vertices to textbook positions, your character will look uncanny because the proportions are slightly off. The workaround I used was to reference axial CT scans rather than illustrations. I imported DICOM data into Blender and used the built-in segmentation tools. This took longer upfront — about four hours to process one scan — but the resulting mesh had accurate internal proportions that no illustration could guarantee. For a single project, the time investment pays off. For routine work, I now keep a library of scan-based reference models organized by body type.
The Ribs And Their Connection Points
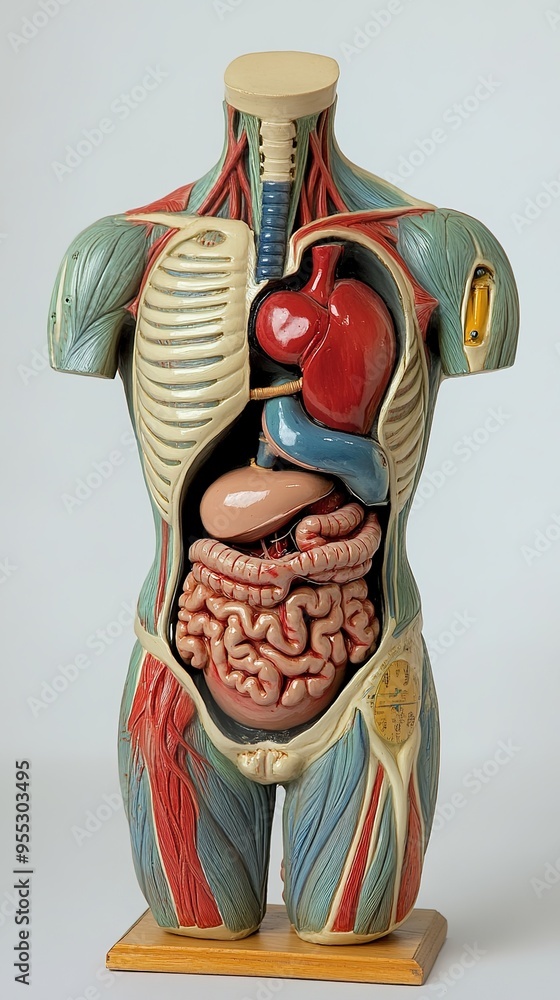
The thoracic cage has 12 pairs of ribs. Pairs one through seven attach directly to the sternum via costal cartilage. Pairs eight through ten connect indirectly through shared cartilage that merges with the seventh rib's attachment. Pairs eleven and twelve are floating ribs with no anterior attachment. This classification matters for construction because it determines how much lateral expansion is possible during inhalation. The sternum consists of three parts: the manubrium at the top, the body in the middle, and the xiphoid process at the bottom. The manubrium articulates with the clavicles and the first two pairs of ribs. The body receives ribs two through seven. The xiphoid is cartilaginous in young people and ossifies around age 40. When you're drawing surface anatomy, the xiphoid is often visible as a small projection in lean individuals, but it's frequently mispositioned in references. It sits at the level of the tenth thoracic vertebra, not at the bottom of the sternum as many illustrations show. The costal angle — where the inferior margins of the ribcage meet at the sternum — is typically 70 to 90 degrees in healthy adults. This angle increases in conditions like emphysema and decreases with obesity. For artistic reference, noting this angle gives you immediate information about the subject's body composition and posture without needing to measure anything.
Get the Full Details
I've seen too many 3D modelers treat the sternum as a flat plate. It's actually keel-shaped in cross-section, wider anteriorly and narrowing posteriorly toward the costal cartilages. This shape matters for UV mapping and collision detection in game engines. A flat sternum creates visual artifacts when lighting hits the chest from certain angles. The correct topology follows the keel curve, which means your edge loops should wrap around the sternum rather than running straight across.
Musculature That Actually Matters
The external oblique is the most superficial abdominal muscle. Its fibers run inferomedially — down and toward the midline. This direction is counter-intuitive because it means the muscle acts like it's pulling the ribcage toward the pelvis, not the other way around. When you flex your obliques against resistance, you're actually compressing the abdominal cavity and rotating the torso contralaterally. The fiber direction determines this action, and getting it wrong in a model makes the pose look mechanically impossible. The internal oblique lies deep to the external oblique with fibers running perpendicular — superomedially. This creates a crisscross pattern that provides torsional stability. In the upper abdomen, the internal oblique is absent on the anterior surface, replaced by aponeurotic tissue that becomes part of the rectus sheath. This anatomical variation is why the lateral abdominal wall looks thinner in some regions and thicker in others. The transversus abdominis is the deepest layer. Its fibers run horizontally around the abdomen. This muscle acts as a natural corset, increasing intra-abdominal pressure. When you bracing for impact or preparing to lift something heavy, this muscle activates first. In figure drawing, it's rarely visible on the surface except in very lean subjects, but understanding its position helps you construct the underlying form correctly before adding more superficial layers.
A common pitfall I encountered with a student working on a digital sculpt was the latissimus dorsi insertion. This muscle originates from the lower spine, iliac crest, and lower ribs, then inserts onto the humerus. The insertion point is often drawn too high in references, making the armpit area look structurally incorrect. The actual insertion is at the intertubercular groove of the humerus, which sits well below the axilla. When the arm is raised, the latissimus creates a prominent fold that extends from the posterior axillary fold toward the spine. Modeling this fold correctly requires understanding the muscle's tension path, not just its outline.

The Diaphragm As A Functional Divider
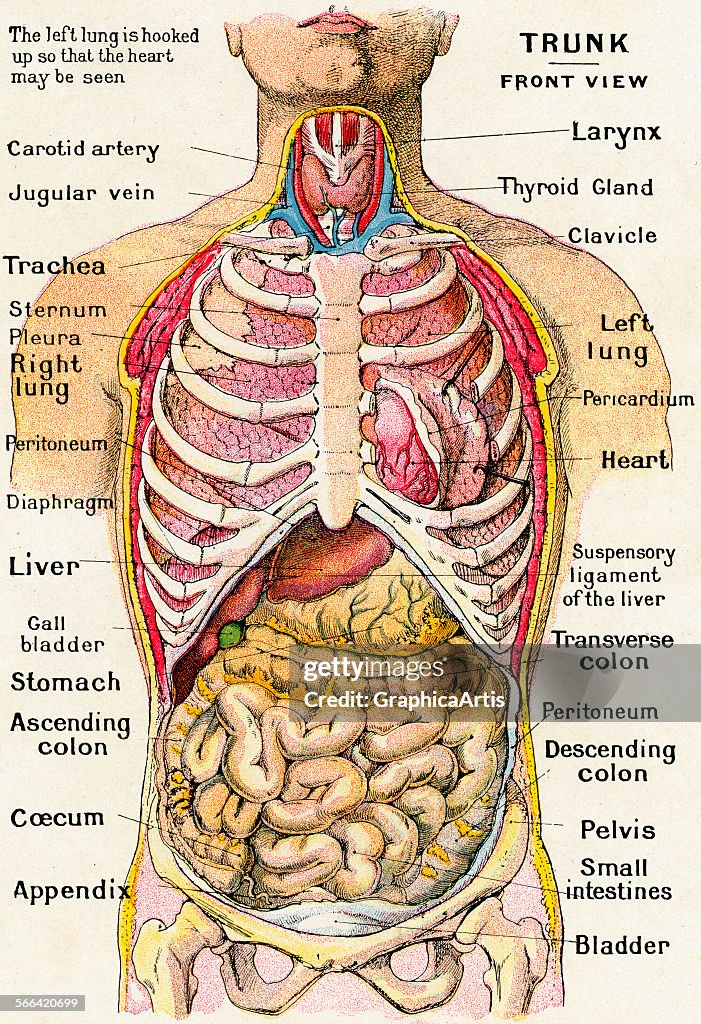
The diaphragm is a dome-shaped muscle that separates the thoracic cavity from the abdominal cavity. It has three major openings: the caval opening at T8, the esophageal hiatus at T10, and the aortic hiatus at T12. These vertebral levels are useful landmarks for understanding what structures pass between the cavities. For visual purposes, the diaphragm's position matters because it determines the lowest point of the ribcage's internal volume. When the diaphragm contracts during inhalation, it flattens and descends approximately 1.5 to 2 centimeters. This movement expands the thoracic cavity vertically. The costal diaphragm — the portion attached to the ribs — is the primary mover. The lumbar and sternal portions are smaller and serve mainly as attachment points for other structures. In anatomy visualization, the diaphragm is often omitted or shown incorrectly as a flat sheet. It's actually a three-cupped structure with the right cup higher than the left because of the liver's position beneath it. When you're creating cross-sectional views or cutaway models, this asymmetry should be preserved. Getting it wrong makes the liver appear to occupy space it shouldn't, which breaks the internal logic of the visualization.
I once worked on a project where the client wanted animated breathing cycles. The initial implementation used a simple scale transform on the ribcage mesh. This produced unnatural motion because the ribs don't just expand outward — they also rotate. The pump-handle movement of the upper ribs increases anteroposterior diameter. The bucket-handle movement of the lower ribs increases transverse diameter. Combining both movements required animating individual rib segments rather than the cage as a whole. The result looked more realistic but took significantly longer to rig and keyframe.
Surface Landmarks You Can Actually Feel
The xiphoid process is palpable in most people, though it's often missed because it's small and cartilaginous in younger adults. Place your fingers at the bottom of the sternum and press gently. You'll feel a small, firm projection. In lean individuals, it's clearly visible as a bump. In others, it's hidden beneath subcutaneous tissue. The costal margin — the inferior border of the ribcage — is formed by ribs seven through ten. This margin is palpable on both sides and creates a V-shape pointing toward the umbilicus. The angle of this V varies with body type. In athletic individuals with low body fat, the costal margin is sharply defined. In others, it's softened by subcutaneous fat and abdominal musculature. The midclavicular line is a vertical reference that runs through the nipple in males and the midpoint of the breast in females. It intersects the costal margin at the ninth rib. This landmark is useful for locating the liver edge and the gallbladder fossa. When palpating the abdomen, moving your fingers along this line from the costal margin toward the umbilicus helps you assess organ size and position.
The anterior superior iliac spine is the bony prominence at the front of the pelvis. It's easily palpable and serves as a landmark for hernia repairs, iliac bone grafts, and nerve blocks. In figure drawing, this spine marks the highest point of the hip and creates a visible projection in lean subjects. The distance between the two ASIS points is approximately 25 centimeters in average adult males and 20 centimeters in females. This measurement varies with pelvic width and body composition.
Common Misconceptions In Visual References
The navel is frequently drawn at the wrong level in anatomy references. It's not at the midpoint between the sternum and pubis. The actual position is at the level of the L3-L4 intervertebral disc, which sits roughly at the level of the umbilicus but varies with posture and body type. When standing, the navel sits slightly higher than when supine because abdominal organs shift with gravity. The rectus sheath is another area where references often oversimplify. The anterior rectus sheath is formed by the aponeuroses of the external oblique, the anterior layer of the internal oblique, and the transversus abdominis. The posterior sheath exists only above the arcuate line, which is located about one-third of the distance from the umbilicus to the pubic symphysis. Below this line, all three aponeuroses pass anterior to the rectus abdominis, leaving only transversalis fascia and extraperitoneal fat posteriorly. This anatomical detail matters for surgical references and realistic injury depiction. I've seen medical illustration students struggle with the inguinal ligament. This structure forms the inferior border of the external oblique aponeurosis and runs from the ASIS to the pubic tubercle. It's often drawn as a simple line, but it's actually a thickened band of fascia with significant structural importance. The inguinal ligament creates the inferior boundary of the abdomen and the superior boundary of the thigh. When Hernias occur in the inguinal region, they're categorized as either direct (medial to the inferior epigastric vessels) or indirect (lateral to these vessels). This distinction depends on understanding the ligament's relationship to surrounding structures.
Practical Applications For Different Workflows
If you're working in traditional figure drawing, focus on the ribcage-pelvis relationship first. Block in these two forms as tilted ovoids before adding any musculature. The tilt angles determine the pose's energy. A forward-tilted pelvis with a counter-rotated ribcage creates contrapposto. Matching tilts create a neutral stance. Getting these angles right makes the figure look grounded regardless of how detailed your rendering becomes. For 3D modelers, topology direction matters more than polygon count. Create edge loops that follow the muscle fiber directions: circular around the ribcage, inferomedial for external obliques, and superomedial for internal obliques. This topology deforms correctly during animation. Random topology creates pinching and unnatural stretching when the character moves. Medical illustrators should prioritize accuracy over aesthetics. The liver occupies the right upper quadrant beneath the diaphragm. The stomach sits in the left upper quadrant, anterior to the spleen. The intestines fill the lower abdomen and pelvic cavity. These relationships must be preserved even if it means showing structures that aren't visible on the surface. A cross-sectional view is often more valuable than an external representation for educational purposes.

I've found that building a personal reference library pays dividends. Collect CT scans, MRI slices, and dissection photographs from reliable sources. Organize them by anatomical region and body position. When you encounter a specific problem — like determining the exact attachment point of the pectoralis major on the humerus — having immediate access to verified references saves hours of guesswork. The initial investment in gathering and organizing references is substantial, but the time savings compound with each project. The download links and additional resources mentioned in various forums often point to outdated textbooks or incomplete datasets. Before relying on any external source, verify the anatomical accuracy against current Gray's Anatomy or Netter's Atlas standards. The field evolves, and references that were accurate a decade ago may contain errors that have since been corrected. Cross-referencing multiple sources protects against propagating mistakes into your own work.

