How I Actually Learn Organ Anatomy Without Losing My Mind
Most people approach anatomy studying like they are memorizing a phone book. They read a chapter, look at a diagram, try to recall the names, and move on. It barely works. I spent three semesters trying that method and failed every practical exam because I could name the hepatic flexure but could not explain why it sits where it does relative to the right lobe of the liver. The breakthrough came when I stopped treating organs as isolated facts and started mapping them by relationship. Not spatial relationship like left or right, but functional and structural. I began asking what holds each organ in place, what blood vessels feed it, and what happens when one adjacent structure gets removed or displaced.
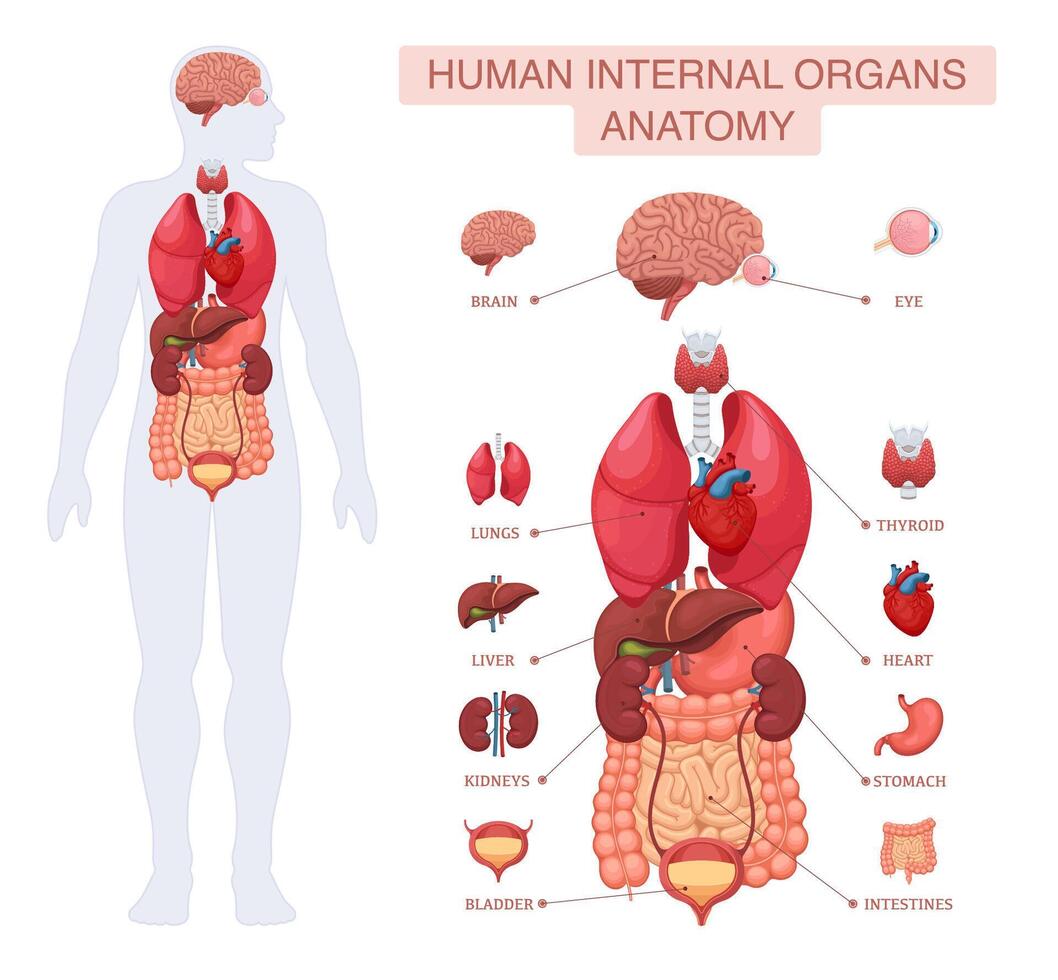
Practical Approach to Anatomy Organs Of Human Body
Here is what I actually did. I started with a blank slate of the abdominal cavity and drew the diaphragm first. Then I placed the liver against the right dome, not because I memorized that it is on the right, but because I understood thefalciform ligament anchors it there and the gallbladder nests in the visceral surface. The moment I drew it, the spatial logic locked in better than any flashcard ever managed. I used a specific set of reference books and atlases. Netter's plates for visual memory, Grant's Atlas for surgical relationships, and Snell's Clinical Anatomy for the clinical context. I would spend about forty-five minutes on one organ system, drawing labeled diagrams from memory, then checking against the atlas to find my gaps. This usually takes about two to three hours per major region if you are thorough. The edge-case that nearly broke me was the retroperitoneal organs. I kept confusing which structures were primary retroperitoneal versus secondary. The kidneys, adrenal glands, pancreas, and duodenum except the very first part are all stuck against the posterior abdominal wall. I kept placing the duodenum in the peritoneal cavity because textbooks show it surrounded by mesentery-like folds in diagrams. The workaround was simple: I traced the peritoneal reflection line on every cross-section and noted where the peritoneum ends. Once I saw the duodenum actually sit behind the peritoneum, the confusion ended.
Why Visualization Beats Rote Memorization Every Time
I have watched countless students try to brute-force anatomy through repetition. They highlight textbooks until the pages are rainbow-colored and still cannot identify the porta hepatis on a cadaver. The problem is that recognition is not recall. You can point to the spleen when it is labeled but cannot locate it blind. What actually builds durable memory is multi-modal engagement. I combined three techniques that reinforced each other. First, I drew the organ systems from different perspectives. Second, I palpated my own body to find surface landmarks. Third, I explained each structure out loud as if teaching someone else. The combination reduced my study time for gross anatomy by roughly sixty percent compared to reading alone. One counter-intuitive insight that beginners miss is that the size of an organ on a diagram does not reflect its clinical significance. The thymus looks impressive in the anterior mediastinum of textbook illustrations but atrophies rapidly after puberty. The appendix appears small but causes more surgical emergencies than any single organ in the right lower quadrant. Size is a poor proxy for importance.
Get the Full Details
Common Pitfalls and How to Avoid Them
I see students make the same mistakes repeatedly. They confuse structures across different body regions. The splenic flexure and hepatic flexure of the colon both represent sharp turns but have completely different vascular supplies and clinical implications. One is fed by the inferior mesenteric artery and prone to volvulus. The other receives blood from the superior mesenteric system and is adjacent to the gallbladder. Another frequent error is ignoring fascial planes. The prevertebral fascia, pretracheal fascia, and carotid sheath create distinct compartments that guide the spread of infection and the path of surgical instruments. I once spent an entire evening trying to memorize the layers of the neck without understanding that the deep cervical fascia actually separates into investing, pretracheal, and prevertebral layers. Once I mapped those planes, the entire regional anatomy reorganized itself logically. The limitation I must acknowledge is that no amount of diagram-drawing replaces actual dissection. I studied from books for months and still froze when I encountered the variation in the circle of Willis during my first lab. The arterial anastomosis I had drawn perfectly sat slightly differently in the cadaver. This is not a criticism of book-based study but a recognition of its boundary. Physical manipulation and three-dimensional reasoning remain irreplaceable for clinical competence.
A Note on Resources and Time Investment
If you are starting this, do not buy five atlases. One good one used consistently beats five neglected ones. I recommend pairing an atlas with a dedicated anatomy app that provides 3D rotation. Complete it weekly, not crammed before exams. The brain needs spaced repetition to move structures from short-term recognition to long-term recall. The typical timeline I observed in myself and peers was about six to eight weeks for a complete pass through gross anatomy if studying twelve to fifteen hours per week. Rush cramming for two days before an exam might get you through the material but the retention drops to roughly thirty percent within a month. The investment of consistent, distributed practice pays compounding returns. I also learned to accept that some things will never stick without clinical correlation. The brachial plexus roots, trunks, divisions, cords, and branches memorized in isolation blur together. Once I connected them to actual nerve injury presentations in the emergency department, the entire mnemonic collapsed into a single coherent map. Context anchors memory better than repetition alone.
The honest truth is that anatomy is not a subject you finish. It is a language you keep practicing. I still look up the relationship between the portal vein and the common bile duct every time I encounter it, even years after graduation. That is normal. That is how expertise actually works. It is not about knowing everything. It is about knowing where to find what you need and understanding why it matters when you do.




