Getting Through Anatomy Terminology Activity Without Losing Your Mind
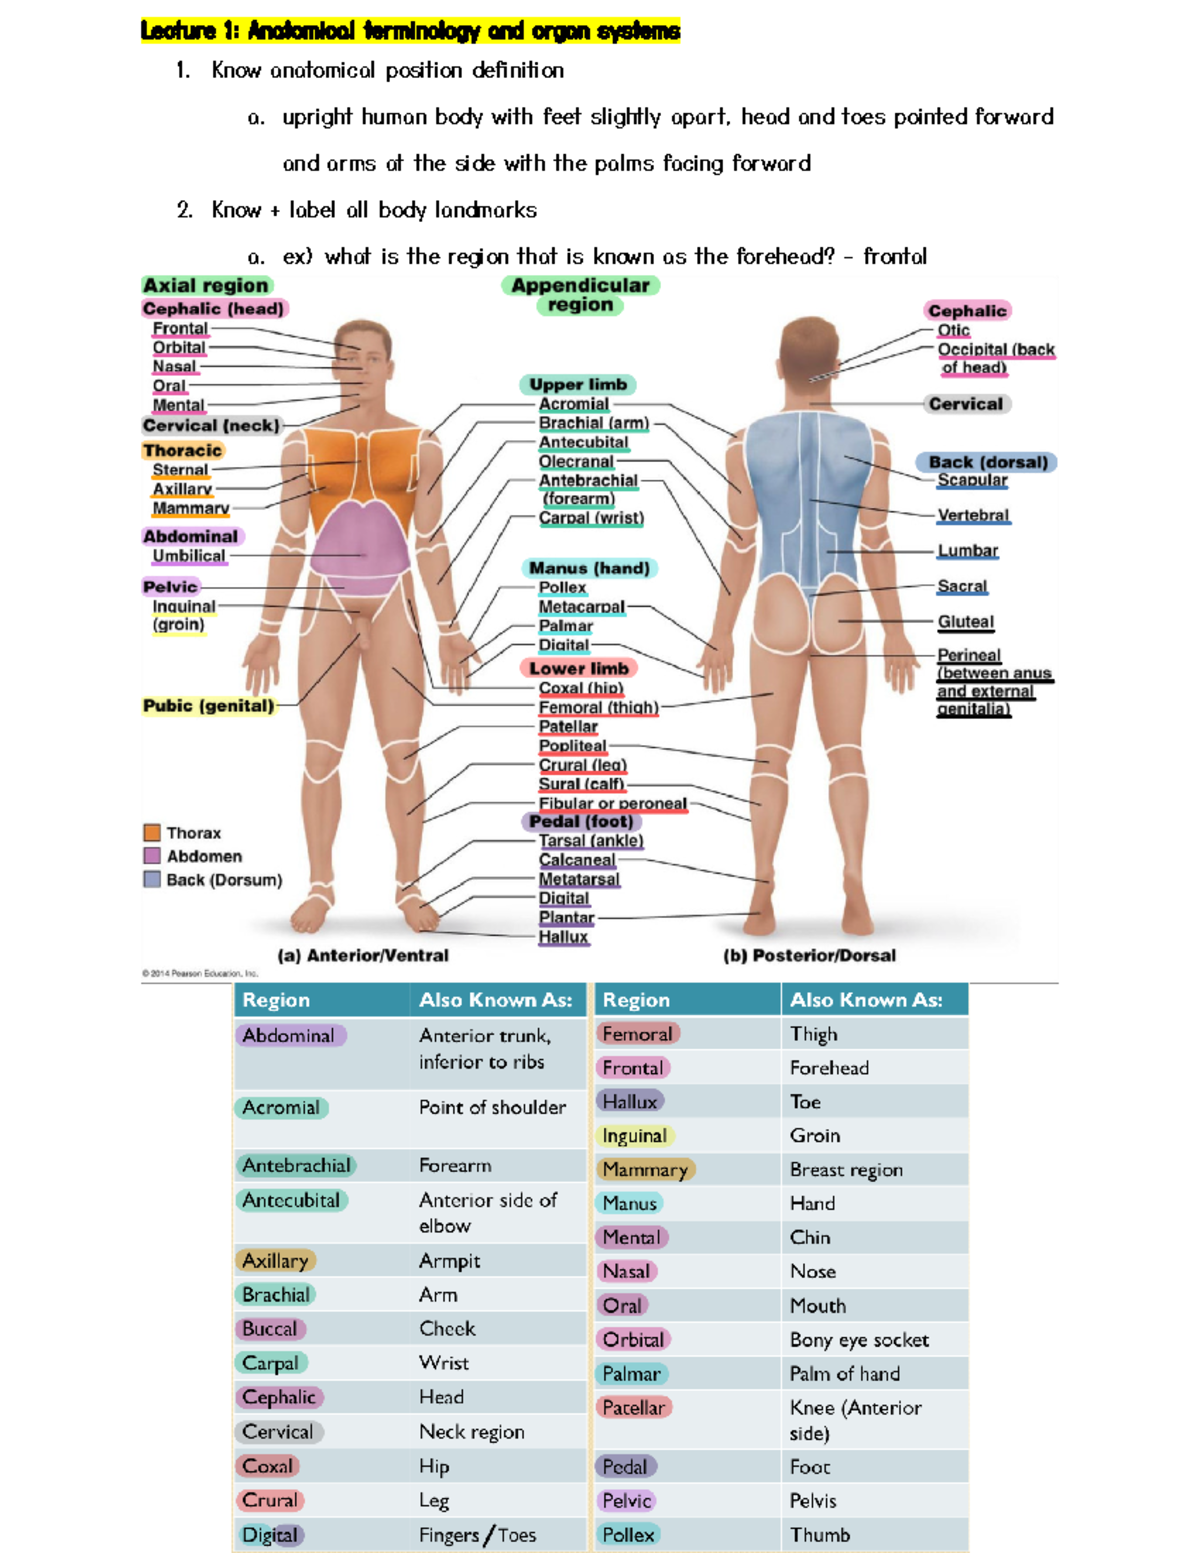
Most people approach anatomy terminology activity materials as a vocabulary drill. That is one of the first mistakes students make. It is not vocabulary. It is a language system. When you treat it like a list of words to memorize, you will spend weeks forgetting half of it by exam time. The structure underneath the terms is what actually matters. Directional terms, planes, regions, and the relationships between them. Get those down and the rest of it clicks into place. Miss them and every quiz feels like guesswork. I ran into this problem last semester with a group of nursing students who were struggling through their first gross anatomy lab. They had spent three weeks hammering flashcards for anatomical position and directional terminology. During the practical exam, I watched them freeze on a question that asked them to describe the relationship between the popliteal and patellar regions. They knew "popliteal" meant back of knee and "patellar" meant front of knee. But when they had to write out the directional relationship, they kept second-guessing themselves because the terms felt disconnected from anything real. The fix was simple and it took about ten minutes. I had them stand up and physically point to each region on themselves while saying the terms out loud. Then I asked them to describe one region's location relative to the other using only directional language. Almost every single one of them got it right immediately. The problem was never that they did not know the terms. The problem was that they had stored the terms in isolation rather than in relation to each other.
This is why anatomy terminology activity sheets that just list terms alphabetically are largely useless. You need to encounter terms in context. Pair them with actual body positions, real imaging, or at minimum diagrams that show spatial relationships. The moment you can visualize where something is, the term stops being abstract and starts being functional.
The Core Components You Actually Need to Know
Directional terminology is the foundation. Anterior, posterior, medial, lateral, proximal, distal, superficial, deep. These eight terms alone cover the vast majority of everything you will read in any anatomy textbook. Beyond that, you need the standard anatomical position locked in. Standing upright, palms facing forward, feet shoulder-width apart. If your mental image of this position is wrong, every directional term you apply to it will also be wrong. I have seen students lose points on multiple choice questions simply because they were visualizing the palms turned inward instead of outward. Planes of section come next. Sagittal, coronal, transverse. These are not just labels. They determine how you interpret any cross-sectional imaging. A radiologist reading a CT scan is thinking in transverse planes. A surgeon planning an approach is often thinking in sagittal or coronal planes. Understanding which plane an image is presented in changes how you describe the location of a structure. This is where most students start to get tripped up in upper-level courses. The terminology does not change. The reference frame does. Regions of the body require a bit more dedicated study. The abdomen alone has nine regional divisions that every clinical procedure references.RUQ pain means something very specific. If you cannot quickly locate the right upper quadrant on a diagram, you are going to have a rough time in clinical rotations. The same goes for brachial versus antebrachial, crural versus femoral, pedal versus plantar. These pairs show up constantly in documentation and nobody explains where the boundary actually lies.
Get the Full Details

A Counter-Intuitive Thing About Memorization
Most people think the best way to learn anatomical terms is to repeat them. Spaced repetition with flashcards. Anki decks. Highlighting textbooks. All of that works to some degree. But the research and my own experience both point to something most students overlook. Active retrieval with physical movement beats passive review every time. When you say a term while touching the corresponding region on your own body, you create a motor memory alongside the verbal memory. Two recall pathways instead of one. I started doing this consistently about five years into teaching anatomy. Before that I was just assigning flashcard sets like everyone else. After switching to a method where students had to identify regions on themselves and on partners before looking at any diagrams, their practical exam scores went up noticeably. Not dramatically, but enough that I stopped assigning pure memorization worksheets and built everything around active identification. The total time spent on the activity did not change. Just how that time was used. Another thing beginners miss: Latin and Greek roots are not decoration. They are a pattern recognition system. If you know that "hepato-" means liver, "nephro-" means kidney, and "cardio-" means heart, you do not need to memorize each term as a standalone word. You are decoding it. A single evening of learning common roots will save you dozens of hours of rote memorization later. Focus on the roots first, then let the full terms fill in around them.
Where Anatomy Terminology Activity Falls Short
Term sheets and digital quizzes have a real limitation. They cannot teach you variation. The textbooks describe ideal anatomy. Real bodies do not always cooperate. A structure that is supposed to be deep might sit more superficially in a particular person. A branch that is described on the medial side might appear laterally. Terminology gives you the baseline. It does not prepare you for anatomical variance, which shows up frequently in cadaver labs and later in surgical settings. Another bottleneck is that written terminology activities rarely train you to communicate findings under time pressure. In a clinical setting, you might have thirty seconds to tell a colleague exactly where a fracture is. Saying "the anterior proximal third of the tibia" is precise. Saying "the front of my shin about halfway up" is faster and most clinicians will understand it. Knowing both registers matters. Most anatomy courses focus on the precise register and leave the clinical shorthand to osce prep later. If you are relying solely on a terminology worksheet or app, you will hit a wall somewhere around midterms. The material shifts from naming structures to describing relationships and spatial reasoning. The workaround I recommend is to supplement whatever activity you are using with actual cadaver lab time or high-quality 3D anatomy software. CompleteDx, Complete Anatomy, or even free options like Visible Body give you the spatial component that flat worksheets cannot. Spend at least an hour each week manipulating structures in three dimensions. It changes how you retain the terminology permanently.
Bottom Line on Anatomy Terminology Activity
The activity itself is only as useful as how you approach it. Treat it as a language to decode rather than a list to cram. Anchor terms to physical locations on your own body. Learn the root words so you are not starting from zero each time. And accept that no worksheet will ever fully replace seeing the actual structures in space. The terms are the map. The body is the territory. Studying the map exclusively will get you lost.