Mapping the Lower Extremity Vasculature Without Losing Your Mind
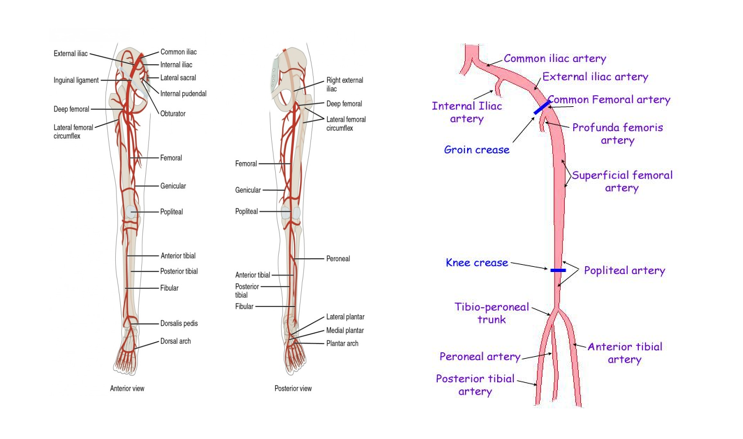
The vascular anatomy of the lower extremity is not a neat textbook diagram. It is a maze of branching vessels that vary significantly from patient to patient. When I first started studying it, I treated it like I would map a road system. Memorize the main arteries, follow them down, and you will know where everything goes. That approach fails quickly because the iliac bifurcation alone is a nightmare of individual variation, and most students skip the actual clinical relevance until it is too late. The core structure begins with the common iliac artery branching at roughly the L4 vertebral level. From there, the external iliac continues inferiorly and becomes the femoral artery as it passes behind the inguinal ligament. This transition point matters more than most people realize. The profunda femoris branches off the lateral and posterior aspect of the femoral artery, usually within two centimeters of the inguinal ligament. Missing this relationship on imaging leads to complications during interventions. Below the knee, the popliteal artery divides into the anterior and posterior tibial arteries plus the peroneal artery. That trifurcation is standard in most textbooks, but in practice, the peroneal artery can arise much higher or be absent entirely. I learned this the hard way when reviewing angiographic data for a peripheral artery disease case. The peroneal was running along the posterior interosseous membrane instead of taking its usual course. If you are planning an endovascular approach, that variation changes everything about your wire trajectory.
The venous system presents its own set of frustrations. The deep femoral vein, small saphenous, and great saphenous veins form anastomotic networks that bypass obstruction efficiently. This is clinically useful until you need to cannulate a specific vein for access. The perforating veins connecting the deep and superficial systems are unpredictable. One study I reviewed showed over thirty percent of lower extremities had atypical perforator locations.
How to Actually Map This Anatomy in Practice
Start with cross-sectional imaging. CT angiography gives you the best overall view of arterial architecture. Magnetic resonance angiography works if the patient cannot tolerate contrast. Ultrasound remains the workhorse for real-time assessment of stenosis or occlusion. I rely on duplex ultrasound most of the time because it shows hemodynamic significance, not just anatomy. A vessel can look narrowed on CT and be completely functional under flow conditions. When you are learning this material, do not just look at static images. Watch live flow. I spent two months watching lower extremity angiograms from start to finish before I felt confident navigating them myself. You need to see how contrast moves through the vessels, where it pools, where it stalls. That visual memory sticks with you during procedures far better than any flashcard system. For manual mapping, I use a simplified landmark-based approach. The femoral pulse location at the mid-inguinal point marks the common femoral artery. From there, trace the vessel medially toward the adductor hiatus, which transitions into the popliteal artery. The tibial pulses are your final check points. Posterior tibial pulse sits just behind the medial malleolus. Dorsalis pedis pulse lies on the dorsum of the foot between the first and second metatarsals. Neither pulse is present in every healthy adult. The absence of a dorsalis pedis pulse is normal in approximately eight percent of the population.
Get the Full Details
Edge Cases and Workarounds
During a recent case involving a diabetic patient with multilevel disease, I encountered a scenario where the superficial femoral artery was chronically occluded from the origin of the profunda femoris all the way down to the adductor canal. Collateral circulation was robust enough that the leg was viable at rest, but the patient had claudication within two blocks. The standard approach would be surgical bypass, but the distal target vessels were small and calcified. I mapped the anatomy using intravascular ultrasound through a retrograde popliteal access. The vessel I could salvage was the posterior tibial artery, which was unexpectedly patent despite appearing diseased on conventional angiography. Using the IVUS guidance, I successfully performed an endovascular recanalization. That would have been impossible without understanding the three-dimensional relationships in this vascular territory. Another common pitfall involves the geniculate arterial network around the knee. Beginners often overlook how extensively these vessels collateralize. When the superficial femoral artery is blocked, the geniculates can maintain perfusion to the lower leg. Interventionalists sometimes miss this and attempt unnecessary revascularization. The body already has a working solution. Recognize it before intervening.
Where This Knowledge Falls Short
No anatomical model covers every variation. Some patients have accessory femoral arteries, duplicated iliac segments, or complete absence of the peroneal artery with compensatory hypertrophy of the anterior tibial system. Imaging can only show so much. Surgical exploration remains the definitive reference standard, and even that has limits. Cadaver studies show different results from living subjects because hemodynamics change vessel caliber and branching patterns. If you are studying this material for clinical purposes, do not treat any single resource as the final word. Combine Cross-sectional imaging databases, cadaveric atlases, and live procedural observation. The field of vascular anatomy evolves constantly with new imaging technology revealing details we missed twenty years ago. The lower extremity vasculature is complex enough that no shortcut replaces thorough study. But the right approach makes the difference between guessing during a procedure and knowing what you are looking at.