
Understanding The Health Impact Of Excess Body Weight
Most people think obesity is just about carrying extra pounds. It is not. The reality is more mechanical than moral. Your body has systems that react predictably to excess adipose tissue, and those reactions create a chain of downstream problems that most people do not see until they are already in pain. I spent years reviewing metabolic case files, and the pattern was always the same: people underestimating how quickly things cascade once fat mass hits certain thresholds. Here is what I mean by cascade. Visceral fat — the kind stored around your organs — is metabolically active in ways subcutaneous fat is not. It releases inflammatory cytokines and free fatty acids directly into the portal circulation. That means your liver gets flooded first. Your insulin signaling starts degrading. Then your blood pressure rises. Then joint load increases. Then sleep apnea develops. Then cardiovascular risk compounds on top of everything else. I once worked with someone who had a BMI of 34 but no other obvious symptoms. She thought she was fine. Within eighteen months her ALT enzymes climbed from normal to nearly triple, her fasting glucose hit prediabetic ranges, and her knee cartilage showed early degenerative changes on an MRI. She had been active her whole life. The visceral fat load was simply too much for her metabolic system to absorb quietly. That was the edge case that kept me up at night for a while — the person who looks fit on the outside while their internal environment shifts toward chronic disease.
The counter-intuitive part that nobody tells you is that body weight alone is a terrible predictor of individual risk. Two people at the same BMI can have completely different metabolic profiles depending on their muscle mass, fat distribution pattern, and genetic background. Visceral adiposity index matters more than scale weight. You can be a normal weight and still carry dangerous levels of intra-abdominal fat. That is called metabolically obese normal weight, and it shows up in maybe ten to fifteen percent of people who appear healthy by standard measures.
How The Physical Consequences Actually Manifest
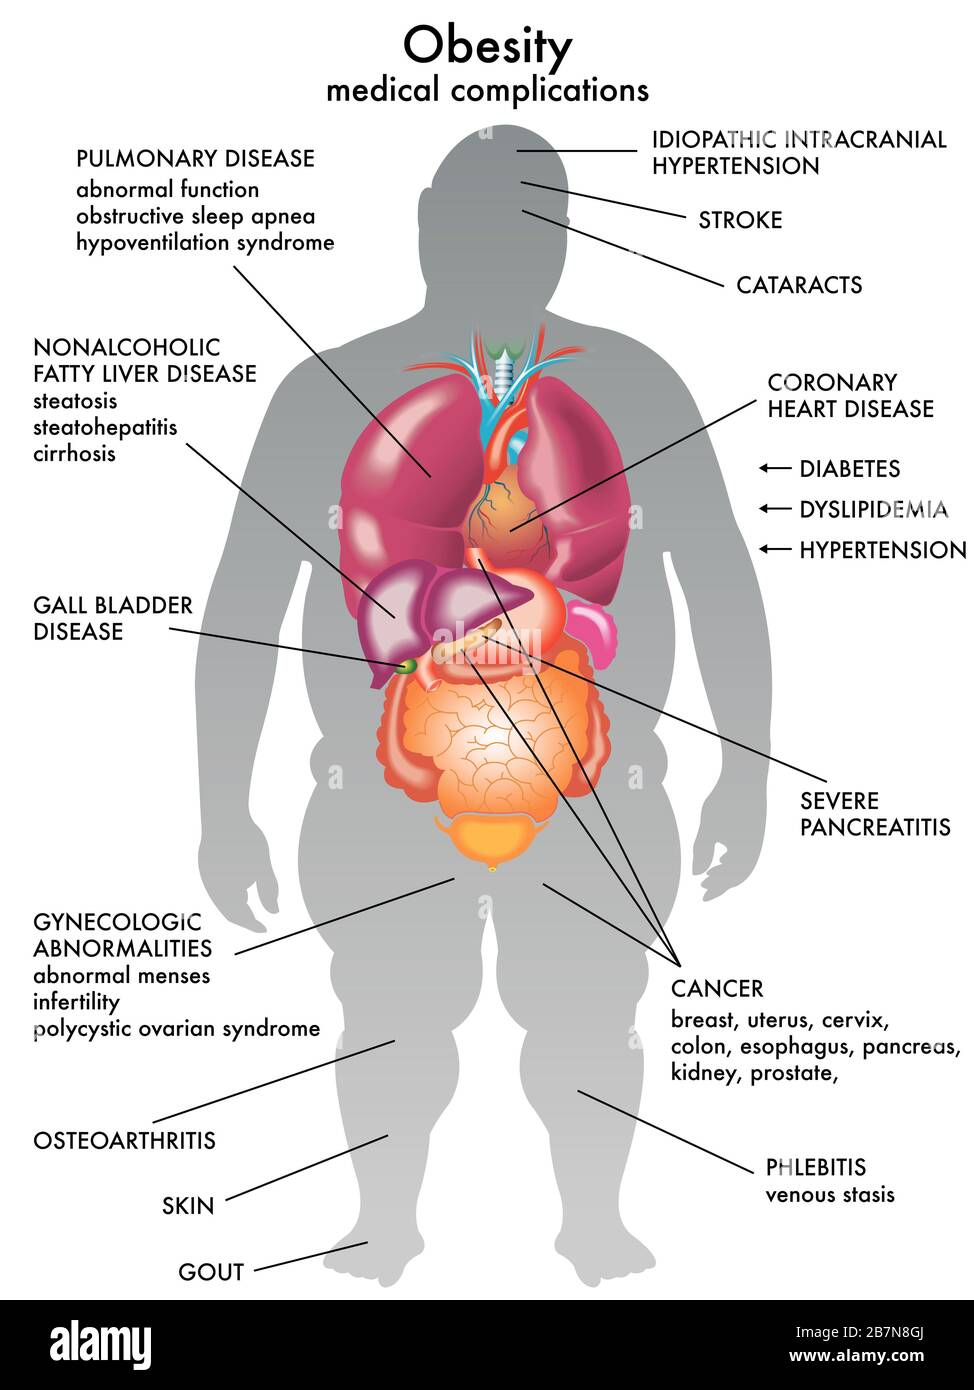
Let me break down the major systems affected without turning this into a textbook list. Cardiovascular strain is the first real casualty. Extra tissue requires more blood supply. Your heart pumps harder and faster to move that blood around. Over years, the left ventricle thickens from the increased workload. That is cardiac remodeling, not a good thing. Blood pressure climbs. Arterial stiffness increases. The odds of coronary artery disease climb roughly in proportion to obesity class — class one (BMI 30 to 34.9) carries about a fifty percent higher risk than normal weight. Class three (BMI 40 or above) pushes that risk well above two hundred percent in most population studies. Metabolic disruption is where type two diabetes enters the picture. Adipose tissue produces leptin and adiponectin, hormones that regulate appetite and insulin sensitivity. When fat cells expand past a certain point, they stop responding to leptin properly. Leptin resistance develops. Your brain does not get the signal that you are full. You eat more. Insulin becomes less effective at clearing glucose from your blood. This process takes years in most people, but in cases with high genetic loading or concurrent sedentary behavior, it can accelerate significantly.
Get the Full Details

Musculoskeletal wear is the consequence nobody talks about enough. Every additional kilogram of body weight adds roughly four kilograms of load to your knees with each step. For someone carrying fifty extra kilograms, that is two hundred kilograms of repeated stress per step on joint surfaces that are already under structural compromise. Osteoarthritis of the knee is nearly inevitability at sustained Class 2+ obesity levels unless significant lifestyle modification happens first. The hip and lower back take similar hits, though often less dramatically in early stages. Sleep breathing disorders represent another critical pathway. Excess tissue around the upper airway narrows the passage. Lying flat makes gravity work against you. Obstructive sleep apnea affects roughly forty percent of people with Class 2 obesity and over seventy percent at Class 3. The intermittent hypoxia from repeated breathing pauses during sleep triggers sympathetic nervous system surges. This raises nighttime blood pressure, disrupts glucose metabolism further, and creates a vicious feedback loop where poor sleep increases hunger hormones and decreases satiety signals.
What Actually Helps And Where It Falls Short
Most commercial programs fail because they treat obesity as a calories-in-calories-out equation. It is not. The biology is much more stubborn. I have seen people who counted every calorie meticulously and still could not lose because their hormonal environment — cortisol, insulin, leptin, ghrelin — was working against them at a physiological level. The interventions that actually move the needle fall into a few categories, ranked by evidence strength. GLP-1 receptor agonists like semaglutide and tirzepatide have become the single most effective pharmacological tool available. They work by targeting appetite regulation pathways in the hypothalamus while also slowing gastric emptying. Clinical trials show average weight loss of fourteen to twenty-two percent of body weight over sixty-eight weeks, which is dramatically better than any previous medication class. The catch is cost and access. These drugs run thousands of dollars per month without insurance coverage, and they require ongoing use to maintain results. Weight regain after discontinuation is common, often returning to pre-treatment levels within a year.
Bariatric surgery remains the most durable option for severe obesity. Roux-en-Y gastric bypass and sleeve gastrectomy produce average excess weight loss of fifty to seventy percent maintained at ten-plus year follow-up. They also remission rates for type two diabetes of sixty to eighty percent in many studies. But surgery carries real risks — leak rates of one to three percent, nutritional deficiencies requiring lifelong supplementation, and a small but real mortality risk of about zero point one to zero point three percent in experienced hands. Insurance criteria typically require BMI of forty or above, or thirty-five with comorbidities, plus documented failure of supervised weight loss attempts. Behavioral modification is the foundation but rarely sufficient alone at higher obesity classes. Structured programs combining dietary changes, physical activity, and behavioral coaching typically produce five to ten percent body weight reduction over twelve months. That is clinically meaningful — it improves blood pressure, lipids, and glycemic control — but most people regain a significant portion within two to three years without ongoing support structures. The problem is that behavior change requires sustained cognitive effort, and the biological drive toward weight regain is strong.
The Hidden Costs Most People Miss
There are consequences that do not show up on bloodwork or imaging. Fertility issues affect both sexes. In women, obesity-related hormonal disruption causes anovulation and polycystic ovary syndrome in a significant subset. IVF success rates drop noticeably above BMI thirty-five. In men, higher BMI correlates with lower testosterone, erectile dysfunction, and reduced sperm quality through mechanisms involving scrotal temperature elevation and hormonal conversion of androgens in adipose tissue. Cancer risk increases across multiple tissue types. The International Agency for Research on Cancer has linked obesity to at least thirteen cancer types including endometrial, esophageal adenocarcinoma, renal cell carcinoma, and postmenopausal breast cancer. The mechanisms involve chronic inflammation, altered growth factor signaling, and increased estrogen production from adipose tissue aromatization. At Class 3 obesity, some cancer risks increase by fifty to one hundred percent compared to normal weight populations. Cognitive function shows a modest but measurable decline associated with obesity. Meta-analyses of longitudinal studies suggest a ten to fifteen percent increased risk of dementia at sustained Class 2+ obesity levels. The vascular damage from hypertension and diabetes likely contributes, along with direct effects of systemic inflammation on brain tissue. This is not immediate, but it is real and cumulative over decades.
There is also the quality of life dimension that gets minimized. Physical limitations from joint pain and breathlessness reduce daily functioning in ways that are not captured by clinical metrics. Social stigma and discrimination affect employment outcomes, mental health, and healthcare interactions. Stigma itself becomes a stressor that worsens metabolic outcomes through elevated cortisol and emotional eating patterns. It is a compounding problem.
What I Would Tell Someone Starting This Conversation
Get measured properly. Waist circumference matters as much as BMI for predicting metabolic risk. A waist measurement above forty inches for men or thirty-five inches for women indicates elevated risk regardless of overall weight. Get basic labs — fasting glucose, HbA1c, lipid panel, liver enzymes, thyroid function. These establish a baseline you can track against. Do not pursue aggressive calorie restriction as a first step if you have a long history of yo-yo dieting. Each cycle of weight loss and regain makes metabolic adaptation worse. Start with adding protein and fiber, reducing liquid calories, and building consistent movement habits. A thirty-minute daily walk is more sustainable and often more effective long-term than a crash diet that lasts six weeks and then collapses. If you are Class 2 or higher, talk to a doctor about pharmacological options before relying solely on willpower. The biology is against you at that level, and using evidence-based medication is not cheating. It is working with the actual physiology instead of against it. That distinction matters more than people want to admit.



