Why Some Ankles Never Truly Feel Stable After a Sprain
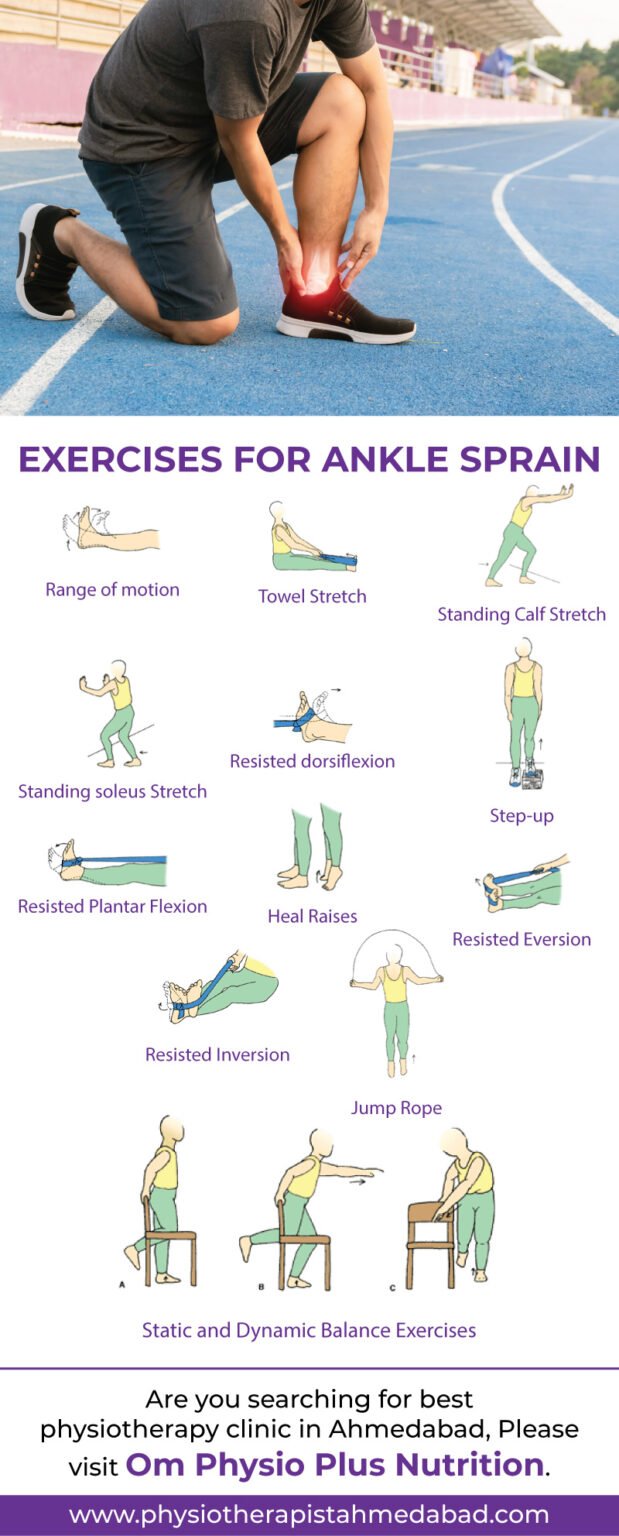
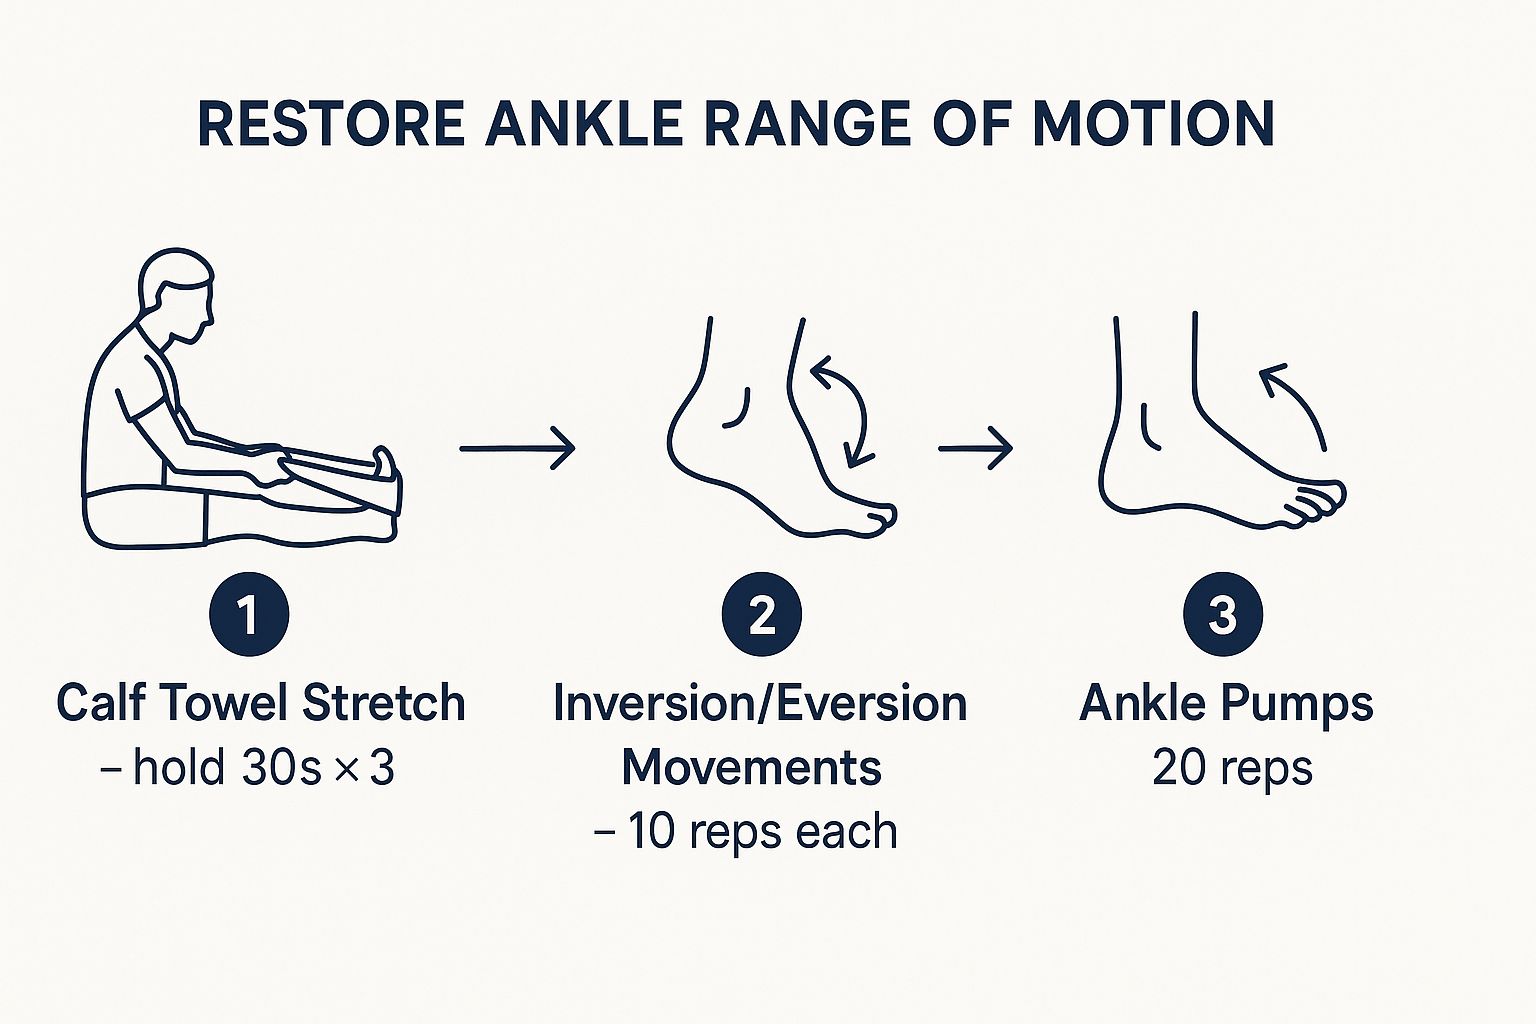
I spent three weeks trying to rehabilitate a Grade 2 lateral ankle sprain using the standard RICE protocol and a generic set of stretching routines I found online. The swelling went down. The pain faded. But when I tried to jog on uneven ground six weeks later, the ankle gave out on me like it had never healed at all. It wasn't weakness. It was proprioception — your nervous system's ability to tell where your joint is in space — that was missing, not strength. Most people skip the balance work entirely because it feels silly. Doing single-leg stands on a folded towel while closing your eyes does not look like exercise. It feels like standing still. That's exactly why it works, and why it's the part everyone drops. Ankle rehab isn't about making the ligament stronger. Ligaments don't respond to exercise the way muscles do. They heal on their own timeline, usually six to twelve weeks for a moderate sprain, and then they stay permanently slightly looser than they were before. What rehab actually rebuilds is the dynamic stabilizer system around the joint — the tendons, the peroneal muscles, the arch supports, and the neural feedback loops that tell your brain to fire those muscles before you even hit the ground. Without that system, you're relying on a loose band of tissue to hold your leg upright, and that fails under load. The most important phase is the early mobility work, and it starts within days of the injury, not weeks. Once the acute pain and swelling settle enough — usually 48 to 72 hours for a mild to moderate sprain — you begin controlled range of motion. Alphabet tracing is the classic recommendation: sit with your leg elevated and write the alphabet in the air with your big toe. It sounds absurd. It takes about ten minutes. It prevents the scar tissue from binding the joint capsule in a shortened position, which is what causes that permanent stiff feeling people complain about months later. I learned this the hard way after my second sprain. I skipped the alphabet work because it felt pointless. Six months later I still couldn't dorsiflex my ankle past neutral on the injured side, and simple calf stretches wouldn't fix it because the restriction was inside the joint, not in the muscle.
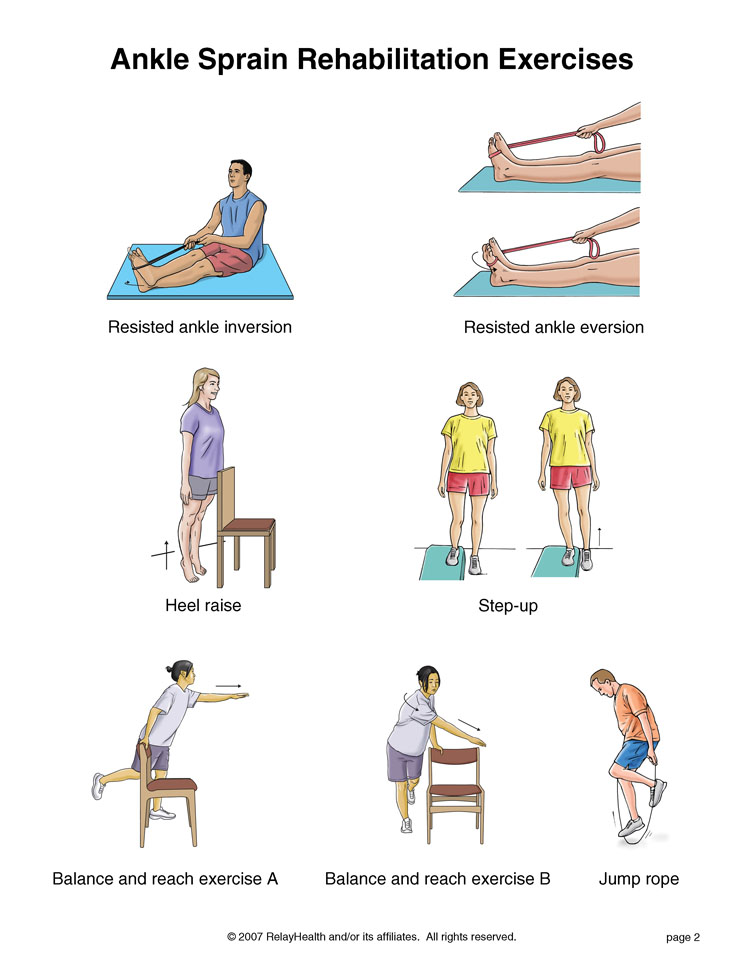
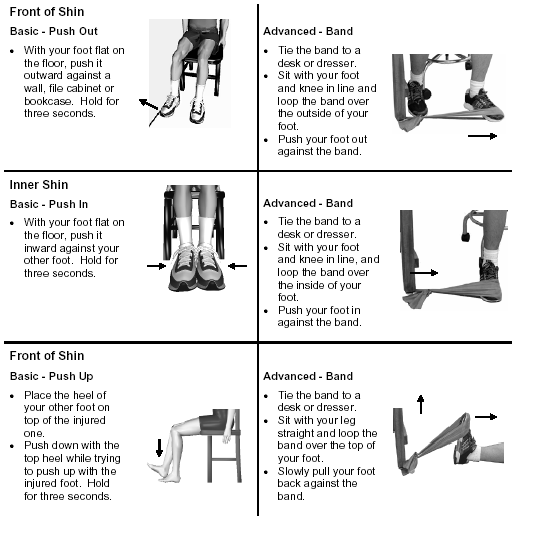
From there, you move into isometric loading. This is where you push against an immovable object — press your foot outward against a wall or your other foot pressing inward, holding for thirty seconds, three to five reps. Isometrics don't shorten or lengthen the muscle. They recruit the fibers and signal the nervous system without stressing the healing ligament. This is usually where people plateau because isometrics feel too easy. They're supposed to. The goal isn't fatigue. The goal is safe motor unit recruitment while the ligament is still vulnerable to stretch forces.
The Progression That Actually Matters
After isometrics come concentric and eccentric strengthening, primarily targeting the peroneal muscles on the outside of the lower leg. These are the muscles that prevent your ankle from rolling outward — the exact motion that caused most sprains in the first place. Resistance band eversion, where you strap a band around the foot and pull outward against resistance, is the foundational move. Three sets of twelve reps, twice a day. It should burn by the third set. If it doesn't, the band is too light or you're not controlling the tempo. Eccentric calf raises are non-negotiable and almost always neglected. Stand on the edge of a step on both feet, raise up on your toes with both legs, then shift your weight to the injured side and lower slowly — four to six seconds down. Three sets of eight. This loads the Achilles tendon and the gastrocnemius-soleus complex through a full range of motion under tension. Tendons adapt to eccentric load better than anything else, and a stiff Achilles transfers less force to the ankle ligaments during landing. I've seen patients who rebuilt perfect balance and strength but reinjured the same ankle within a month because they never addressed the eccentric deficit. Their calves were strong but their tendons were stiff and reactive. Balance work starts with double-leg stances on firm ground, progresses to single-leg on firm ground, then single-leg on foam, then single-leg with head turns, then single-leg with eyes closed. Each progression adds a sensory challenge that forces the proprioceptive system to recalibrate. The eyes-closed single-leg stand on foam is where most people think they're ready when they're not. Try it. You'll probably wobble significantly on the previously injured side. That wobble is data. It tells you exactly how much rehab is still needed before sport-specific loading.
Get the Full Details

When Ankle Rehab Exercises Fail and What to Do Instead
There are scenarios where standard rehab protocols don't work, and recognizing them early saves months of wasted effort. Chronic ankle instability affects roughly thirty percent of people after a moderate sprain, and it usually means one of two things: either the mechanoreceptors in the ligament were destroyed and never regenerated, or there's an underlying biomechanical issue like excessive pronation or a tight posterior chain that keeps the ankle in a vulnerable position with every step. If you complete a full twelve-week rehab program and your ankle still feels unreliable on uneven surfaces, you need a gait analysis, not more exercises. A physical therapist can assess whether your foot strikes ground in a way that forces the ankle into inversion on impact. Many people with flat feet or overpronation have their ankle rolling inward before their peroneal muscles even have a chance to fire. No amount of balance training fixes that. You need orthotics, a gait retraining program, or in some cases a bracing strategy during sport. I had a client who did every exercise perfectly for four months and kept re spraining the same ankle on the third minute of every basketball game. We discovered through video analysis that she was landing with her knee valgus — knee caving inward — which put her ankle in inversion before her muscles could react. The fix wasn't more rehab. It was hip abductor strengthening and a conscious cue to push her knee outward on landing. She stopped reinjuring within two weeks. Another common failure point is returning to sport too quickly based on pain alone. Pain is a terrible metric for tissue readiness. You can have zero pain and still have ligaments that are mechanically insufficient to handle cutting and pivoting forces. The return-to-sport benchmark should be objective: equal range of motion, equal strength measured by single-leg heel raise count, equal balance on a modified Star Excursion Balance Test, and successful completion of sport-specific agility drills without compensation. If you can't hop on the injured leg ten times without your trunk leaning away from that side, you're not ready. The lean is your body's unconscious strategy to offload the joint, and it's a reliable indicator that the stabilizer system isn't firing fast enough yet.
Practical Timeline and Realistic Expectations
Week one after a moderate sprain: rest, compression, elevation, and the alphabet range-of-motion work. Walk with a normal gait as pain allows, using a brace or tape for support. Week two: introduce isometrics and begin light resistance band work in all directions. Week three to four: progress to weight-bearing strengthening, single-leg balance on firm ground, and stationary cycling if available. Week five to eight: add eccentric calf work, single-leg balance on unstable surfaces, and begin agility drills like figure-eight walking and controlled hopping. Week eight to twelve: sport-specific drilling, progressive return to cutting and jumping, and continued balance maintenance. This timeline assumes a Grade 1 or 2 sprain with no fractures and adequate compliance. Grade 3 tears — complete ligament ruptures — often require immobilization for two to four weeks before rehab begins, and the full timeline extends to four to six months. People who ignore the early mobility phase and jump straight into strengthening usually end up with stiff joints and strength that doesn't translate to function. The ankle needs to move freely through its full range before you load it heavily. A stiff ankle with strong muscles is more injury-prone than a mobile ankle with moderate strength. Maintenance matters indefinitely. Once you've completed rehab, you don't stop. Two or three balance sessions per week, ten minutes each, are enough to preserve proprioceptive gains. Single-leg stands on one foot while brushing your teeth. That's it. The gains fade within weeks of stopping, and the neural adaptations that protect your ankle are only maintained through consistent, low-effort practice. I still do my balance work four years after my last sprain. Not because I'm worried. Because I know what happens when I skip it.