Working With Boykin and Schoenhofer in Clinical Practice
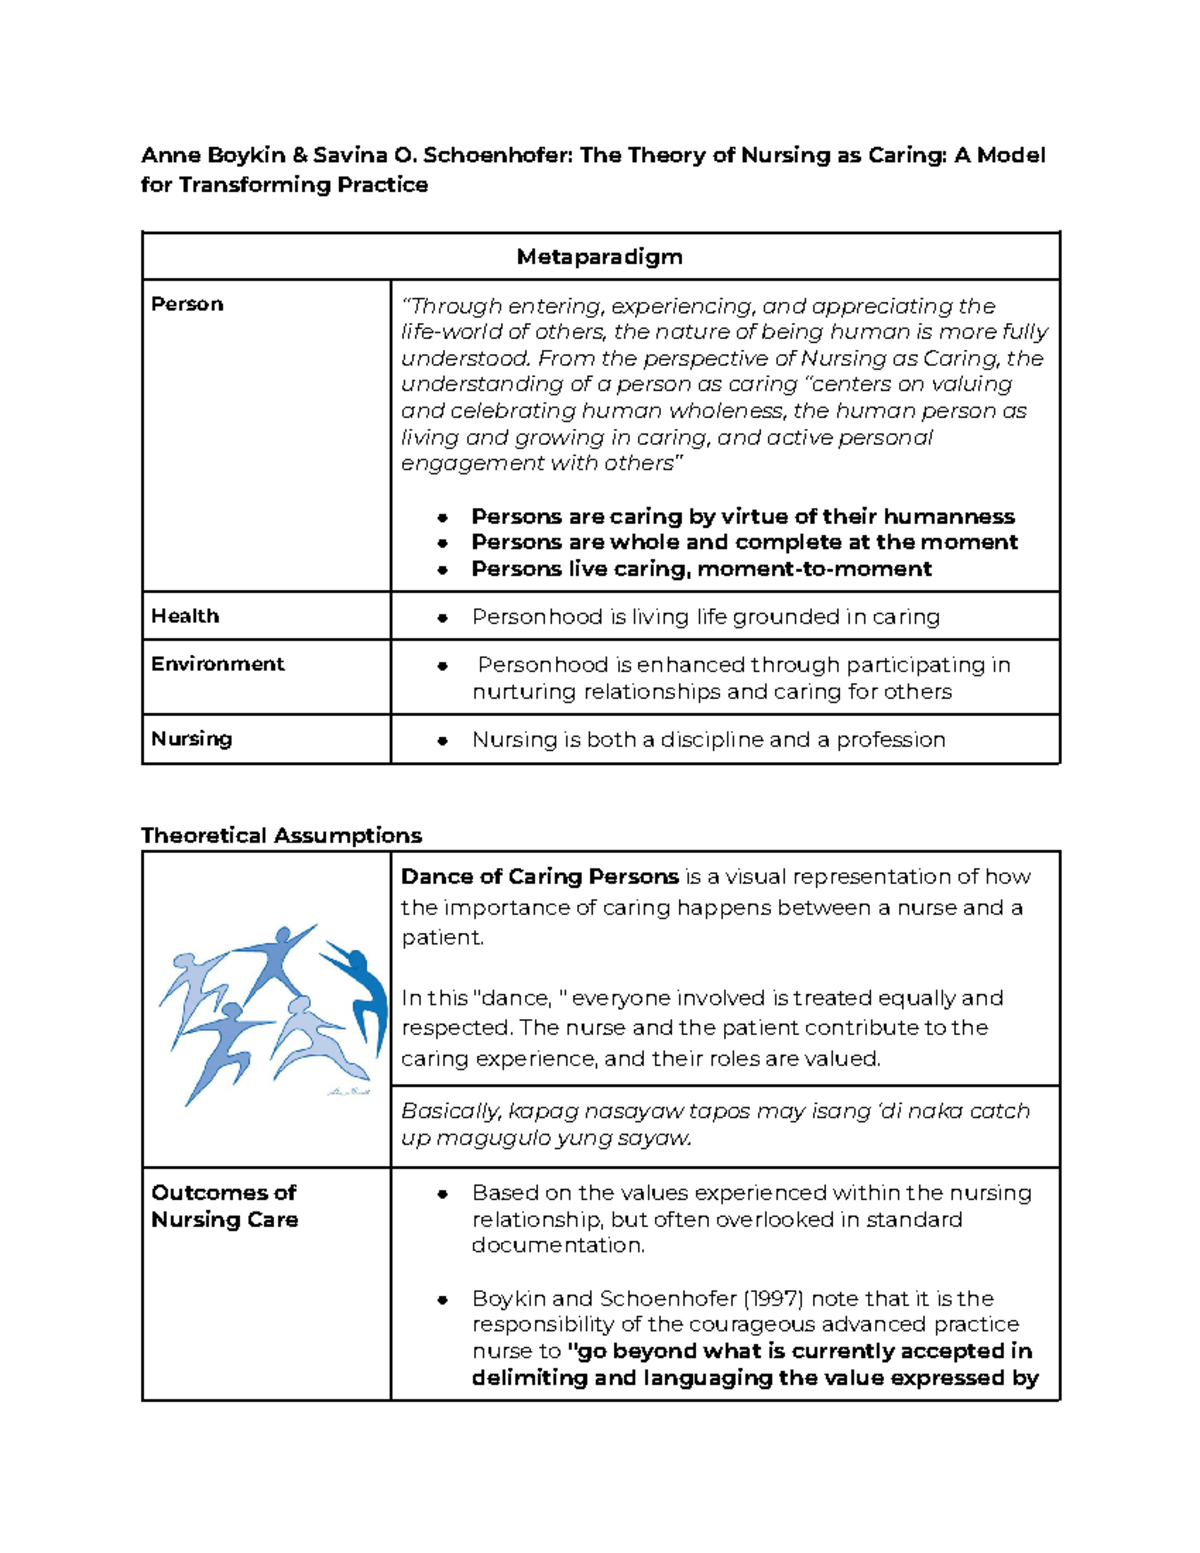
I have seen a lot of nursing students and even some practicing nurses try to apply the Boykin and Schoenhofer framework to patient care, and most of them get stuck on the same problems. The theory is solid on paper but translating it into daily practice takes more work than textbooks let on. I want to walk through what this actually means, how it shows up in real hospital floors and home health visits, and where people regularly mess it up. Their framework is called Nursing as Caring. It is not a theory of nursing in the traditional diagnostic-problem-solving sense. It treats nursing as fundamentally about human flourishing. That word matters because it changes how you approach every interaction. Instead of asking what is wrong with the patient and how to fix it, the starting question becomes how can this person flourish in their current situation. The central proposition is that nursing's purpose is to help persons flourish by engaging in caring movements that create opportunities for living well as caring beings. A caring movement is any action, verbal or nonverbal, that opens space for someone to live into their caring nature. It sounds abstract until you have to write it in a care plan or justify it during a shift handoff.
The Five Caring Practices
This is the part most people actually use, even if they do not realize it. Boykin and Schoenhofer outlined five caring practices that nurses can intentionally employ: Informing means sharing knowledge and helping the person understand their situation. This is not just handing over a brochure. It is tailoring the information to where the person actually is in their understanding. Validating involves acknowledging the person as a caring being. You recognize their experiences and circumstances without judgment. This practice alone changes how patients respond to treatment plans in my experience.
Enabling is about helping the person move toward their goals. It is the practical bridge between knowing what to do and actually doing it. Manifesting caring means doing things in ways that demonstrate you are genuinely engaged. This is the behavioral expression of the theory. Eye contact, sitting down before starting a procedure, putting down your clipboard. Knowing means entering into the person's world. Not assuming you understand their situation because you have seen it before. This one requires actual time and attention, which is exactly what most units do not have.
Get the Full Details

How It Works on a Real Shift
Here is where it gets complicated. I worked a medical-surgical unit where we tried implementing this framework for about six months. The problem was not the theory. The problem was the environment. You cannot genuinely know a patient, validate their experience, and enable their goals when you are assigned ten patients and expected to complete tasks within rigid time windows. The workflow mismatch is the single biggest issue with this framework in acute care settings. The theory assumes a pace and depth of interaction that most hospital systems do not support. I found the most realistic way to apply it was to treat it as a lens rather than a checklist. Instead of trying to do all five practices perfectly for every patient on every shift, I picked one or two that would make the actual difference for that specific person. For example, with a diabetic patient who was clearly resistant to learning about insulin management, the enabling practice meant stepping back and finding out what was actually blocking them. It turned out they worked night shifts and the entire education plan assumed daytime routines. The knowledge gap was not resistance. It was poor alignment.
Common Pitfalls I See Repeatedly
First, people treat the caring practices as a box-checking exercise. They tick off informing and validating without any real engagement. Patients notice this immediately. The framework loses all effectiveness when it becomes another administrative task. Second, there is a temptation to conflate caring with just being nice. This is not the same thing. You can be pleasant and still miss the substantive work of helping someone flourish. The theory requires intentional practice, not just a warm disposition. Third, documentation is a real headache. Most EHR systems are built for problem-focused nursing diagnoses, not for documenting flourishing or caring movements. I spent considerable time figuring out how to write notes that satisfied charting requirements while actually reflecting what the framework demands. The workaround I used was to anchor care plan language in observable behaviors that aligned with the five practices. Instead of writing "patient validated as caring being," which sounds ridiculous in a medical record, I wrote about specific interactions that demonstrated validation and enabled goal-setting. It is less elegant but it actually works in a system that demands concrete documentation.
Where the Framework Falls Short
This is important and rarely discussed. The Boykin and Schoenhofer framework is weakest in high-acuity, time-critical situations. During code responses, trauma activations, or any scenario where rapid decision-making and task completion are the priority, the caring as transformation model does not provide actionable guidance. It is not designed for that. Expecting it to cover every clinical situation is a mistake. It also places a heavy burden on the individual nurse rather than the system. If the unit culture, staffing ratios, and workflow do not support relational practice, the nurse is left trying to force a square peg into a round hole. I have watched competent, caring nurses burn out trying to apply this framework under conditions that actively work against it. The framework should inform your philosophy, but it cannot substitute for adequate staffing and institutional support. For acute procedural contexts, standard problem-based nursing frameworks like NANDA-I diagnoses paired with NIC interventions give you more direct operational guidance. The caring framework complements those approaches rather than replacing them.
Practical Takeaways
If you are studying this for a course, focus on understanding the five caring practices and be ready to give concrete examples of how each one looks in a clinical interaction. Professors will ask for specifics, not abstract definitions. If you are a practicing nurse considering whether to use this, start small. Pick one patient per shift where you intentionally apply one of the caring practices with genuine attention. Notice what changes. The framework is not going to transform your entire shift overnight, and it is not going to work if you treat it as poetry rather than a practical guide. The version of this framework you will find in most nursing textbooks is the Nursing as Caring framework published through Pearson. The core texts are Nursing as Caring: Reflections on the Theory and Its Practice and The Theory of Caring: Reflective and Relational Practice in Nursing. There is no single software download or tool associated with it. It is a conceptual framework, not a product. Any site claiming to offer a download of the theory itself is misunderstanding what it is.