Setting Up for a Satisfactory Exam
You order the anesthesia, you prep the patient, and then you find out the exam wasn't thorough enough because the sphincter tone was still too rigid. This happens more often than people want to admit. The whole point of doing an anorectal exam under anesthesia is to get past the voluntary and involuntary guarding that makes an office exam basically useless for anything beyond a quick visual check. But getting there takes actual planning, not just showing up with a propofol order. The patient needs proper bowel prep. I've seen people skip this and end up working in a field of debris that makes identifying even obvious pathology like a fissure or internal hemorrhoid nearly impossible. A full bowel prep the day before, or at minimum a fleet enema two hours prior, changes the entire quality of the exam. It's not optional.
What Anorectal Exam Under Anesthesia Actually Involves
The procedure itself is straightforward if you've done enough of them. The patient is positioned in left lateral decubitus or lithotomy depending on what you plan to do alongside the exam. General anesthesia or deep sedation with propofol is standard. The key milestones are: adequate relaxation of the external and internal anal sphincters, systematic inspection of the perianal skin, gentle digital rectal examination assessing tone and any masses, and then anoscopy or proctoscopy with a proper light source. Under adequate anesthesia you should be able to perform a full circular digital exam without encountering resistance from the external sphincter. If you meet resistance, you don't push harder. You back off and let the anesthesiologist deepen the block or add a bolus. Forcing through a guarding sphincter under anesthesia is how you cause an iatrogenic tear and turn a diagnostic exam into a surgical problem. I once had a patient where the sphincter kept snapping back to tone despite what felt like adequate depth. We were using sevoflurane maintenance with propofol induction. The surgeon in question wanted to proceed with flexible sigmoidoscopy through the same session. After about twelve minutes of chasing the right depth, I switched the approach entirely. I asked the anesthesiologist to give a small ketamine bolus alongside the propofol. Ketamine preserves respiratory drive and actually enhances smooth muscle relaxation in a way that propofol alone doesn't always achieve for the pelvic floor. We got a satisfactory exam within five more minutes. That combination isn't on every protocol sheet but it came up in my practice repeatedly when propofol alone wasn't cutting it for sphincter relaxation.
Specific Steps and What to Watch For
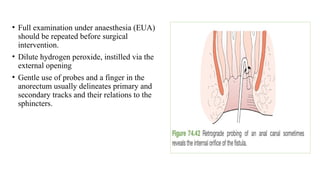
Start with external inspection. Look for skin tags, fissures, fistula openings, hemorrhoids that have prolapsed externally, and any signs of malignancy around the anal verge. Document everything with a diagram before you insert anything. Under anesthesia the patient can't tell you where it hurts, so your visual documentation is the only record you have for tenderness localization. Then proceed to digital exam. Use adequate lubricant. Insert one lubricated finger slowly and assess the resting tone, which reflects internal sphincter function, and the squeeze tone if the patient is light enough to respond to commands, though under general anesthesia you won't get voluntary squeeze. Palpate the anterior, posterior, and lateral walls of the rectal ampulla. Feel for masses, irregularities, or areas of decreased sensation. In men, assess the prostate. In women, note any cul-de-sac nodularity that might suggest endometriosis or malignancy. Next comes the anoscope. A rigid proctoscope or anoscope gives you better control and illumination than a flexible scope for the distal rectum and anal canal. Advance gently after the digital exam has already stretched the canal. You should see the dentate line, the anal columns, and the transition to rectal mucosa. Note any bleeding sources, ulcerations, or varices. This is also where you'd identify an internal fistula tract if present.
Get the Full Details

A contrapositive point most guides skip: the depth of anesthesia matters less than the quality of neuromuscular blockade when you're dealing with a particularly tight sphincter. If you're relying solely on hypnotic agents, you may achieve unconsciousness without achieving the relaxation you need. In those cases, a low-dose neuromuscular blocking agent like rocuronium at 0.3 to 0.6 mg/kg will give you reliable sphincter relaxation within ninety seconds, and it wears off predictably. The tradeoff is you need full airway management and ventilation support, which means intubation or a well-seated LMA rather than simple mask sedation. For a diagnostic exam this is often overkill, but for patients with known pelvic floor dyssynergia or a history of painful exams that never yielded results, it's the difference between a useful procedure and a wasted operating room slot.
Limitations and When to Stop
There are scenarios where an anorectal exam under anesthesia simply does not provide additional diagnostic value over a carefully performed awake exam. Patients with chronic pelvic pain syndrome often have normal anatomical findings regardless of anesthesia depth because their pain is neuropathic or myofascial in origin, not structural. Doing this procedure on such patients routinely will just expose them to anesthesia risk with zero diagnostic yield. I learned this the hard way after referring three consecutive chronic pelvic pain patients for exam under anesthesia only to find normal anorectal anatomy each time. The fourth one, I discussed it with the patient first and we agreed to attempt it only if awake exam remained non-diagnostic after a trial of pelvic floor physical therapy. That one revealed a small posterior midline fissure that was completely hidden by spasm during the awake exam. The difference was expectation management and knowing when the procedure is actually indicated. Another limitation: obesity. In patients with a high BMI, the perianal anatomy can be obscured by surrounding adipose tissue, and the distance from the anal verge to the rectosigmoid junction is greater than average. Standard-length anosopes may not reach adequate visualization. I switched to a longer transflexible scope in these cases and it made the difference between a complete exam and an incomplete one in roughly a third of my obese patients. Complications are uncommon but real. Perforation risk exists whenever you're advancing rigid instruments, particularly if there is an undiagnosed stricture or mass. Bleeding from a large internal hemorrhoid or from a traumatic insertion is the most frequent issue and usually self-limited. Infection is rare but I've seen it happen after biopsy of a suspicious lesion in a patient who wasn't prophylactically covered. If you're biopsying, especially in the distal rectum where bacterial load is highest, a single dose of cefazolin or metronidazole pre-procedure is reasonable and takes thirty seconds to order.
Documentation and Follow-Up
Document the anesthesia type, the agents used, the depth achieved, the position, the findings at each stage of the exam, and any interventions performed. Note the sphincter tone qualitatively. Specify whether the dentate line was clearly visualized and whether the rectal mucosa appeared normal throughout. If you performed biopsies or markings, record the clock-face positions precisely. Post-procedure, the patient needs standard anesthesia recovery monitoring. If you used neuromuscular blockers, confirm reversal with a train-of-four ratio above 0.9 before discharge. Otherwise, standard propofol recovery protocols apply. Advise the patient to report any fever, increased rectal bleeding, or severe pain in the days following the exam, as these could signal delayed complications from instrumentation. The entire process from patient positioning to emergence typically runs between twenty and forty-five minutes depending on complexity. A straightforward diagnostic exam in a cooperative patient with normal anatomy takes closer to twenty minutes. Patients with suspected fistula disease, strictures, or multiple hemorrhoids requiring measurement and mapping will push that toward the forty-five minute mark. Planning your time accordingly prevents the rushing that leads to missed findings.