Functional Anatomy You Actually Need
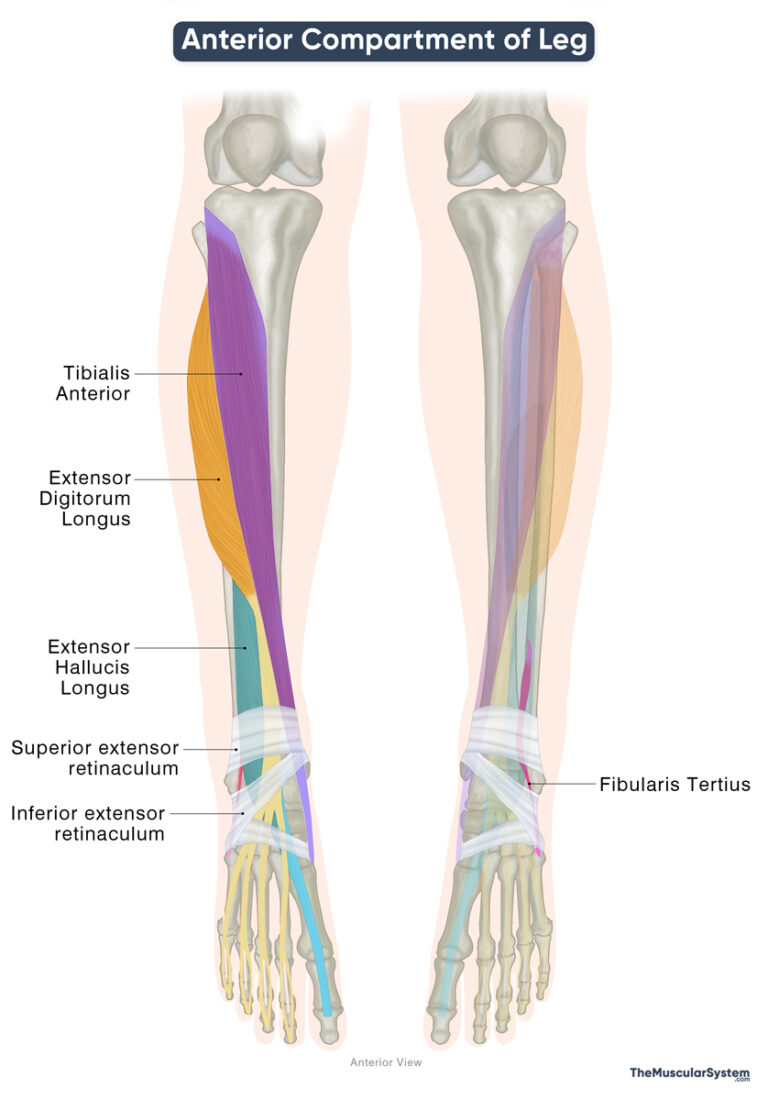
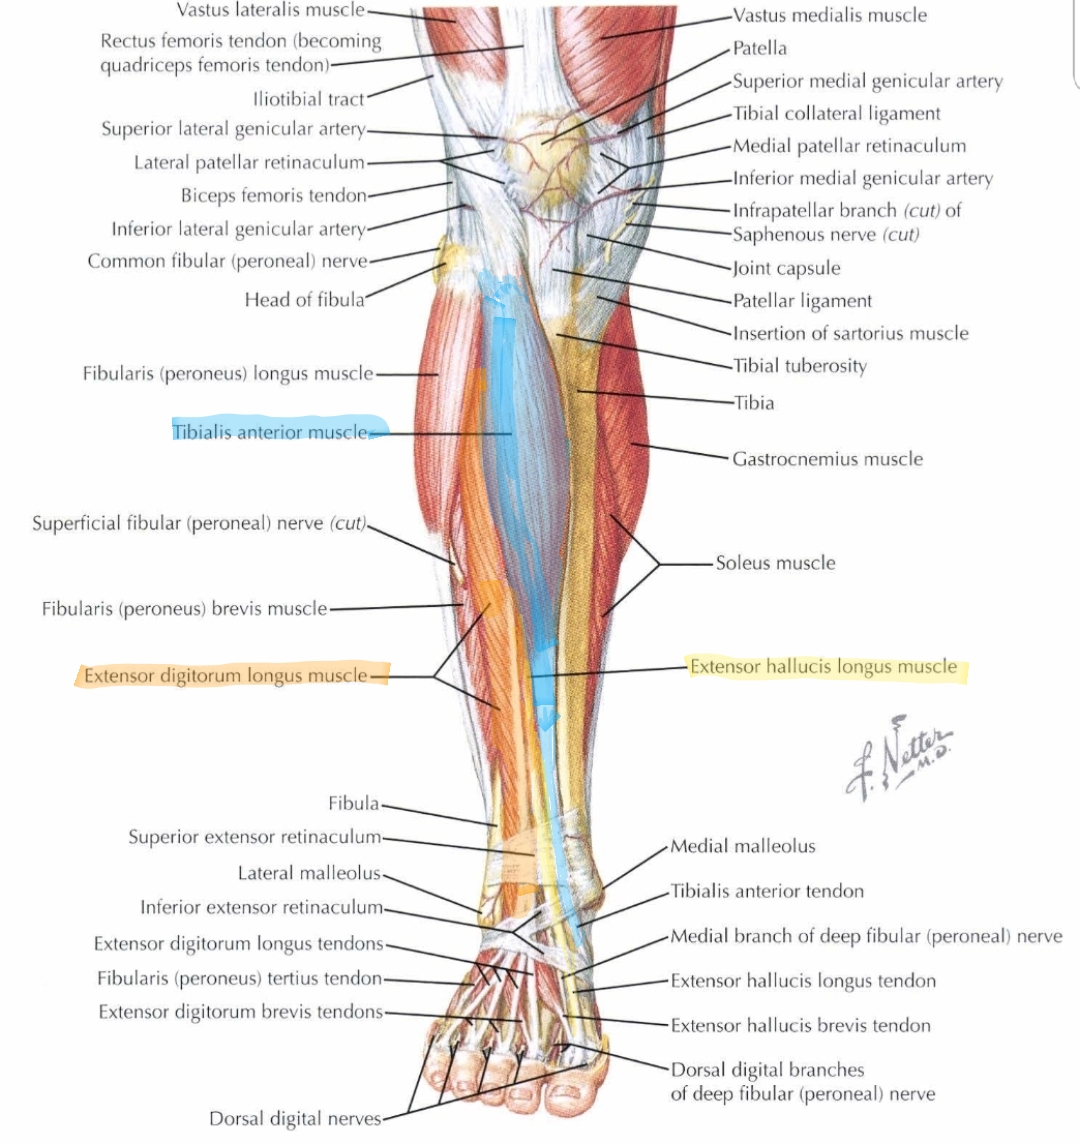
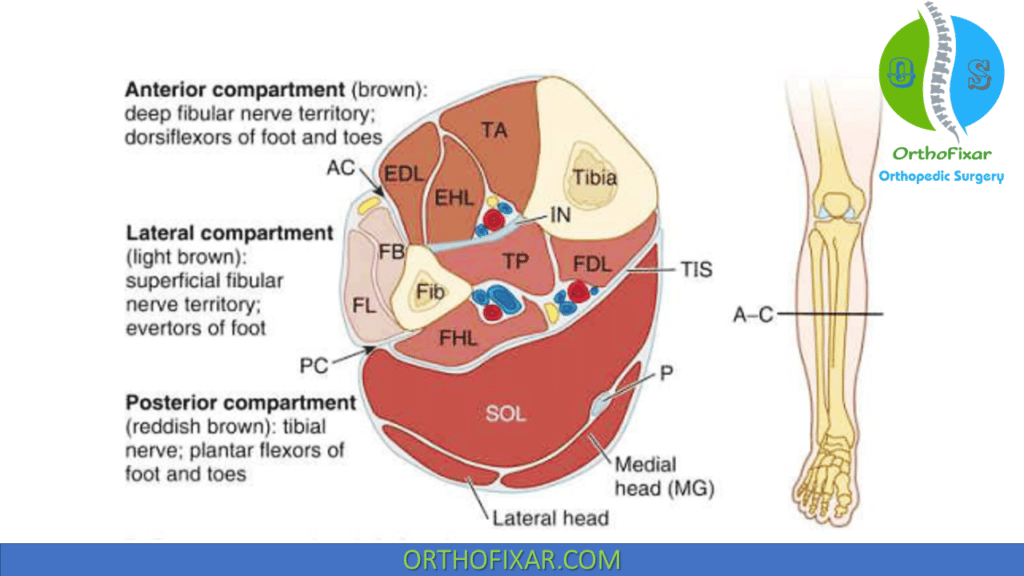
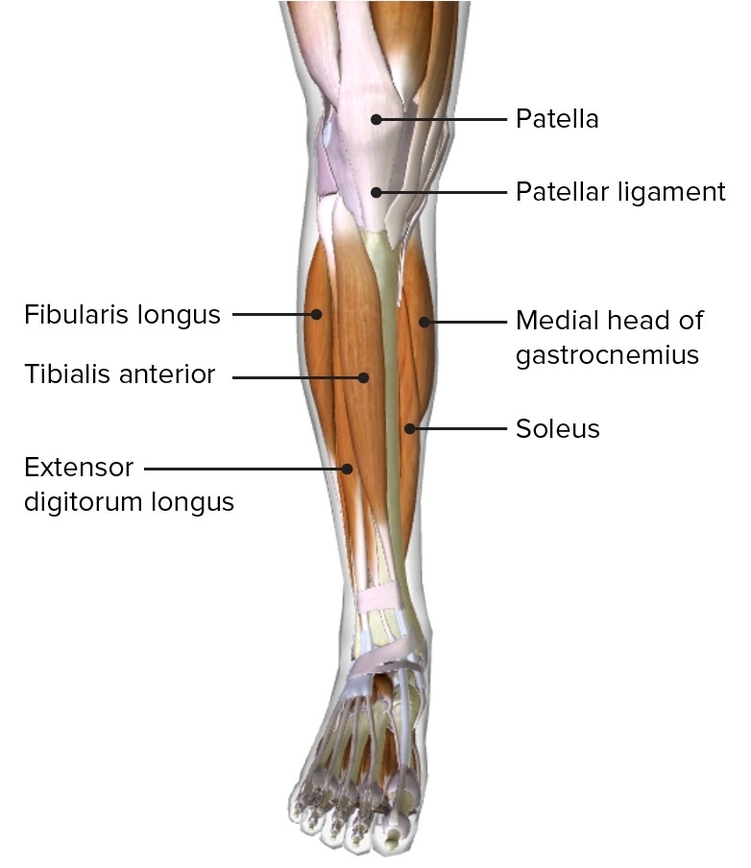
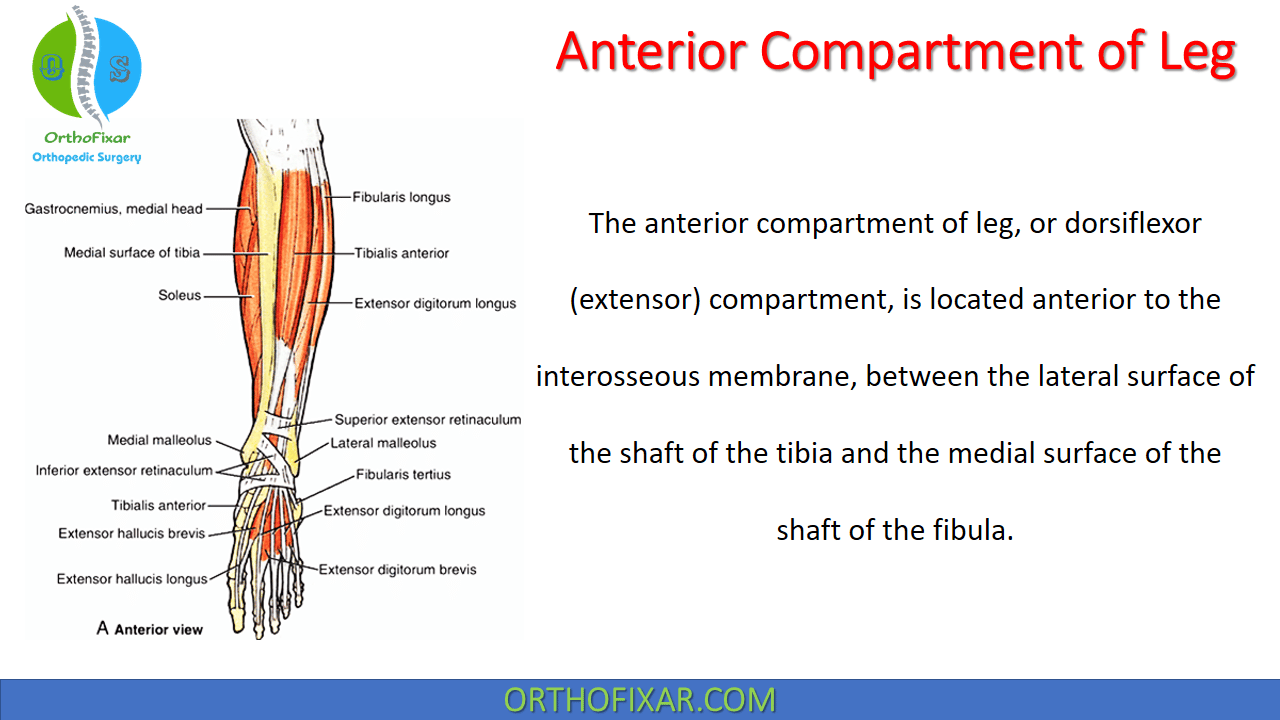
The anterior compartment of the leg sits between the tibia and fibula, bounded posteriorly by the interosseous membrane and anteriorly by the deep fascia. It contains four muscles: tibialis anterior, extensor digitorum longus, extensor hallucis longus, and peroneus tertius. All of them are innervated by the deep fibular nerve, which comes off the common fibular nerve at the fibular neck and threads forward through the compartment. The blood supply runs with it—anterior tibial artery, a branch of the posterior tibial artery that passes through the proximal interosseous membrane. This compartment does dorsiflexion and inversion of the foot. That's it. When you walk, the tibialis anterior fires during the swing phase to keep your toes from dragging. The extensor digitorum longus and extensor hallucis longus extend the toes. Peroneus tertius is small and sometimes absent, but it assists in dorsiflexion and eversion. Simple job, simple anatomy. Complicated when something goes wrong.
Approaching the Anterior Compartment Of Leg in Clinical Practice
I've been doing this long enough to know that surface anatomy here is misleading. The tibialis anterior belly is obvious on most people, but its tendon isn't where you'd expect. It inserts on the medial cuneiform and base of the first metatarsal, and it passes deep to the superior extensor retinaculum at the level of the malleoli. If you're palpating for pulse or planning an incision, don't rely on the muscle belly alone. Track the tendon distally from the anterosuperior iliac spine down the lateral edge of the tibia and confirm by having the patient dorsiflex against resistance. Here's a practical problem I ran into with a patient presenting with foot drop after a knee injury. The common fibular nerve was the issue, not the anterior compartment itself. People see weakness in dorsiflexion and assume compartment syndrome, but that patient had intact compartments and no pain on passive stretch. The nerve injury was at the fibular neck from the trauma. I checked for sensation over the first web space, tested the extensor hallucis longus separately from tibialis anterior, and traced the nerve proximally before sending them for an MRI. Missed that distinction and you're looking at unnecessary fasciotomy work. Another thing that trips people up: the deep fibular nerve has a sensory branch. It innervates the skin between the first and second toes. If you're assessing nerve function, don't just test motor. A patient can have preserved dorsiflexion with isolated sensory loss and still have nerve pathology. I've seen post-op charts where the nerve was documented as intact because the motor response was there, but the patient had persistent numbness in that web space. That's a missed diagnosis.
The anterior compartment is confined by bone on the medial and lateral sides and the interosseous membrane posteriorly. This means any swelling inside it has nowhere to go. Compartment pressure monitoring is the standard here, not visual inspection. Normal pressure is below 10 mmHg. Above 30 mmHg with symptoms is the threshold where I'd be considering fasciotomy. But numbers alone don't make the call. Pain out of proportion, pain on passive stretch of the toes, paresthesia in the deep fibular distribution, and pallor or pulselessness late in the game—that's the clinical picture. Pulses don't disappear until compartment pressure exceeds arterial pressure, which is late and dangerous to wait for. One more counter-intuitive point: crural fascia thickness varies enormously between individuals. In some people, the anterior compartment is well-separated by a thick band of fascia. In others, the boundary is thin and vague. This matters if you're doing surgical exposure. I've had cases where I planned a standard interval approach between tibialis anterior and extensor digitorum longus, only to find the septum was nearly absent. The planes were sloppy. I adjusted by using the muscle bellies themselves as landmarks and staying closer to the bone to protect the peroneal tendon sheath on the lateral side. You can't rely on textbook descriptions of fascial septa here. Explore first, commit second. Summary of key points
Get the Full Details

Deep fibular nerve injury presents with foot drop but preserves ankle sensation via the superficial fibular nerve. Always test both nerves independently. Compartment syndrome is a clinical diagnosis. Pressure measurements help but shouldn't delay intervention when the clinical picture is clear. Anterior tibial artery runs with the deep fibular nerve and is at risk during any anterior surgical approach to the proximal tibia. Tibialis anterior tendon rupture is rare but happens in middle-aged patients with chronic tenosynovitis. It presents as sudden weakness in dorsiflexion with a palpable gap above the medial malleolus. Surgical repair within two weeks gives significantly better outcomes than delayed reconstruction.