Why your lower back keeps hurting despite "fixing" your posture
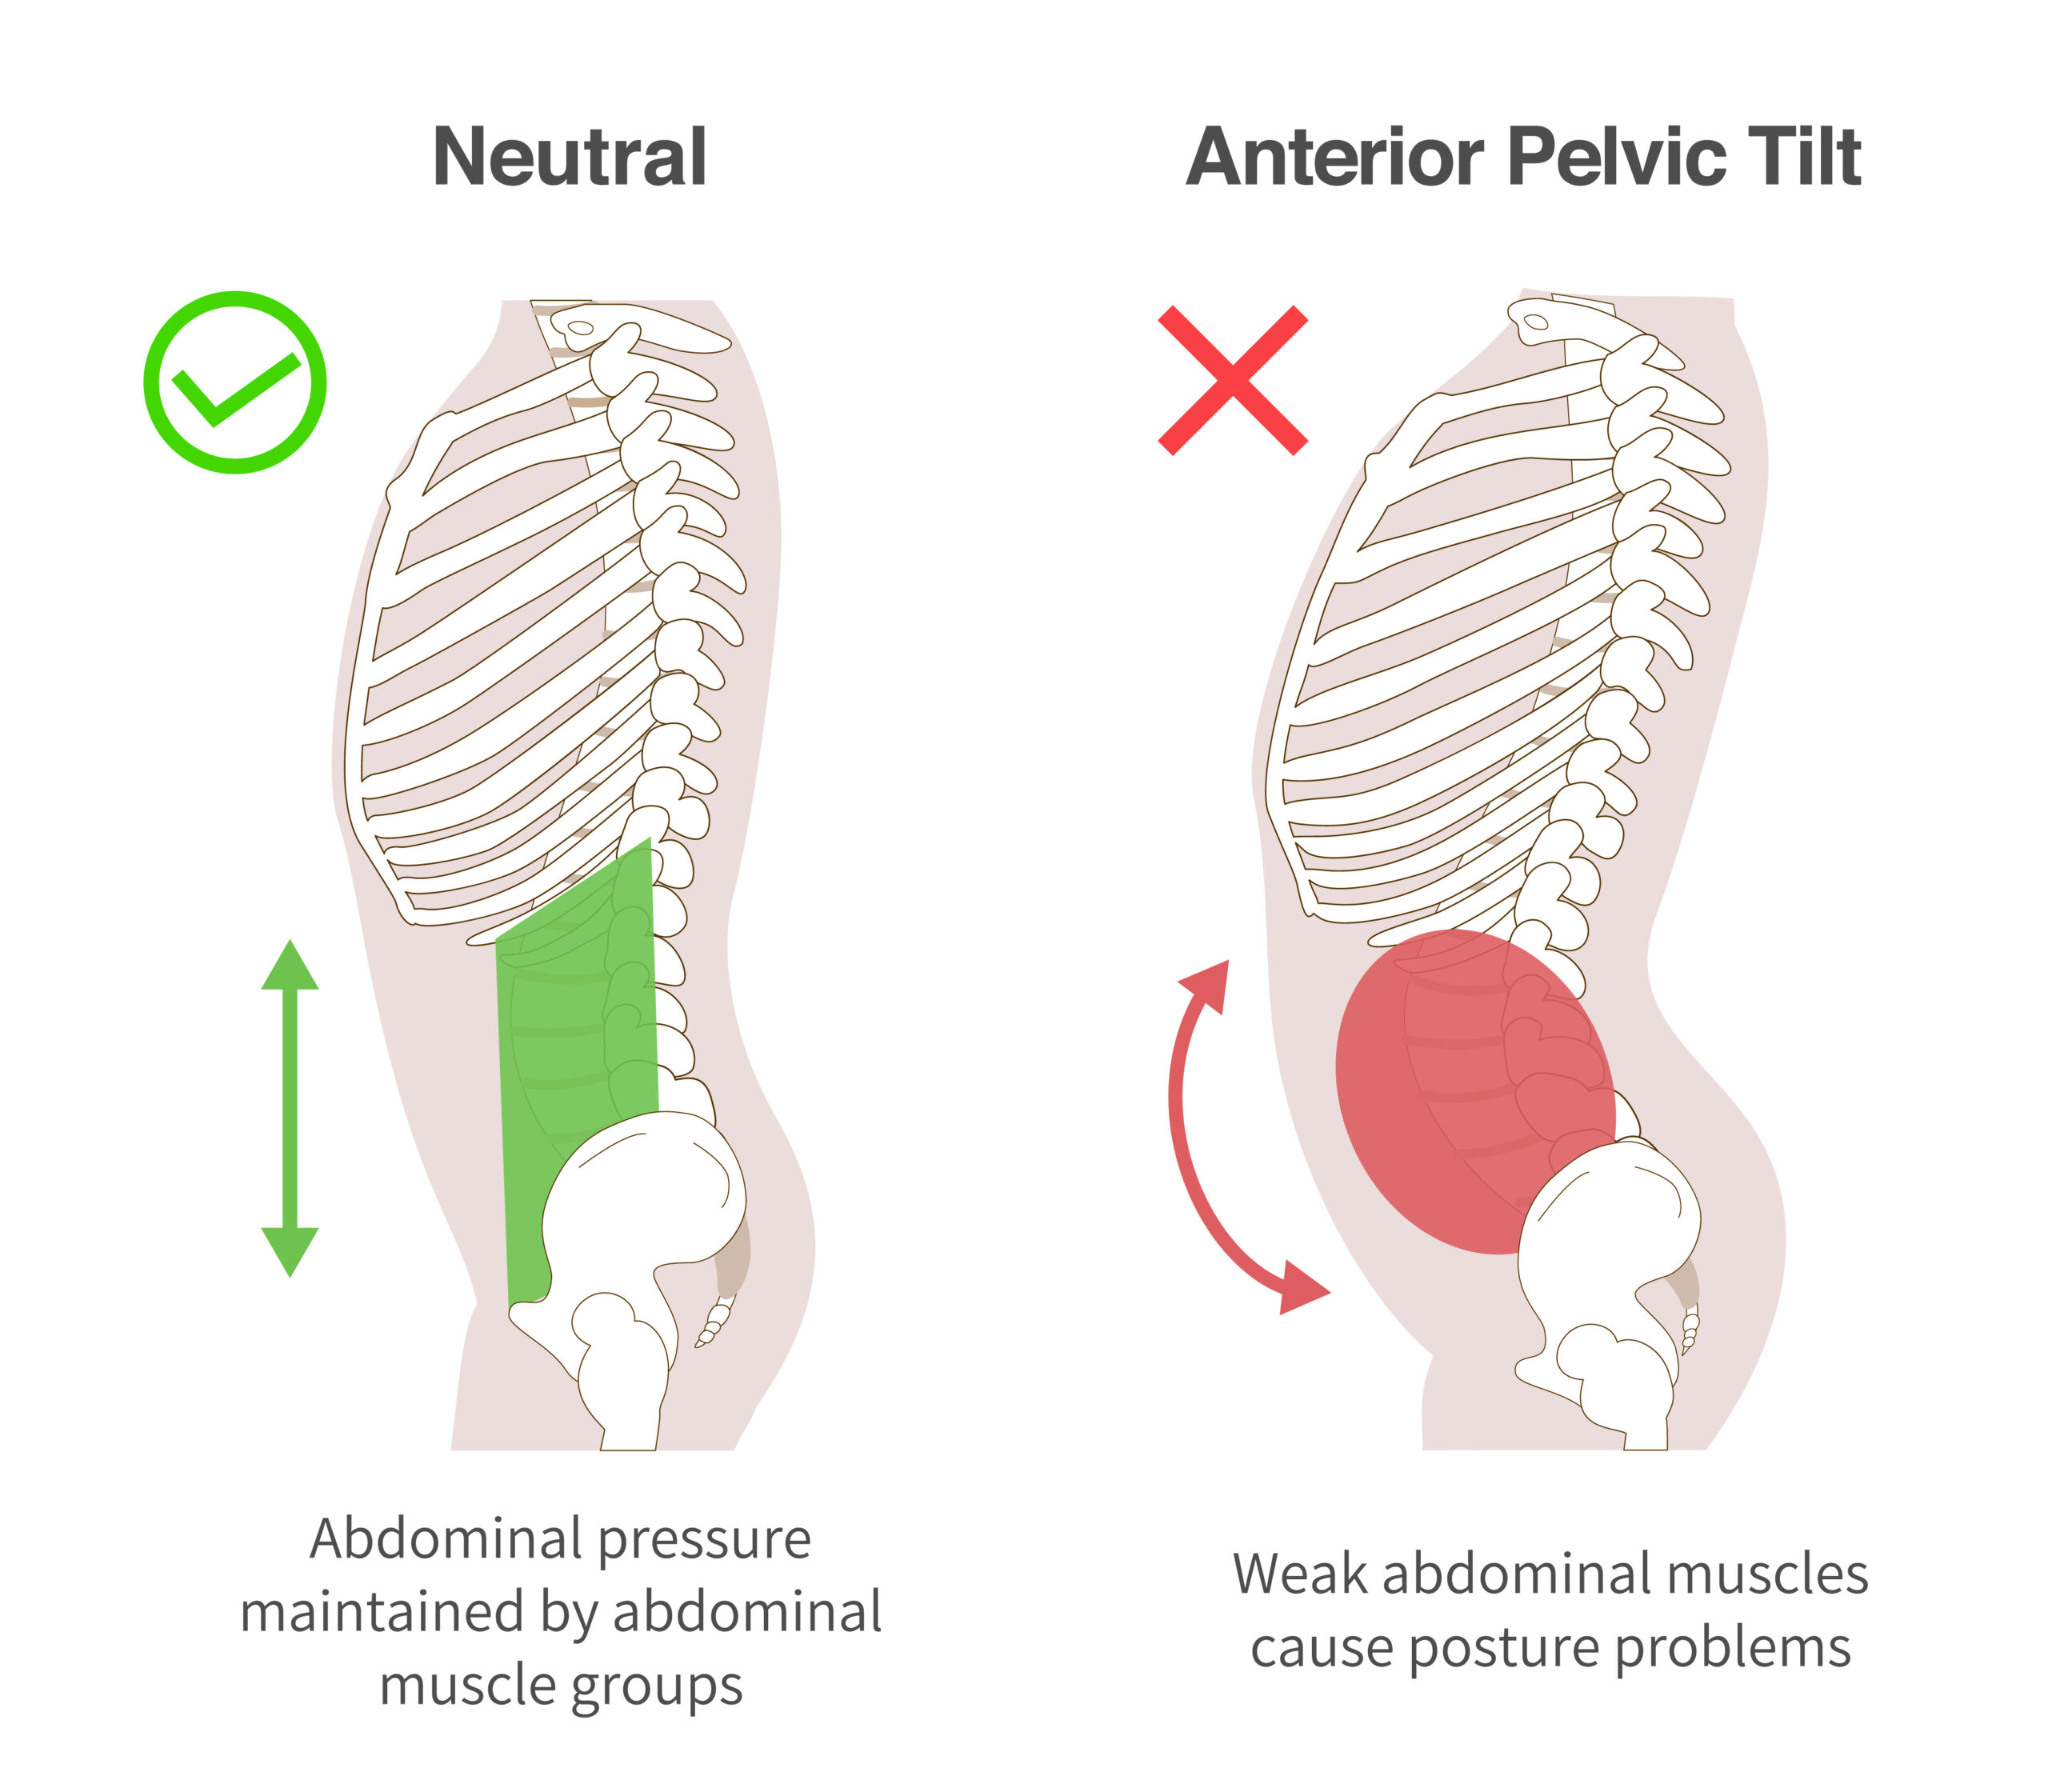
Most people who come to me with anterior pelvic tilt have already tried everything. They've watched the YouTube videos about tight hip flexors and weak glutes. They've done the stretches. They've even bought those silly posture-correcting braces. And still, six weeks later, their lower back is just as achy as before. The problem isn't that they're doing it wrong. It's that they're treating the symptom and ignoring the actual mechanical bottleneck. Anterior pelvic tilt is essentially a postural positioning issue where the pelvis rotates forward. The top of the ilium tips ahead, the sacrum tucks under, and the lumbar spine exaggerates its natural lordotic curve. On paper it sounds straightforward. In practice, it's one of the most stubborn clinical presentations I deal with because the pelvis doesn't just sit there. It drives everything above and below it. Hip extension gets limited. Knee tracking changes. Thoracic mobility suffers because the ribcage compensates for the lumbar overextension. You can stretch the hip flexors until your arms give out, but if the underlying motor control pattern hasn't shifted, the tilt comes right back.
What Anterior Pelvic Tilt Physical Therapy actually involves
Physical therapy for anterior pelvic tilt isn't a single intervention. It's a layered approach that prioritizes what most people skip. Here's the breakdown from how I actually run it in the clinic. Phase one is assessment and tissue mobilization. I need to know whether the tilt is structural or postural. Structural means there's a bony or contractural component that won't change with exercise. Postural means the muscles are imbalanced but movable. I check this with a simple standing observation first, then measure the angle between the ASIS and the pubic symphysis relative to a vertical plumb line. If the difference is less than 5 degrees between standing and supine, it's primarily postural. Anything more suggests a structural contribution, and the treatment changes significantly. The tissue work I do most often is self-myofascial release on the psoas major and the rectus femoris. Not the iliacus. The psoas. Most people confuse the two. The psoas crosses the lumbar vertebrae directly. When it's shortened and hypertonic, it literally pulls the lumbar spine into hyperextension, creating that exaggerated arch. I have clients use a lacrosse ball against a wall, positioned about two inches lateral to the navel, leaning just enough to find the tender spot. Twenty seconds per side. Three rounds. It's not comfortable. It's supposed to be uncomfortable. But it's also not permanent. The tissue will rebound within 24 to 48 hours unless you pair it with the next phase.
Phase two is strengthening in lengthened positions. This is where most programs fail. They tell people to do glute bridges and clamshells while the hips are flexed or neutral. That's not the problem position. The pelvis is tilted forward when you're standing, when you're walking, when you're squatting. You need to train the glutes and hamstrings to fire when the hip is extended, not just when it's neutral. Romanian deadlifts at a light weight, three sets of eight, twice a week, with a deliberate pause at the top where the hips are fully extended and the glutes are squeezed. Not a bounce. A pause. The nervous system needs to register the end range before it'll recruit the muscle there on its own. Phase three is motor control retraining during functional movement. I use something called posterior pelvic tilt marching. You lie on your back, knees bent at 90 degrees, press the lower back into the floor by tilting the pelvis backward, and then alternate lifting one foot while maintaining that tilt. Ten reps per side. The moment the back arches again, you stop and reset. Most people can't do ten without losing form on rep six. That's the whole problem in a nutshell. The muscles work fine in isolation. They forget how to work together under load and in dynamic positions. I ran into a specific case about a year ago that illustrates this well. A client, mid-thirties, office worker, reported that her anterior pelvic tilt was manageable with stretching in the morning but progressively worsened through the day. Standard protocol didn't touch it. I spent two sessions trying different hip flexor releases, core work, glute activation. Nothing moved the needle. Then I noticed something odd. Her tilt was minimal when she sat with her feet flat on the floor, but dramatically worse when she sat with her feet elevated or dangling. The issue wasn't tight hip flexors. It was a weak iliopsoas that couldn't maintain hip extension against gravity when she stood. Her hip flexors weren't short. They were weak and inhibited. I switched from stretching to strengthening the psoas in standing using resisted hip raises with a light band anchored low. Three sets of six, holding each rep for five seconds at full extension. Within three weeks, her pelvic position had noticeably improved, and her lower back pain dropped from a six out of ten to a two. I'd been treating it as a flexibility problem when it was actually a strength and endurance problem. Classic mistake. Easy to make if you're following a standard algorithm without really looking at the person.
Get the Full Details

The counter-intuitive stuff nobody tells you
Here are a few things that will surprise you if you've only ever read blog posts about this. Stretching tight hip flexors won't fix anterior pelvic tilt if your abdominal wall is also weak or dysfunctional. The abs are what pull the pelvis back into a neutral position. If you've ever seen someone with a pronounced belly who also has an exaggerated lumbar curve, that's not a coincidence. The abs can't counteract the pull of the hip flexors when they're weak. Front planks are useless here because most people sag through the midsection and end up reinforcing the exact pattern you're trying to break. Dead bugs are better. Bird dogs are better still. The key is maintaining contact between the lumbar spine and the floor throughout the entire movement. If your lower back lifts even a centimeter, the exercise is over. Reset and try again with less range of motion. Another thing: not everyone with anterior pelvic tilt needs the same intervention. Some people have a genuinely flat back and an exaggerated lordosis because of a hip flexion contracture from years of sitting. Others have it because their glutes are so inhibited that the lumbar erectors take over the job of hip extension and spasm into overdrive. I've seen both. The first group responds to aggressive stretching and nerve glides for the femoral nerve. The second group needs neuromuscular re-education before any aggressive stretching. Doing the wrong thing first makes it worse. That's why the assessment phase matters more than any exercise you'll ever do.
There's also the question of footwear. People don't think about this, but a two-inch heel drop shoe worn daily will subtly encourage anterior pelvic tilt over time by keeping the ankle in plantarflexion, which cascades up the kinetic chain. Switching to a zero-drop shoe or barefoot training for even an hour a day can change the mechanical loading on the pelvis. I had a client whose tilt improved measurably after three weeks just from swapping his shoes. No other changes.
When this approach won't work
I need to be honest about the limitations. Anterior pelvic tilt physical therapy doesn't work for everyone, and it doesn't work fast. Even in ideal cases, you're looking at six to twelve weeks of consistent work before you see measurable postural change. Fourteen weeks before it starts feeling automatic. If you're only doing the exercises three times a week instead of four or five, double that timeline. It also fails completely when there's an underlying structural issue like spondylolisthesis, degenerative disc disease with significant facet joint arthritis, or a leg length discrepancy greater than half an inch. In those cases, stretching and strengthening won't reposition the pelvis. You'd need orthotics, bracing, or in some cases surgical consultation. A good physical therapist should rule these out first. If yours hasn't ordered imaging or referred you for it, find someone who will. Another hard limit: if your daily habits haven't changed, the tilt will return. You can do all the exercises in the world, but if you're sitting eight hours a day with poor posture and no breaks, the muscular imbalances will rebuild themselves. I always tell clients that the exercises are the renovation. The habit changes are the foundation. Skip the foundation and the house cracks again.

For people who've tried everything and still can't get relief, the next step is often a different type of practitioner. A osteopath or a skilled manual therapist can address fascial restrictions and joint dysfunctions that exercise alone can't touch. Sometimes the pelvis itself has a rotational fault that needs to be manually corrected before the muscles will cooperate. It's not a failure of physical therapy. It's a recognition that some problems need a different tool in the box.


