Memory Loss Isn't One Thing
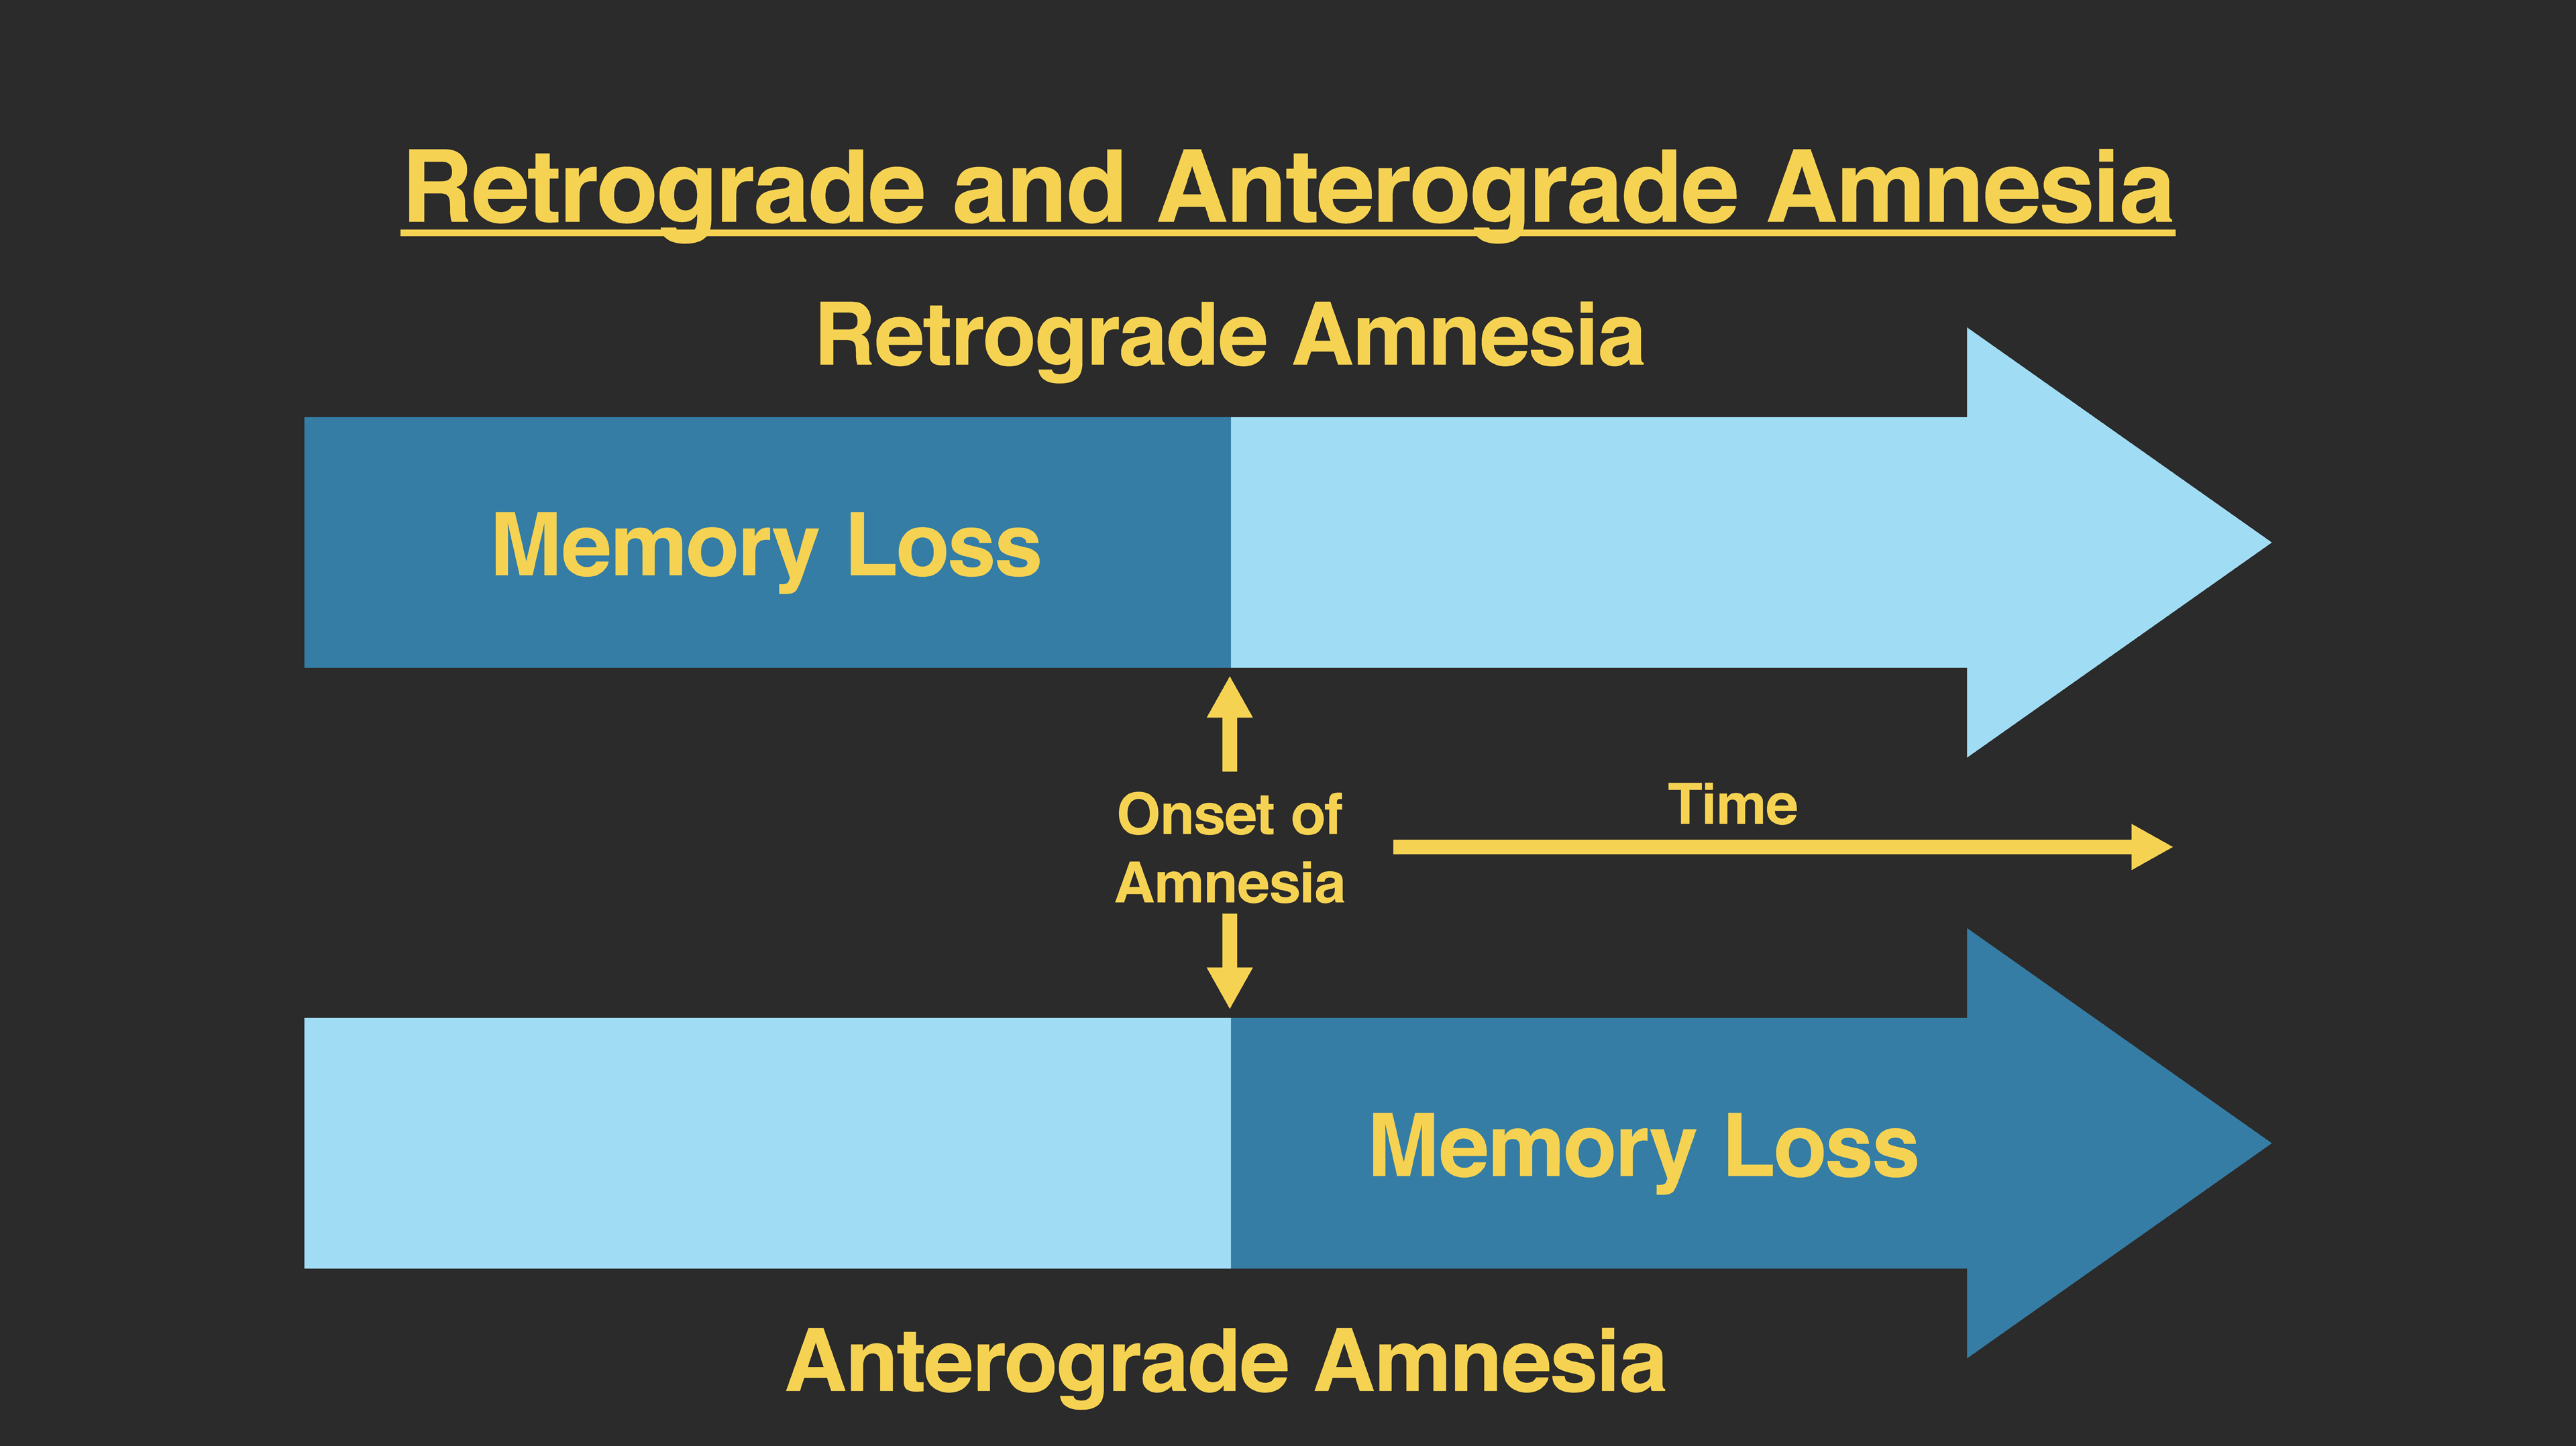
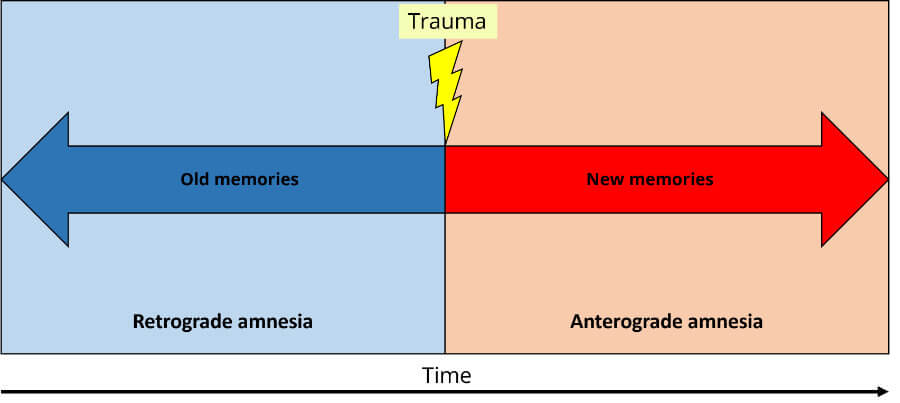
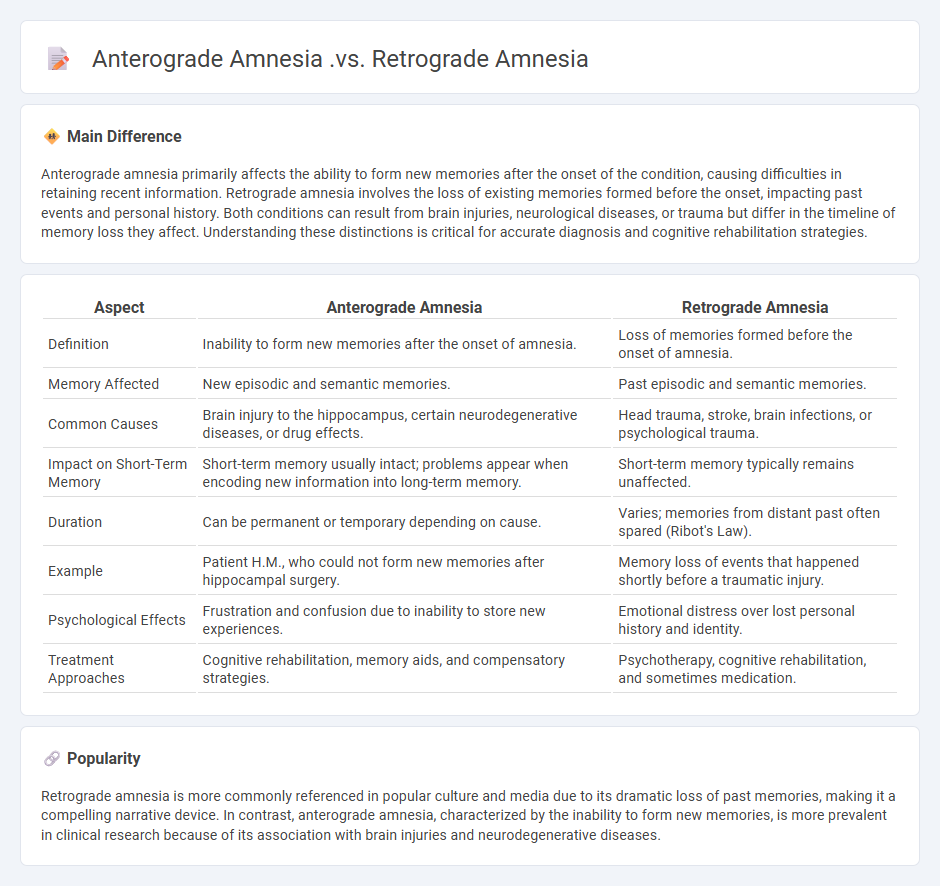
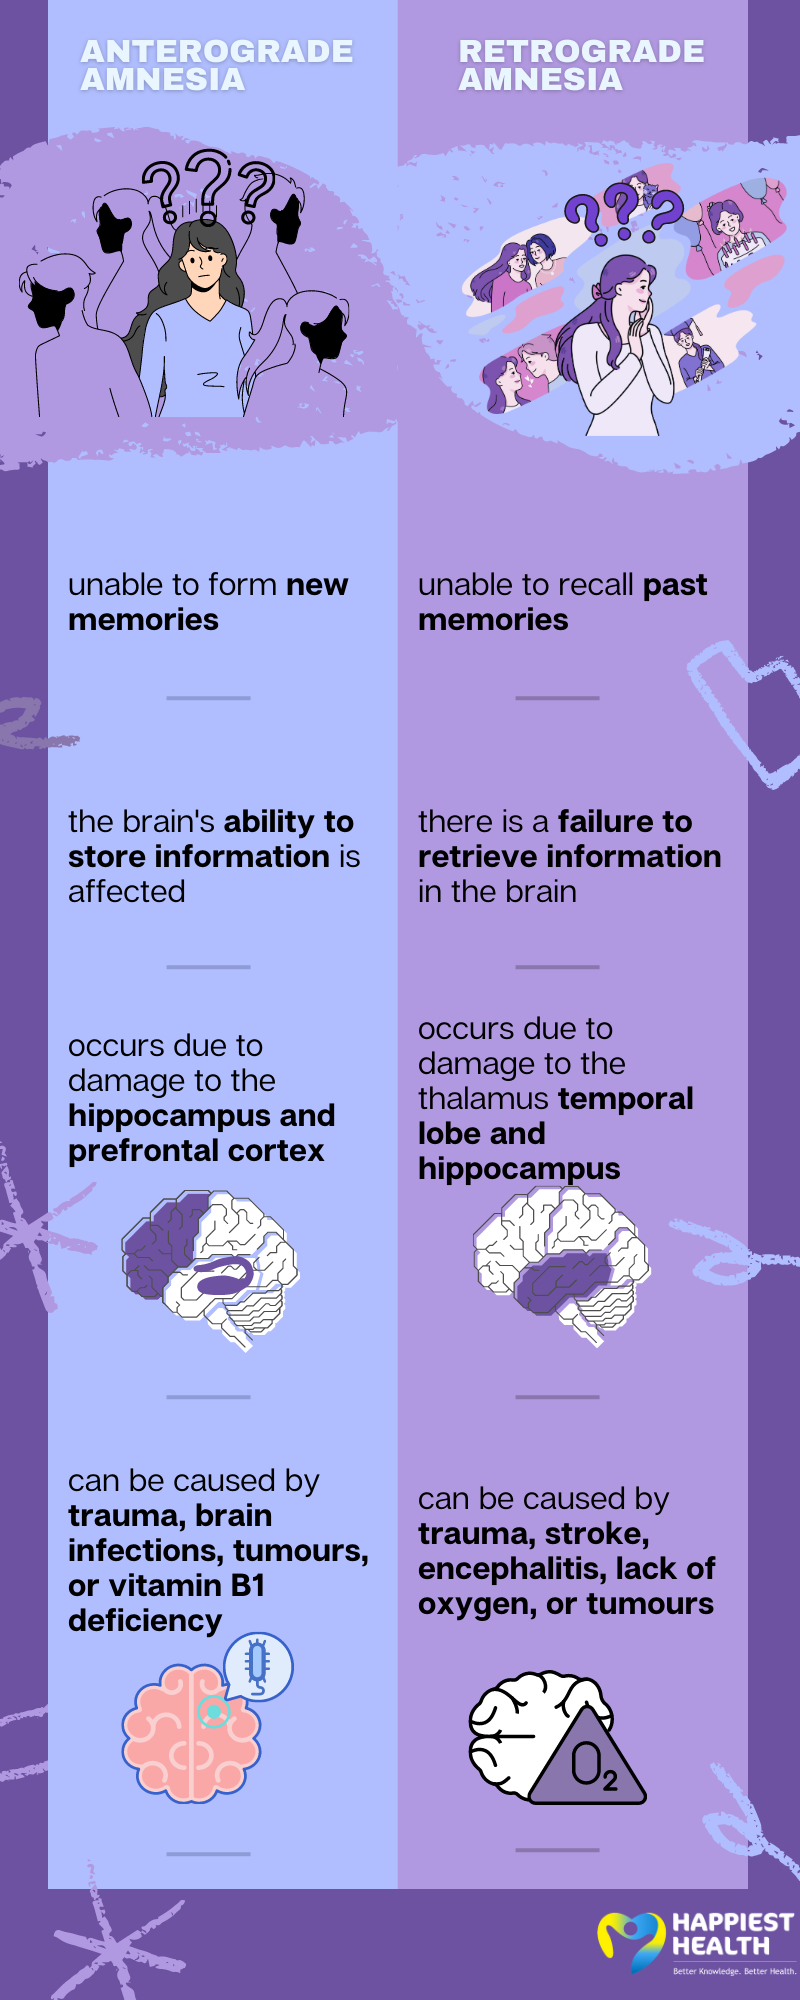
You will see people conflate anterograde and retrograde amnesia as if they are the same condition viewed from different angles. They are not. One is about losing the ability to lay down new memories, the other is about losing access to old ones. Getting them confused will get you in trouble fast, especially if you are dealing with a real case. Anterograde amnesia means your brain cannot convert new experiences into lasting memories. A person with it can walk into a room, have a conversation, eat a meal, and then moments later have no record any of it happened. It is not forgetfulness. It is a hardware-level failure to encode. Retrograde amnesia means memories that were already stored before the injury become inaccessible. The filing system is intact but the files are corrupt or gone. Time matters here. Recent memories are usually more vulnerable than remote ones. This is called Ribot's gradient and it shows up consistently across cases.
The two frequently overlap. A car accident or a bout of encephalitis can damage brain regions involved in both forward and backward memory functions. But they do not have to. There are documented cases of pure anterograde amnesia with only patchy retrograde loss and vice versa. The dissociation is clinically useful because it tells you which neural circuits are damaged and which are still working.
How to Tell Them Apart in Practice
The simplest way is to test both directions. Ask someone to learn a small set of word pairs, like table-red, chair-blue, lamp-green. Test recall after five minutes. If they score near zero, that points toward anterograde impairment. Then ask about childhood events, first day of school, what they had for breakfast yesterday. Incomplete or absent answers to the second set suggest retrograde involvement. I once worked with a patient whose family reported she could not remember her doctor's visit from the morning, but could recount details of her wedding from forty years earlier with vivid specificity. She also learned a new piano piece through repetition over several sessions without ever consciously remembering practicing it. That was procedural memory surviving while declarative memory failed. The distinction between those systems matters more than people realize.
Get the Full Details
What Actually Causes Each Type
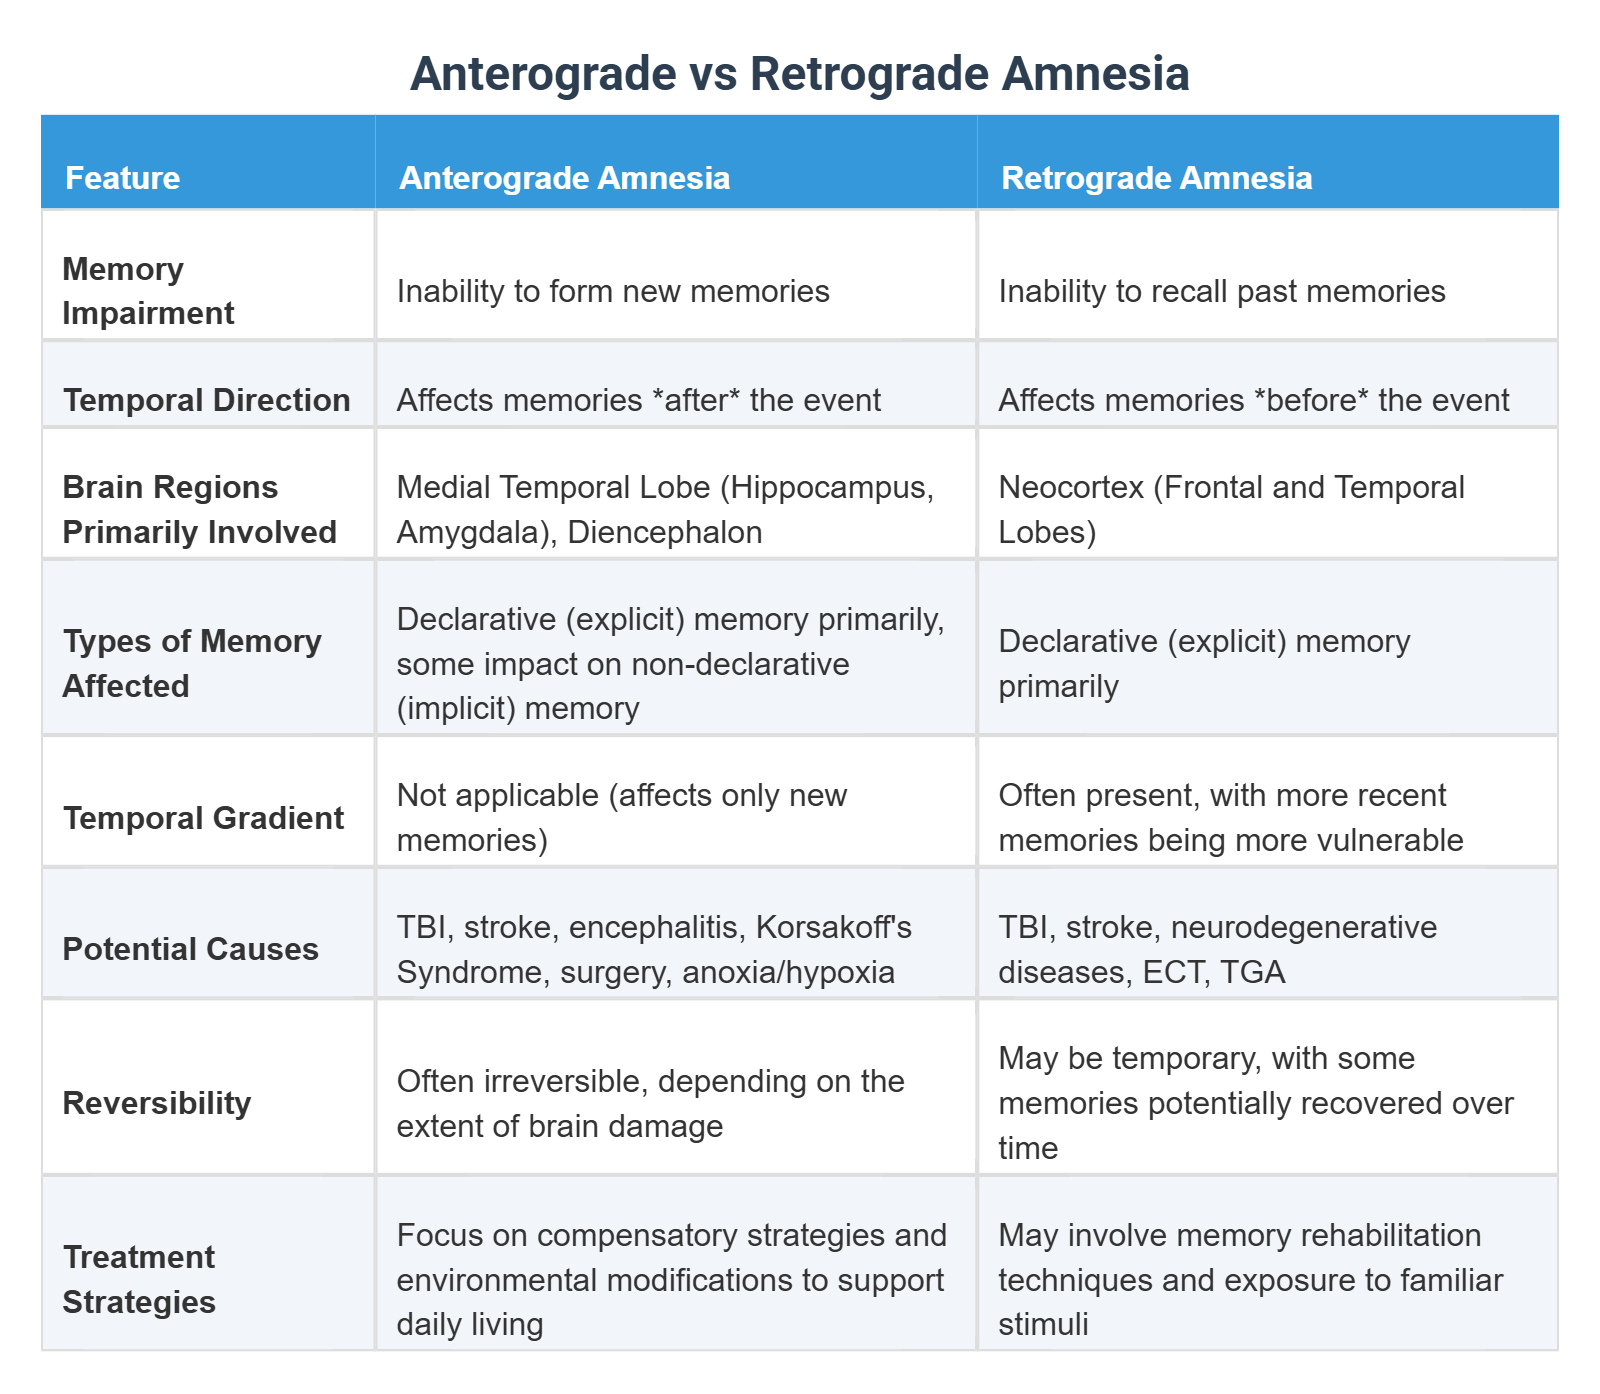
Anterograde amnesia most commonly involves the hippocampus and surrounding medial temporal lobe structures. Bilateral damage here produces the classic pattern. Herpes simplex encephalitis has a particular tropism for the temporal lobes and is one of the leading causes of severe permanent anterograde amnesia. Ischemia from the posterior cerebral artery affects the same territory. Chronic alcoholism with thiamine deficiency produces Korsakoff syndrome, which is largely anterograde with some retrograde components. Retrograde amnesia tends to involve broader networks. The cortex stores consolidated memories in distributed patterns, so widespread damage can wipe out large chunks of the past. Hypoxic events, diffuse axonal injury from trauma, and certain neurodegenerative diseases follow this pattern. The temporal gradient usually holds, but it is not universal. Some cases show flat retrograde loss across all time periods, which suggests the consolidation process itself was disrupted rather than just retrieval pathways being damaged.
Common Pitfalls That Beginners Miss
One big mistake is assuming that retrograde amnesia gets progressively worse over time. It does not. Unlike a tumor growing or a degenerative disease spreading, retrograde amnesia from a single insult is generally stable. The lost memories do not keep disappearing months later. What changes is that the gap between the injury date and the present grows, so the proportion of life without memory shrinks. That is a psychological effect, not a neurological progression. Another mistake is confusing confabulation with memory loss. Confabulation is when the brain fills gaps with fabricated memories, usually without intent to deceive. It is most common in Korsakoff syndrome and some frontal lobe injuries. A patient might confidently describe events that never happened. That is not the same as failing to retrieve a real memory. Treating the two identically leads to wrong management decisions. Here is the part nobody warns you about: surface-level testing can miss partial retrograde amnesia. A standard MMSE or even a full neuropsychological battery might show normal recall if the test uses familiar material. The deficit only shows up when you use personally meaningful, episodic memories. I learned this the hard way when a patient scored within normal limits on hospital admission tests but could not name what he had for dinner the previous three days or recall his daughter's last visit. We ended up using a structured autobiographical interview with calendar prompts and that is when the retrograde gaps became obvious. Standard tools are blunt instruments for this kind of damage.
Handling the Overlap Cases
Most real patients sit somewhere in the middle. They have trouble forming new memories and also lost some older ones. The clinical priority is determining the severity of each component separately because rehabilitation strategies differ. Anterograde impairment responds to compensatory external memory aids. Retrograde impairment is harder to address directly since you cannot rebuild stored traces easily. For anterograde support, I rely on a combination of smartphone reminders, photo journals, and a dedicated notebook that the patient carries at all times. The key is making the system frictionless. If it takes more than thirty seconds to record or check something, compliance drops dramatically. I also train caregivers to provide context cues at transitions. A simple statement like "you are here because you have a follow-up appointment" repeated at each shift change reduces disorientation more than people expect. Retrograde work is mostly about reconstruction. Family photos, music from specific eras, and guided life narrative sessions can help anchor identity. This does not restore lost memories. It rebuilds the scaffolding around them so the remaining traces have somewhere to latch onto. The emotional benefit is real even if the factual recovery is limited.
When Treatment Fails Completely
Severe bilateral medial temporal lobe damage produces anterograde amnesia that is essentially permanent. There is no pharmacological intervention that restores encoding capacity at that level. Benzodiazepines and scopolamine can temporarily worsen encoding in healthy brains, which confirms how fragile the mechanism is, but no drug reverses established damage. Cognitive rehabilitation improves adaptation, not the underlying deficit. Retrograde amnesia from hypoxic injury sometimes shows partial spontaneous recovery over twelve to eighteen months as inflammation resolves and neural networks reorganize. But the recovered memories are usually fragments, not full narratives. Anyone promising complete memory restoration for established amnesia is not being honest. The science does not support it. If you are looking for resources or tools to support someone managing these conditions, the Alzheimer's Association and Brain Injury Association of America both maintain updated guides on memory aids and caregiver strategies. Those are more practical than trying to find clinical protocols online, which tend to be either too technical or too vague to use.