What actually happens when you inject anti-VEGF into the eye
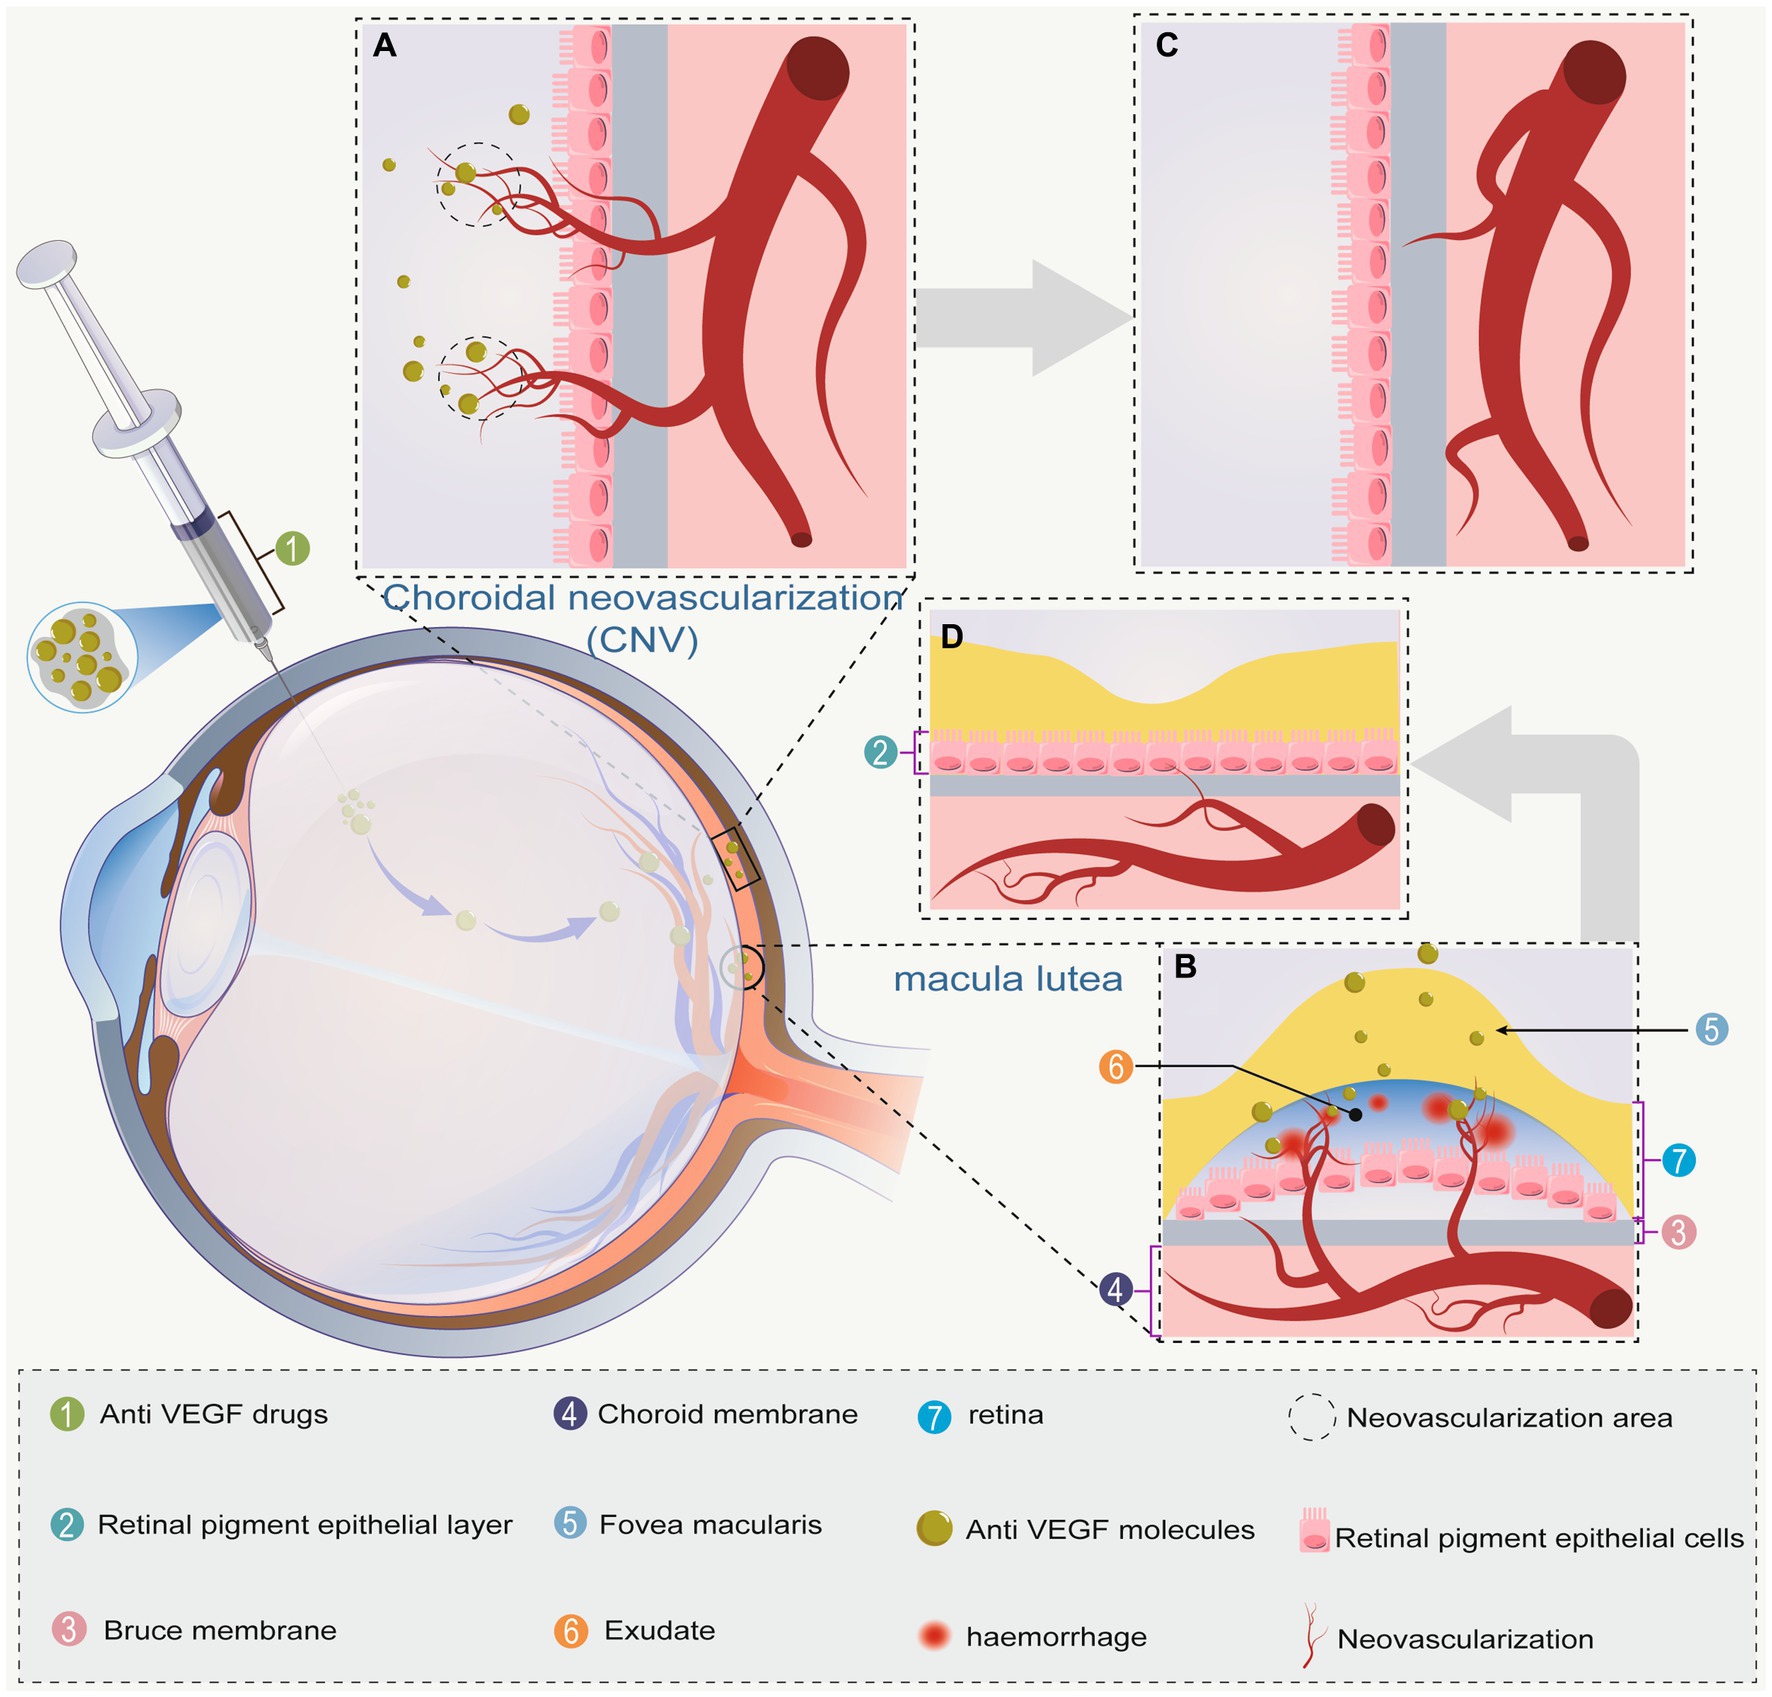
Most people reading about this therapy are either patients trying to understand what their ophthalmologist is doing or caregivers helping someone navigate the treatment schedule. Either way, the clinical reality is fairly mundane once you strip away the fear factor. Anti VEGF Therapy For Macular Degeneration involves intravitreal injection of a monoclonal antibody or protein fusion compound directly into the vitreous cavity of the eye. The target is vascular endothelial growth factor, a signaling protein that drives abnormal blood vessel growth and leakage. In wet age-related macular degeneration, those vessels grow where they should not and leak fluid or blood onto the retina, blurring central vision. The drugs you will encounter most often are ranibizumab (Lucentis), aflibercept (Eylea), and bevacizumab (Avastin). Bevacizumab is technically approved for cancer but is used off-label in ophthalmology at a fraction of the cost. Faricimab (Vabysmo) is the newer option that targets both VEGF-A and Ang-2 pathways. Brolucizumab (Beovu) exists but carries a higher incidence of intraocular inflammation, so many clinicians avoid it as a first-line choice.
The injection procedure and what to expect week to week
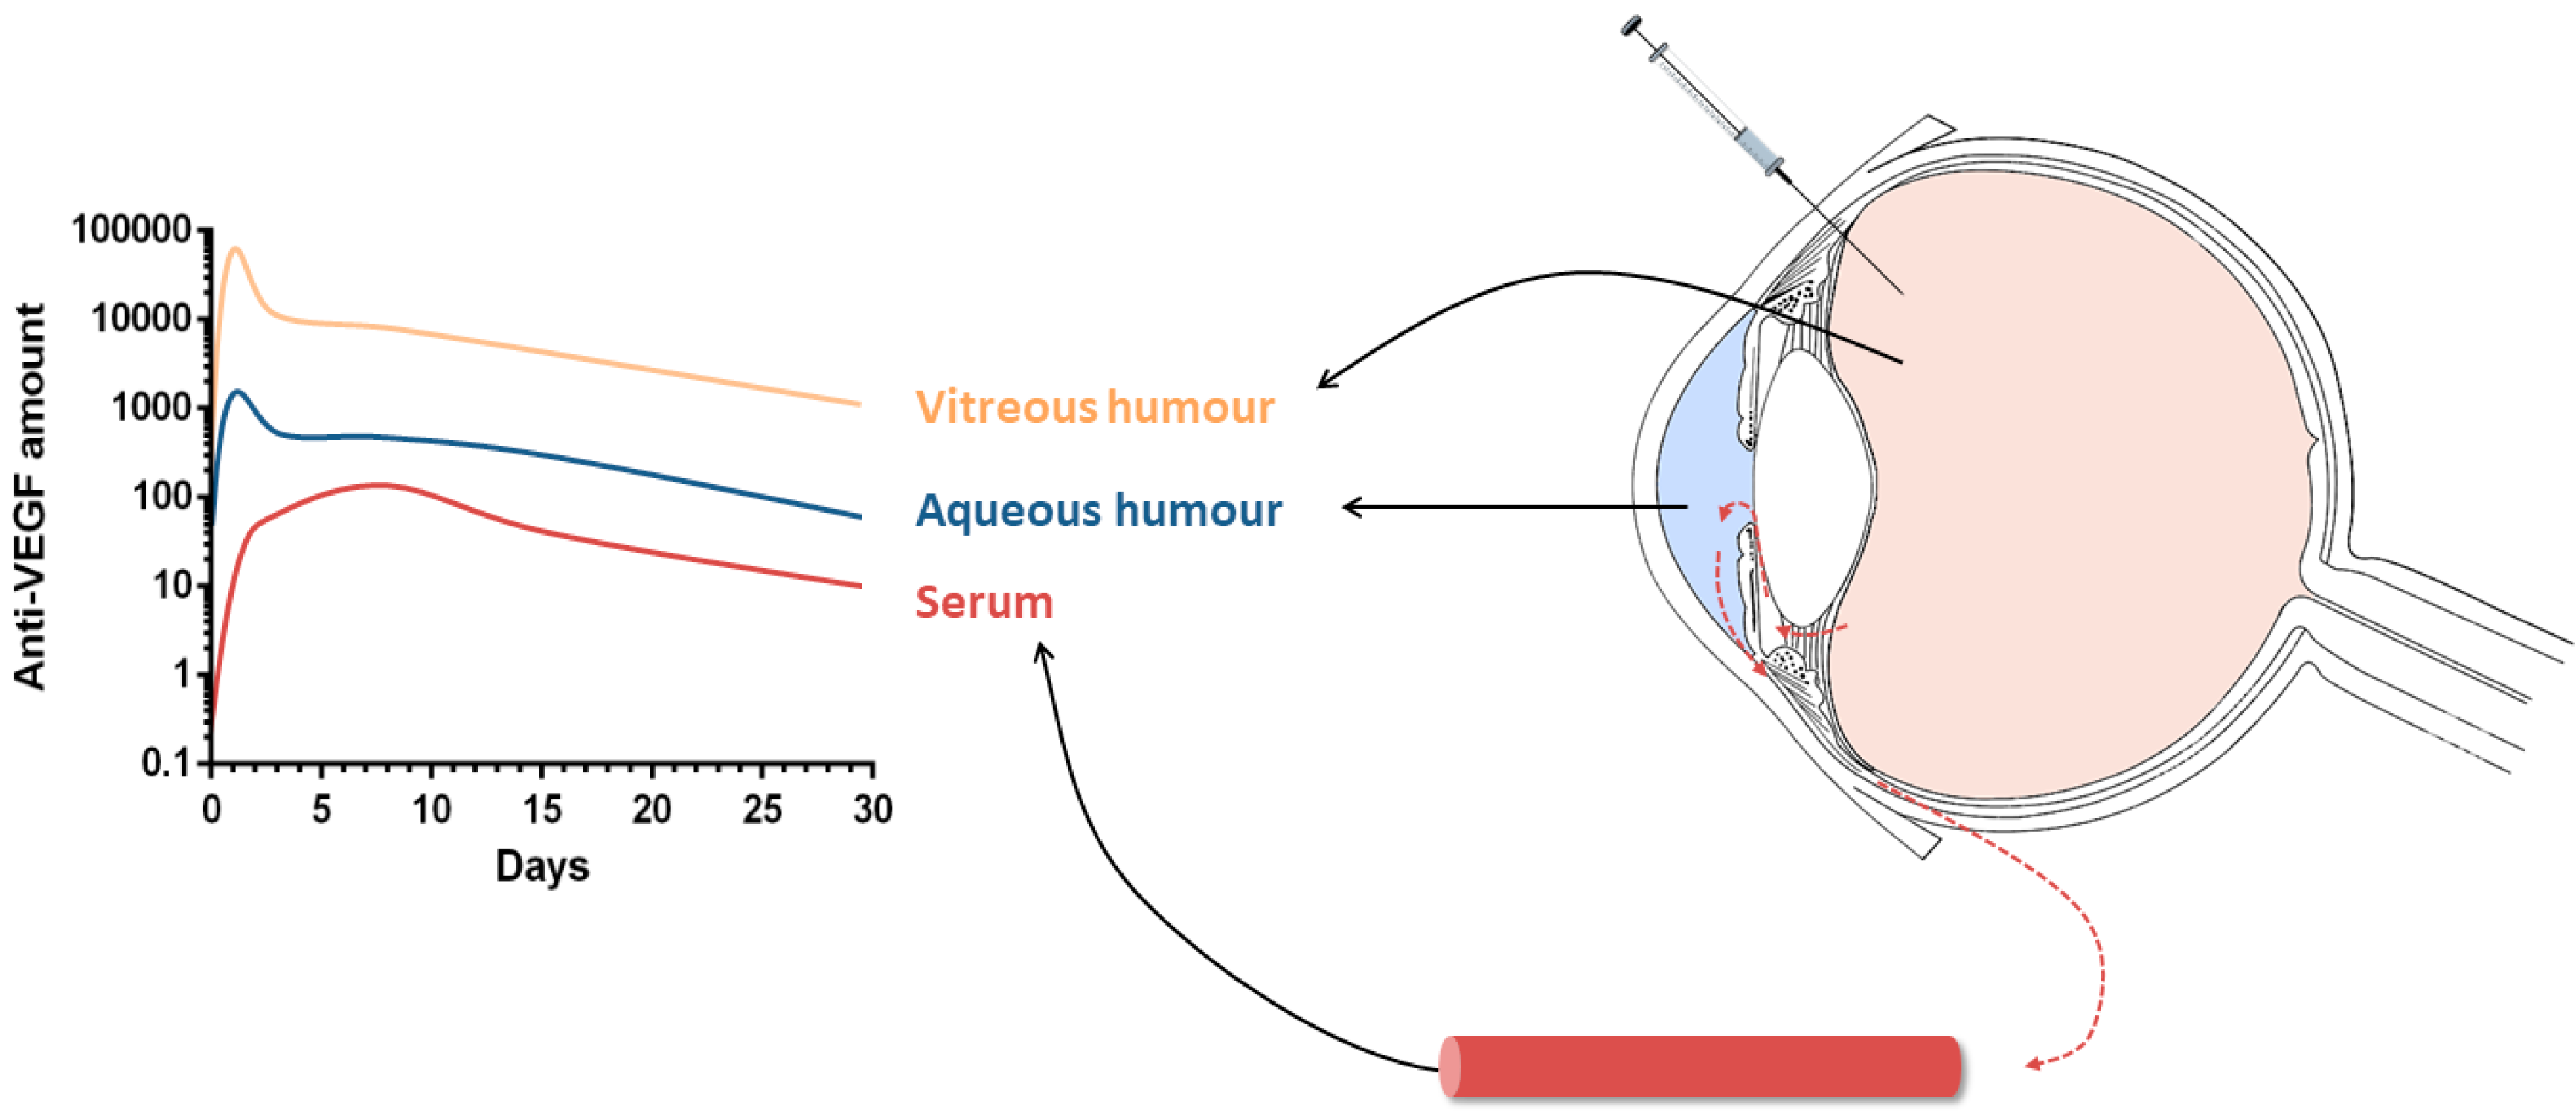
I have sat through more of these procedures than I care to count, mostly as a consultant reviewing imaging for clinical trials and case audits. The actual injection takes maybe thirty seconds once the eye is prepped. Topical anesthetic drops go in first. Then a speculum holds the eyelids open. The injection site is usually the superior temporal quadrant, about 3.5 to 4 millimeters posterior to the limbus, entering through the pars plana. A 30-gauge needle penetrates the sclera and delivers roughly 0.05 mL of medication into the vitreous. That is it. The whole visit runs about fifteen to twenty minutes from start to finish. The dosing schedules vary by drug. Ranibizumab traditionally uses a treat-and-extend approach, starting with monthly injections and gradually lengthening the interval if the eye stays dry. Aflibercept follows a similar model but often allows longer intervals between doses. Bevacizumab protocols tend to be more aggressive initially, sometimes monthly for three to four doses, then extended. Faricimab has shown the ability to maintain quiescence at eight-week intervals in a significant portion of patients in the BALCONY and YOSEMITE trials. I once had a case where a patient kept developing cystoid macular edema right at the end of each treat-and-extend cycle, consistently at week nine regardless of which drug we used. Switching to a fixed eight-week schedule with faricimab resolved it. The takeaway is that the individual response timeline matters more than any published protocol. You do not have to wait for the textbook interval to decide something is not working.
How the drugs actually work inside the eye
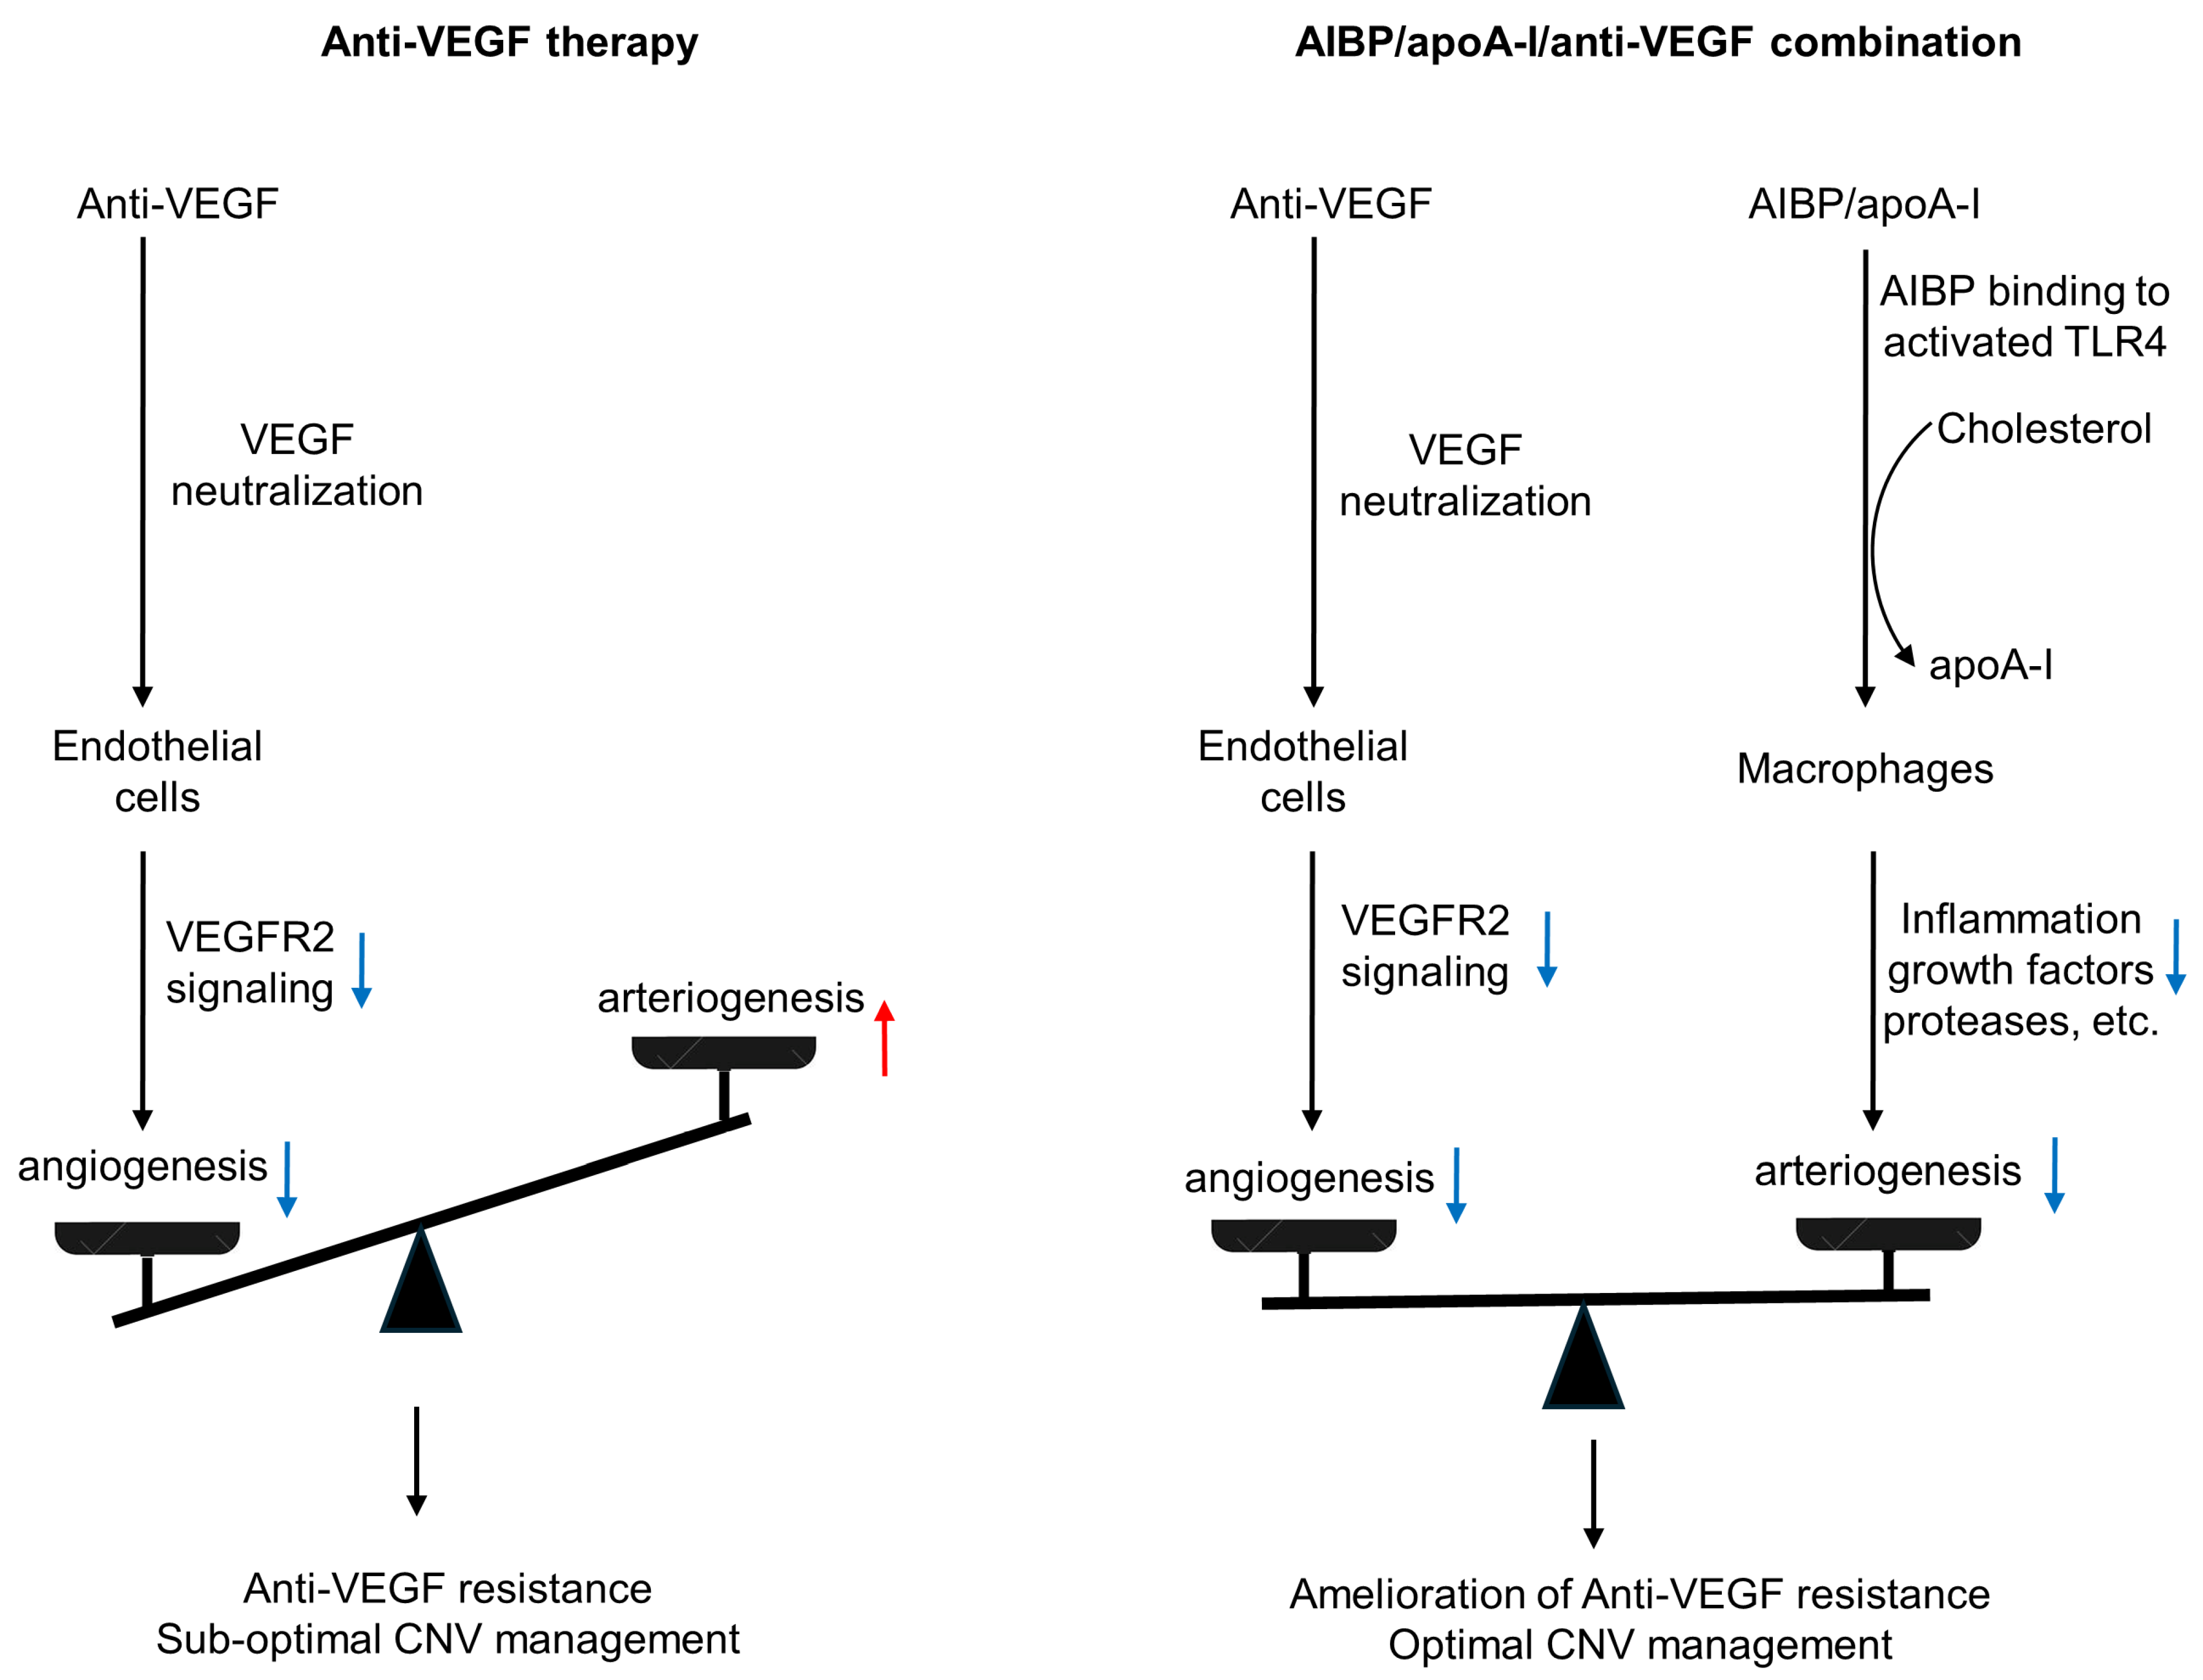
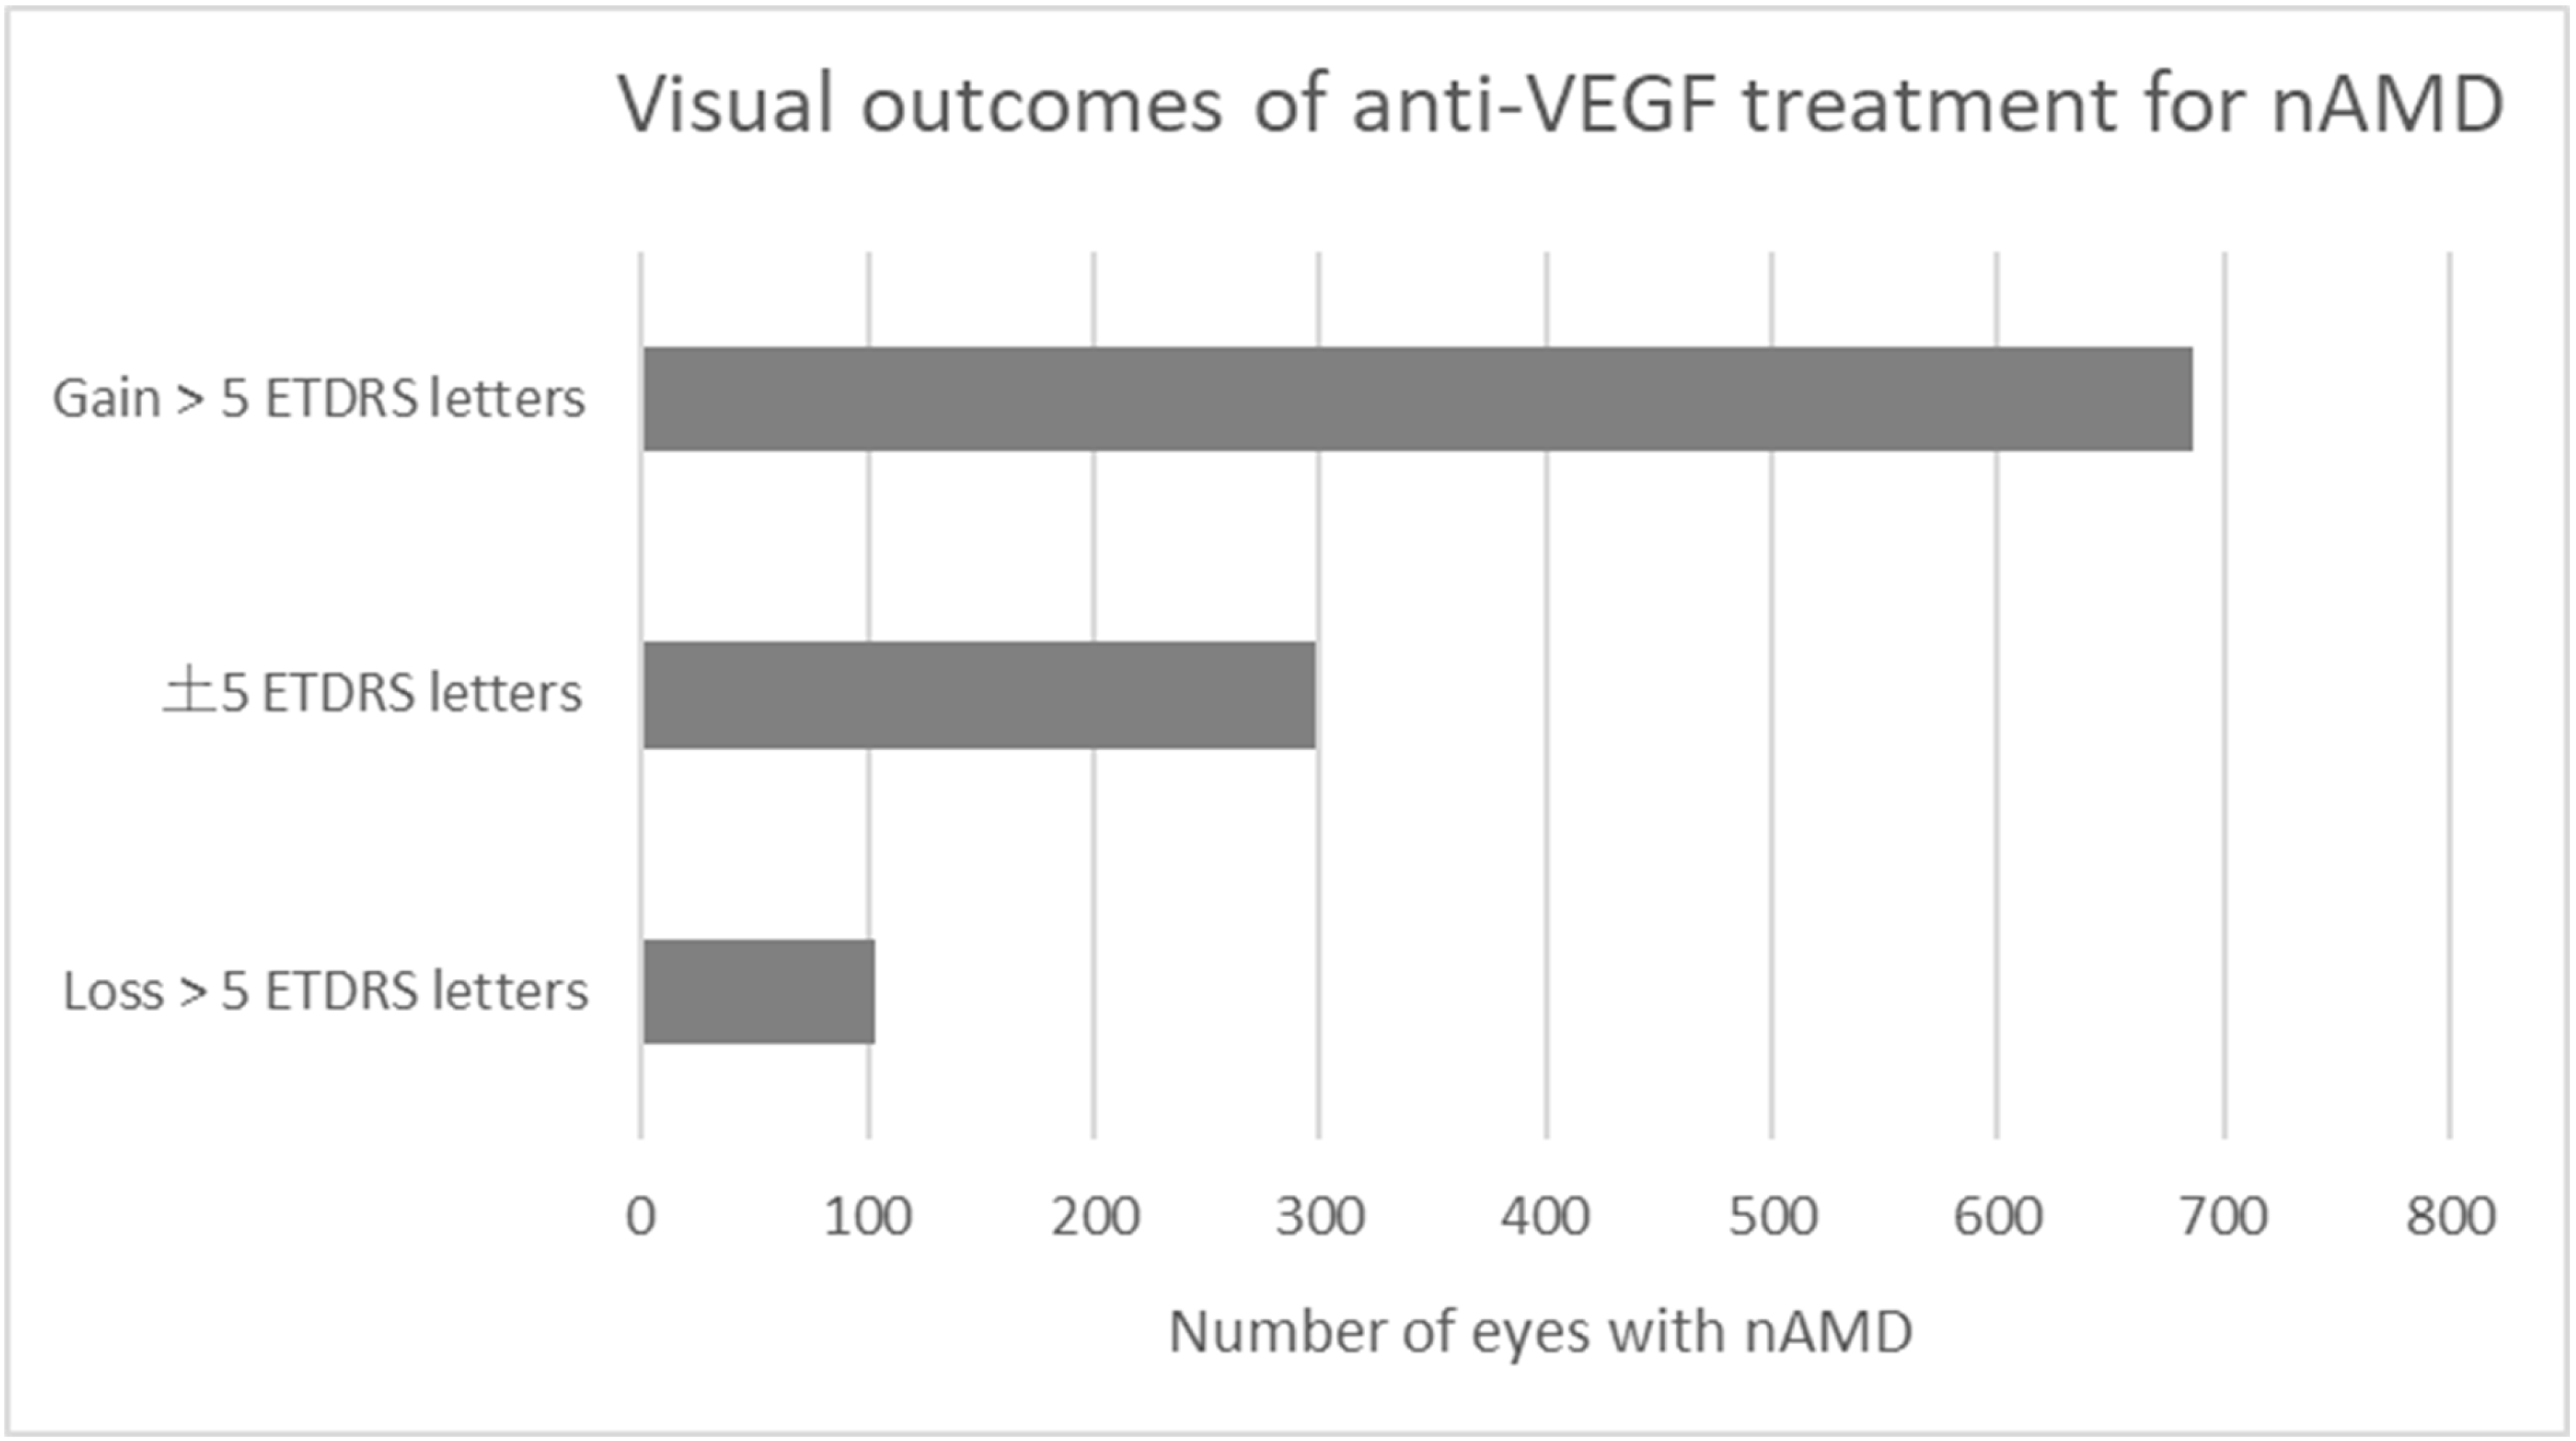
VEGF-A binds to receptors VEGFR-1 and VEGFR-2 on endothelial cells. This signaling triggers proliferation, migration, and increased vascular permeability. In AMD, hypoxia and other stressors in the subretinal space upregulate VEGF expression, and the resulting neovascular membrane compromises the blood-retina barrier. The anti-VEGF agents neutralize this process by binding the ligand or its receptor directly. Ranibizumab is a Fab fragment that binds VEGF-A with high affinity. It is smaller than the full antibody, which theoretically allows better tissue penetration but also means it clears faster from the vitreous. Aflibercept is a fusion protein acting as a decoy receptor, soaking up VEGF-A, VEGF-B, and PlGF. Its larger molecular size gives it a longer vitreous half-life, which is part of why longer dosing intervals are feasible. Bevacizumab is a full-length IgG1 antibody. It is not formulated for intravitreal use, which is why compounding pharmacies prepare it, but the molecule itself is well studied and effective. Faricimab is a bispecific antibody targeting both VEGF-A and Ang-2, addressing two pathways involved in vessel instability rather than one. Here is something many patients miss. These drugs do not cure macular degeneration. They suppress the active disease process. If you stop treatment, the VEGF pathway reactivates and the neovascular membrane typically starts leaking again within weeks. The goal is vision stabilization, and in a meaningful subset of patients, actual visual improvement. About one in three patients on ranibizumab in the MARINA and ANCHOR trials gained fifteen or more letters on the ETDRS chart. Aflibercept data in the VIEW trials showed similar outcomes. The numbers are solid, but they are not miraculous for everyone.
Get the Full Details
Complications and when things go wrong
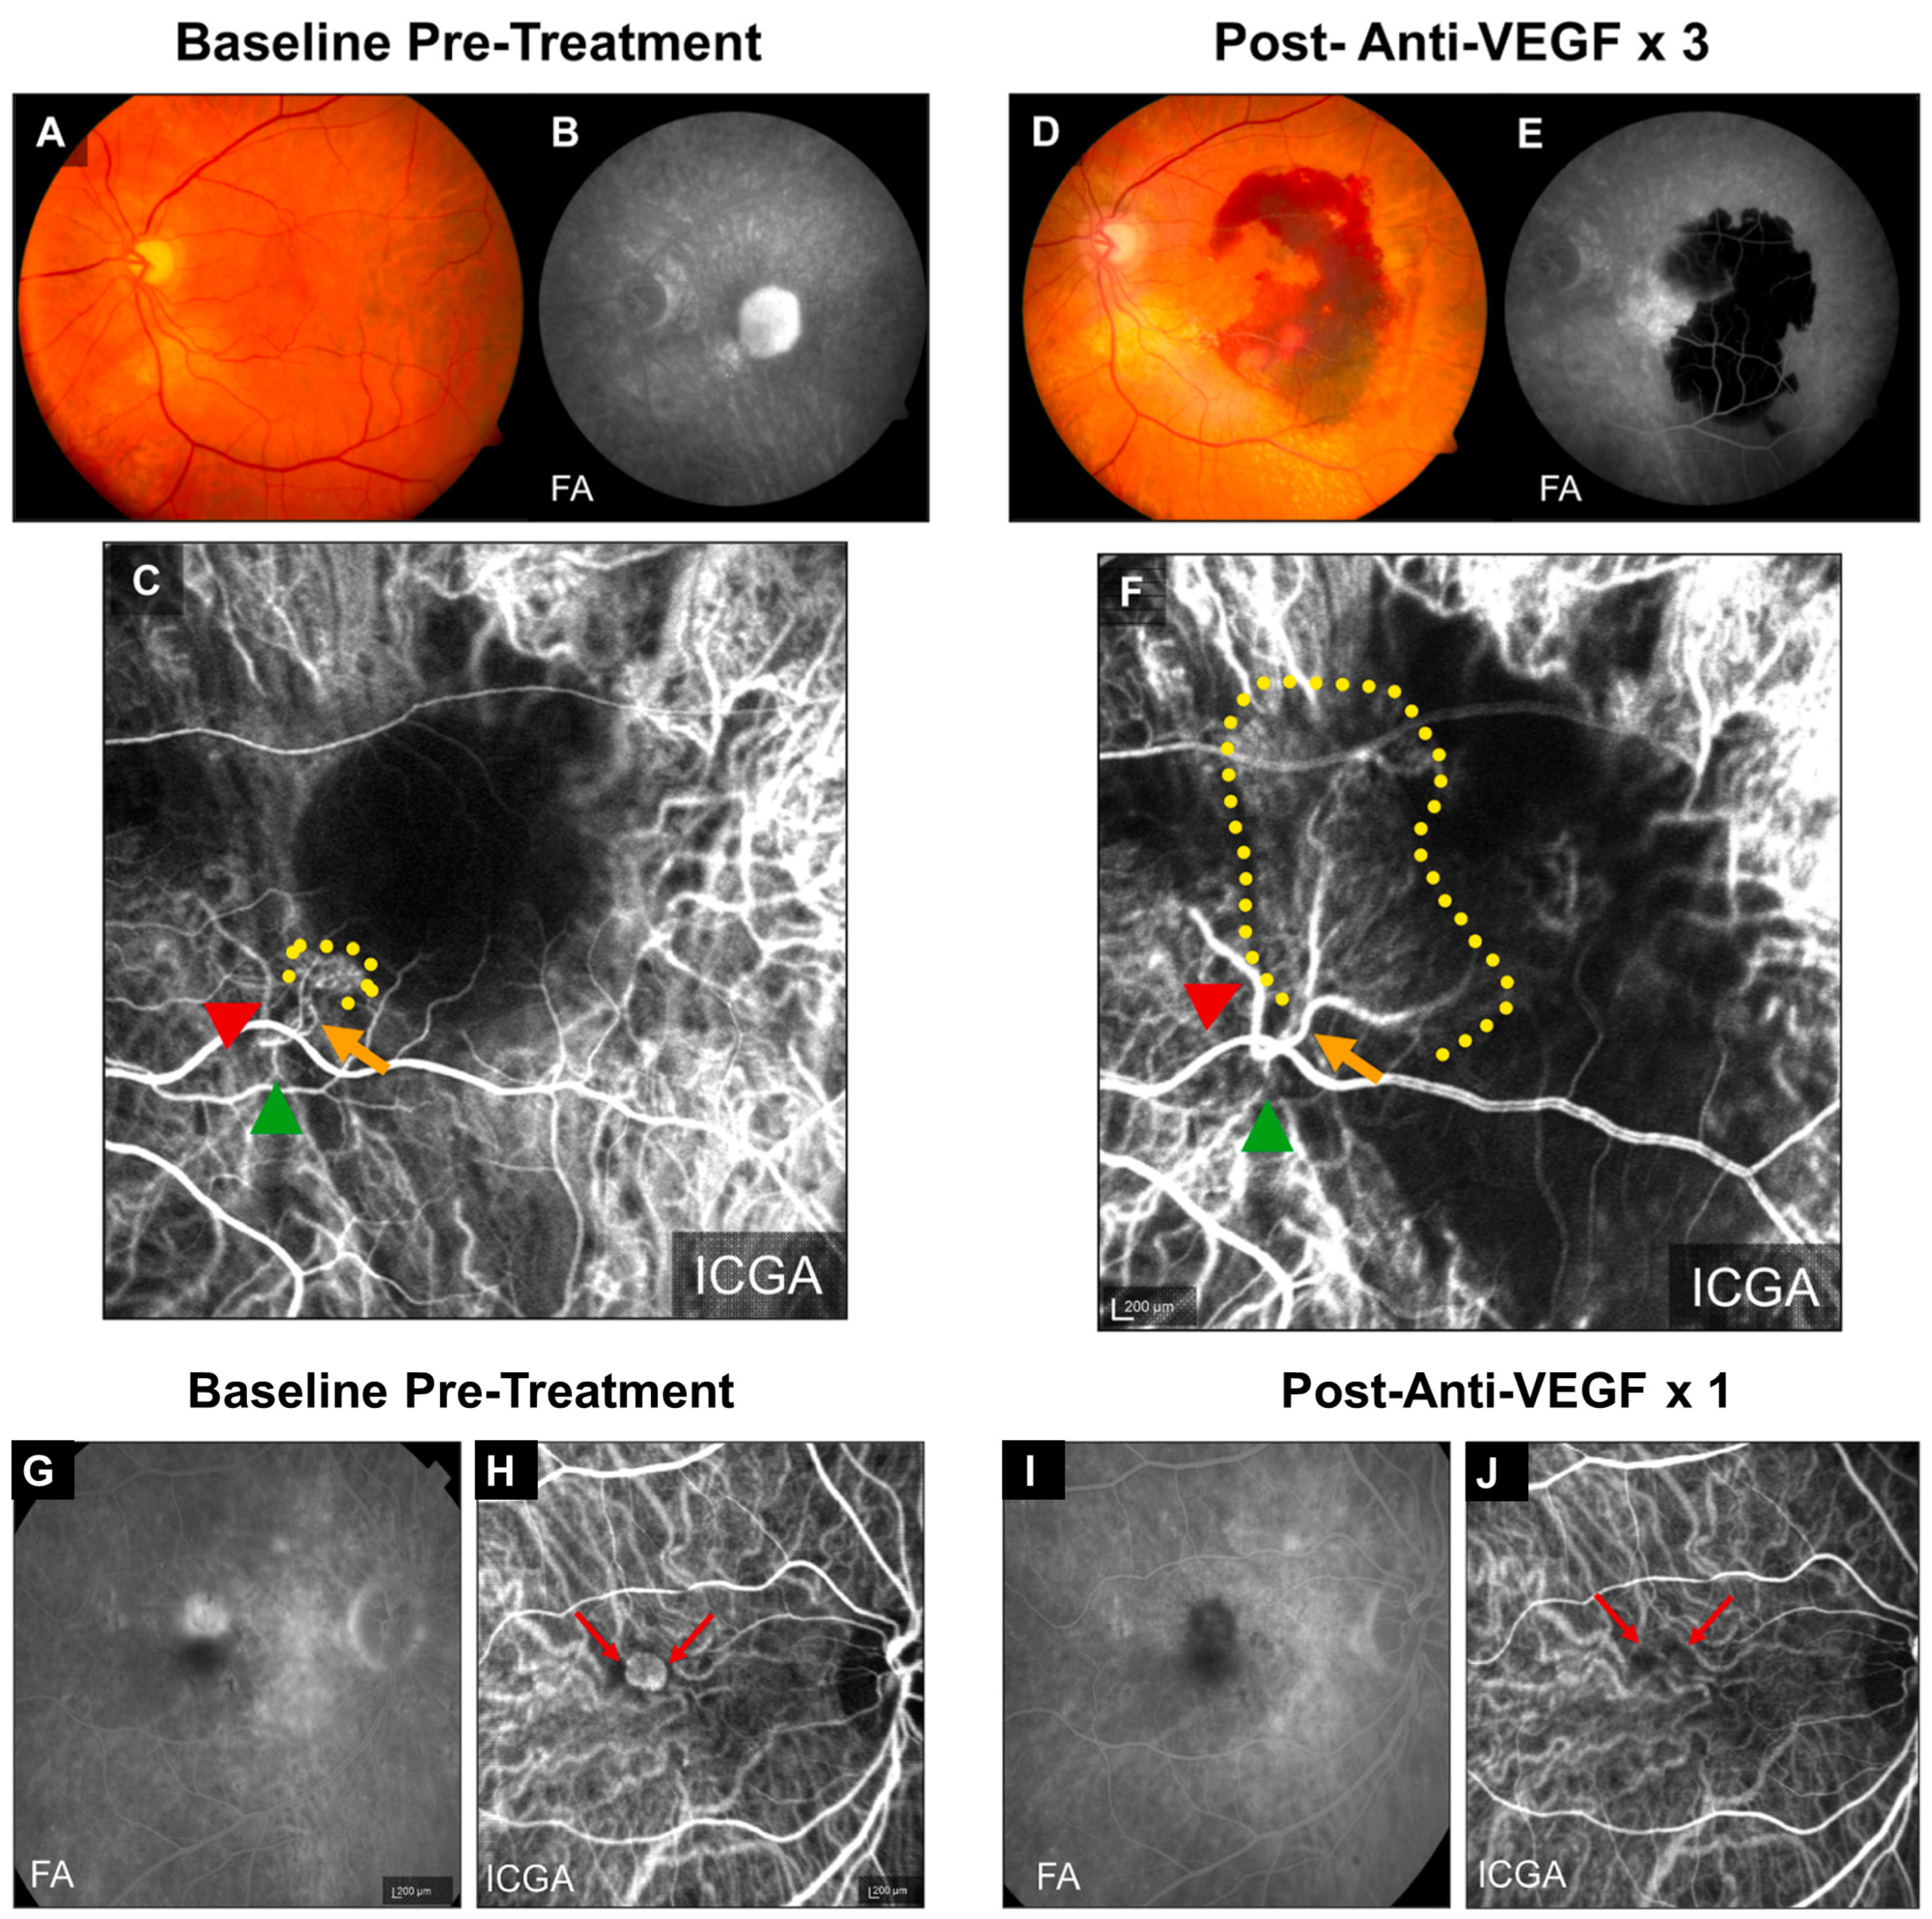
The most common side effect is a temporary increase in intraocular pressure, usually peaking within thirty minutes of injection and resolving on its own. Your doctor will check your pressure before you leave the chair. Subconjunctival hemorrhage is also extremely common and looks worse than it is. A tiny red patch on the white of the eye, nothing to worry about. Intraocular infection, or endophthalmitis, is the feared complication. The risk is approximately one in two thousand to one in three thousand injections. The EVAPORATE and RESTORE studies documented rates in that range. If it happens, it usually presents within three to seven days post-injection with pain, redness, and decreased vision. Immediate vitreous tap and inject antibiotics. Most cases respond to treatment if caught early. This is why I always tell people to have a low threshold for calling the clinic if vision drops suddenly after an injection, even if they think it might just be floaters. One edge case that comes up more than you would expect: patients who develop persistent subretinal fluid despite seemingly adequate VEGF suppression. In my experience, this often points to an underlying polarity issue. The fluid is not posterior enough for standard drainage and not anterior enough to be simple cystoid edema. Checking for polypoidal choroidal vasculopathy with indocyanine green angiography can change the entire management plan. Some of these patients respond better to photodynamic therapy combined with anti-VEGF than to anti-VEGF alone.
There are also patients who respond poorly to one agent but well to another. Switching from ranibizumab to aflibercept, or vice versa, is a routine clinical decision when response is inadequate. Insurance coverage often complicates this, but clinically it makes straightforward sense. The pharmacokinetics and binding profiles are different enough that a poor response to one does not predict a poor response to another.
Practical considerations that are rarely discussed
The treatment burden is real. Monthly or bimonthly visits for years, sometimes indefinitely. Each visit involves dilation, photography, OCT scanning, and the injection itself. For elderly patients with limited mobility or transportation, this adds up quickly. Some clinics offer home nursing for injections now, which helps, but the monitoring visits still require travel. Negative press coverage of brolucizumab in 2020 caused genuine concern. Cases of retinal vasculitis and retinal vascular occlusion were reported at rates higher than expected. The FDA issued a boxed warning. While the absolute risk remains low, most retinal specialists simply avoid this drug unless other options have been exhausted. It is worth knowing this exists if your doctor ever mentions it as a possibility. Cost is another practical issue. A single dose of aflibercept can run several thousand dollars without insurance. Bevacizumab costs roughly forty to sixty dollars per vial, but the out-of-pocket cost advantage depends entirely on your insurance covering the off-label use. Some plans require prior authorization and step therapy, meaning you have to try and fail on one drug before they will approve another. The Clinical Anti-VEGF Negotiation Act has started to address pricing in the United States, but full implementation is still underway and the details matter enormously for individual patients.
If you are considering this treatment, ask your ophthalmologist about the treat-and-extend protocol they use, what their target interval is, and how they decide when to extend versus when to shorten the gap. A clinic that never extends beyond eight weeks is being overly conservative. A clinic that routinely goes past twelve weeks may be risking disease reactivation. The sweet spot varies by patient, but somewhere between six and ten weeks is where most well-managed cases land. The therapy has saved the central vision of millions of people with wet AMD. It is not perfect. It requires commitment, it carries small but real risks, and it does not restore vision that has already been lost. But for the vast majority of patients who start treatment early, the alternative is steady, predictable decline. That is the tradeoff, and it is a reasonable one.