Coding Anticoagulant Therapy Isn't as Straightforward as It Looks
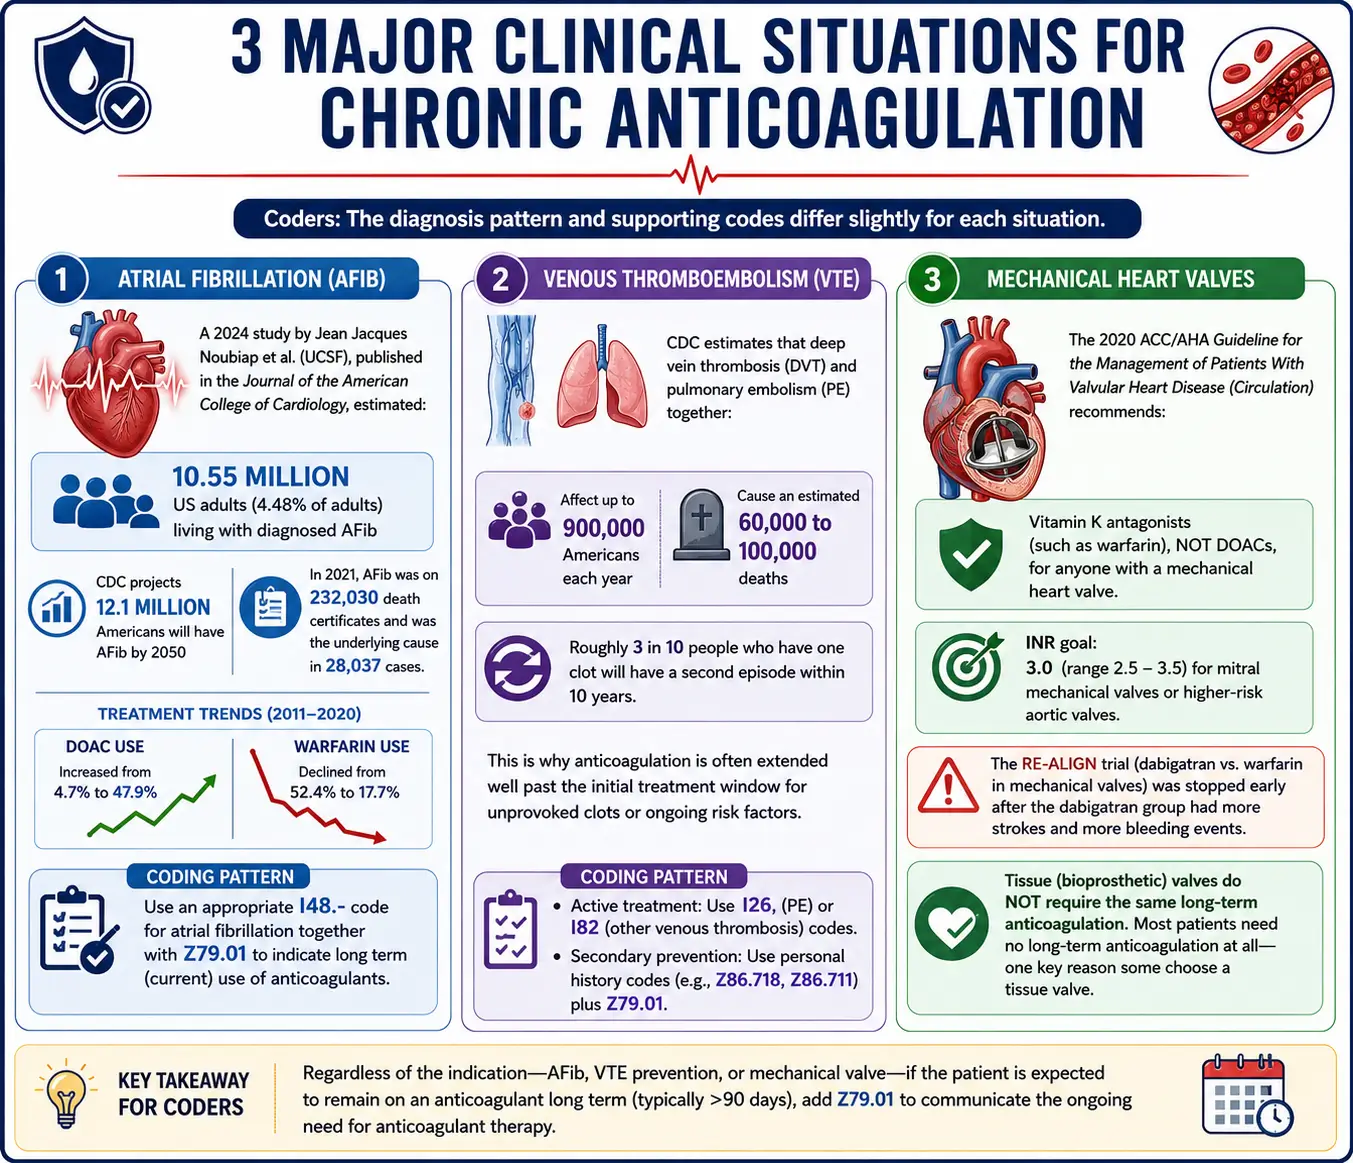
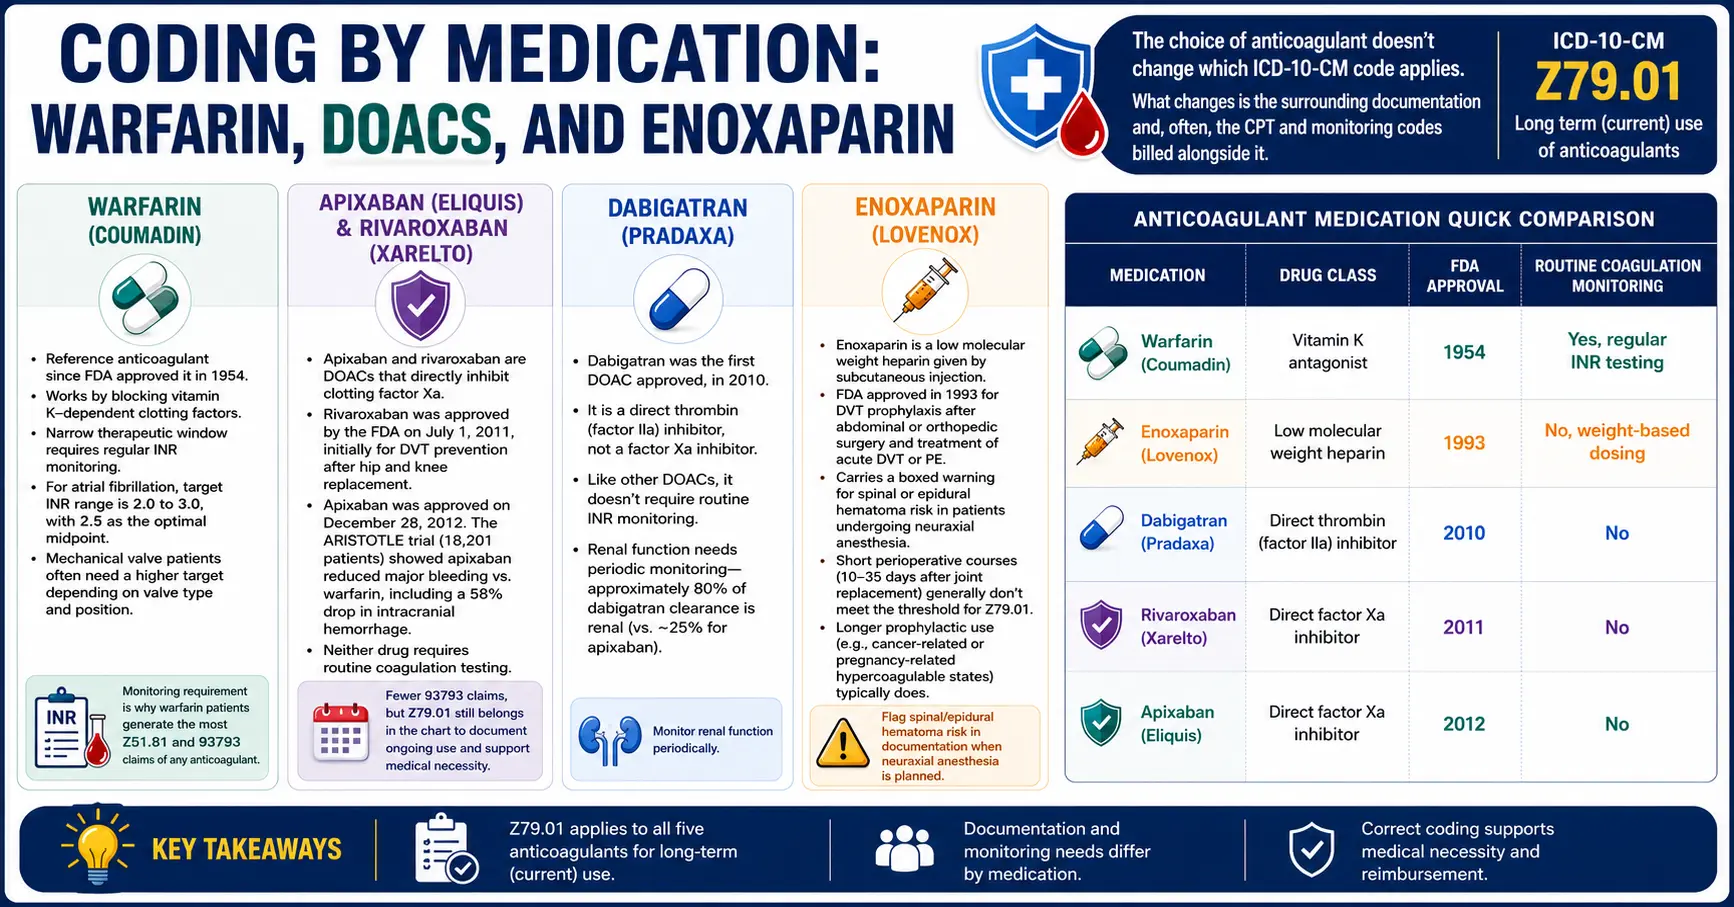
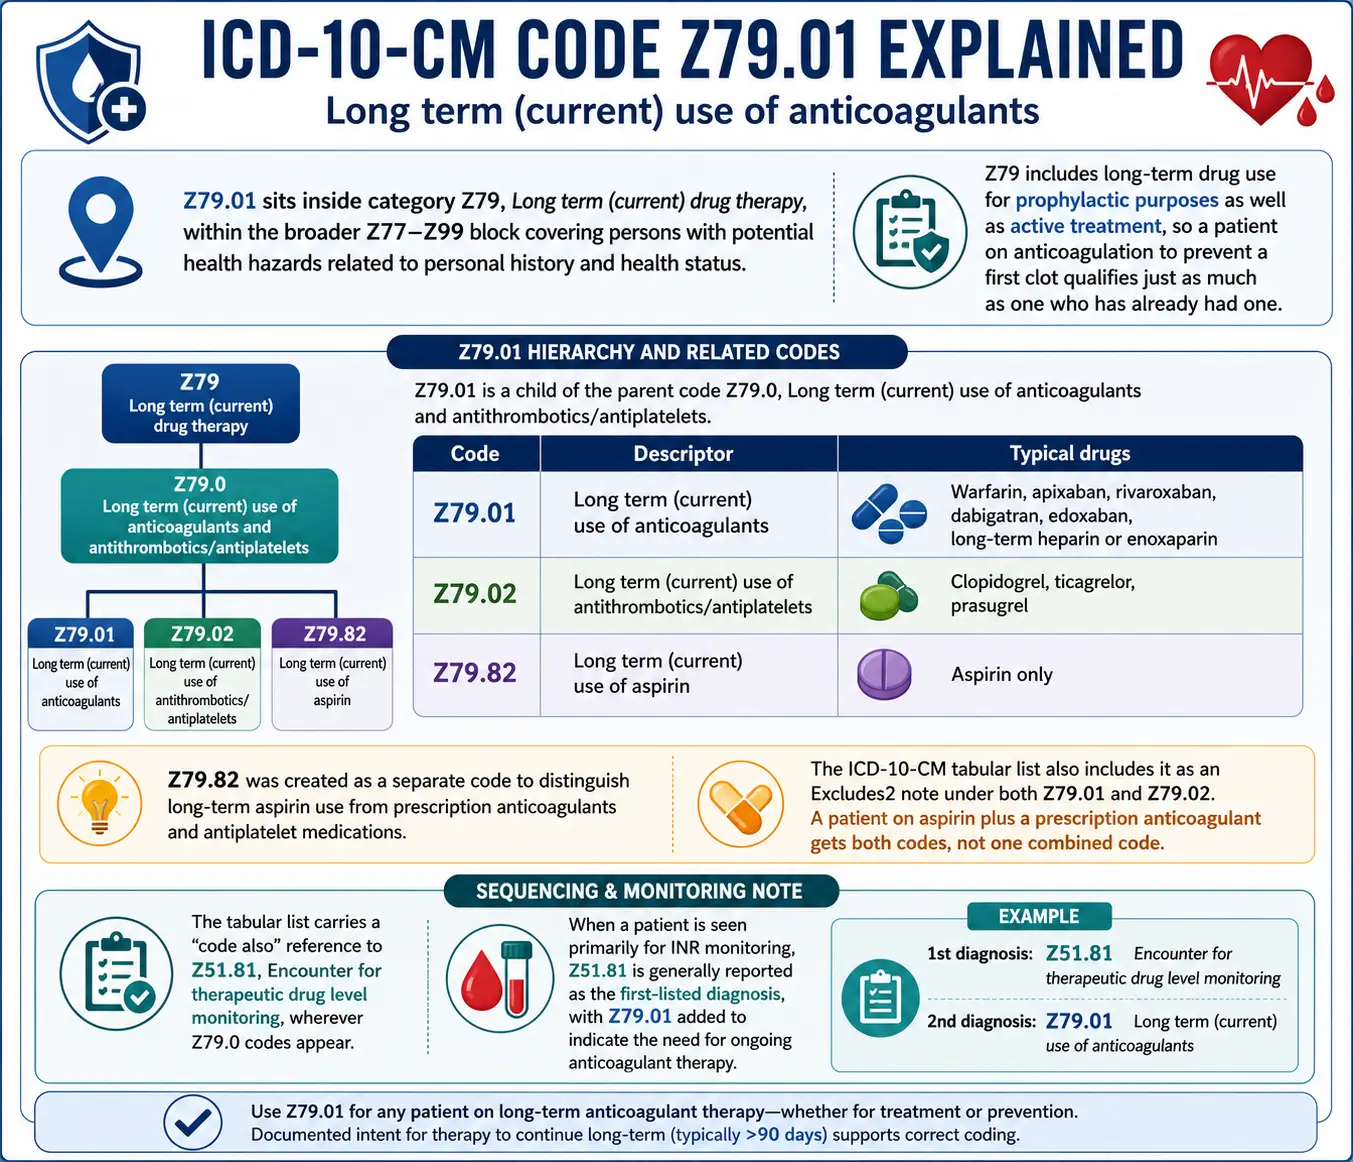
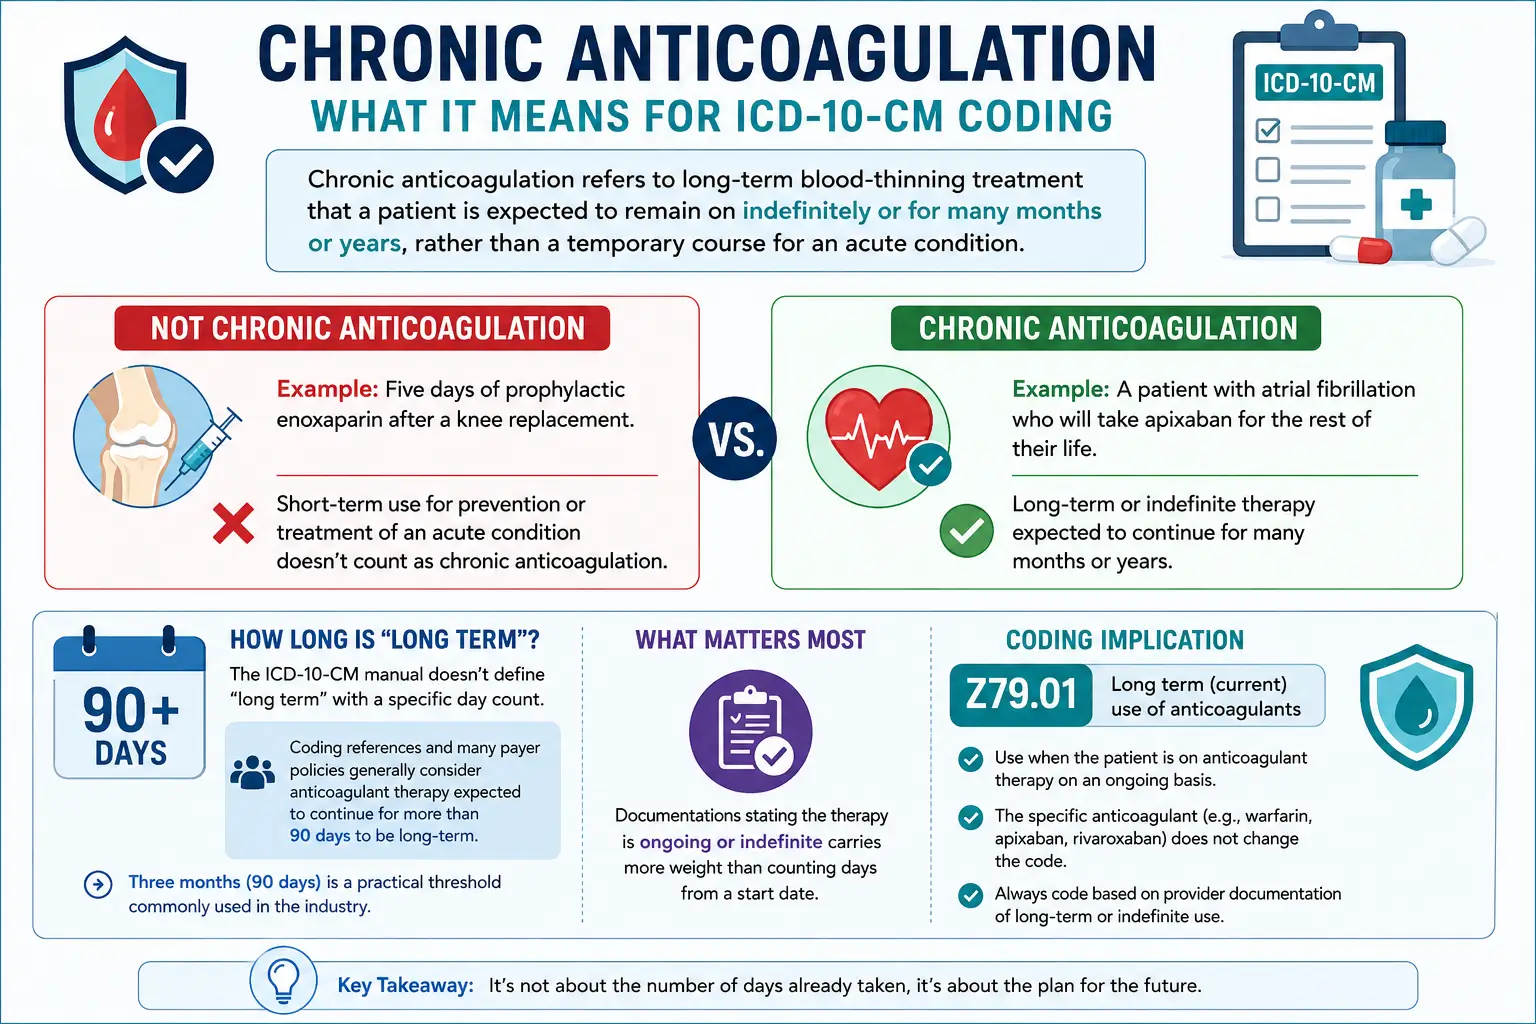
ICD-10 code Z79.01 covers long-term (current) use of anticoagulants. It sounds simple enough, but coders regularly mess this up. You need to understand exactly when it applies and, more importantly, when it does not. Z79.01 is a Z-code, which means it lives in Chapter 21 (Factors Influencing Health Status and Contact with Health Services). These codes are supplemental. They describe a status or a risk factor, not a disease or acute condition. That matters because payers treat Z79.01 differently than primary diagnosis codes. The code applies when a patient is actively taking an anticoagulant on a long-term basis. This includes warfarin, apixaban, rivaroxaban, dabigatran, edoxaban, heparin infusions, and similar agents. The key word is long-term. The code does not apply to short-term therapeutic anticoagulation during an acute hospitalization for something else, like a post-surgical DVT that gets treated with heparin during the admission and then stopped before discharge.
I ran into a case recently where a patient came in for a knee replacement and had a history of atrial fibrillation. She was on apixaban at home. The surgeon held the apixaban for five days before the procedure and restarted it post-op. The outpatient follow-up visit coded Z79.01 alongside the primary diagnosis. I pushed back on that because the anticoagulant was intentionally interrupted for surgery. The correct approach was to code the reason for the procedure and the post-procedure status, not the long-term anticoagulant use. Z79.01 only applies when the anticoagulant is being taken continuously as part of ongoing management, not when it is deliberately paused for an intervention.
How to Code It Correctly
First, check the medical record for documentation that the patient is currently taking an anticoagulant. "Current use of anticoagulants" needs to be explicitly stated or clearly implied by the medication list and the treatment plan. If the provider writes "continue apixaban 5 mg BID," that qualifies. If the note just lists the medication without indicating ongoing use, you need to clarify. Second, make sure the condition being treated is also coded. Z79.01 is never a primary code. It always accompanies the underlying indication: atrial fibrillation (I48), mechanical heart valve (Z95.2), deep vein thrombosis (I82.4-, I26), or pulmonary embolism. The anticoagulant code sits alongside these, not instead of them. Third, distinguish between therapeutic and prophylactic dosing. Z79.01 covers both. A patient on prophylactic LMWH for VTE prevention after bariatric surgery still qualifies if the use is ongoing and long-term. Short-term inpatient prophylaxis does not qualify. The boundary between short-term and long-term is where most disputes happen.
Get the Full Details
I once worked with a coder who put Z79.01 on a chart for a patient admitted with sepsis who received a single dose of prophylactic enoxaparin in the ED before being transferred to the ICU. That was incorrect. The anticoagulant was a one-time dose, not long-term therapy. I removed the code and added a note explaining that Z79.01 requires documented ongoing use, not incidental administration. The auditor agreed with the change during the subsequent review.
Common Pitfalls and Edge Cases
One issue that trips people up involves reversal agents. If a patient on warfarin comes in with an elevated INR and receives vitamin K or PCC, Z79.01 is still appropriate if the intent is to continue warfarin after the reversal. But if the provider documents discontinuation of warfarin permanently, Z79.01 should not be used. The code reflects current use, not past use. Another frequent error: using Z79.01 when the patient is on antiplatelet therapy instead. Z79.02 covers long-term use of antiplatelets. Clopidogrel, aspirin, and ticagrelor fall under Z79.02, not Z79.01. These are different drug classes with different clinical implications, and mixing them up can trigger payer audits. There is also a problem with inpatient vs. outpatient coding. In the inpatient setting, Z-codes are generally not reported as principal diagnoses. They can appear as secondary diagnoses if they affect care, but some payers will deny claims that rely too heavily on Z-codes for reimbursement. Outpatient settings are more flexible with Z-codes, but you still need to follow the specific payer's guidelines. I have seen denial rates spike by nearly 18% when facilities started using Z79.01 liberally on inpatient claims without linking it to a qualifying underlying condition.
What Z79.01 Does Not Cover
The code does not cover patients who have a history of anticoagulant use but are no longer on it. For that, use Z79.899 or the appropriate personal history code depending on the context. It does not cover acute overdose or adverse effects of anticoagulants. If a patient presents with a bleeding complication from warfarin, you code the adverse effect (T40.6X5A for warfarin-induced hemorrhage) alongside the appropriate current or past use code, not Z79.01 alone. It also does not apply to patients receiving anticoagulation only during a dialysis session or in a procedural suite for a single event. The biggest limitation of Z79.01 is that it carries no DRG weight in inpatient settings. Some hospitals try to leverage it to justify extended length of stay or additional monitoring, but it will not move the severity metric. If your facility is counting on Z79.01 for revenue purposes, you are barking up the wrong tree. It is a clinical documentation code, not a financial one.
Practical Takeaway
Verify the documentation. Ensure the patient is actively on an anticoagulant for a legitimate ongoing reason. Pair it with the correct underlying diagnosis. Avoid using it for single-dose or periprocedural anticoagulation. And never substitute it for the condition being treated. When in doubt, ask the provider to clarify the intent and duration of the anticoagulant therapy. That single question saves more rework than anything else in this space.